Getting a Grip on Anterior and Posterior Muscle Maps
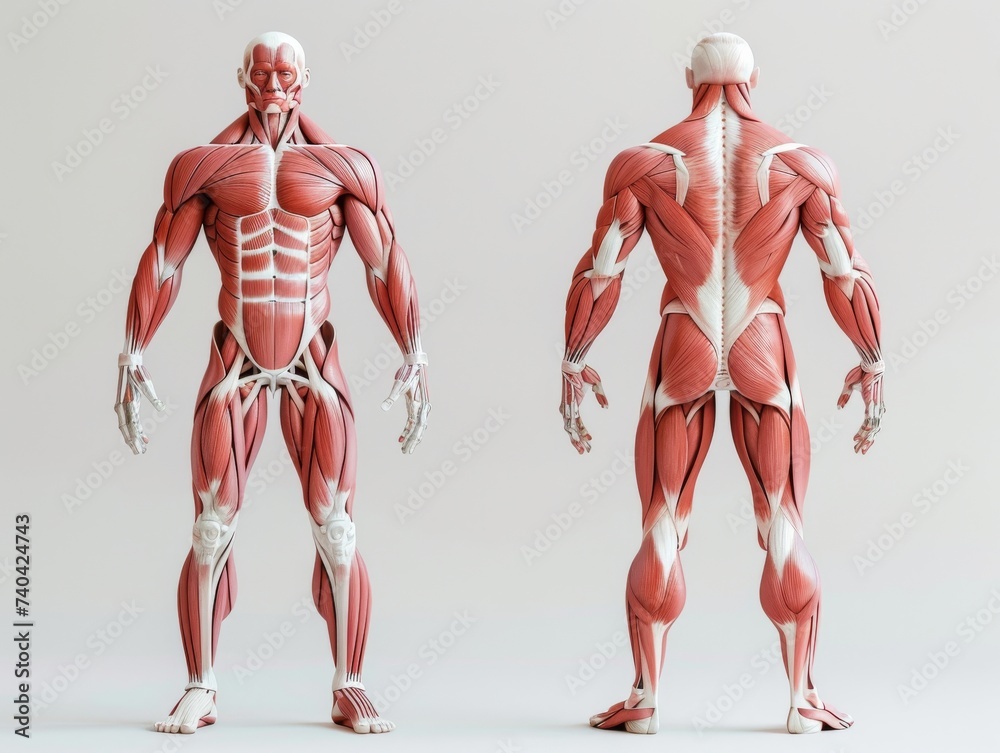
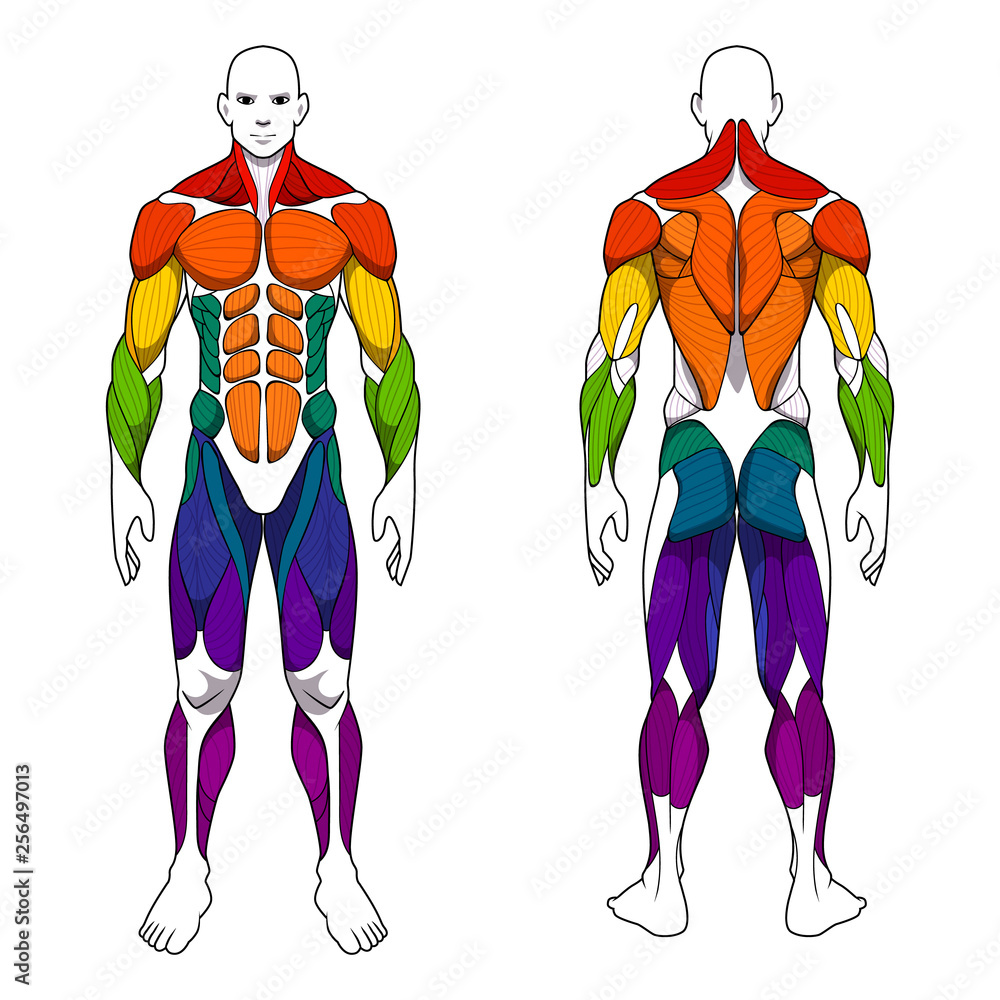
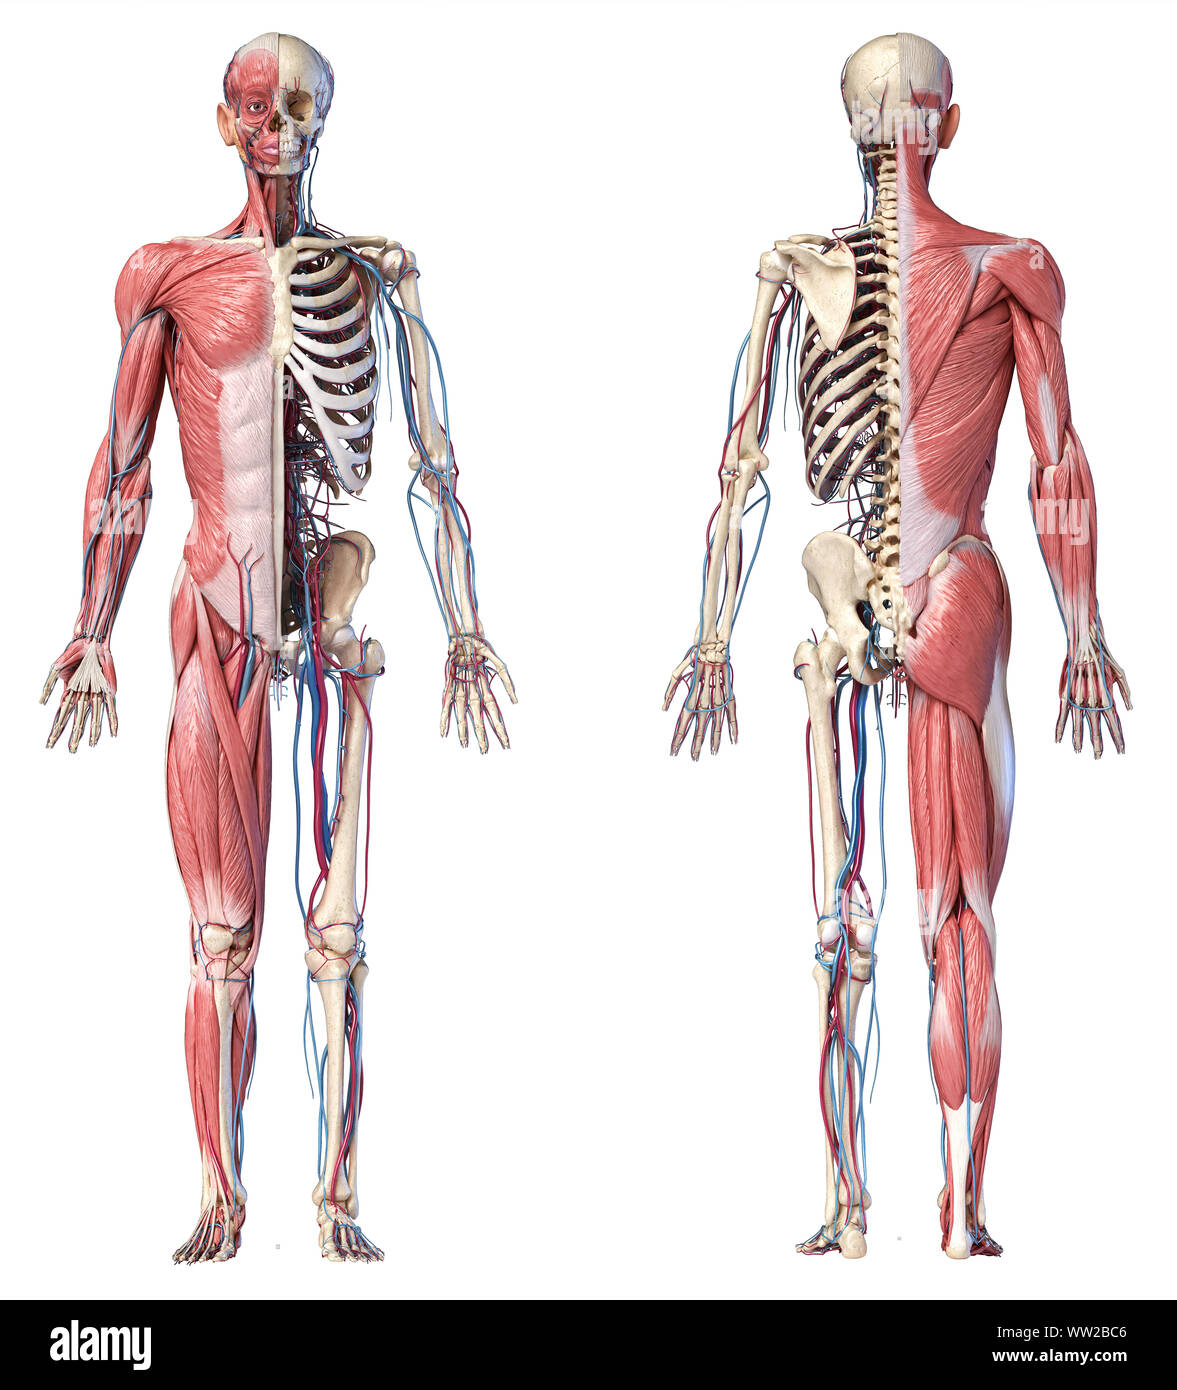
Most people who need a reliable Muscular System Front And Back reference end up drowning in a sea of poorly labeled diagrams from stock image sites. You know the ones. The labels overlap, the muscles are either missing or exaggerated, and nobody bothered to indicate which layer they are showing. I spent a couple of years dealing with this while putting together training materials for a physical therapy clinic. It was tedious work. I started with the Netter plates because they are clean, but they are static and not always layered properly. Then I switched to using a combination of Visible Body's anatomy atlas as a base and cross-referencing with the Gray's Anatomy illustrations for anything involving deeper structures like the rotator cuff or the gluteal compartment. The workflow is straightforward once you figure out which source handles which region best.Muscular System Front And Back
Here is the practical breakdown. When you are looking at the anterior view, the surface muscles are fairly predictable. You have the sternocleidomastoid running from the mastoid process to the clavicle and sternum. The pectoralis major covers the upper chest with its clavicular and sternal heads. Below that sits the rectus abdominis, and on the sides you have the external and internal obliques. The quadriceps femoris makes up most of the anterior thigh, with the rectus femoris sitting in the middle and the vastus lateralis and medialis flanking it. You cannot forget the sartorius, that long strap-like muscle that crosses diagonally from the ASIS down toward the medial knee. The posterior view is more complex because there are more overlapping layers. The trapezius dominates the upper back, but if you are studying someone for shoulder rehabilitation, you need to see the rhomboids underneath it. The latissimus dorsi fans out from the lower spine and inserts on the humerus. In the arm, the triceps brachi has three heads. The long head originates from the infraglenoid tubercle of the scapula, which matters if you are dealing with overhead athletes. For the lower back and hips, the erector spinae runs vertically along the entire spinal column. The gluteus maximus is the most superficial hip extensor, but the gluteus medius and minimus sit underneath it and are critical for pelvic stability. In the posterior thigh, the hamstrings consist of the biceps femoris, semitendinosus, and semimembranosus. The biceps femoris has a long head from the ischial tuberosity and a short head from the linea aspera of the femur. Beginners often miss that distinction, and it changes how you approach hamstring strain rehab.I ran into a specific problem with a client who had chronic anterior knee pain. The standard quad stretch routine was making it worse because I had been focusing only on the rectus femoris. The actual issue was tightness in the vastus intermedius, which is deep to the rectus and not visible on surface anatomy charts. Once I adjusted the approach to include deep tissue work on that layer along with hip flexor release, the pain dropped significantly within three weeks. Surface-level diagrams do not tell you that story.
The calves follow a similar pattern of hidden complexity. The gastrocnemius is the two-headed muscle you see from behind, but the soleus lies directly beneath it and is actually the bigger contributor to plantar flexion strength. If you are only stretching the gastrocnemius, you are missing half the picture. For anyone building their own reference materials or trying to study from downloaded charts, here is a method that actually works. Print or display the anterior and posterior views side by side. Trace the muscle bellies and tendons on a tablet using a lightweight app like Complete Anatomy or even just a basic drawing tool. The act of tracing forces you to notice where one muscle ends and another begins. It takes longer upfront but the retention is significantly better than passive viewing. One thing most guides skip over: the fascia. When you look at a muscular system diagram, the deep fascia is usually invisible or omitted entirely. But in practice, the fascia lata around the thigh and the thoracolumbar fascia in the lower back are major contributors to force transmission. Ignoring them leads to incomplete movement assessments. I learned this the hard way after watching a physiotherapist miss a key restriction in a patient's lumbar region because she was only palpating the erector spinae muscles and not the fascial connections. If you are looking for download sources, the Open Anatomy project provides some freely available layered models. They are not perfect but they are a solid starting point. For more detailed commercial versions, Complete Anatomy and Human Anatomy Atlas are reliable, though they cost money. Free Wikipedia commons images can work for basic study but the labeling accuracy is inconsistent across different versions. A word of caution about these resources. Many free anatomical charts conflate the brachialis and the deep portion of the biceps brachii. They also routinely mislabel the coracobrachialis as part of the biceps rather than its own distinct muscle. If you are using these for clinical reference, always verify against a textbook. The diagrams are useful for orientation but not accurate enough to rely on without cross-checking. The anterior compartment of the leg deserves special mention because it is frequently misunderstood. The tibialis anterior, extensor digitorum longus, and extensor hallucis longus all originate from the tibia and fibula. People often think the anterior shin muscle is just the tibialis anterior, but the other two extensors are right there and they serve different toe movements. Understanding this distinction matters if you are dealing with foot drop or ankle instability. For the back of the arm, the anconeus is a small triangular muscle that attaches to the olecranon. It gets left out of most simplified diagrams but it assists in elbow extension and stabilizes the joint during loading. Skipping it is fine for introductory study. It becomes relevant if you are dealing with elbow hyperextension issues or post-surgical rehab. The most important takeaway is that front and back views are just the beginning. Real anatomical knowledge requires understanding how these muscles interact across joints. A muscle like the iliacus is visible in anterior dissections but irrelevant to someone only looking at surface anatomy. Similarly, the multifidus in the posterior spine is too deep to show on most external reference charts but is critical for spinal segmental control. Most resources will give you a list of muscles and their attachments. Very few will explain why certain muscle relationships matter in a practical setting. That is where the real value lies, and it is something you pick up through hands-on study rather than downloading another chart.