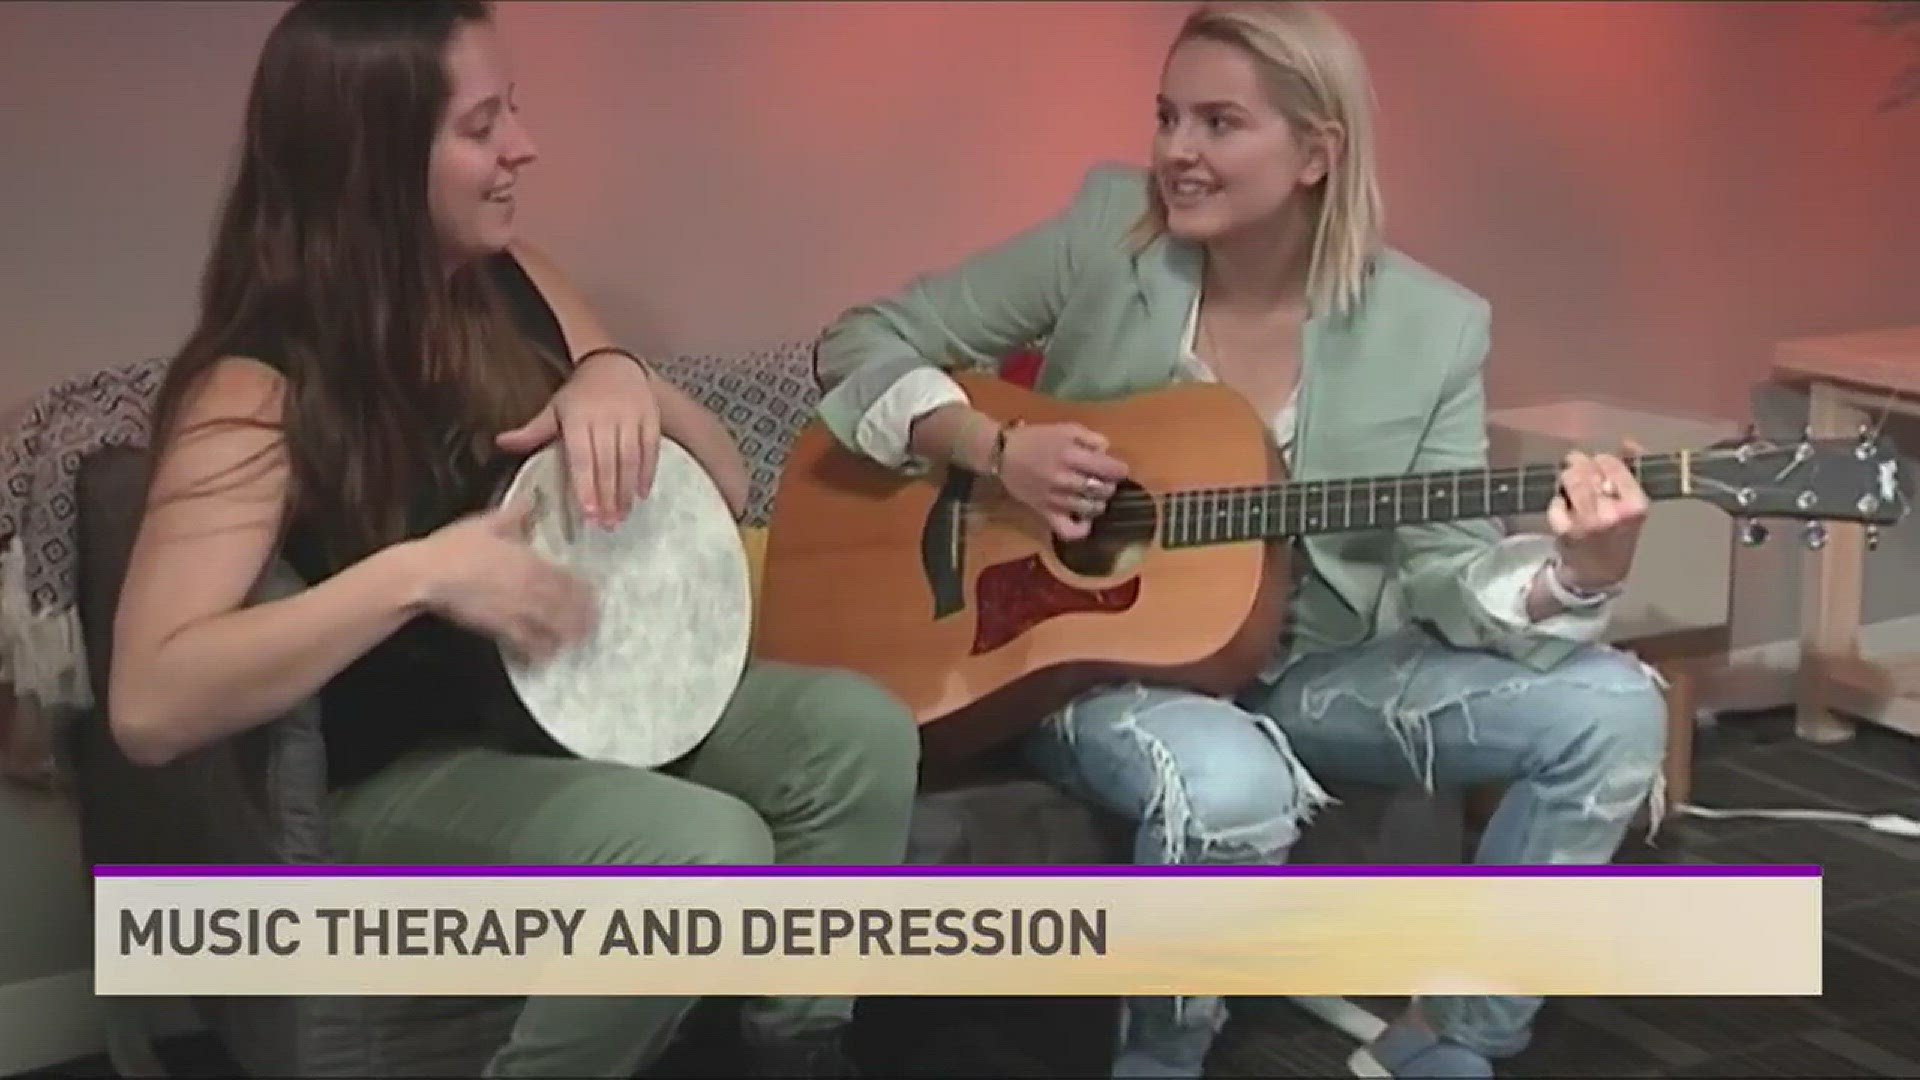The Unpopular Truth About Getting Teens to Actually Engage With Music Therapy
Most parents and even some clinicians approach music therapy for teens with a fundamental misunderstanding. They think the kid just needs to listen to calming playlists and everything will sort itself out. That is not how it works, and it rarely does. I have sat across from enough seventeen-year-olds who told me straight up that their therapist was trying too hard before I started adjusting my approach entirely. The ones who actually get something out of it are the ones where the music feels like theirs, not something prescribed by an adult with good intentions. Let me explain what the actual mechanism looks like in practice before we get into the procedural stuff. Music therapy for teens operates on something called iso-principle pacing, which is just a clinical way of saying you match the music to the teen's current emotional state first, then gradually shift it toward the state you want them to reach. You do not start a depressed or agitated teenager with something upbeat and calming. It reads as dismissive to them. You start with music that matches their energy, even if that means starting with something heavy or sad, and you move from there over multiple sessions. This is counter-intuitive to most people entering the field because the instinct is always to fix the mood immediately. Fixing it immediately does not work. Meeting them where they are does.
How to actually set up Music Therapy For Teens in a home or clinical setting
Here is the practical part. You need a structured but flexible framework. I usually start with a basic session structure that looks like this: five minutes of check-in using music as a prompt, twenty minutes of active music-making or guided listening with a specific therapeutic goal, and ten minutes of reflection or processing. The active portion is where most people go wrong. They let the session become unstructured jam time and wonder why progress stalls. Active music-making with teens needs a clear intention even if it does not feel rigid. Maybe the intention is emotional regulation through rhythm matching. Maybe it is building social connection through collaborative songwriting. Maybe it is processing grief through lyric analysis. Whatever the intention, it needs to be visible to both the therapist and the teen. The tools you need are fairly simple. A decent MIDI keyboard or even a good tablet with a quality app like GarageBand or BandLab. A few percussion instruments. A Spotify or Apple Music account with pre-made playlists you have thoughtfully curated. Recording equipment, even a simple phone, so you can capture sessions and revisit them. And most importantly, a library of popular songs spanning multiple genres that your teen actually recognizes. If you are doing this in a clinical setting, having a collection of lyric sheets and instrumental tracks is essential because karaoke-style sing-alongs and lyric discussion are some of the most effective interventions available for this age group. I ran into a specific problem last year with a fifteen-year-old male client who was completely resistant to any form of music engagement. He would sit in silence, refuse to play any instrument, and shut down during any musical activity. Standard approaches were not working. What I ended up doing was bringing in a software called Sonic Pi, which is a code-based music creation tool. He had been into programming on his own time. I framed it as just experimenting with code that made sound, nothing therapy-related. Within three sessions he was creating his own compositions and slowly opening up about what was going on for him. The workaround was recognizing that the barrier was not music itself but the frame around music. Once I removed the clinical framing and presented it as something aligned with his existing interests, everything changed. You have to be willing to abandon your standard toolkit when it clearly is not working.
What most people miss about the process
The biggest mistake I see is treating music therapy as a replacement for talk therapy rather than a parallel modality. It is not interchangeable. Some teens who cannot articulate their feelings in words can express them through music just fine. Others need the music as a bridge to eventually engage in traditional verbal processing. Knowing which trajectory your client is on takes observation over time. You watch how they respond to different types of musical interventions. Do they gravitate toward creating or consuming? Do they engage more with rhythm or melody? These preferences tell you a lot about their processing style and what kind of therapeutic approach will land. Another thing that trips people up is the expectation of measurable outcomes too quickly. Music therapy with adolescents does not produce dramatic visible shifts in a single session or even a handful of sessions. The gains are often subtle and cumulative. A teen who was completely nonverbal in session one might hum along in session three. That is progress, even if it does not look like much to an outside observer. Documenting these small shifts is important because without documentation it is easy to doubt whether the approach is working at all. I usually track simple behavioral markers: engagement level, duration of participation, voluntary sharing, and emotional regulation between sessions. These are easier to measure than you might think if you actually commit to recording them consistently. There are also legitimate limitations you need to be honest about. Music therapy is not appropriate for every teen presenting with mental health concerns. Acute psychotic episodes, severe mania, or situations where music triggers traumatic associations can make structured music therapy contraindicated or at least problematic without significant modifications. I had a case where a teenage girl had experienced sexual assault in a car while a specific song was playing on the radio. That song became a trauma trigger and any attempt to use music therapeutically had to be paused until we addressed the trauma through a different modality first. Music is powerful and it is not always the right tool for every situation. Sometimes talk therapy, EMDR, or other evidence-based approaches are simply more appropriate and using music in those cases can be retraumatizing.
Get the Full Details

If you are looking for resources to get started, the Association for Music Therapy International publishes a directory of certified practitioners at amta.org, which is useful if you are a parent trying to find qualified help rather than attempting this alone. For self-guided approaches, there are downloadable lyric analysis worksheets and mood-tracking templates available through various clinical resource sites, though I would caution against treating online materials as a substitute for professional guidance. The dynamics involved in working with teenagers are complex enough that attempting to run a music therapy program without proper training can easily do more harm than good, especially if you miss warning signs or misinterpret behavioral cues. The reality is that doing this well requires patience, genuine interest in the teen's musical world, and a willingness to adapt constantly. The kids who benefit most are not the ones who get handed a structured program and told to follow it. They are the ones who feel like the music has space for their actual experience. That space does not happen by accident. It happens because someone took the time to learn what the teenager actually listens to, what they respond to, and what kind of musical engagement makes them feel seen rather than manipulated. Most people skip that part and wonder why it does not work.