What We're Actually Talking About
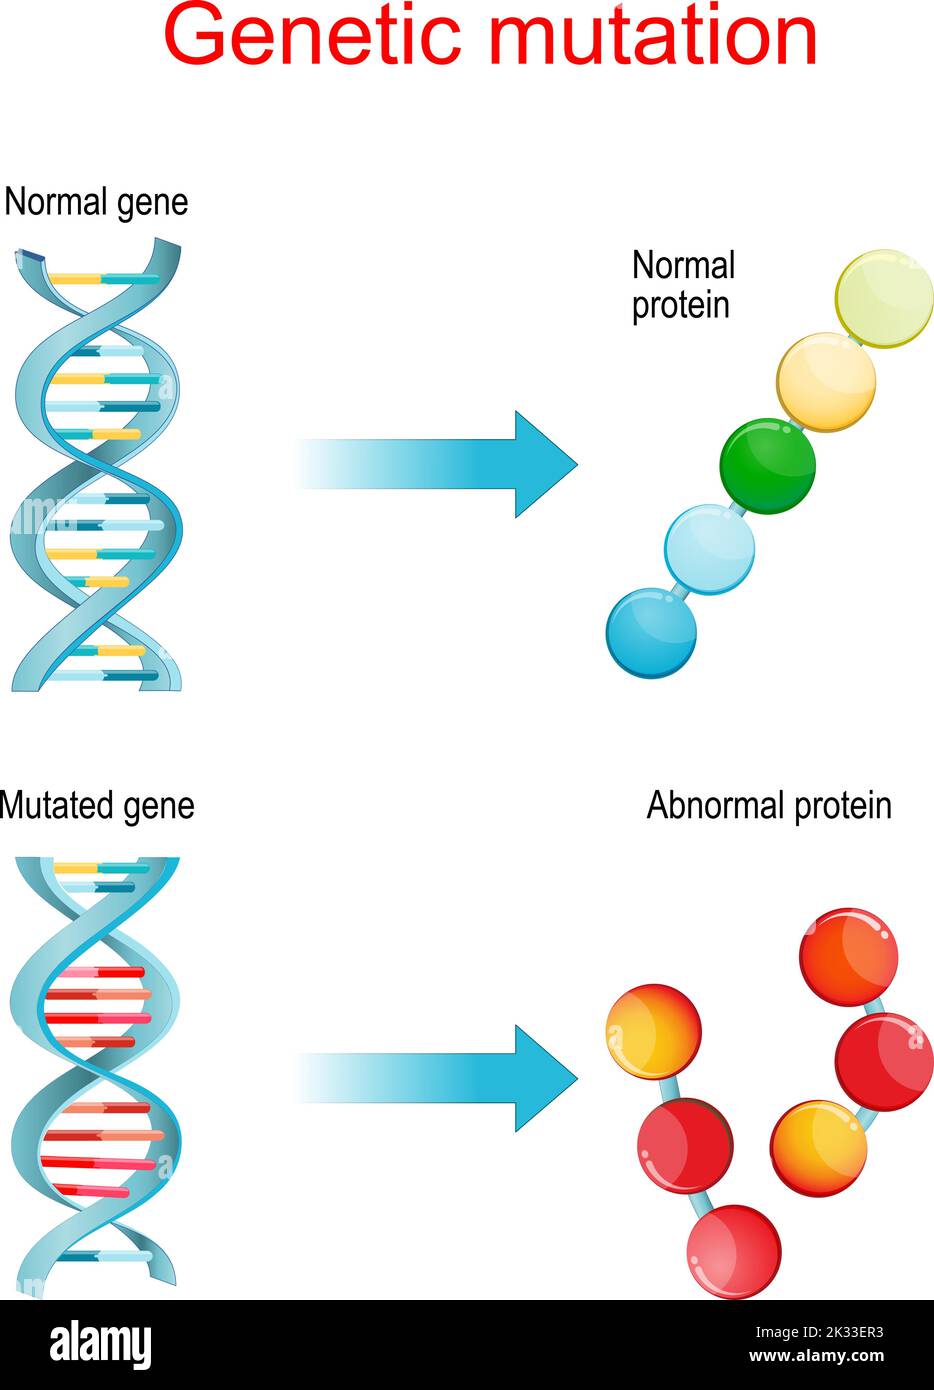
A mutation is just a change in the DNA sequence. That's it. It sounds too simple because most people are overthinking it from the start. I spent years debugging variant calling pipelines before I stopped treating every edge case like it was novel. The Mutation Definition Biology question comes up constantly because the way you define a mutation depends entirely on what you're trying to do with it. A somatic cell line mutation means something different than a germline variant in a clinical report, even when they're the exact same base change.
Mutation Definition Biology in Practice
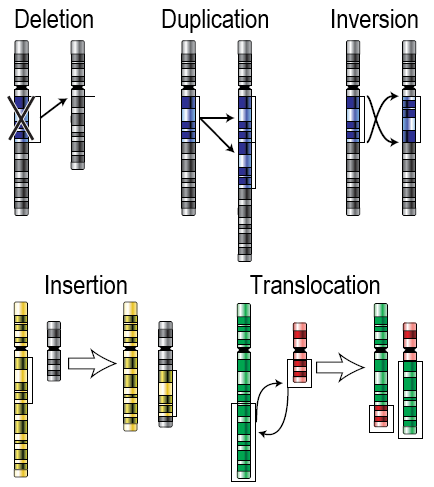
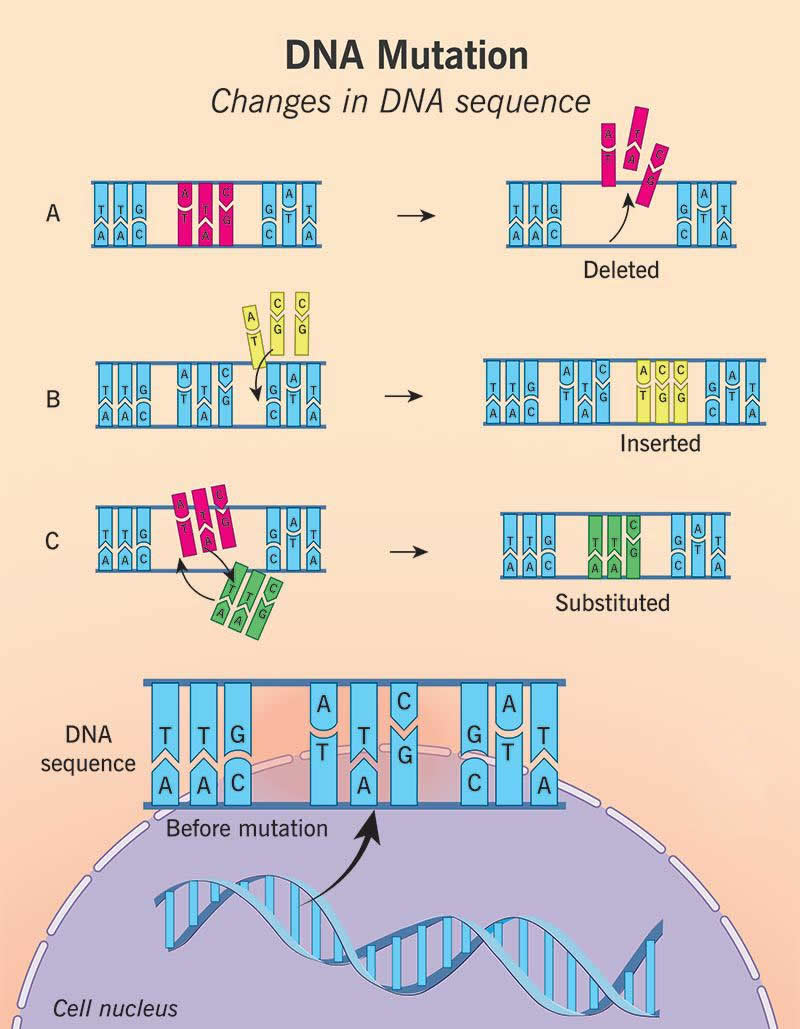
When I'm looking at sequencing data, the first thing I check is how the variant called itself. The definition isn't just "a changed nucleotide." It includes the context: is it a single nucleotide substitution, an insertion, a deletion, a frameshift, a copy number variation? How it's classified determines whether it matters to you. Here's what most people miss. A silent mutation can absolutely be functionally significant. The definition changes depending on whether you're asking about the DNA level or the protein level. I had a case last year where a "synonymous" variant in BRCA1 was actually causing abnormal splicing. The variant caller labeled it VUS (variant of uncertain significance) because it looked harmless at the coding level. We caught it by checking RNA data, not just DNA. The workaround I use now for these edge cases is to run splicing prediction algorithms alongside standard variant annotation. Tools like SpliceAI or MaxEntScan catch what the basic pipeline misses. It adds maybe ten minutes to a run, but it saves days of follow-up confusion.
How Mutations Get Defined Across Contexts
Different fields use different thresholds. Cancer researchers often call anything above a 1% variant allele frequency in a tumor sample a mutation. Clinical geneticists usually require segregation data, population frequency checks, and functional evidence before calling something pathogenic. Population geneticists treat any difference from a reference genome as a variant and only later classify its significance. The terminology overlaps but it's not interchangeable. A polymorphism is a variant seen in more than 1% of a population. A mutation is any change, regardless of frequency. The ACMG guidelines have formal criteria for pathogenicity classifications, but those guidelines were written for clinical diagnostics, not for research screening. I've seen people apply clinical criteria to research data and end up classifying way too many variants as benign simply because the thresholds weren't designed for that use case. It's not a small error either. It skews downstream analysis and makes comparisons across studies nearly impossible.
Get the Full Details
The Technical Side Without the Fluff
Calling a mutation involves alignment, variant detection, and filtering. The hard part isn't the alignment anymore, that's solved. The hard part is distinguishing real variants from sequencing artifacts, especially in low-coverage regions or homopolymer runs. I've run Illumina and Nanopore data side by side on the same sample. The conflict rate in repetitive regions was high enough that I stopped trusting either platform alone for indel calling. For SNPs, Illumina is fine. For structural variants, Nanopore gives you long reads that actually span the problem region. The tradeoff is error rate. You end up needing higher coverage, which means higher cost and longer compute time. There's no free lunch here. One thing nobody warns you about is reference genome bias. If your sample comes from a population poorly represented in the reference assembly, you'll flag common population-specific variants as mutations. This shows up most often in non-European cohorts. Using a graph-based reference instead of a linear one reduces false positives, but it's still not widely adopted in routine pipelines.
When Definitions Break Down
Somatic mosaicism is where the standard definition gets messy. A mutation present in only a fraction of cells won't show up clearly in blood-derived sequencing. I once spent three weeks chasing a variant that appeared in a tissue biopsy but was completely absent from the matched blood sample. The initial call was discarded as contamination until we realized the variant was real, just confined to a specific tissue lineage. Chimerism, technical artifacts, and contamination all look like mutations until you've checked the right controls. Always use a matched normal sample when possible. If you can't, at minimum run decoy-aware alignment and check for known artifact sites in your lab's platform-specific panels. There's no clean definition that covers all cases because biology doesn't fit neatly into categories. The closest you get is specifying your criteria upfront: what you're sequencing, what threshold you're using, and what evidence you're willing to accept as confirmation. Everything else is guessing.