Working with Myasthenia Gravis Functional Assessment Tools
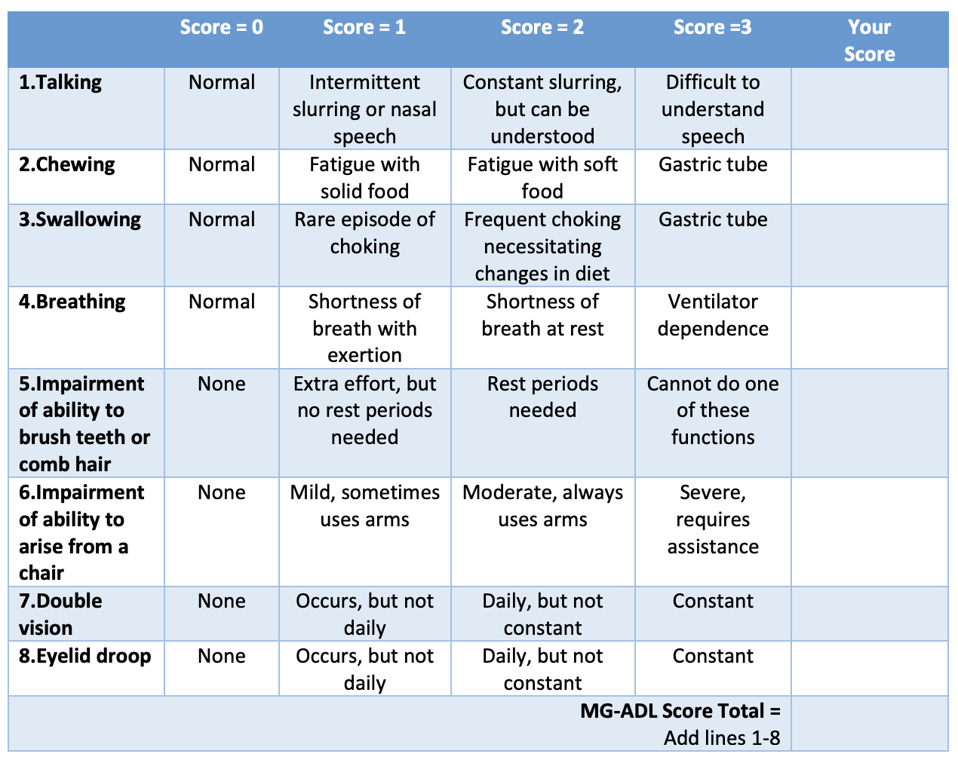
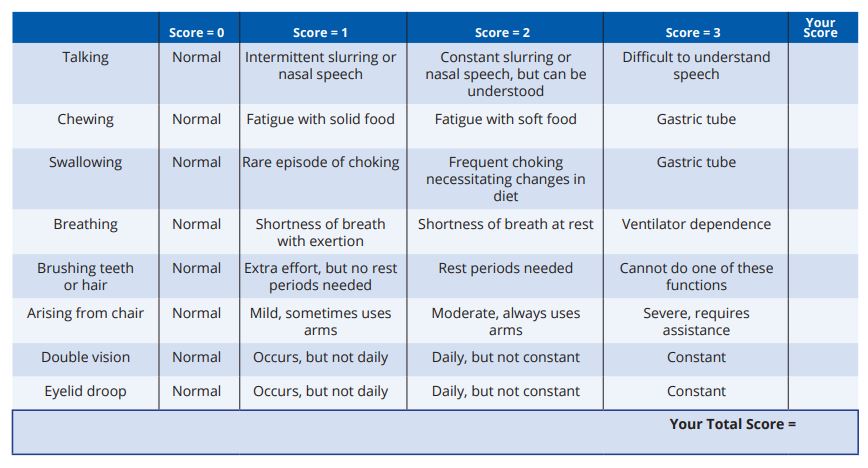
The MG-ADL and QMG are the two scales most people actually use in clinical practice. I have been doing this for years, and honestly, the paperwork side is where things usually go wrong, not the scoring itself. The MG-ADL questionnaire asks patients to rate six specific activities over the past 24 hours: speech, swallowing, chewing, breathing, upper extremities, and eyelid closure. Each item uses a 0 to 5 scale. The total possible score ranges from 0 to 30, with higher numbers indicating more severe impairment. The scoring sheet is straightforward. You ask the patient to rate each function. Then you add the numbers. That is the entire process, assuming you follow the instructions carefully.
Here is something most beginners miss. The MG-ADL only captures what happened yesterday, not today. A patient who took extra rest in the morning might score much better than someone who was active. This creates real variability in serial assessments unless the timing is standardized.
Practical Use and Common Problems
I once had a patient who scored 3 on chewing but 0 on swallowing. When I asked follow-up questions, she had been eating soft foods all day. The scale does not account for dietary modifications. She was compensating without the score reflecting that effort. I started documenting the diet type alongside the score, and it made follow-up notes much clearer. The QMG is the clinician-rated version. A neurologist or trained examiner observes function rather than relying on patient report. It covers the same domains but adds items like facial expression and neck strength. The range goes from 0 to 40. Lower scores mean better function.
Get the Full Details

How to Administer the MG-ADL Correctly
Ask the patient to rate each item based on their worst moment in the previous 24 hours, not their best day. Most patients default to their good days when filling it out, and that understates their actual burden. Tell them to think about the times they struggled, not the times they felt fine. Timing matters. Try to administer the assessment at the same time of day for serial measurements. Morning scores are typically lower due to medication wearing off overnight. Afternoon and evening scores reflect fatigue buildup from daily activity. Document everything. Note the time of assessment, what medications were taken recently, and whether the patient did any unusual activity that morning. These details explain score fluctuations better than the raw number alone.
When These Tools Fall Short
The MG-ADL and QMG both miss respiratory muscle weakness unless it is severe enough to affect the rated items. A patient can have significant respiratory compromise while scoring in the mild range on the ADL scale. I always add a quick forced vital capacity check when the clinical picture does not match the score. The swallowing item is another gap. Some patients rate themselves poorly on chewing but fine on swallowing because they modified their technique without realizing it affects oral intake efficiency. If you suspect dysphagia beyond what the scale shows, add a formal swallowing assessment. The eyelid item often confuses people. Ptosis scoring is subjective. One examiner might see 1 mm of lid coverage difference as a full point change. Another might not. Train your raters or use video documentation for consistency across visits.
Recording Results
Write the total score clearly. Add the date, time of day, and relevant context notes. Track the trend over multiple visits rather than focusing on a single number. A score that drops from 18 to 12 over three months means something very different than a random fluctuation between 15 and 16. If you want the official scoring forms, they are available through the Myasthenia Gravis Foundation of America website and the MGFA clinical guidelines. Most hospitals also have their own versions in the electronic health record templates, though they sometimes omit the timing note field that makes serial comparison actually useful.

Alternatives Worth Knowing
The MG-QOL15R measures quality of life impact rather than physical function. It asks about social functioning, emotional health, and daily limitations. Use it alongside the MG-ADL if you want the full picture. The QMG remains the standard for clinical trials and drug efficacy studies. If you are not doing research, the MG-ADL plus clinical observation covers most routine needs. The key takeaway is that these tools work well when you understand their limits. They measure what they are designed to measure. They do not replace a thorough neurological exam or the clinical context that surrounds the score.