What Actually Happens in OT for MG
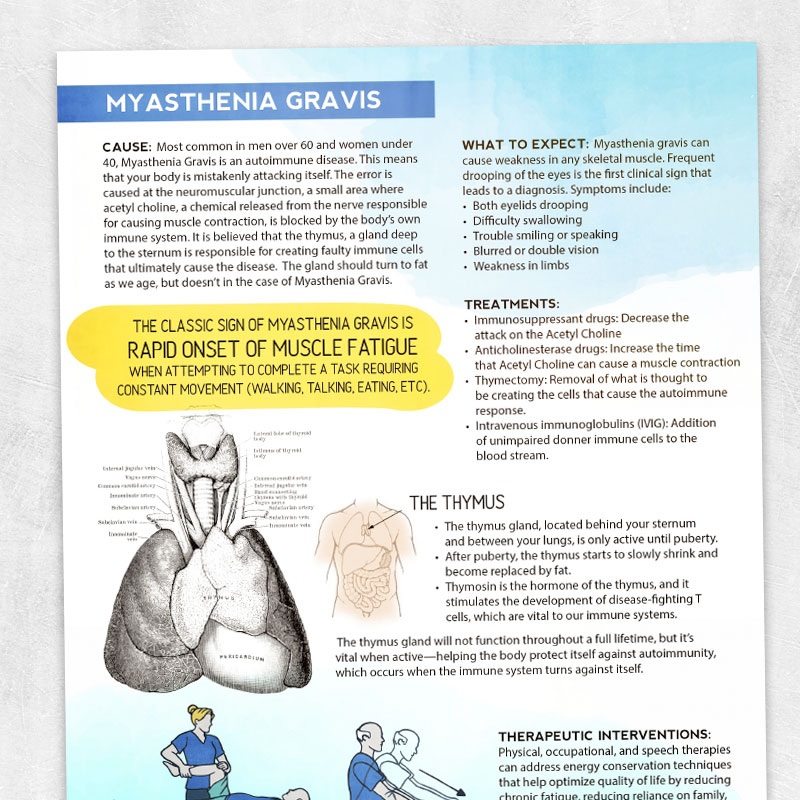
Myasthenia Gravis is a neuromuscular junction disorder. The basic problem is antibodies attacking acetylcholine receptors, so muscles fire inconsistently and fatigue rapidly. Occupational therapy doesn't fix that. It manages what comes after. I've worked with enough MG patients to know the typical picture: someone who can dress themselves at 9am but can't manage the same task by 2pm without collapsing. The fatigue isn't generic tiredness. It's a specific muscle-specific exhaustion that follows a diurnal pattern and worsens with repetition. Standard energy conservation models from stroke or COPD don't map cleanly onto this because MG fatigue is unpredictable in timing and severity.
Myasthenia Gravis Occupational Therapy Treatment
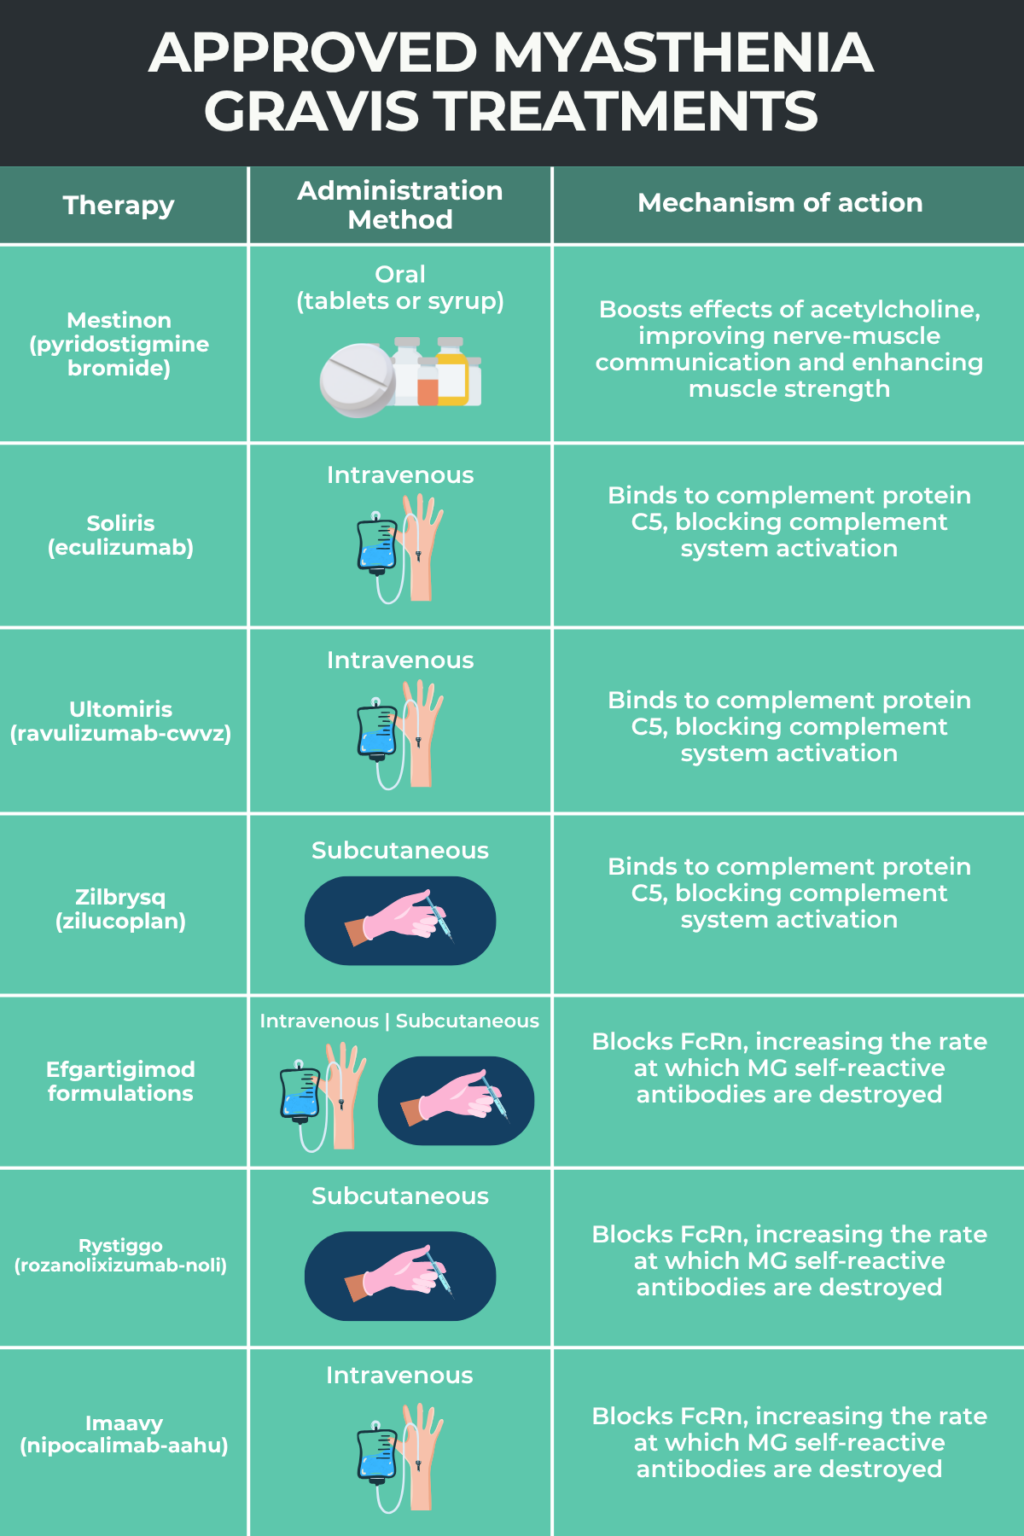
The treatment itself breaks down into a few core components. Energy conservation comes first, and most therapists jump straight to scheduling and pacing. That's fine for mild cases. What actually works is teaching patients to recognize their personal baseline before the disease worsens or before medication changes it. I had a patient in my practice last year who couldn't grasp why her pacing strategies kept failing. She had just been switched from pyridostigmine to add prednisone. Her energy curve shifted completely. The same routine that worked at 8am now left her bedbound by 11am. We restructured around her new medication window instead of trying to force the old schedule. That's the kind of thing that doesn't show up in textbooks. Adaptive equipment is the second pillar. Spoon utensils with built-up handles. Reachers. Dressing sticks. Button hooks. Shower chairs. All standard. The catch is that not every device helps everyone. A reaching grabber sounds useful until you realize someone with shoulder girdle weakness can't operate it without exhausting their entire upper body. I found that for patients with proximal weakness, minimizing the equipment list and focusing only on the tasks they genuinely struggle with produces better adherence than handing out a full catalog of tools they won't use anyway. Joint protection techniques matter less here than in rheumatoid arthritis because MG doesn't primarily attack joints. But protecting fatigued muscles from strain still counts. Pacing activities into shorter segments with planned rest periods between them tends to preserve function longer than pushing through. The trick is that rest periods in MG need to be actual rest, not just slowing down. Sitting quietly for five minutes after a task often restores more function than forty-five seconds of reduced pace.
Assessment Before Intervention
You can't treat what you haven't measured. The MG-ADL scale and the Quantitative MG score are standard clinical measures. For occupational therapy specifically, the Arm Function subscale of the MG-QoL15 gives you useful practical data. Beyond that, a detailed activity analysis is non-negotiable. Map out exactly which movements trigger weakness in which muscle groups and at what time of day. I use a simple but effective log sheet where patients record three things: what task they attempted, the time of day, and a strength rating from one to five for the affected muscle group immediately after. This takes about ten minutes daily and usually reveals patterns within two weeks. One pattern I see repeatedly but never expect to see is that hand grip strength drops disproportionately compared to arm strength in some patients. You'd think proximal weakness would dominate the picture, but distal fatigue shows up consistently enough to matter for fine motor tasks like buttoning or manipulating keys.
Get the Full Details

Practical Interventions That Actually Work
Task simplification is the broadest category. Break every daily activity into its component movements and eliminate the ones that don't contribute to the outcome. Bathing doesn't require standing the whole time. Cooking doesn't require chopping everything by hand. These seem obvious until you watch someone attempt a fourteen-step shower routine when six would accomplish the same thing. Environmental modification follows naturally. Raise the bed if getting out requires significant leg strength. Install grab bars strategically, not everywhere. Keep frequently used items at waist level to avoid overhead reaching, which disproportionately affects MG patients because shoulder abduction fatigues quickly. I once worked with a woman who couldn't reach her medication bottle on a high shelf. She kept climbing a step stool, grabbing the bottle, then losing grip on the way down. We moved the medication to a drawer at counter height. Problem solved. No fancy equipment needed. Conservation techniques need individualization. The usual four Ps—prioritize, plan, pace, position—are correct in principle but mechanically applied they fail. Prioritization in MG means something different than in other conditions. It's not about choosing what matters most emotionally. It's about identifying which tasks absolutely cannot be skipped on a given day based on disease severity and medication timing. Planning means building rest into the task itself, not just scheduling rest between tasks. Pacing means matching the speed of movement to the patient's actual capacity at that moment, not some average capacity from last week. Positioning means supporting weakened muscles during the activity so they don't have to work as hard.
Medication Timing and OT Scheduling
This is where most treatment plans break down. Pyridostigmine typically peaks between thirty and ninety minutes after ingestion. Scheduling demanding occupational therapy activities during that window is standard advice. But it's not that simple. Some patients experience a cholinergic crisis if they take their dose too close to activity, causing paradoxical weakness from excess acetylcholine. Others find that taking the medication on an empty stomach causes gastrointestinal side effects that derail the entire day. I had a patient whose therapist scheduled all her home exercise program for the morning before her medication dose. The patient felt terrible afterward and stopped doing the exercises entirely. We rescheduled everything to ninety minutes post-dose. Compliance improved dramatically. The lesson is that the occupational therapist needs to coordinate with the neurologist on medication timing. Standing alone and designing a schedule without that input is a common mistake.
When OT Isn't Enough
Severe bulbar weakness changes everything. Swallowing difficulty, speech impairment, and respiratory compromise require intervention from speech-language pathology and pulmonology first. Occupational therapy in those cases focuses on compensatory strategies for feeding and communication rather than general daily activity training. There's a threshold where standard OT approaches simply don't apply and the patient needs a different level of care entirely. Ignoring that threshold leads to frustration for everyone involved. Another limitation is the variability of the disease itself. MG has remissions and exacerbations that don't always follow predictable patterns. A treatment plan designed for a stable phase can become obsolete overnight during a flare. The best approach is building flexibility into the plan from the start. Sessions should be shorter and more frequent during active phases, with clear criteria for when to adjust. Rigid long-term plans tend to fail because they don't account for the natural ebb and flow of the disease.
Measuring Progress
Progress in MG occupational therapy isn't linear. Improvement might mean someone can dress independently for three days instead of one. That's measurable and real, but it doesn't look like the steady progress graphs you see in rehabilitation textbooks. Using the MG-QoL15 or the Functional Independence Measure at regular intervals gives you objective data points that help both therapist and patient see improvement that might otherwise go unnoticed. One thing I've found useful is tracking the number of rest breaks required per task over time. If a patient needed four breaks to complete morning hygiene on week one and only two on week four, that's a concrete indicator of improvement even if the total time taken hasn't changed significantly. It reflects genuine gains in endurance and efficiency. The overall approach to Myasthenia Gravis Occupational Therapy Treatment requires coordination across specialties, constant adjustment to disease state, and a willingness to discard standard protocols when they don't fit the individual patient. It works when you treat it as a moving target rather than a fixed program.