How to Set Up and Manage an NG Tube With Suction
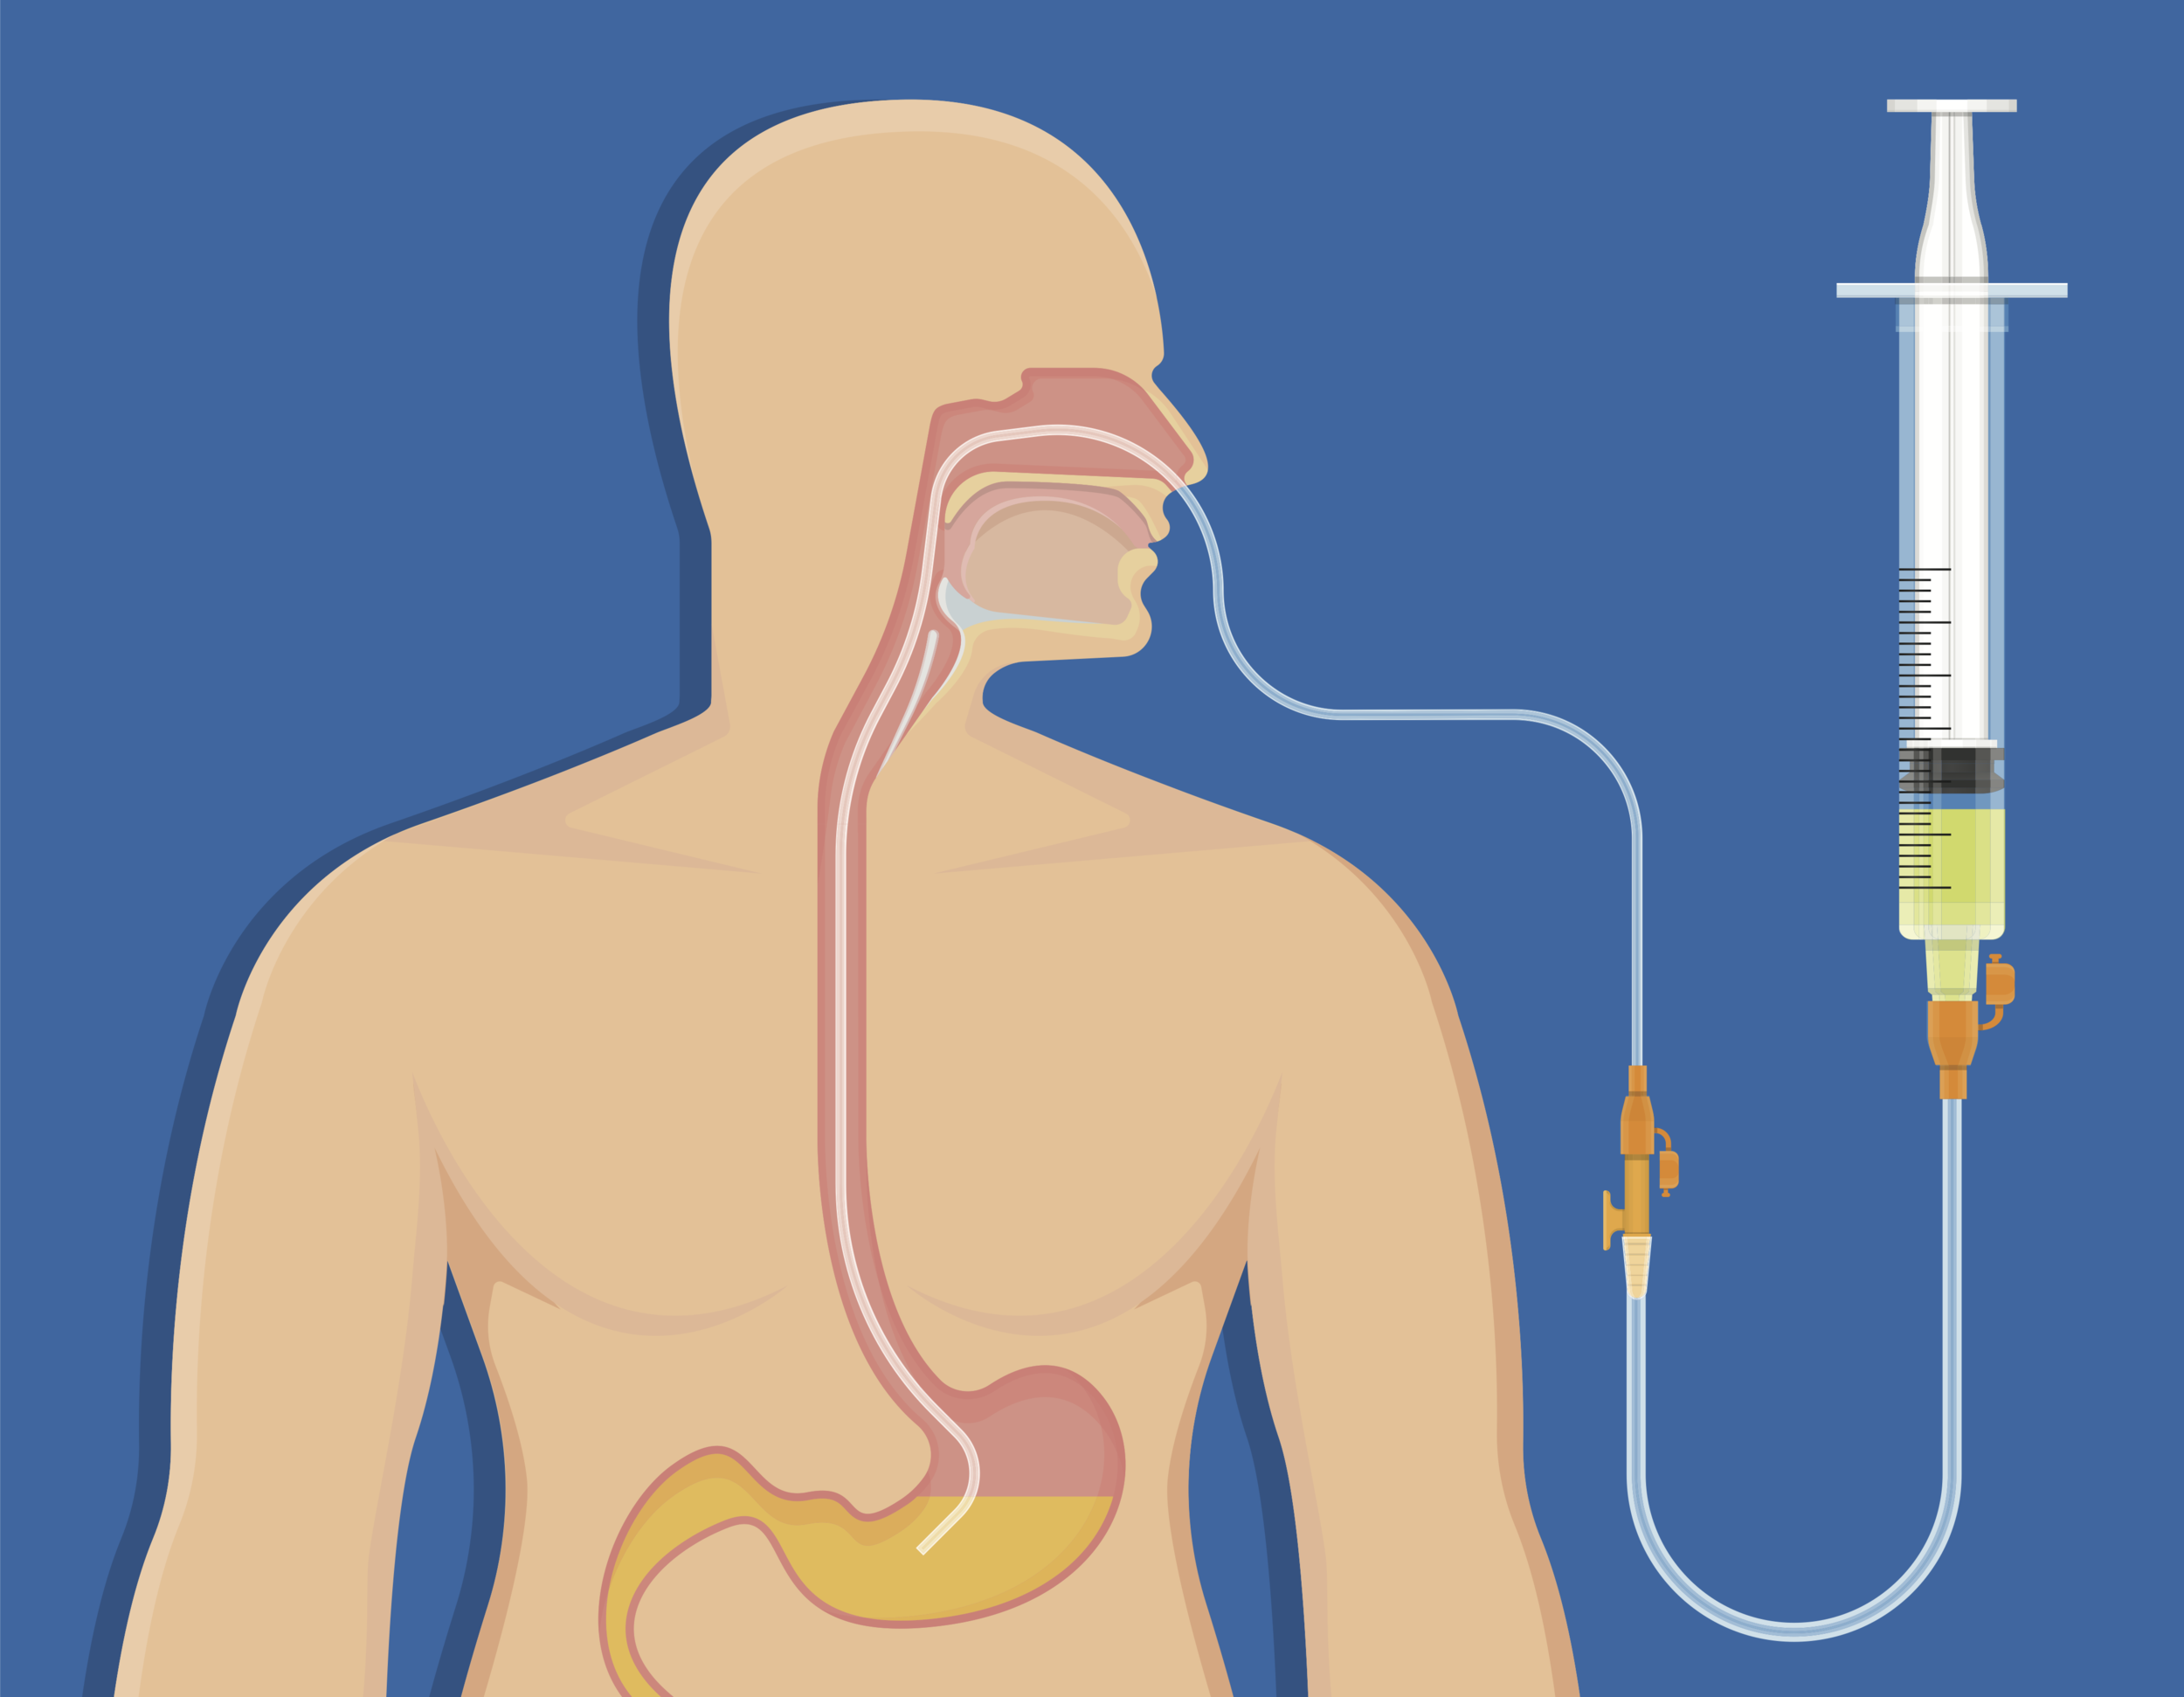
Most people learning about Nasogastric Tube With Suction get confused about the manometer setting and whether to use continuous or intermittent suction. Here is what actually works. Start by confirming the tube is below the gastroesophageal junction, which you do with an abdominal X-ray. Then attach the NG tube to a canister. Connect the canister to the wall suction outlet through a manometer. Set the manometer to no more than 100-120 mmHg. Do not exceed this. Higher pressures press the tube tip against the gastric mucosa and cause erosion. I have pulled tubes stuck to the stomach wall after a patient ran their suction at maximum. The tissue came away looking raw and weepy. This happens more often than you would think. I now set the initial suction at 80 mmHg and increase only if decompression is inadequate.
Nasogastric Tube With Suction: Practical Setup Steps
The setup itself is not complicated. The mistakes happen after the tube is in. Verify placement first. You need radiographic confirmation. Clinical methods like listening for a puff of air are unreliable. Check the pH of aspirate too. A pH below 5.5 supports gastric placement. If the pH reads higher than 6, the tube may have slipped into the respiratory tract and you should not apply suction. Once placement is confirmed, flush the tube with 30 ml of normal saline before attaching suction. This clears any blood or mucus that may be blocking the eyelets. Then connect to low intermittent suction. The cycle is typically 15 minutes on, 15 minutes off. Some units run continuous low suction instead. Intermittent is preferred by most surgical teams because continuous suction increases the risk of mucosal injury. The exact cycle varies by hospital policy. Monitor the output volume and character every four hours. Note the color. Coffee-ground material means old blood. Bright red blood is an acute bleed and needs urgent review. Feculent output suggests a distal bowel obstruction. Bilious output is expected with a functioning duodenal connection.
I ran into a problem last year where a post-op patient had nearly no output from the NG tube despite obvious abdominal distension. The tube was patent on aspiration but nothing was coming through under suction. I repositioned the patient to the left lateral decubitus position, flushed with 30 ml of normal saline and a 20 ml air bolus, then rolled them to the right side. The output started immediately. The tube tip had been abutting the posterior gastric wall and suction was just holding it there. This maneuver shifts the stomach contents away from the tip. It has saved me several tube changes since then.
Get the Full Details

When Suction Is Not the Right Approach
There are situations where a Nasogastric Tube With Suction will not solve the underlying problem. Small bowel obstruction with a competent ileocecal valve is one. The tube can decompress the stomach but cannot bypass a distal blockage. In these cases the small bowel remains distended and the risk of ischemia is real. Surgical consultation is needed rather than prolonged NG management. Prolonged suction without repositioning or flushing leads to electrolyte depletion. Gastric fluid contains significant potassium and hydrogen ions. A patient on continuous NG suction for more than 48 hours can develop metabolic alkalosis and hypokalemia. Check electrolytes daily. Replace potassium as needed. This is not optional. Another issue is nasopharyngeal discomfort. Patients with an NG tube in place often swallow air, which actually increases gastric distension. This is counterproductive. Teach the patient to breathe through the mouth. Use lip balm on the nose. Secure the tube well so it does not migrate. Check the external marking against the original insertion depth every shift.
The tube is also contraindicated in basal skull fracture. Insertion can lead to intracranial placement. Do not attempt it. Use an orogastric tube instead if gastric decompression is required.
Removal and Aftercare
Remove the tube when bowel function returns. This is shown by the return of flatus, resolution of nausea, and decreasing abdominal distension. Clamp the tube for a trial period first. Some teams keep it on suction for 24 hours before removal to see if symptoms recur. There is no strong evidence supporting one approach over the other. Before pulling the tube, have the patient take a deep breath and hold it. This closes the glottis and reduces the risk of aspiration during removal. Wipe the nostril and secure area with a gentle cleanser. Inspect the nares for pressure sores. Most damage is minor but can become infected if neglected. The biggest mistake I see is leaving the suction running on an empty stomach. The tube will just keep drawing mucosa into the eyelets. Turn it off or switch to gravity drainage with periodic saline flushes once decompression goals are met. This simple change reduces mucosal irritation significantly and is often overlooked in busy wards.