
Why My First Round of NDT Handlers Failed So Hard
I spent three years working NDT into my OT practice after picking it up from a conference workshop. The training itself was thorough on paper, but nothing prepared me for the gap between what the manual says should happen and what actually happens when you put your hands on a person who has spent eighteen months compensating for a left MCA stroke. NDT in occupational therapy is not a separate modality you "add on." It is a way of looking at how tone, alignment, and sensory processing interact during functional tasks. You learn to feel for the quality of movement rather than just counting repetitions. When you pick up a bowl to stir, you are evaluating proximal stability, scapular control, hand opening, and wrist extension all at once. The training teaches you to prioritize the proximal before the distal. Most beginners skip that because it feels slow. The core idea is straightforward enough. You use handling to influence tone, facilitate more normal movement patterns, and inhibit abnormal ones while the patient practices a meaningful task. The Bobath concept of "key points of control" — around the trunk, pelvis, scapula, and wrist — is where the technique lives. You are not doing stretches. You are not strengthening through reps. You are providing sensory input that guides the nervous system toward better organization during activity.
What Ndt Training Occupational Therapy Actually Looks Like in a Session
Here is the sequence I use, and it took me about fourteen months of supervised cases before I stopped fumbling through it. First, you observe. Not a quick look. I mean watching the patient attempt a task for at least three full repetitions without intervening. I watched a woman with right hemiplegia try to pour water from a pitcher. Her trunk rotated to the right before her arm even started moving. Her scapula was protracted and depressed. The pouring happened entirely from shoulder hiking and trunk compensation. Nobody had ever watched her do this before asking her to "just lift your arm higher." Second, you position. You set up the body so the tone has the best chance of settling. For my pouring patient, I had her sit with her right foot flat, pelvis neutral, and a small towel roll under her right scapula. That single roll changed everything. It stopped the scapular dropping, which allowed her truncal control to shift from holding herself up to actually balancing while reaching.
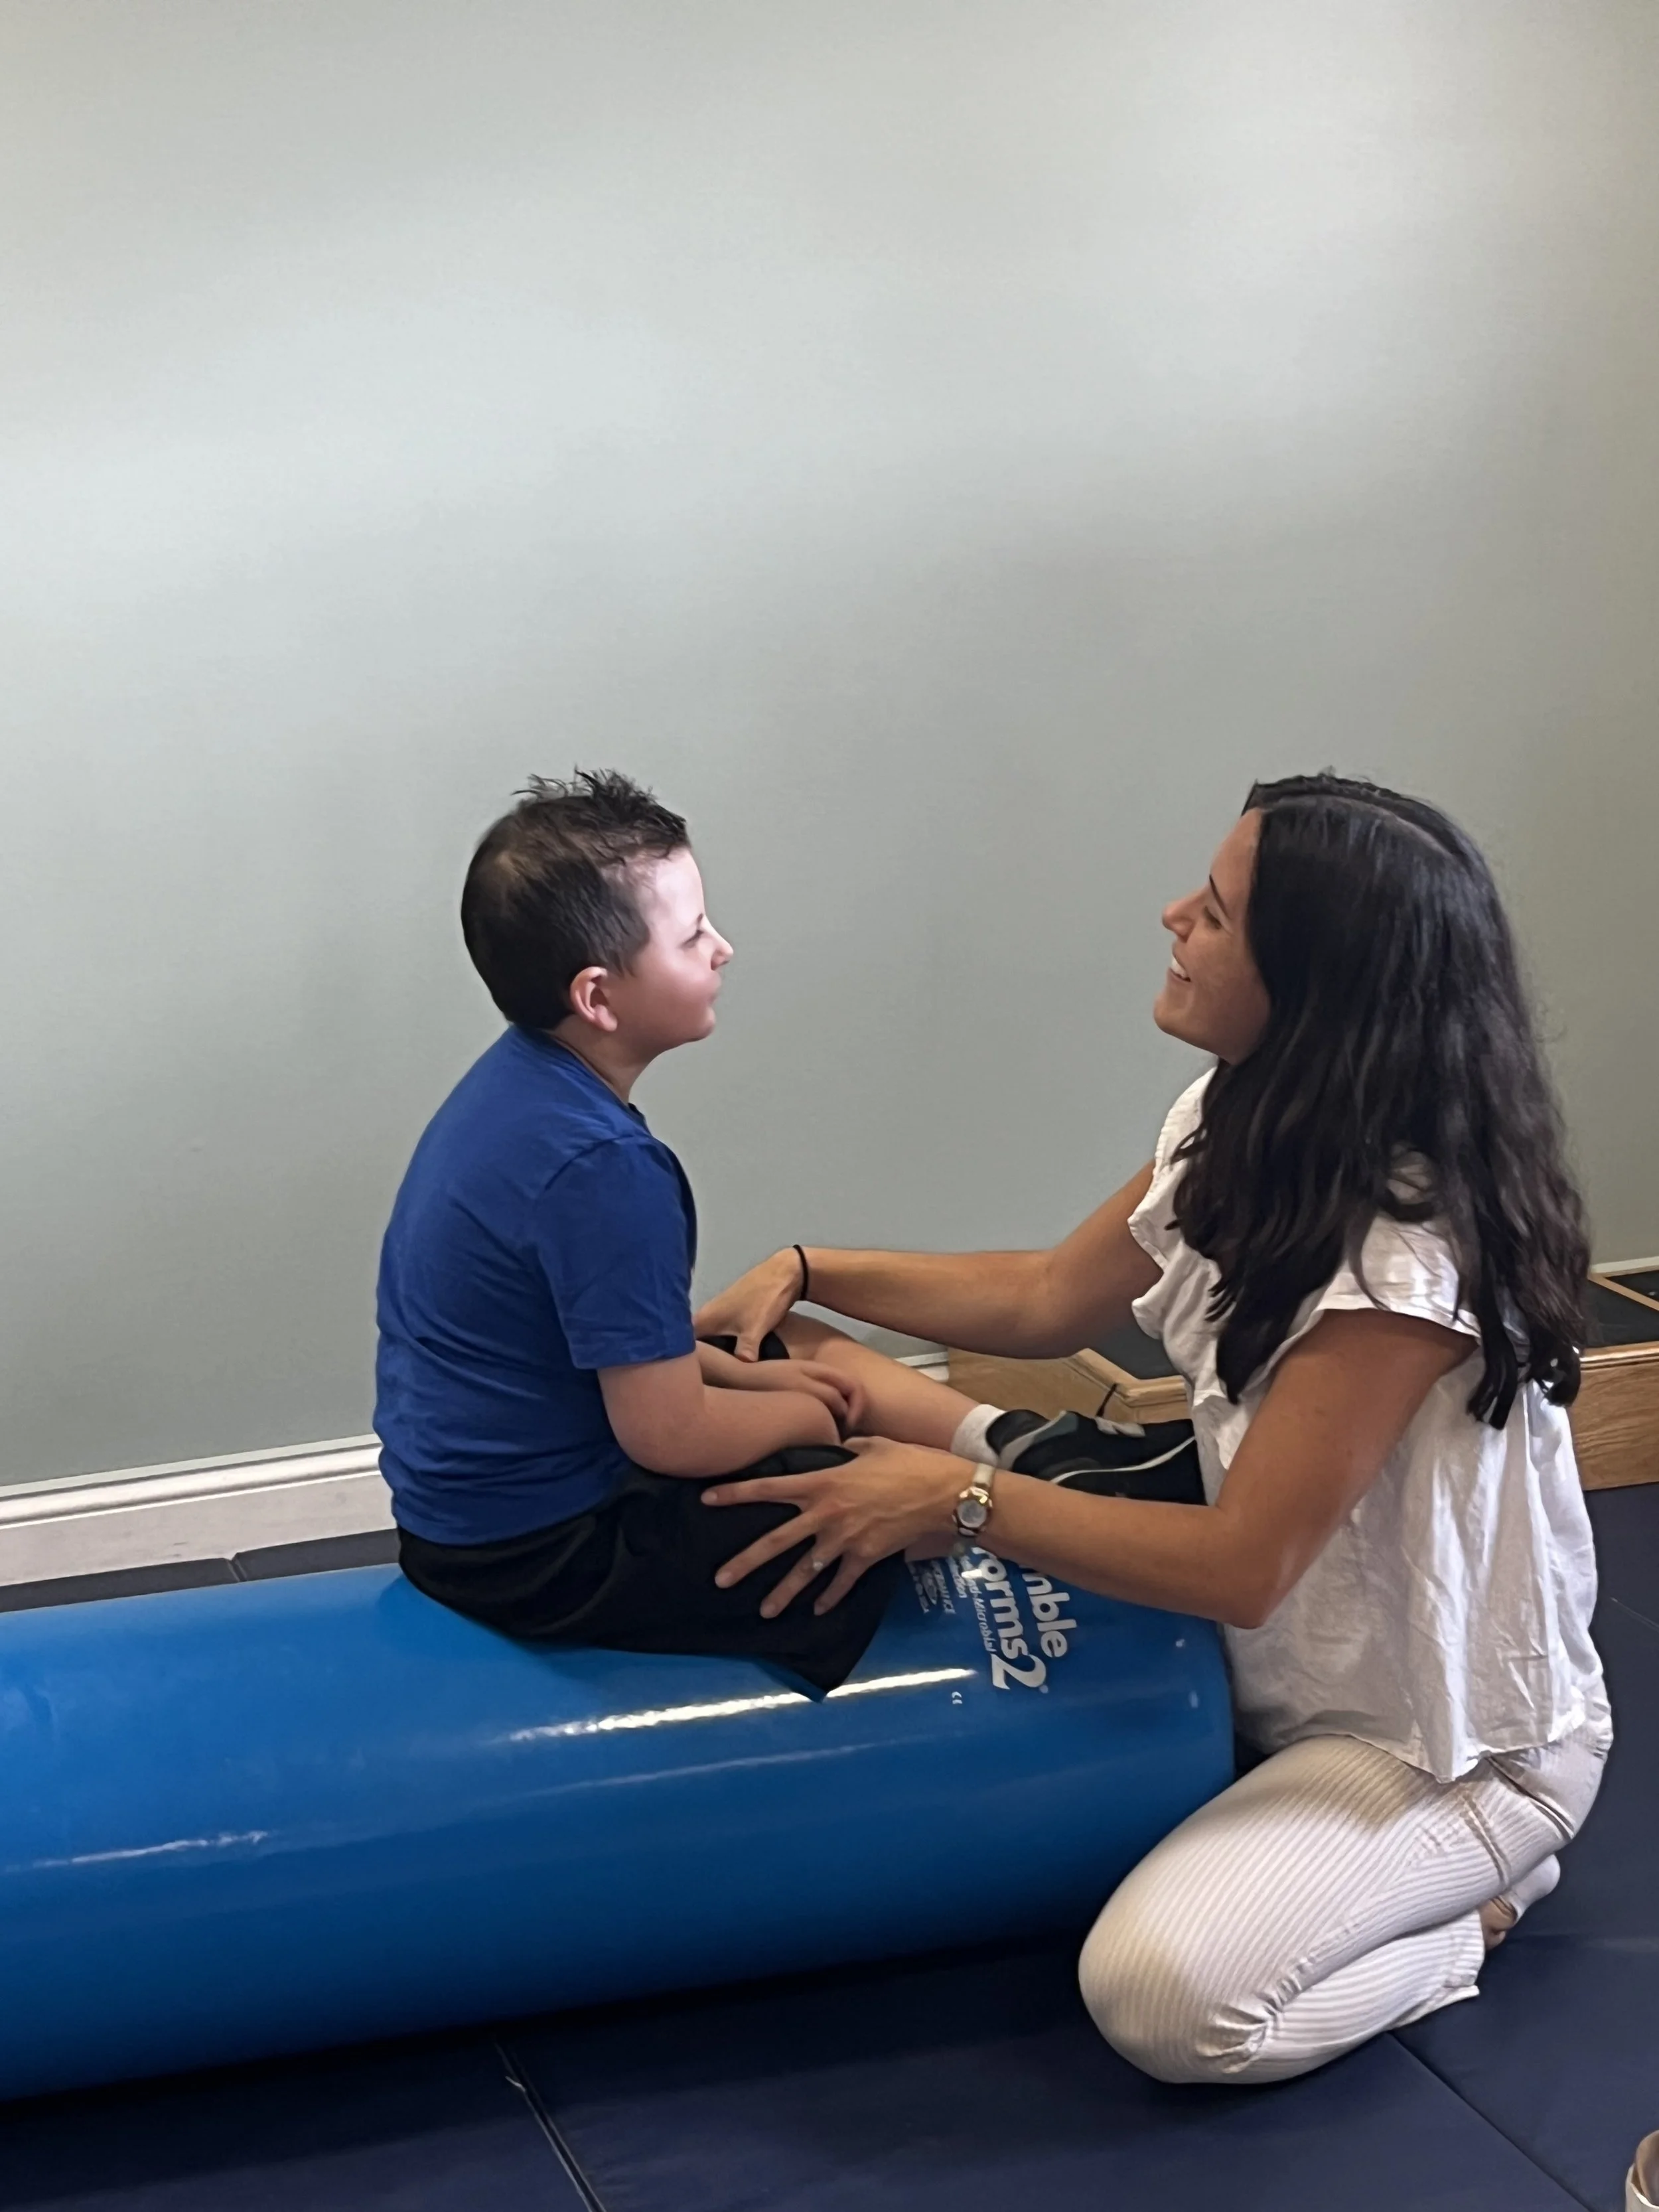
Third, you handle during the task. This is where most OTs stop because handling while someone is actively moving is harder than static positioning. I placed my left hand on her right iliac crest to guide lateral weight shift, and my right hand supported her right forearm near the wrist, facilitating extension without forcing it. She poured. The water stayed in the glass. Her trunk stayed more centered. It looked like barely anything had changed to an observer, but the difference in her upper extremity quality was dramatic. You repeat this cycle. Position, handle, observe, adjust. A typical thirty-minute block might contain only eight to twelve successful repetitions because the setup and observation take real time. This is not inefficiency. It is the method.
Get the Full Details
The Case That Made Me Rethink How I Used Inhibition
Early in my practice, I had a patient with cerebral palsy, spastic diplegia, who could not independently transfer from bed to chair. His hip extensors were hypertonic, and his quads would fire whenever he tried to flex his hips. The standard NDT approach would be to inhibit the extensors through sustained pressure and slow stretching before the transfer attempt. It did not work. Not even close. I spent six sessions doing pre-transfer inhibition and his transfer ability actually got worse because he learned to brace harder in anticipation of the stretch. Here is what I finally figured out: his hypertonicity was not primarily a tone problem. It was a fear-based protective strategy rooted in poor proprioceptive feedback from his ankle dorsiflexors. He could not feel where his feet were, so he co-contracted everything to create artificial stability. My workaround was to abandon pre-task inhibition and instead use handling to provide accurate proprioceptive input during the movement itself. I had him sit at the edge of the bed with my hands on his posterior calves and medial malleoli, giving clear boundary feedback as he shifted weight forward. I did not stretch. I did not hold pressure to reduce tone. I simply helped his nervous system feel the positions it needed to execute the transfer. Three sessions later, he was transferring with minimal assistance. The tone dropped incidentally because the reason for the co-contraction was gone.
This is the part nobody puts in the basics training: inhibition does not always come before the task. Sometimes the inhibition happens because the task becomes possible when the sensory input is correct. You have to know the difference.
Advanced Nuances That Separate People Who Actually Use NDT From People Who Just Talk About It
Most people trained in NDT can recite the sequence of assess-position-handle-repractice. The people who are actually good at it understand two things that are easy to miss. First, tone is context-dependent in ways that make it nearly impossible to treat in isolation. A patient might present with low tone in the clinic but recruit abnormally high tone the moment they attempt a kitchen task. This is not contradiction. It is the nervous system responding to sensory demand. If you only treat the tone you measure in a passive sitting position, you are treating a snapshot, not the condition. I learned to carry my NDT principles into the kitchen simulation room and re-evaluate tone there before designing any intervention. Half the patients I referred for NDT-based strengthening turned out to have normal or low tone once they were standing and reaching. Second, the timing of your facilitation matters more than the direction of your force. Beginners push or pull in the "right" direction. Experts time their input to coincide with the patient's own motor intent. If you facilitate too early, you take over the movement. If you facilitate too late, the abnormal pattern has already fired. The window is often less than two hundred milliseconds. I used to miss this constantly and then wonder why my handling felt like I was wrestling the patient. The answer was almost always that I was reacting to their movement instead of anticipating it.

What NDT Training Occupational Therapy Gets Wrong or Leaves Out
I am going to be blunt about the limitations because the training programs do not always emphasize them. NDT is not effective for patients who have significant cognitive impairment that prevents them from participating in the motor learning process. The whole facilitation-and-practice loop requires at least some capacity for motor intent and feedback processing. I had a patient with moderate traumatic brain injury who responded beautifully to NDT principles during sitting balance work but completely regressed during community mobility tasks because the cognitive load exceeded his capacity to process the handling cues. In those cases, a cueing and repetition-based approach with environmental modification worked better. NDT was not the failure. It was just the wrong tool for that specific combination of deficits. The training also tends to underprepare OTs for acute care settings. The principles are designed around a patient who can sit unsupported and attend to a task. Applying them to a patient who is still intubated and sedated requires a different skill set that most continuing education courses do not cover. I found myself guessing at handling techniques for ventilator-dependent stroke patients until I found a neuro-ICU therapist who had adapted Bobath concepts for that population. That knowledge was not in my original certification curriculum.
There is also the issue of documentation. NDT-based interventions are genuinely hard to document in a way that payers find acceptable. Saying you provided "handling to facilitate proximal stability and inhibit extensor synergy during ADL training" does not map neatly onto standard billing codes. I spent considerable time learning how to translate NDT procedures into language that insurance reviewers would recognize as medically necessary. This is a practical bottleneck that the training does not address.
Practical Steps to Integrate NDT Into Your OT Practice
If you want to move beyond theory, here is what actually works. Start with one patient. Pick someone with a clear focal neurological deficit where proximal instability is driving the distal dysfunction. Stroke with hemiplegia works well. Do not try NDT on everyone. You need a candidate where the approach will obviously change the outcome so you can recognize the difference. Record your sessions if possible. Even audio recordings help. Listening back to your own handling cues reveals timing problems you cannot feel in the moment. I caught myself consistently facilitating too late on my tenth recorded session. That was the session where I realized I was waiting for the patient to start moving instead of entering their movement at the onset.

Find a mentor who actually uses NDT clinically, not just teaches it. Conference workshops give you the framework. Real mentoring fixes your hands. I watched a colleague who had been using NDT for twelve years handle a patient with spastic hemiplegia and realized I had been handling the same condition for five years with completely different touch quality. The difference was not knowledge. It was tactile discrimination built through thousands of repetitions with feedback. Track your outcomes with simple measures. Fugl-Meyer for motor control, modified Ashworth for tone, and any ADL scale your facility uses. NDT effects are gradual. You will not see dramatic change in three sessions. You will see it over eight to twelve weeks if the patient is appropriate and your handling is accurate. The data will tell you whether you are actually doing it or just going through the motions. Integrate NDT principles with other approaches rather than treating it as a standalone system. I combine NDT handling with task-oriented training and constraint-induced principles when the patient has recovered enough proximal control to benefit from higher repetition. The NDT work sets the foundation. The other methods build capacity on top of it. Neither works as well alone for many of the patients I see.
The training gave me a lens. The practice taught me when to use it and when to put it down. That distinction is what separates competent NDT-informed OTs from the ones who try to fit every patient into the same handling template regardless of whether it helps.
.jpg "What is NDT? - Neuromotion Physiotherapy + Rehabilitation")

