Understanding Neck Cross Sectional Anatomy Through Imaging
Neck cross sectional anatomy is something you deal with constantly if you work in radiology, head and neck surgery, or ultrasound. It's not academic theory. It's the difference between hitting a tumor margin and leaving residual disease, or missing a vascular anomaly before you start cutting. The neck is organized in levels, and those levels aren't just labels. They're surgically meaningful boundaries. Level I sits above the hyoid, level II runs from the skull base down to the hyoid at the carotid sheath, level III is mid-neck, level IV goes to the clavicle, and level V is the posterior triangle behind the sternocleidomastoid. Knowing which structures sit at each level on an axial slice is the actual job, not memorizing Latin names for things you can't locate.
How to Read a Cross Section of the Neck at the Thyroid Level
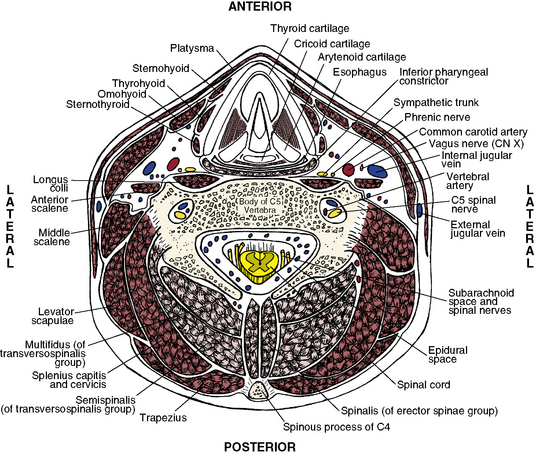
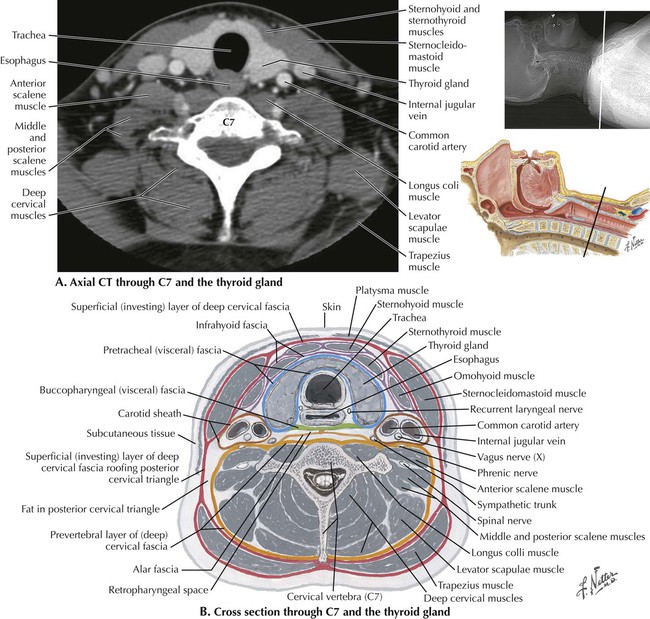
Start with the thyroid cartilage as your landmark. On an axial CT at that level, you're looking at the airway as a black circle in the midline. Anterior to it is the thyrohyoid membrane. Lateral to the airway are the false vocal cords and the paraglottic space. The true vocal cords sit just below that plane. If you're using ultrasound instead, the trachea is the bright curved line with reverberation artifact behind it, and the thyroid lobes sit anterolateral on each side. Here's what beginners get wrong. They look for the recurrent laryngeal nerve like it's a structure you can reliably identify on every scan. It's not. At the thyroid level, the RLN is running in the tracheoesophageal groove, but it's often submillimeter and surrounded by fat and connective tissue. On standard clinical CT with 3mm slices, you're lucky to see it as a dot. On ultrasound it's barely visible unless you have a high frequency probe and a good operator. The workaround I use is to track it indirectly. Find the inferior thyroid artery crossing the nerve, then work back along the esophageal border. That usually gets you in the right neighborhood. I ran into a specific problem last year with a thyroidectomy case. The preoperative CT showed what looked like normal level VI lymph nodes anterior to the trachea. But during dissection, two of those nodes were actually outside the pretracheal fascia, sitting in the paratracheal fat plane that wasn't clearly demarcated on the scan. The CT had shown them, but I hadn't recognized that the fascial plane was shifted laterally by a goiter. The workaround was straightforward: I went back to the ultrasound and traced the pretracheal fascia in real time while the patient was in the supine position with the neck extended. That positional change made the fascia visible as a thin echogenic line, and it clarified exactly which nodes were truly within the surgical field versus outside it. Saved about twenty minutes of unnecessary dissection.
The carotid sheath deserves its own attention. It contains the common carotid artery, internal jugular vein, and the vagus nerve. On axial imaging the IJV is usually lateral and compressible. The carotid artery is round and thick-walled. The vagus nerve sits between them, posterior and slightly medial, but you can't count on seeing it. It's there. You just might not see it depending on slice thickness and contrast timing. At the level of the cricoid cartilage, things shift. The thyroid cartilage is gone, the cricoid is a complete ring, and the subglottis sits just below. This is where the paralaryngeal fat pad becomes important. It's the space between the thyroid cartilage and the vocal cord apparatus. When that fat pad gets effaced on imaging, it's a sign of glottic cancer spreading out of the cord. That's a useful finding because it changes staging from T1 to T3 in most classification systems. MRI gives you better soft tissue resolution than CT, but it's slower and more prone to motion artifact from swallowing and breathing. For evaluating perineural spread, especially along the glossopharyngeal or vagus nerves, T1-weighted fat-saturated sequences with gadolinium are the standard. The contrast enhancement makes the nerve pathways visible against the background fat. Without fat suppression, the enhancement blends into the surrounding tissue and you miss early spread.
Get the Full Details
Ultrasound has a different set of constraints. It's operator dependent, which means your results vary depending on who's holding the probe and how much neck adipose tissue the patient has. A thin neck with a large thyroid is the ideal scenario. A thick neck with a small thyroid and lots of overlying strap muscle is about as useful as a brick. I typically use a 12 MHz linear probe for thyroid and level VI nodes. Higher frequency gives better resolution but less penetration, so I drop to 7 MHz when I need to see deeper structures like the carotid sheath or level IV nodes. One counter-intuitive thing about cross sectional anatomy of the neck: the platysma muscle isn't a reliable fascial boundary. People treat it like it is, but it's a thin sheet that varies enormously between patients. Some people have a distinct platysmal layer that separates subcutaneous fat from the deeper cervical fascia. Others barely have it. Using it as a landmark for surgical dissection or for defining infection spread on imaging will lead you astray. The superficial cervical fascia, specifically the investing layer, is the actual boundary you should be tracking. The spinal accessory nerve (CN XI) at the posterior triangle is another structure that's easy to miss but clinically critical. It crosses the internal jugular vein at roughly the level of the cricoid and then descends obliquely through the posterior triangle toward the trapezius. On CT it's invisible in most cases. On ultrasound it's visible in maybe 40 percent of patients with a good probe. The practical approach is to identify the sternocleidomastoid posterior belly edge and then trace a line from the angular process of the hyoid down toward the trapezius insertion. The nerve is somewhere in that corridor. During a level V neck dissection, you find it by following the fascial plane along that path.
Let me address a limitation that doesn't get enough attention. Cross sectional imaging has a fundamental problem with nodal staging in the neck. A lymph node needs to be about 5mm in short axis to be reliably detected on CT, and even then, reactive nodes and metastatic nodes look identical until they're removed and examined microscopically. The commonly used size criteria for Level II nodes being abnormal above 10mm or Level IV above 8mm are rough guides, not diagnostic thresholds. I've seen 7mm nodes with positive margins and 15mm nodes that were completely benign on histology. The imaging tells you about morphology—necrosis, extracapsular extension, shape—but it can't replace pathologic examination for definitive staging. If you're learning this for surgical purposes, the most practical method is to correlate axial, coronal, and sagittal planes simultaneously. Don't rely on axial alone. A lesion that looks confined on an axial slice might be wrapping around the carotid artery when you see the coronal reformation. I keep all three planes open on my workstation at all times. It takes about thirty seconds longer per case to scroll through the coronal and sagittal reconstructions, but it catches things that axial-only review misses consistently. For radiation oncology planning, the delineation of gross tumor volume on cross sectional anatomy follows the same anatomical principles but adds the dimension of radiation field design. The CTV margins extend differently depending on whether you're treating the primary site or elective nodal regions. Level II and III get elective coverage in most oropharyngeal and oral cavity cases. Level IV and V are more situational. The anatomy doesn't change, but your interpretation of which levels to include based on the primary tumor's drainage pattern does, and that's where the real knowledge comes in.
Common Pitfalls When Working With Neck Cross Sectional Anatomy
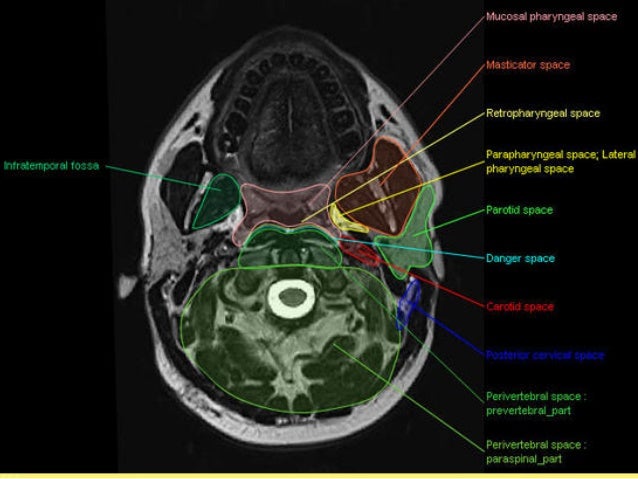
Artifact from dental fillings on CT is a real problem at the level of the oral cavity and oropharynx. Beam hardening streaks can obscure the tongue base, the vallecula, and the base of tongue structures you need to evaluate. Reducing the kVp helps somewhat, but the most effective workaround is to have the patient tilt their head slightly forward if positioning allows, which moves the mandible out of the field of view for the structures you care about. Alternatively, metal artifact reduction algorithms on modern CT scanners can clean up enough of the streaks to make the anatomy readable again. On MRI, flow void in the carotid arteries can sometimes be mistaken for calcification or a vascular anomaly if you're not expecting it. The key is recognizing that flow voids are signal absence that follows the expected anatomical course of a vessel. Calcification appears as high signal on some sequences and low signal on others. A true vascular anomaly would deviate from the normal anatomical pathway. The retropharyngeal space is another area where mistakes happen regularly. It lies posterior to the pharynx and anterior to the prevertebral fascia. On axial CT it's a potential space filled with fat and a few small lymph nodes. When it fills with fluid or mass, it usually means infection from a deep neck space or metastatic disease from the nasopharynx or oropharynx. The retropharyngeal lymph nodes drain the nasopharynx specifically, so a mass in that space in an adult should make you think about nasopharyngeal carcinoma until proven otherwise. In a child, it's most commonly infectious.

The prevertebral space sits just anterior to the vertebral bodies and extends from the skull base to the sacrum. It contains the longus colli and longus capitis muscles, the cervical spine, and the sympathetic chain. An abscess in this space is different from a retropharyngeal abscess both in etiology and in surgical approach. A prevertebral abscess usually tracks along the longus colli muscle and can extend into the posterior mediastinum. You need to image well below the diaphragm to check for that extension on the CT. Missing it means you're doing an incomplete drainage procedure. For anyone studying this subject, the most efficient resource combination is a good cross sectional anatomy atlas paired with actual cases. Books like Gray's Anatomy for Students or Netter's have decent axial neck images, but they don't replicate the variability you see in real clinical imaging. The atlas images are too clean. Real scans have motion, artifact, anatomical variants, and pathology that distorts normal relationships. Spend time looking at axial, coronal, and sagittal reformats from actual CT and MRI studies. The variation between a normal scan and the textbook diagram is where your learning actually happens. The lateral neck compartment boundaries are defined by the sternocleidomastoid muscle anteriorly, the trapezius posteriorly, and the clavicle inferiorly. The posterior border of the sternocleidomastoid is the key landmark for distinguishing level II from level III nodes. Level II is above the inferior border of the hyoid, level III extends down to the lower border of the hyoid. In practice, that inferior hyoid border is not always clearly visible on every axial slice, especially on thicker cuts or with poor contrast. Using the cricoid cartilage as a secondary landmark helps. The inferior thyroid artery crosses at roughly the level of the cricoid, and that helps you orient yourself when the hyoid is ambiguous.
If you need downloadable reference material, most university radiology departments have axial anatomy atlases available on their websites. The RadPrimer and Radiopaedia both have free axial neck cross section sets with labeled structures. They're not perfect—some labels are simplified—but they're better than nothing for building your mental atlas. For surgical anatomy specifically, the Head and Neck Surgical Anatomy by Som and Curtin remains the standard reference despite its age. The CT correlation plates in that book are still useful. The biggest mistake I see residents make is trying to memorize every structure at every level instead of learning the key landmarks and working outward from them. Learn the airway, the carotid sheath, the thyroid, and the prevertebral muscles. Those four anchor points let you orient yourself anywhere in the neck on any imaging modality. Everything else branches off from them.