The honest truth about neck work after a bulging disc diagnosis
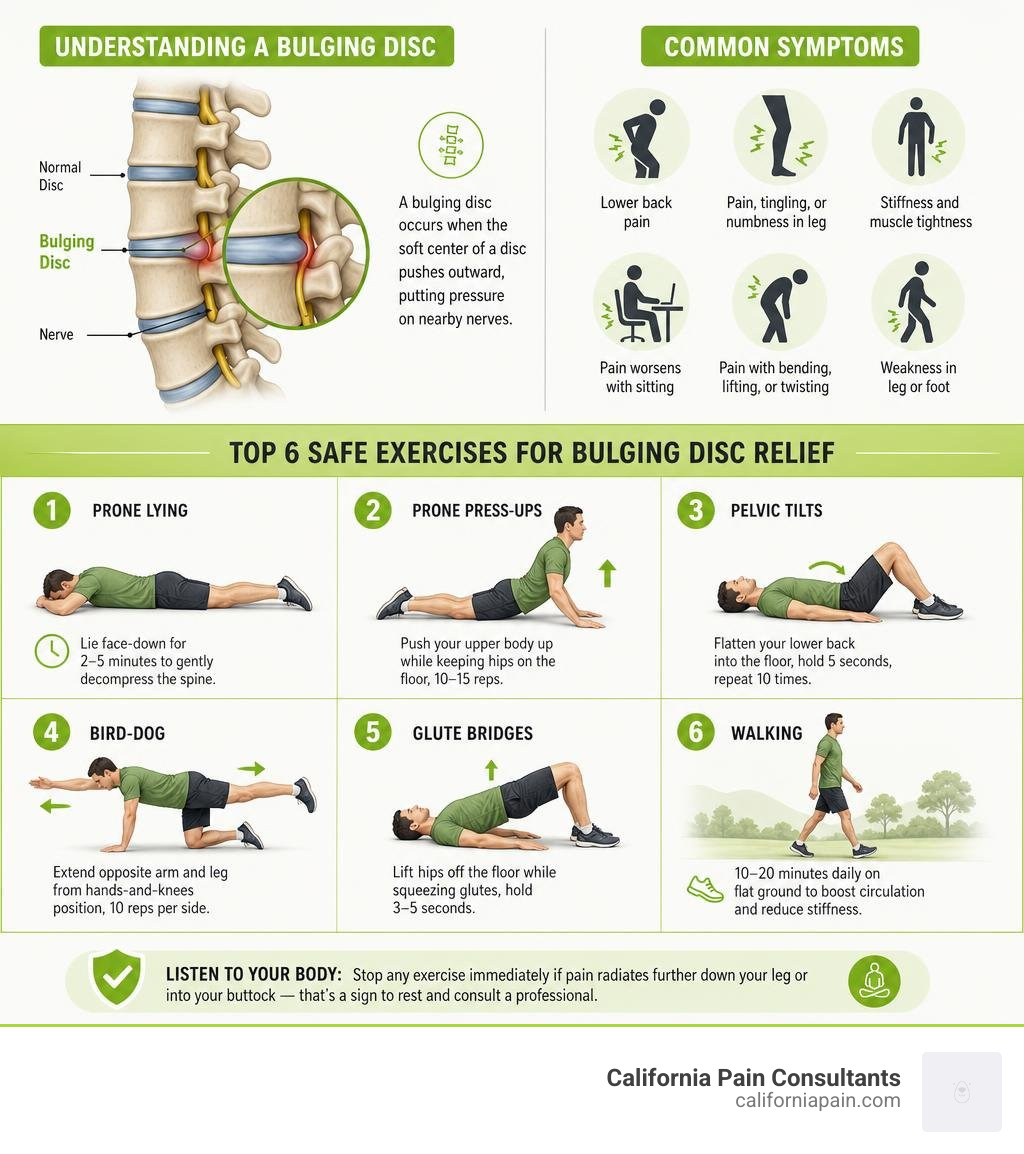
I get asked about this constantly because the internet is flooded with people claiming certain stretches will "fix" a bulging disc. They won't. But the right exercises absolutely help you function better and reduce how much your neck complains on a daily basis. Here is how to approach Neck Exercises For Bulging Discs without making things worse, based on what I have actually seen work in clinical settings over many years. A bulging disc is your intervertebral disc pushing outward beyond its normal boundary, usually from chronic wear or sudden strain. It does not necessarily mean nerve compression. Many people have bulging discs on MRI and zero symptoms. When symptoms do occur, it is typically due to local inflammation, muscle guarding, or actual nerve root irritation. The goal of exercise is not to push the disc back in. Nothing physically does that. The goal is to improve the surrounding muscular support, reduce protective spasm, and create an environment where the tissues can settle down. Your deep neck flexors and scapular stabilizers do most of the heavy lifting here. I once had a patient who came in convinced she needed aggressive stretching to decompress her cervical spine. She was doing aggressive overhead stretches and neck circles every morning. Within three weeks, her radicular symptoms had worsened significantly. We stopped all stretching immediately and focused exclusively on isometric holds and scapular retraction work. Her pain dropped substantially over the following month. The lesson was obvious in retrospect, but people rarely stop when the wrong approach makes things worse.
Chin tucks — the foundation
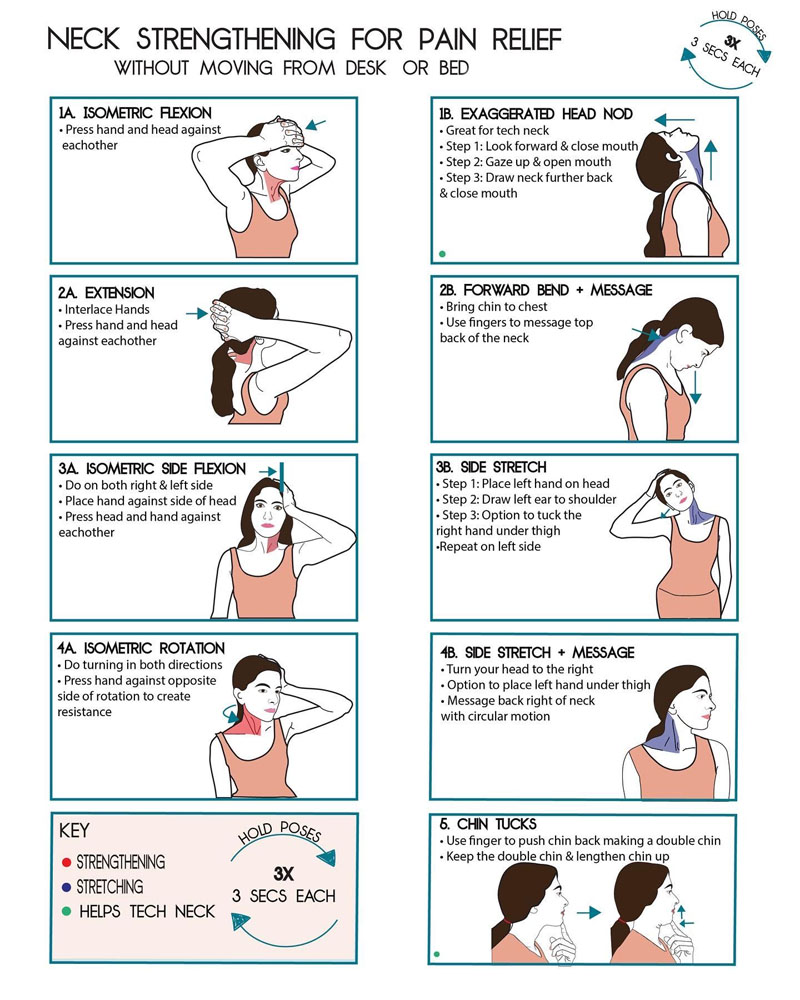
Chin tucks activate the deep cervical flexors, specifically the longus colli and longus capitis, without heavily recruiting the superficial sternocleidomastoid. Most people do these wrong by jut-ting their jaw forward or tilting their head down. The correct movement is a horizontal retraction of the head, like you are drawing your chin straight back to create a subtle double chin. Hold for five seconds, release. Start with three sets of ten repetitions, twice daily. Do not push into pain. Discomfort from muscle activation is fine. Sharp or radiating pain means you are irritating the nerve root or aggravating the disc. Back off immediately. If your neck muscles reflexively contract and lock up during the movement, your motor control pattern is disrupted from pain inhibition. In that case, start with isometric chin tucks where you gently press your head back into your hand without allowing any movement. This reduces the demand on the nervous system while still providing a strengthening signal.
Scapular retraction with resistance
Weak mid-back musculature forces your cervical spine to compensate. When your rhomboids and lower trapezius are underdeveloped, your upper trapezius and levator scapulae take over, pulling your neck into a chronic elevated position. This increases compressive load on the cervical facets and posterior disc structures. Using a light resistance band anchored at chest height, perform seated rows with emphasis on squeezing your shoulder blades together. Two to three sets of twelve to fifteen repetitions, three times per week. The resistance should be light enough that you can maintain perfect form throughout. Heavy loading here shifts the work to your upper traps and defeats the purpose entirely. Isometric holds are where most people find real relief, especially in the early stages when movement provokes symptoms. Lie on your back with your head supported. Press the back of your head gently into your hand or a pillow, engaging your posterior neck muscles without moving your head. Hold for five to seven seconds. Repeat on the sides and front. Four holds per direction, two sessions daily. This approach bypasses the painful range of motion while still building endurance in the supporting musculature. I recall a client whose scalenes would fire so aggressively during any rotational movement that his symptoms spiked after every workout. We abandoned all rotation work for six weeks and stuck exclusively to supine isometrics in a neutral position. Once his nervous system stopped perceiving the neck as a threat, we gradually reintroduced gentle rotation. The entire recalibration took roughly eight weeks. He is back to normal activity now, but that was a slow process that required patience most people do not want to give.
Get the Full Details

What to avoid completely
Aggressive neck circles and full-range cervical rotation stretches. These compress the posterior disc structures and can aggravate an already irritated nerve root. Weighted neck curls with a harness. The loads involved place enormous compressive force on healing disc tissue. Cracking or self-manipulating your neck. This is unpredictable and can destabilize an already compromised segment. Any exercise that sends pain into your arm or shoulder. That is radicular referral, and continuing through it will only prolong the issue. Sit-ups and overhead pressing. Both position your cervical spine in a vulnerable loaded state. These exercises manage symptoms and improve function. They do not reverse a structural disc problem. If you have progressive neurological deficits such as worsening weakness in your arms or legs, loss of bowel or bladder control, or severe unrelenting pain, you need immediate medical evaluation. Exercise is not the answer in those scenarios. Even with a straightforward bulging disc, approximately ten to fifteen percent of cases do not respond well to conservative management alone. If you complete six weeks of consistent, proper exercise with no meaningful improvement, stop and see a specialist. You may be dealing with a herniation rather than a simple bulge, or there may be a different anatomical issue entirely. The timeline matters too. Most people notice some reduction in daily discomfort within two to four weeks of consistent work. Full stabilization and return to unrestricted activity typically takes eight to twelve weeks. If you are not seeing any change by week four, your program likely needs adjustment rather than continued persistence. Pushing harder on the wrong exercises is counterproductive. Scaling back to isometrics and scapular work, then slowly rebuilding, is usually the smarter path.