
Neck Exercises Physical Therapy: What Actually Works
Neck Exercises Physical Therapy Done Right
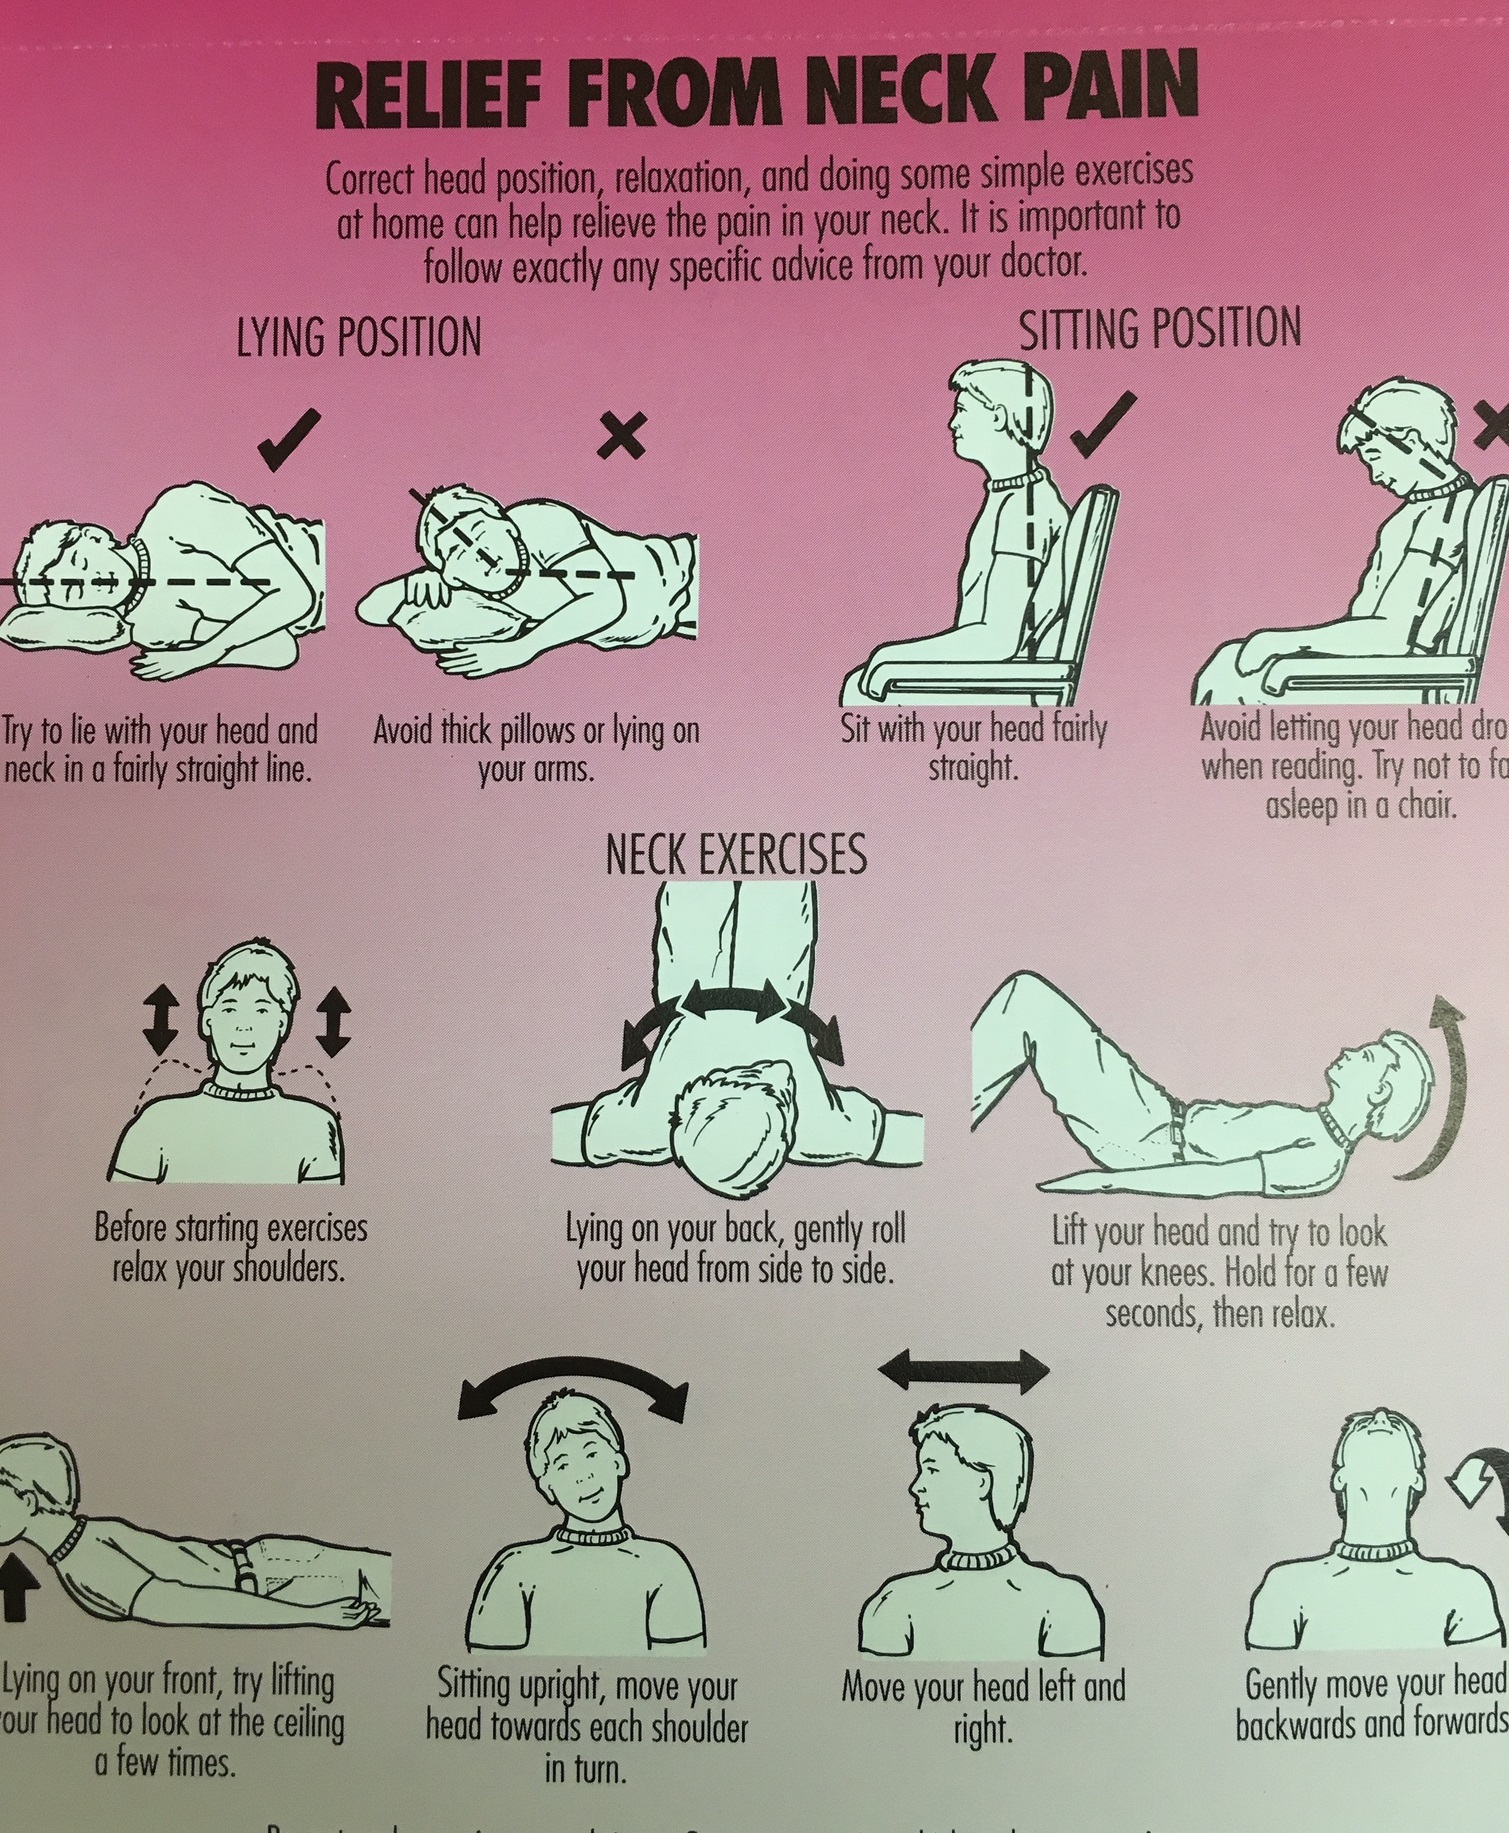
The problem with neck exercises is that most people are training the wrong muscles. They stretch their traps and roll their shoulders, then wonder why the tension never leaves. The real issue usually sits deeper. The scalenes, the suboccipitals, and the deep cervical flexors are the ones running the show when your neck stays tight. If you're only working the superficial layer, you're polishing the surface while the actual problem keeps getting worse. I had a client a few years back who came in with what looked like a textbook tension neck. Thirty-eight years old, accountant, two hours a day on his phone. We spent three weeks going through the standard protocol — chin tucks, scapular retractions, even some manual release on his levator scapulae — and he was still coming in every other day with the same pain. Turns out his thoracic spine was so kyphotic from years of slumping that every time he did a chin tuck, his entire upper back just folded forward and the movement never reached the deep flexors. He wasn't failing the exercise. The exercise was failing his posture. We spent a month first opening up his thoracic extension and pectoral region, and only then did the neck work start producing results. Once we re-established basic mobility upstream, his neck tension dropped by roughly sixty percent in about four weeks. The foundation of any effective neck rehab program is deep neck flexor re-education. This isn't about building size. It's about teaching your anterior neck muscles to actually fire before your accessory muscles take over. The standard movement here is the chin tuck. You sit or stand with your spine neutral and draw your head straight back, not down, creating a kind of horizontal retraction. You should feel this in the front of your throat, not the back of your neck. Hold for ten seconds, breathe normally, release. That's it. Three sets of eight to ten repetitions, once daily. Most people do this wrong within the first attempt because their sternocleidomastoid dominates and they just jut their chin forward slightly before pulling back. The distinction matters. If you can't feel the engagement in your deep anterior neck, you're not doing it correctly.
Supine cervical curls come next. You lie flat on your back, arms at your sides, and perform an extremely small chin tuck followed by a lift of maybe an inch or two off the surface. That's the entire range of motion. Hold for five seconds, lower slowly. Ten repetitions. Two to three sets. The reason this exercise is so specific is that it removes gravity's influence on your larger neck muscles, forcing the deep flexors to carry the load. It feels ridiculous at first. You'll think nothing is happening. That's because the scalenes and traps are supposed to stay completely inactive. If you feel your sides of neck or your trapezius engaging, you're compensating and the exercise loses its purpose.
The Stretching Component
Stretching the scalenes requires a different approach than what you'll see on YouTube. The common lateral flexion stretch where someone just tilts their head to the side isn't targeting the muscle correctly. The scalenes attach from your cervical transverse processes to your first and second ribs. A pure side bend doesn't create adequate lengthening across that entire fiber bundle. The lever arm method works better. You place your hand on the side of your head above your ear, apply gentle downward pressure toward your shoulder while simultaneously rotating your torso away from the stretched side. This creates a multi-planar stretch that engages the anterior, middle, and posterior scalene fibers. Hold for thirty seconds. Two repetitions per side. Do this after your deep flexor work when the muscles are warm, not cold. The suboccipitals respond differently. These are tiny muscles at the base of your skull, and they don't stretch well through passive movement. They respond better to direct pressure and isometric release. Press your thumbs into the firm area just below your skull where the neck meets the head. Apply moderate pressure while slowly tilting your head forward and back within a pain-free range. Thirty seconds per point. Three points per side. This produces a Golgi tendon organ response that actually inhibits the muscle, which is different from stretching it in the traditional sense.
Get the Full Details
Pectoral work matters more than most people expect. Your pec minor attaches to the coracoid process of your sculpula and pulls it forward when tight. This forward translation of the scapula is what creates the rounded shoulder posture that then forces your neck to compensate. A doorway stretch — forearms on the doorframe at shoulder height, gentle forward lean — held for forty-five seconds, three repetitions, two to three times per day. You should feel this in the front of your shoulder, not your neck. If your neck is taking the sensation, you're arching your back too much and losing the stretch where it matters.
Additional Supporting Work
Scapular retraction and depression exercises form the supporting structure. Retraction means pulling your shoulder blades together. Depression means pulling them down toward your back pockets. Most people with neck tension have scapulae that sit elevated and protracted, which means their traps are constantly engaged and their rotator cuff is in a disadvantaged position. This cascades upward into the neck. Prone Y raises are one of the better exercises here. Lie face down on the floor or on an incline bench with your arms extended overhead in a Y position. Lift your arms off the surface by depressing and retracting your scapulae. The movement should be small. Four to six inches of lift maximum. Ten repetitions. Two to three sets. The focus is on the lower trapezius and rhomboids, not on how high you can lift your arms. If you're shrugging your shoulders as you lift, you've lost the target muscle and are just reinforcing the compensatory pattern you're trying to fix. Isometric neck resistance work rounds out the program. Press your palm against your forehead and push your head forward into your hand while your hand resists. No movement should occur. Hold for ten seconds. Repeat against the sides and the back of the head. Four directions, four holds each. This builds endurance in all planes without the shear forces that come with dynamic movement. Important for people who have disc issues or joint instability where rotation under load might be problematic.
Frequency and Progression
Deep neck flexor work should be done daily. Every day. This isn't optional. The neuromuscular re-education takes consistent repetition, and skipping days resets the adaptation process. Start with one set and add a second set after two weeks if the first set feels easy. The chin tuck hold should progress from ten seconds to fifteen seconds over four to six weeks. The supine curl should progress from five-second holds to ten-second holds over the same period. Scalene stretching can be done two to three times per day, especially during the first phase of treatment when tension is high. As the neck improves, you can drop to once daily. Suboccipital release can be done daily as well, and some people find relief from a single session before bed. Scapular work should be done three to four times per week, alternating with the daily flexor work. The total time investment for a complete session is about twelve to fifteen minutes. Twenty minutes if you include the pectoral stretching and additional work. There's no excuse for not doing this consistently. The people who don't improve are the ones who do it for three days, stop for two weeks, then complain the exercises didn't work. Neuromuscular re-education isn't a one-session intervention. It's a daily practice over weeks and months.

Common Mistakes
The most common error I see is pushing through pain. Mild discomfort during a new exercise is normal. Sharp pain, radiating pain, or pain that increases during the movement is not. If your chin tuck produces a headache or dizziness, you're either engaging the wrong muscles or there's an underlying issue that needs evaluation before you continue. Same with the supine curl. If you feel tingling in your fingers, stop immediately. That's a nerve irritation signal, not a muscle engagement signal. Another mistake is progressing too fast. People add resistance bands or weighted collars to chin tucks after a few weeks because they think more load equals faster results. This is backwards. The deep flexors are small stabilizer muscles. Loading them prematurely reinforces the compensatory pattern you're trying to eliminate. Add resistance only after you can perform the bodyweight version cleanly for three sets of ten with no substitution from larger muscles. That usually takes six to eight weeks minimum for most people.
When This Doesn't Work
Neck Exercises Physical Therapy will not solve every type of neck problem. If your neck pain originates from a herniated disc compressing a nerve root, from facet joint arthropathy, from cervical myelopathy, or from a structural abnormality like Klippel-Feil syndrome, these exercises won't address the underlying cause. They might help manage symptoms, but they won't fix the problem. Imaging and a proper diagnosis are necessary before committing to an exercise-based protocol if your symptoms include neurological deficits, progressive weakness, or pain that doesn't respond to conservative management after six to eight weeks. Vertebral artery insufficiency is another contraindication that people rarely consider. If you have any history of posterior circulation issues, extreme neck extension or rotation should be avoided entirely. Some of the stretches I mentioned involve rotational components, so if you have any vascular concerns, stick to the isometric and flexor work and get clearance from a physician first. The honest assessment is that most neck tension problems resolve with consistent, correct exercise within six to twelve weeks. A significant minority don't, and those cases usually involve overlooked structural issues or compensatory patterns that originated somewhere other than the neck itself. The program I've described is effective for the majority of mechanical neck tension cases. It's not a cure-all. It requires daily effort, correct form, and patience. The people who get results are the ones who treat it like a daily hygiene practice, not a weekly chore.


