Understanding Collapsed Lungs from a Physiology Standpoint
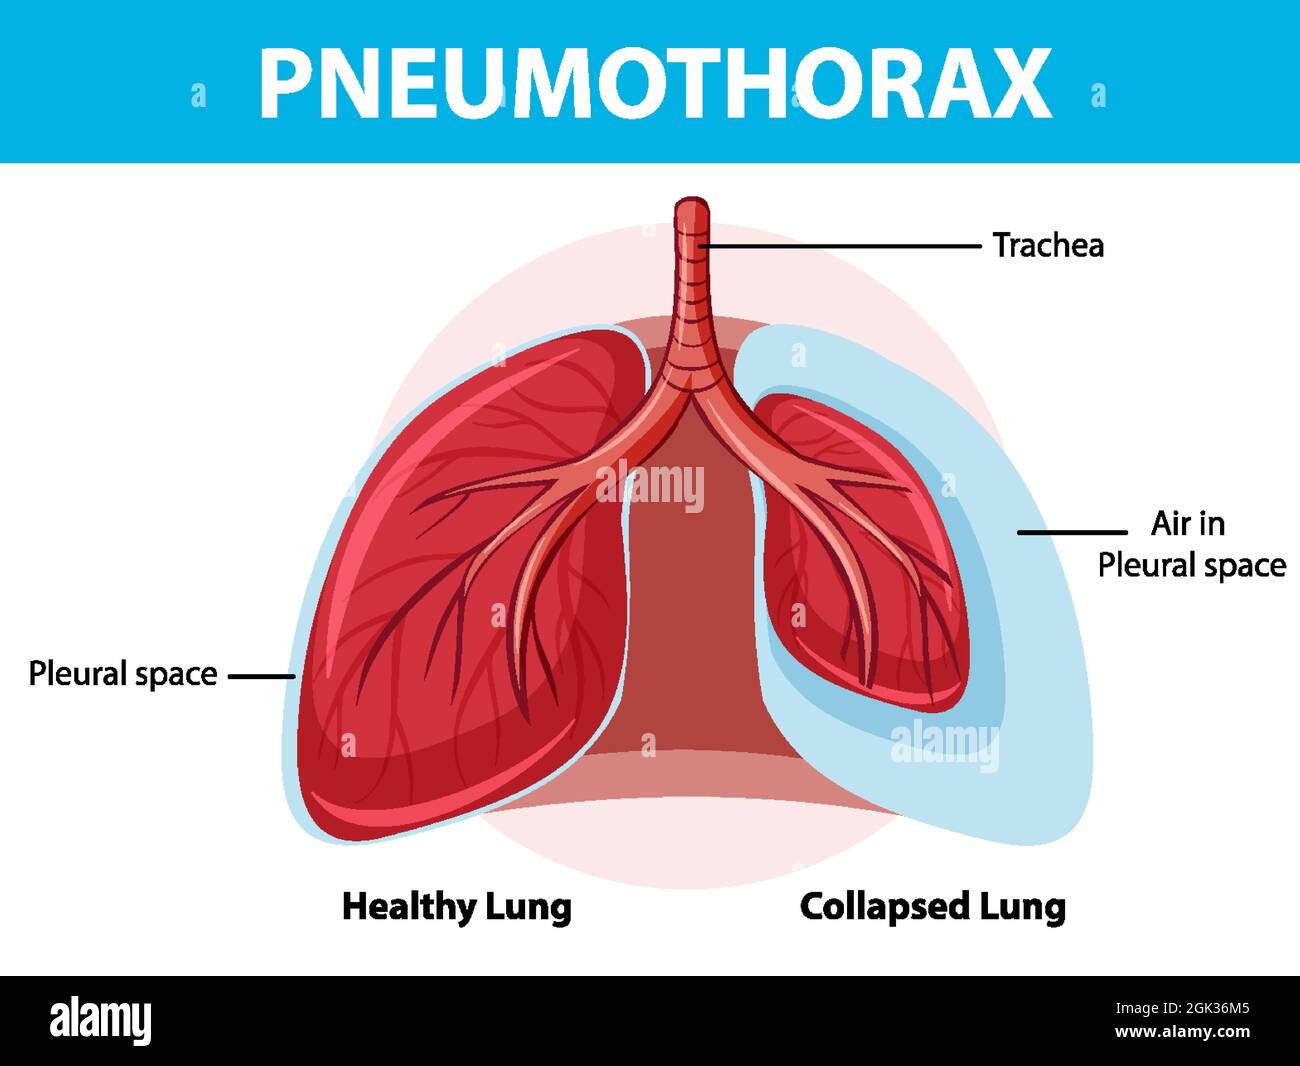
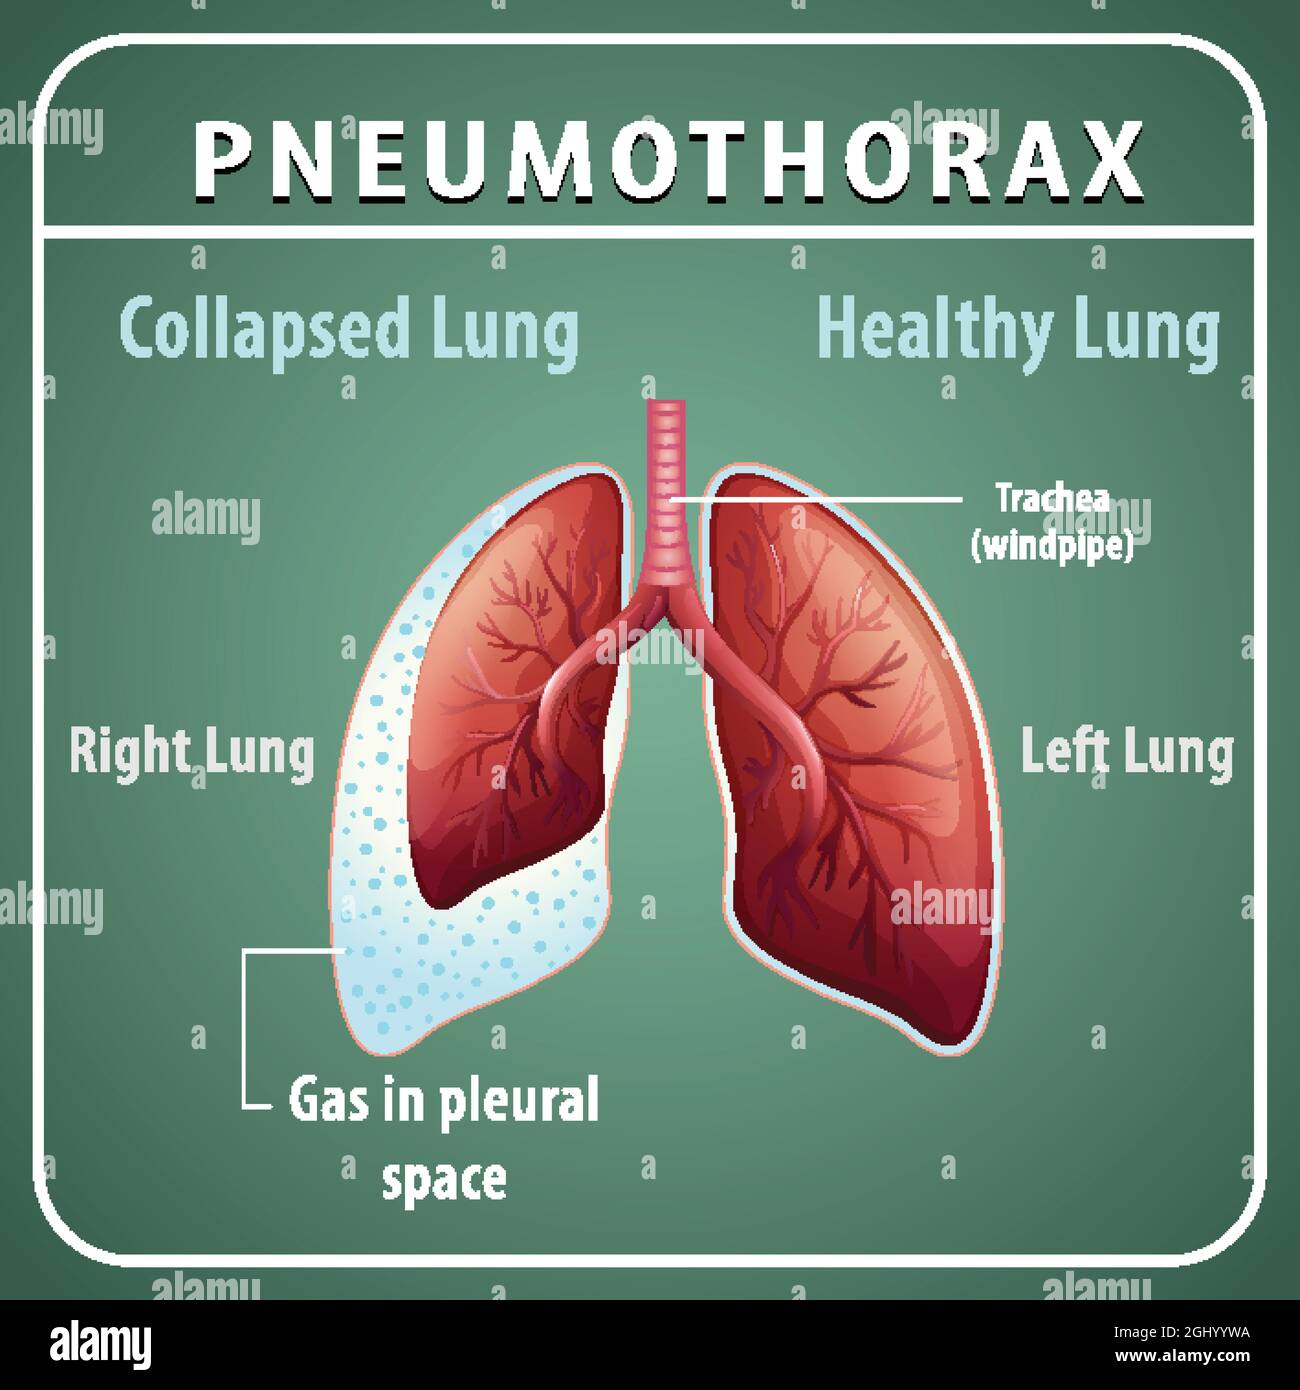
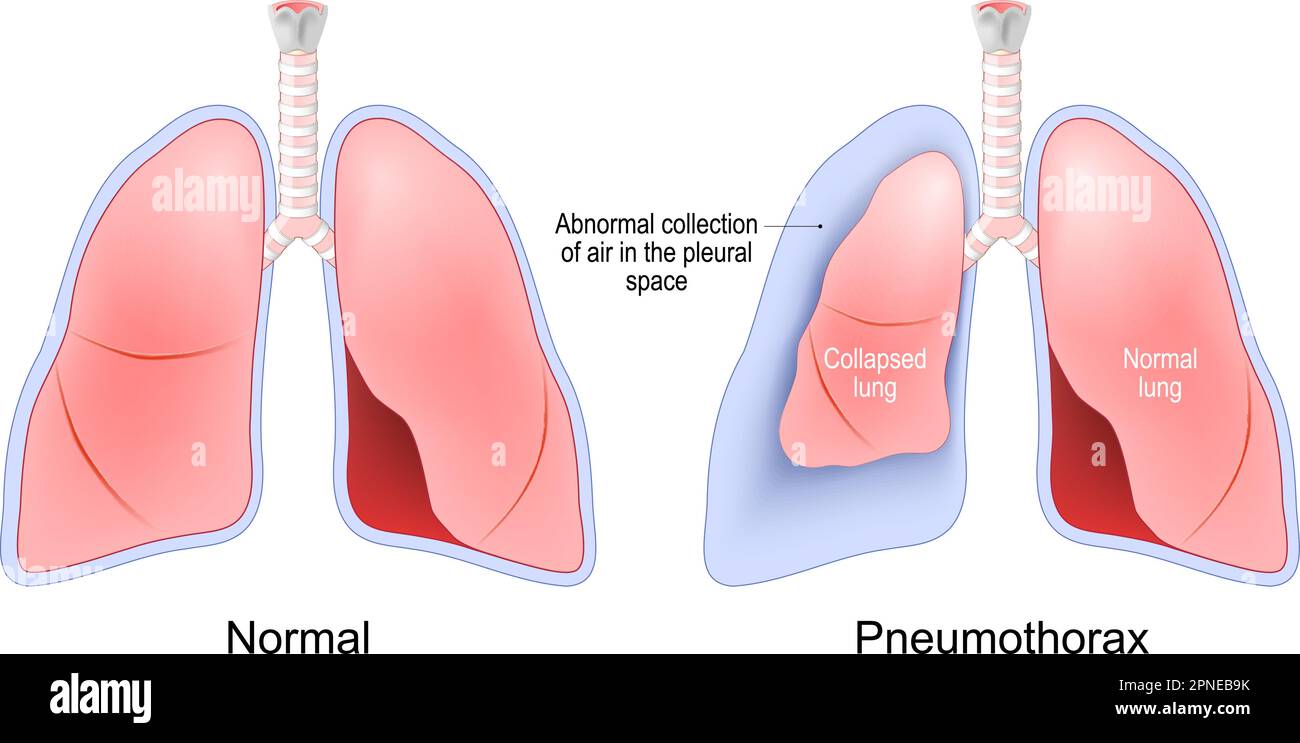
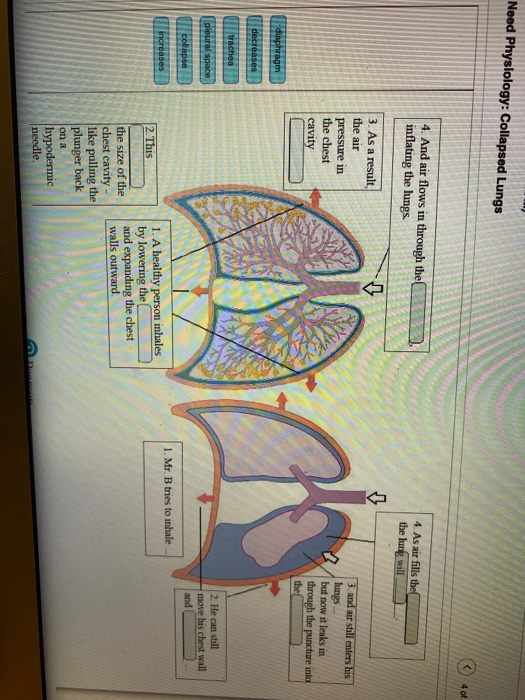
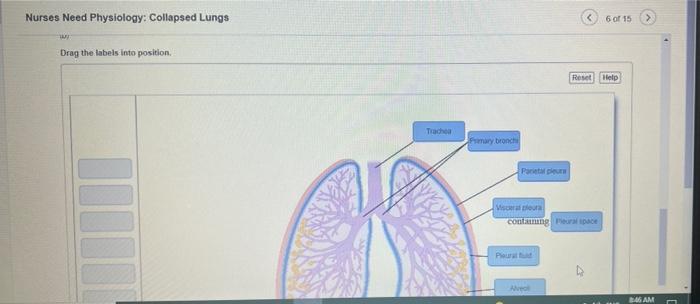
A collapsed lung, medically called a pneumothorax, happens when air gets into the pleural space between the lung and the chest wall. That air accumulation creates pressure that pushes against the lung and prevents it from expanding properly during inhalation. The physiology behind this is straightforward but the clinical presentation can range from barely noticeable to immediately life-threatening depending on how quickly air enters that space and how much volume is involved. The pleural cavity normally exists under negative pressure, usually around minus 5 to minus 8 cm H2O at rest. This negative pressure keeps the lung parenchyma adhered to the chest wall. When that seal is broken, whether from a ruptured bleb, a penetrating chest injury, or a medical procedure complication, atmospheric pressure enters the space and the lung collapses inward due to its own elastic recoil. The degree of collapse depends on the size of the defect and whether air continues to enter with each breath. I dealt with a case last year where a patient had what initially looked like a small apical pneumothorax on imaging. Standard teaching would suggest observation or perhaps a small-bore chest tube. But here's the thing nobody warns you about: when you have a patient with underlying emphysema and bullous disease, even a seemingly modest pneumothorax can progress rapidly because those bullae act as one-way valves. Air keeps getting trapped in the pleural space with each breath and can't escape. We ended up placing a 14 French chest tube and the lung still didn't re-expand for about 48 hours because the underlying lung tissue was too diseased to fill the space properly. In those situations, you're not really treating the pneumothorax anymore, you're managing a persistent air leak while waiting for the visceral pleura to heal on its own.
Tension pneumothorax represents the extreme end of this physiology. Air enters the pleural space through a one-way valve mechanism but cannot exit. Pressure builds with each inspiratory effort, progressively collapsing the affected lung, shifting the mediastinum toward the opposite side, and ultimately compressing the vena cava. This reduces venous return to the heart and can cause obstructive shock within minutes. The classic signs are respiratory distress, tracheal deviation away from the affected side, decreased breath sounds, hypotension, and distended neck veins. I've seen this happen during positive pressure ventilation in the ICU when a barotrauma tear developed into a tension physiology. The patient's blood pressure dropped from 120 over 70 to 75 systolic in under three minutes. Needle decompression at the second intercostal space midclavicular line or the fifth intercostal space anterior axillary line is the immediate intervention, followed by a proper chest tube placement. The diagnostic workup typically starts with a chest X-ray in the upright position. A thin white line representing the visceral pleura becomes visible with an absence of lung markings peripheral to that line. This is the pleural edge. If the diagnosis is uncertain or the patient is unstable, a bedside ultrasound is actually more sensitive than an X-ray for detecting pneumothorax. The presence or absence of lung sliding on ultrasound is highly accurate. You should also be aware that supine portable X-rays, which are common in critically ill patients, can miss up to 50 percent of small pneumothoraces. The deep sulcus sign, where the costophrenic angle appears abnormally deep and radiolucent on a supine film, is a useful clue in those cases. Treatment selection depends heavily on the size of the pneumothorax and the patient's clinical status. For a small primary spontaneous pneumothorax in a stable patient, observation with supplemental oxygen is often sufficient. The oxygen helps accelerate the resorption of pleural air by creating a nitrogen gradient that promotes diffusion back into the bloodstream. Studies show this can reduce the time to resolution by roughly half compared to room air alone. For larger pneumothoraces or symptomatic patients, needle aspiration followed by chest tube insertion is the standard approach. Chest tube sizes generally range from 8 to 14 French for simple pneumothoraces and up to 28 to 32 French for traumatic or hemothorax cases.
One counter-intuitive point that comes up frequently: high positive end-expiratory pressure from mechanical ventilation can actually worsen a pneumothorax by keeping the alveolar-pleural communication open. In ventilated patients with a known or suspected pneumothorax, I always check for a chest tube before increasing PEEP levels, even if the initial X-ray showed only a tiny air collection. The dynamics change completely under positive pressure ventilation. Recurrent pneumothorax is a real concern, occurring in approximately 30 to 50 percent of patients after a first episode. Surgical intervention with VATS, which stands for video-assisted thoracoscopic surgery, combined with pleurodesis or mechanical pleurectomy significantly reduces recurrence rates to around 5 percent. The surgery typically involves resecting apical bullae and creating inflammation on the pleural surface so that the lung adheres permanently to the chest wall. The main limitation with conservative management is that it only works for primary spontaneous pneumothoraces in otherwise healthy patients with small air collections. Secondary spontaneous pneumothoraces, which occur in patients with known lung disease like COPD, cystic fibrosis, or pneumonia, have higher mortality rates and lower success rates with observation alone. These patients generally require more aggressive intervention even for smaller pneumothoraces because their baseline respiratory reserve is already compromised. Catheter-directed water seal drainage with suction is often preferred over simple underwater seal in these cases, though the evidence base for routine suction use remains mixed. Some studies suggest it doesn't significantly improve outcomes and may actually increase pain and air leak duration.
Get the Full Details
If you're looking for detailed physiological references, the gold standard textbooks on critical care medicine and thoracic surgery cover this extensively. I'd recommend checking Elsevier's current guidelines and the British Thoracic Society's pneumothorax management document for the most up-to-date protocols. These sources provide the most reliable information if you need Physiology Collapsed Lungs details for clinical decision-making or academic purposes.