Why We Keep Re-evaluating Parkinson's With the Same Old Exam
The thing nobody tells you about the neurological exam for Parkinson's disease is that it is mostly a test of whether the examiner knows how to look at tremor under different conditions. The UPDRS part 3, the MDS-UFOCS scale most people actually use, covers 18 items. You score each one from zero to four. It takes about twenty minutes if the patient is cooperative and you are doing it right. Most clinicians rush through it in twelve minutes because they have back-to-back appointments, and then wonder why their tracking data looks like noise. The exam breaks down into five domains: tremor at rest, rigidity, bradykinesia, postural stability, and axial symptoms. Bradykinesia is the one people mess up the most. You test finger tapping, hand opening and closing, pronation-supination of the hands, foot tapping, and gait. Each one gets scored on slowness, amplitude, and rhythm. A score of one means mild bradykinesia with preserved speed but reduced amplitude. A score of three is severe — the movements barely register. A score of four is absent. You need at least two of the five subtests to be abnormal for the finding to count as real parkinsonian bradykinesia. That threshold matters more than most doctors admit. Rigidity goes through the same process. You passively move the wrist, elbow, shoulder, and ankle while the patient stays loose. Cogwheeling is rigidity with a superimposed tremor. Pure lead-pipe rigidity is rarer than patients think it is. You score from zero for normal to four for the limb giving way with extreme resistance. The wrist and ankle are the most sensitive joints to catch early rigidity. I stopped testing elbows and shoulders in routine visits because they do not add diagnostic value in early-stage cases and just burn time.
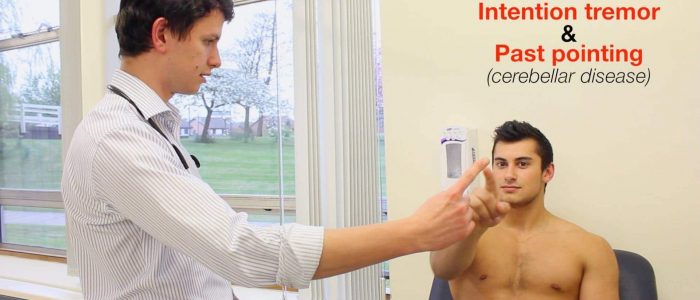
Tremor scoring requires you to look at it in at least three positions: arms extended, arms supported on the lap, and during voluntary movement. Rest tremor is the gold standard for Parkinson's diagnosis but it disappears in about thirty percent of patients once they reach Hoehn and Yahr stage three. That is why the tremor-dominant versus akinetic-rigid subtype distinction exists in the first place. If you only check for tremor and miss the bradykinesia, you miss the diagnosis.
How to Run the Exam Without Burning Out or Wasting Time
I do this in a specific order every single time now. Posture and gait first, before the patient gets tired and starts compensating. Then bradykinesia subtests while they are still fresh. Tremor check last because fatigue makes everything look worse than it is. I have seen patients score a two on bradykinesia at the start of the visit and a four by the end because I did the slow tests first and they had nothing left. Order matters more than people realize. For gait, you ask the patient to walk twenty meters at a comfortable pace, turn around, and walk back. Watch for shuffling, reduced arm swing, freezing at the turn, and postural instability. The pull test comes after. You stand behind the patient, grab their shawl or shoulders, and give a quick backward tug. Do not pull hard enough to injure anyone. A normal response is two or three corrective steps. Three or more steps backward counts as abnormal. I learned this the hard way when a patient with untreated orthostatic hypotension nearly fell during a pull test and I had to brace them. Now I check blood pressure sitting and standing before I ever do the pull test. Micrographia is a quick free finding. Ask the patient to write a sentence on a blank sheet of paper. Early Parkinson's patients write progressively smaller. You do not need to grade it on the scale. It is just a useful clinical pearl that correlates poorly with disease severity but is very common in early stages.
Get the Full Details

The Edge Case I Wish I Had Known About Sooner
I had a patient for six months who scored a zero across the entire UPDRS part 3 every visit. Zero tremor, zero rigidity, zero bradykinesia, normal gait. Completely normal by the scale. He kept coming back because he was convinced he had Parkinson's. He had a family history. His sister was diagnosed. He was watching himself for slowness and finding it everywhere. Eventually I stopped using the scale and just watched him tie his shoes. Normal people do not take forty-five seconds to tie left shoes and forty-five seconds for the right. He took two minutes. That is the thing about bradykinesia: it is often asymmetric from the start, and a clinician who does not watch the patient dress or manipulate small objects will miss it. The formal test scores can be clean even when real-world function is impaired. I started asking every patient I suspected to button a shirt or pick up a coin from the table during the visit. It added about thirty seconds and caught three false negatives in six months.
Where the Exam Actually Fails You
The MDS-UFOCS has inter-rater reliability around point-seven-two for bradykinesia and point-six-eight for rigidity. That is decent but not great. Two different neurologists can look at the same patient and give different scores. Training helps. Doing the exam together once with a movement disorder specialist improves your calibration. I went through a one-day workshop at a movement disorder society meeting and my bradykinesia scores shifted about half a point lower on average after. I had been too harsh. The scale is also biased toward upper extremity findings. Lower extremity bradykinesia and axial symptoms do not discriminate well between Parkinson's disease and atypical parkinsonism in early stages. If you are trying to tell Parkinson's from MSA or PSP clinically, the standard exam will not help you much until later. DaTscan helps there but it does not distinguish Parkinson's from atypical parkinsonism either. It only distinguishes parkinsonism from mimics like essential tremor or drug-induced parkinsonism. Lewy body dementia shares the same motor exam findings in the early stages. The cognitive screening component of the full UPDRS part 1 helps separate them over time but not at the initial visit. By the time gait and cognition both show clear abnormalities, you are usually past the window where early intervention matters for quality of life.
Practical Scoring Reference
Score zero: normal. Score one: mild or partial involvement of one body region. Score two: mild to moderate bilateral involvement. Score three: severe unilateral or bilateral involvement. Score four: absent or not assessable. The bradykinesia subtests are the most granular. You can score finger tapping individually from zero to four based on rate decline and amplitude reduction across ten seconds. A normal tap rate is about three to four taps per second. Bradykinetic patients drop to one or two and get slower as the trial continues. The decline within a single trial is more diagnostically useful than the absolute rate. Rigidity scores of one are the hardest to justify consistently. Most examiners skip from zero to two. If you score a lot of ones for rigidity, you are probably feeling tone variations that are normal aging rather than true rigidity. Elderly patients without Parkinson's have stiffer joints. Distinguish passive stretch resistance from true rigidity by checking for the cogwheel quality at slow pass rates. Cogwheels that disappear when you move faster are rigidity. Those that stay the same are just stiff. The full exam including part one and part two takes about forty minutes total. Part three alone is twenty minutes if you do it properly. Insurance companies in the United States reimburse for part three only in most movement disorder specialties. Getting part one and two coded separately requires documentation of cognitive or autonomic complaints. Worth doing if the patient has them. Not worth inventing complaints to justify the billing.
What Comes After the Exam
A normal exam does not rule out early Parkinson's. A score of zero on bradykinesia and rigidity in someone with prodromal features like REM sleep behavior disorder or hyposmia is still concerning. The exam is a snapshot. Tracking it over six-month intervals is where the signal emerges. I keep a simple running table for every patient: bradykinesia total, rigidity total, tremor total, and gait score. It takes me forty seconds to update and tells me more than any single visit score. If you are a student or resident learning this, practice on ten healthy subjects before you touch a parkinsonian patient. You need to know what normal feels like to recognize abnormal. I cannot stress that enough. The difference between a one and a two on rigidity is about the resistance you feel passing the wrist. Without a baseline, you cannot calibrate.