What Actually Happens When You Start NDT
Neurodevelopmental Therapy for stroke patients is built on the Bobath concept, which means it focuses on how the nervous system reorganizes after injury. The core idea is that normal movement patterns can be retrained by inhibiting abnormal tone and facilitating correct positioning. I have worked with dozens of stroke survivors over the years, and the difference between a therapist who understands NDT and one who just follows a textbook routine is enormous. Most people skip the why and jump straight into exercises. That approach rarely works well. The therapy targets postural control, balance, weight shifting, and selective motor control. It is not just about strengthening weakened limbs. The real work happens in teaching the patient how to use their remaining function intelligently. Abnormal synergies develop quickly after a stroke. If you do not address them early, they become the new normal. Once that pattern locks in, unlearning it takes considerably more time than preventing it in the first place.
Neurodevelopmental Therapy Exercises For Stroke Patients: The Practical Approach
Here is how I break down a typical NDT session. The first ten minutes are always assessment. I watch how the patient sits, stands, and shifts weight before touching them at all. What you see in those first few minutes tells you far more than any standardized score. A patient who cannot maintain midline alignment while sitting will not suddenly manage it during walking practice. Fix the foundation first. The exercises themselves revolve around key points of control. These are specific areas of the body where handling can most effectively influence tone and movement quality. The most important ones are the pelvis, the thorax, the scapula, and the foot. Handling at the pelvis during standing practice, for example, can reduce extensor thrust in the lower extremity almost immediately if done correctly. I had a patient named Richard who presented with severe extensor spasticity in both legs after a left MCA stroke. Standard strengthening did nothing for him. We spent three weeks working purely on pelvic placement and weight distribution. By week four, his extensor tone dropped enough that he could take actual steps with a walker. That took longer than some protocols promise, but it stuck. Role reversal exercises are another cornerstone of NDT work. The affected side often lacks any independent movement, so the therapist moves the limb through functional patterns while the patient actively participates mentally. This is not passive range of motion. The patient has to engage their attention on the movement being facilitated. Studies on motor imagery support this connection. When the patient mentally reheeses the movement simultaneously, cortical reorganization happens faster than with passive motion alone.
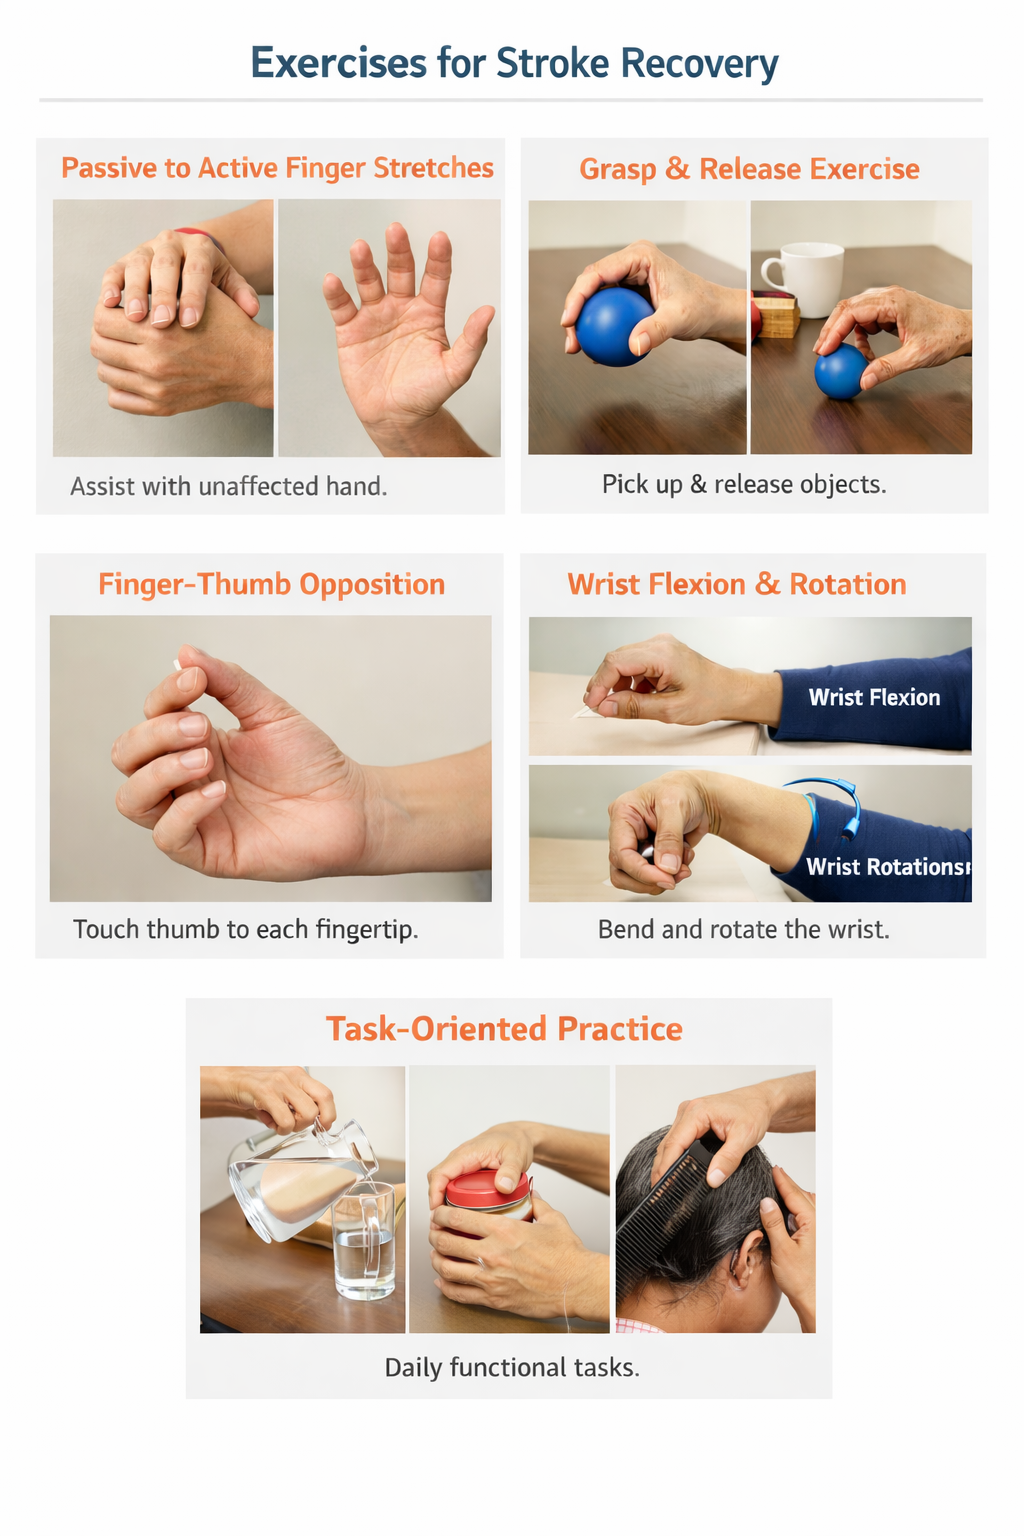
Inhibitory techniques address abnormal tone directly. Sustained stretch, quick ice application, and rhythmic initiation are the tools I reach for most often. Prolonged static stretching of a spastic muscle does not reliably reduce tone long-term. The evidence for that is weak. What works better is combining sustained positioning with active attempts at counter-movement. Ask the patient to gently push against the spastic pattern while you maintain the inhibited position. That produces more lasting change than either action alone. Weight bearing through the affected upper extremity is one of the most underrated interventions in early stroke rehab. I worked with a woman who had moderate right-sided weakness and a very guarded shoulder. Her therapist kept avoiding weight bearing because of subluxation concerns. Instead, we used a rolled towel under her hand and guided her into partial weight bearing while she sat at a table. She started with thirty seconds, three times a day. Within two weeks she was tolerating forty-five seconds with good control. Shoulder pain decreased. Her hand opened more easily afterward. Weight bearing also provides proprioceptive input that helps the brain remap the affected limb. Functional task practice within the NDT framework means embedding therapeutic principles into everyday movements. Reaching for a cup, transferring from bed to chair, stepping over a threshold. Each of these activities becomes an opportunity to reinforce proper alignment and inhibit compensatory strategies. I once had a patient who kept hiking her shoulder to reach forward. We spent two sessions just practicing reaching while keeping the scapula depressed and protracted. That small correction reduced her energy expenditure by roughly a third during all subsequent ADL practice.
Get the Full Details
Where NDT Falls Short
I need to be straightforward about the limitations. NDT is not appropriate for every stroke patient. Those with severe cognitive impairment often cannot engage with the mental component required for effective role reversal and motor imagery. Without that engagement, the therapy loses much of its benefit. In those cases, constraint-induced movement therapy or task-oriented training with heavy repetition may yield better outcomes. Advanced spasticity that has not been managed pharmacologically will fight against any NDT intervention. Botulinum toxin injections paired with therapy can open a window where NDT techniques become effective again. I have seen patients plateau for months simply because their tone was never addressed before therapy began. Checking whether spasticity is being managed adequately should happen before committing to an NDT-only approach. The evidence base for NDT is mixed. Some systematic reviews show modest benefits while others find little advantage over standard care. The variation likely comes down to therapist skill and patient selection. NDT is a highly technique-dependent approach. Two therapists trained in the same method can produce very different results because the hands-on component requires significant clinical judgment. That is why finding a therapist with demonstrated NDT certification and extensive stroke experience matters more than simply choosing any facility that advertises the method.
What to Expect Over Time
Progress in NDT is usually gradual and non-linear. The first measurable changes often appear in tone reduction and basic weight shifting rather than in independent movement. I typically tell families to expect visible improvement in the three-to-six-week range if the patient is medically stable and attending therapy three to five times per week. After that, gains tend to slow unless the complexity of tasks is increased intentionally. Home exercise compliance is where most programs lose momentum. The therapist can only work with the patient for an hour or two a day. The remaining hours matter more for neuroplasticity. Simple home programs should include maintained positioning, assisted weight bearing, and guided weight shifting practice. Keeping a log of daily practice duration and quality helps identify when progress stalls. Often the issue is not the therapy itself but inconsistent practice outside the clinic. I keep a short list of exercises that translate well to home practice. Supine hip abduction with slow controlled lowering. Seated weight shifting from side to side with trunk rotation toward the affected side. Standing march practice with pelvic stability maintained. Each of these targets a specific NDT principle and requires no special equipment. The trick is doing them with correct alignment rather than speed or repetition count. Fifty reps with poor form reinforces the wrong pattern more effectively than it helps the right one.
Putting It Together
Neurodevelopmental Therapy for stroke patients works best when the therapist prioritizes quality of movement over quantity and addresses tone before demanding complex motor output. It is not a quick fix and it does not fit every case. The patients who benefit most are those who can engage cognitively, have manageable spasticity, and have consistent access to skilled therapy. If you are evaluating options for someone recovering from stroke, ask the therapist specifically about their NDT training level, their approach to abnormal tone, and how they integrate functional task practice. Those answers will tell you more than any certificate on the wall.




