What Neurofeedback Actually Looks Like in a Practice
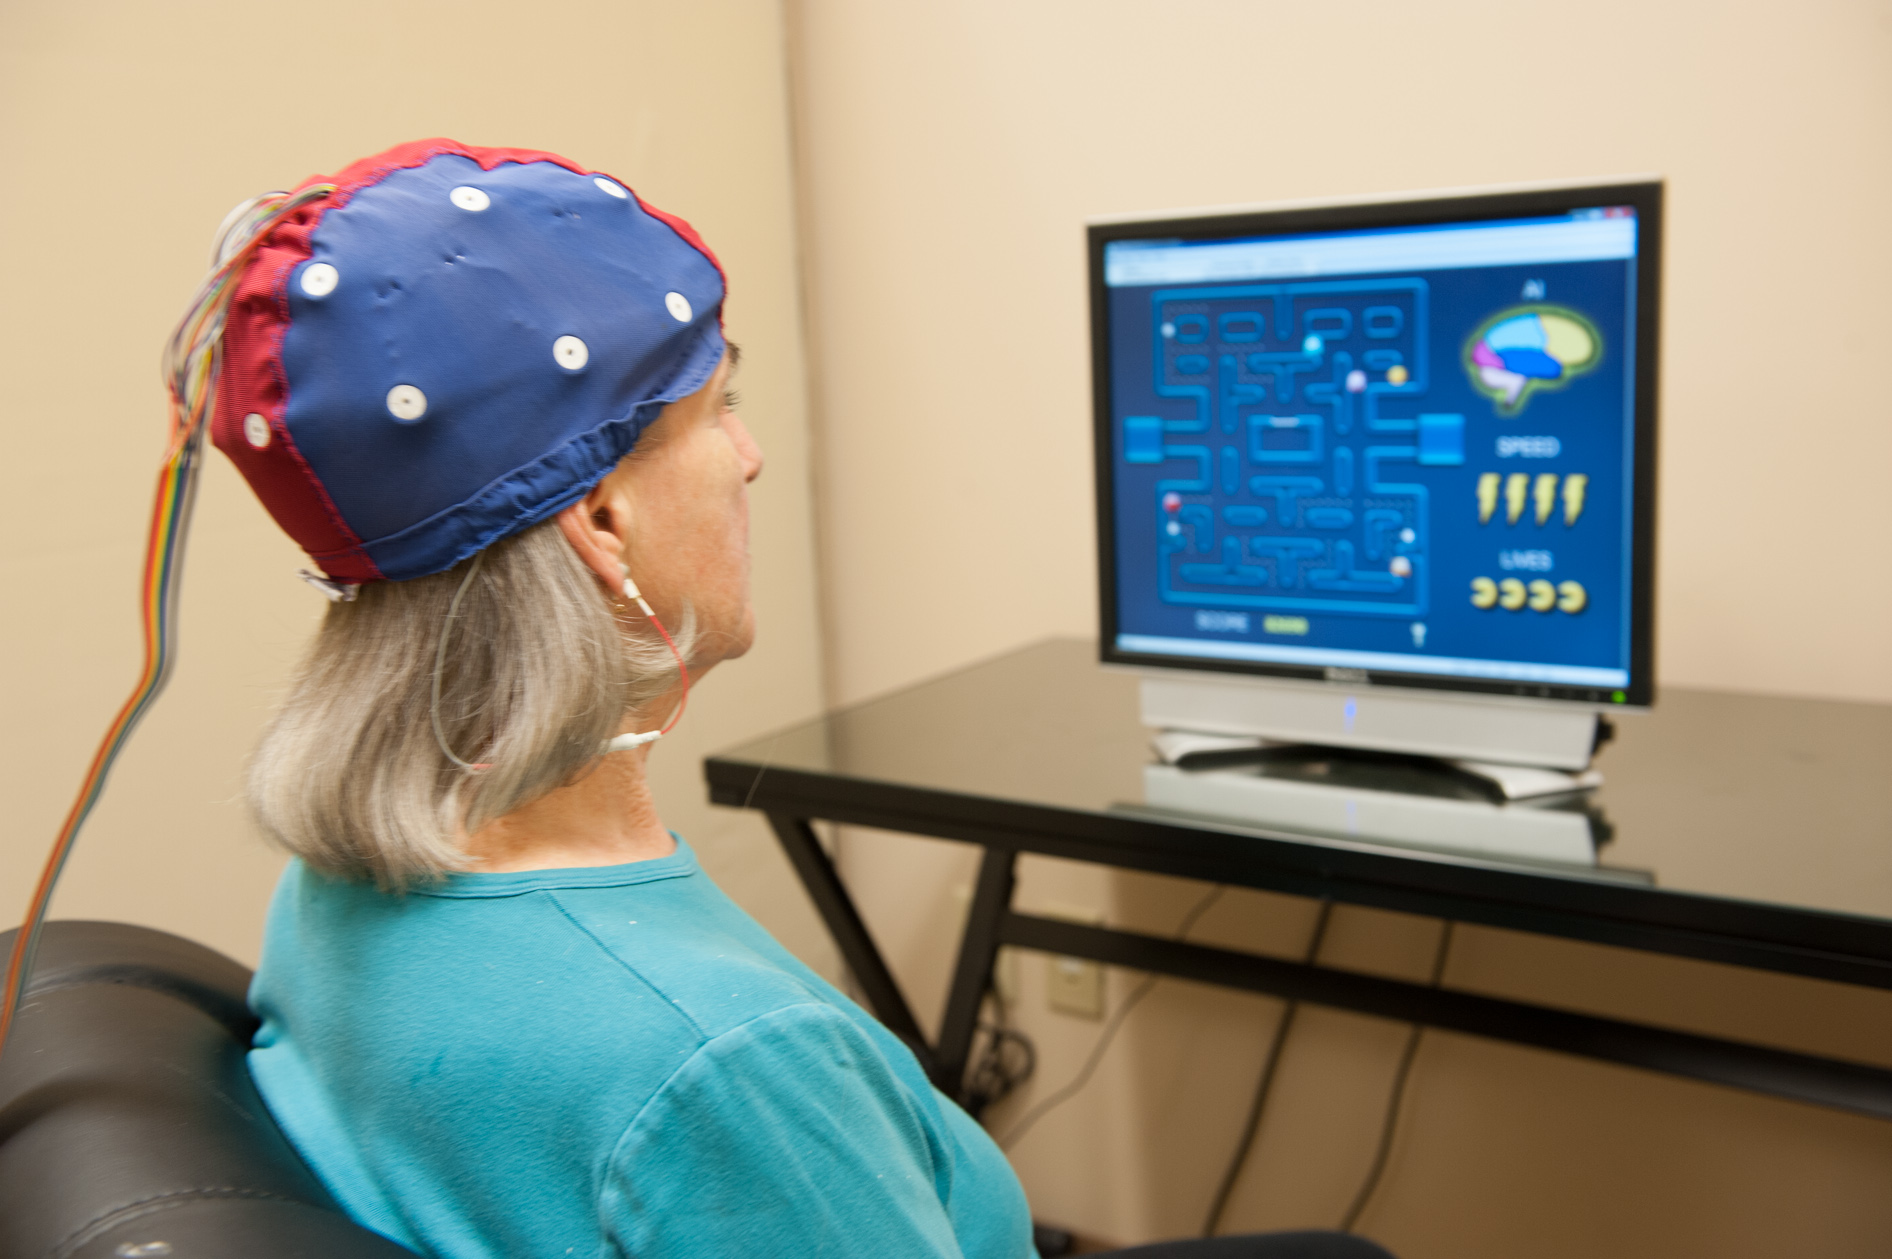
The first thing you will notice when you start buying into Neurofeedback Training For Therapists is that the marketing material says one thing and the equipment does another. Most entry-level systems advertise themselves as plug-and-play. They are not. A good protocol will save you a lot of time, but you still need to understand what you are looking at on the EEG display or you will spend months chasing artifacts and calling it progress. You have three realistic paths when you start this out. The first is a proprietary all-in-one system like those from NeuroStar, BrainWave, or similar brands that bundle the amp, software, and protocol builder. The second is a standalone amplifier with third-party software like OpenVibe, EEGLAB, or AcqKnowledge paired with a qEEG database. The third is a cloud-based platform that handles everything remotely, which is the one most people actually want but rarely get right in their first year. I went with a mid-range proprietary system first. It had a decent library of protocols and the impedance management was automated. The problem was the software locked me into their protocol stack, and I could not easily export raw EEG data when a case needed something custom. After six months I moved to a standalone amp running custom EEG pipelines. That was a much harder week of setup, but it freed me from their closed ecosystem entirely.
Here is the technical breakdown you actually need:
- Electrode placement: Stick with the 10-20 system for consistency. Standard locations like Fz, Cz, Pz, and the lateral sites are where most training protocols live. If your therapist software lets you customize montages, do not skip that step.
- Impedance targets: Keep impedances below 5 kOhms when possible, and below 10 kOhms as a hard ceiling. Anything higher and your signal quality degrades fast enough that you cannot trust what the feedback loop is measuring.
- Sampling rate: Minimum 256 Hz for clinical work. 512 Hz is better if your amplifier supports it. Lower rates introduce aliasing artifacts that mess with frequency band calculations.
- Feedback modality: Audio and visual feedback are standard. Visual graphs are good for initial patient education. Audio-only feedback can be effective and reduces screen fatigue during long sessions.
Setting Up Your First Protocol
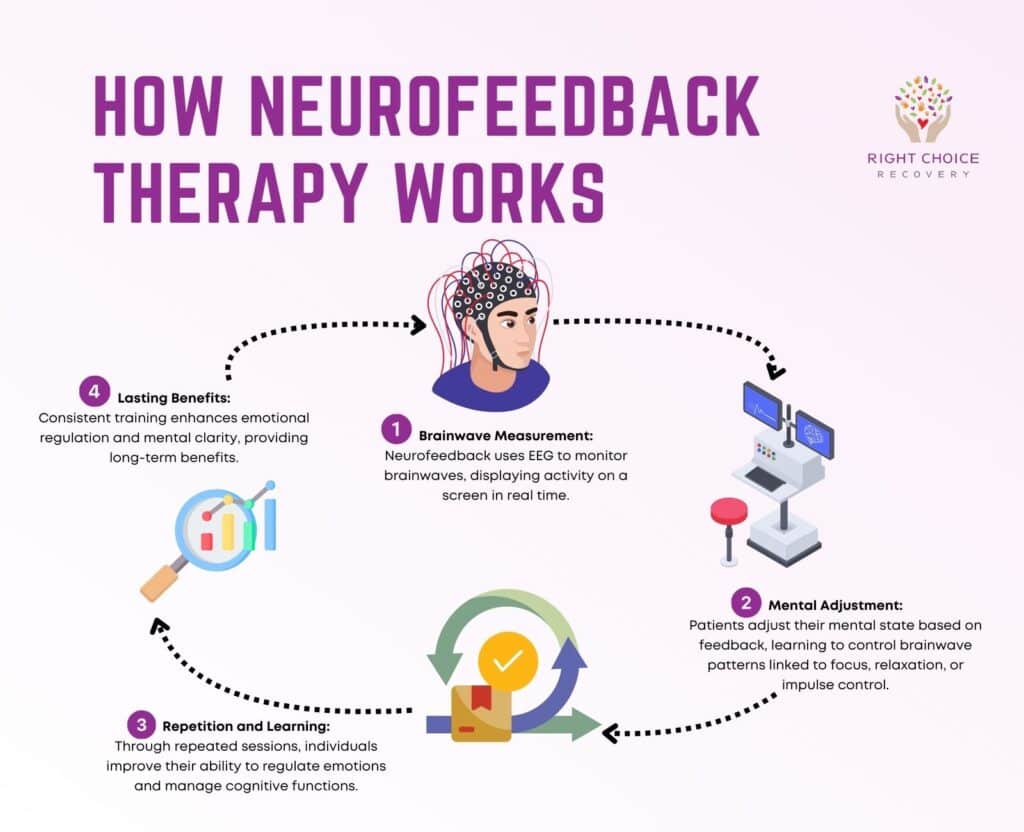
A protocol is simply a rule set that tells the software what brainwave state to reinforce or inhibit. You set thresholds, reward criteria, and session duration. The software then gives the patient positive feedback when the brain moves toward the target state and withholds it when the pattern drifts away. Start with a standard sensorimotor rhythm protocol at C3 or C4, 12 to 15 Hz, beta bandwidth, theta inhibition if you are doing a two-frequency protocol. This is the workhorse setup for ADHD and anxiety cases. Session length should be 20 to 30 minutes for adults and 15 to 20 minutes for children. Anything longer and compliance drops off sharply. One thing people do not tell you about threshold setting: the software default thresholds are usually too easy. If you leave them at factory defaults, patients will hit reward criteria 90 percent of the time and learn very little because the task requires almost no real neural change. Set thresholds so the patient earns rewards about 50 to 65 percent of the time. That is the sweet spot where adaptation happens without frustration.
Get the Full Details

Another detail that matters is the training order. Do not start every session with the same electrode site if you are using multiple locations. Rotate them across sessions. It prevents habituation to the feedback signal and keeps the brain engaged with the task rather than falling into a passive loop.
Common Mistakes When Starting Out
The biggest mistake I see is therapists trying to run neurofeedback before they have done at least forty hours of supervised training. The learning curve is steeper than most package sellers admit. You need to know how to differentiate real brainwave shifts from muscle artifact, eye blinks, and electrical noise before you trust a treatment plan built on that data. Another common error is ignoring baseline assessment. Without a qEEG or at least a structured resting-state EEG recorded before any training begins, you have no reference point. You cannot tell if a change in the patient is from the protocol or from normal day-to-day variability. Record a minimum of two minutes of eyes-closed and two minutes of eyes-open baseline every time you start a new case.
Neurofeedback Training For Therapists: Real-World Problems
Here is a specific situation I ran into that is worth documenting because it comes up more often than you would think. A patient was being treated for insomnia using a standard theta-beta protocol at Cz. Her raw EEG looked clean during training, but her sleep diary scores were flat. There was no improvement past week four. The issue turned out to be a subtle EMG contamination I was not catching. She was clenching her jaw during the theta epochs without realizing it. The EMG was smearing into the theta band and the software was reading it as actual theta increase, which meant the brain was not learning the target state at all. It was just masking the lack of change. The workaround was two steps. First, I added a frontalis electrode pair specifically to monitor frontal EMG and set a hard reject threshold so any trial exceeding the EMG limit was automatically excluded from the reward calculation. Second, I switched the feedback modality from visual to purely auditory for three sessions. That removed the visual cue that was unintentionally prompting her to tense her face muscles while watching the screen.

After those changes, her theta response became measurable and her sleep scores started improving within two weeks. It took me about ten minutes to implement the fix once I knew what to look for, but finding that specific artifact pattern could take hours if you do not know where to check.
What Neurofeedback Cannot Do
Be honest with yourself and your patients about what this approach does not solve. Neurofeedback is not a cure for psychosis, bipolar disorder, or active substance withdrawal. The evidence base is weak to nonexistent for those populations, and pushing it there is clinically irresponsible. It also does not replace medication when medication is indicated. A patient with moderate to severe depression who needs an SSRI should be on that SSRI first. Neurofeedback can be an adjunct, but it is not a first-line standalone treatment for acute clinical depression in most cases. The session dropout rate is another practical constraint. Around 20 to 30 percent of patients do not complete a full protocol series. Some drop out because they do not feel any change, which is a legitimate concern. Others drop out because the repetition gets boring, which is also legitimate but harder to address. You need a conversation about expectations before the first session, not after week six when someone disappears.
If you are looking for a simpler alternative for basic anxiety reduction, guided relaxation and biofeedback with heart rate variability monitoring is easier to set up and has a steeper initial response curve for some patients. Neurofeedback is worth the investment when you need targeted cortical regulation that other modalities cannot reach, but it is not the fastest path to improvement for every case.

Getting Proper Training Yourself
Do not skip your own training. There are programs from organizations like the BCIA, the Neurotherapy Certification Board, and a few university-affiliated courses. A typical comprehensive program runs about 40 to 80 hours of didactic and supervised practical work. Cheaper weekend workshops exist, but they rarely cover enough of the edge cases you will hit in real practice. What you want in a training program is access to real patients, not just simulation software. Theory without hands-on time with actual EEG signals will leave you unprepared for the moment a patient moves and the entire recording goes noisy. Look for programs that require you to log a minimum number of supervised clinical hours before they sign off on certification.
Resources and Where to Find Them
The main directories for verified protocols and equipment are the BCIA credentialing body and the international Association for Applied Psychopharmacology. Most reputable software vendors also publish free protocol libraries, though you should cross-check those protocols against peer-reviewed literature before adopting them as your default. Not every vendor library is equally rigorous. For software, the options range from closed proprietary platforms to open-source frameworks. If you want a single download link for a working system, most vendors will require you to purchase their equipment first. There is no universal free neurofeedback software that is clinically ready to use without some configuration. The closest option is OpenVibe, which is free and functional, but it requires substantial setup effort and EEG hardware that meets clinical standards. My recommendation is to start with a vendor that offers a trial period and requires minimal setup, run a small batch of test cases, evaluate your own comfort level with the interface, and then decide whether you are ready to invest in a more flexible but complex system. That process usually takes about three to four weeks of trial use before you have a clear answer.