The Practical Reality Of Newborn Neurological Assessment
Most people think a neurological assessment of a newborn is this formal, ceremonial thing. It isn't. It's mostly standing over a bassinet in a hospital room at 2 AM, shining a penlight into eyes that won't stay open, and trying to interpret whether a baby's Moro reflex is normal or slightly asymmetrical while your coffee has gone cold. That's the actual day-to-day experience.
The standard tool used here is the Nelson Neurological Screening Test, often combined with the American Academy of Neurology's guidelines and the Brazelton Neonatal Behavioral Assessment Scale (NBAS) for behavioral components. In practice, what you're really doing is checking seven or eight items in about five minutes for a healthy term infant. Preterm infants require a modified approach using the Preterm Infant Behavioral Assessment (PIBAS) or the Newborn Individualized Developmental Care and Assessment Program (NIDCAP) framework.
Neurological Assessment Of Newborn: How It Actually Works
You start with general appearance and consciousness. The baby should be alert during at least some observation window in the first 24 hours. If the infant is profoundly lethargic or persistently irritable without an identifiable metabolic or infectious cause, that's a red flag worth documenting and escalating.
Then you move through cranial nerves. Most clinicians check the pupils for constriction to light, though newborn pupils can be small and sluggish normally due to immature autonomic regulation. A normal finding is equal constriction, not a dramatic response. You check the rooting reflex by stroking the cheek. You check the suck reflex. You observe eye tracking — newborns can track a face or high-contrast object for roughly 5 to 10 centimeters at about 20 to 30 centimeters distance, and that range expands over the first weeks.
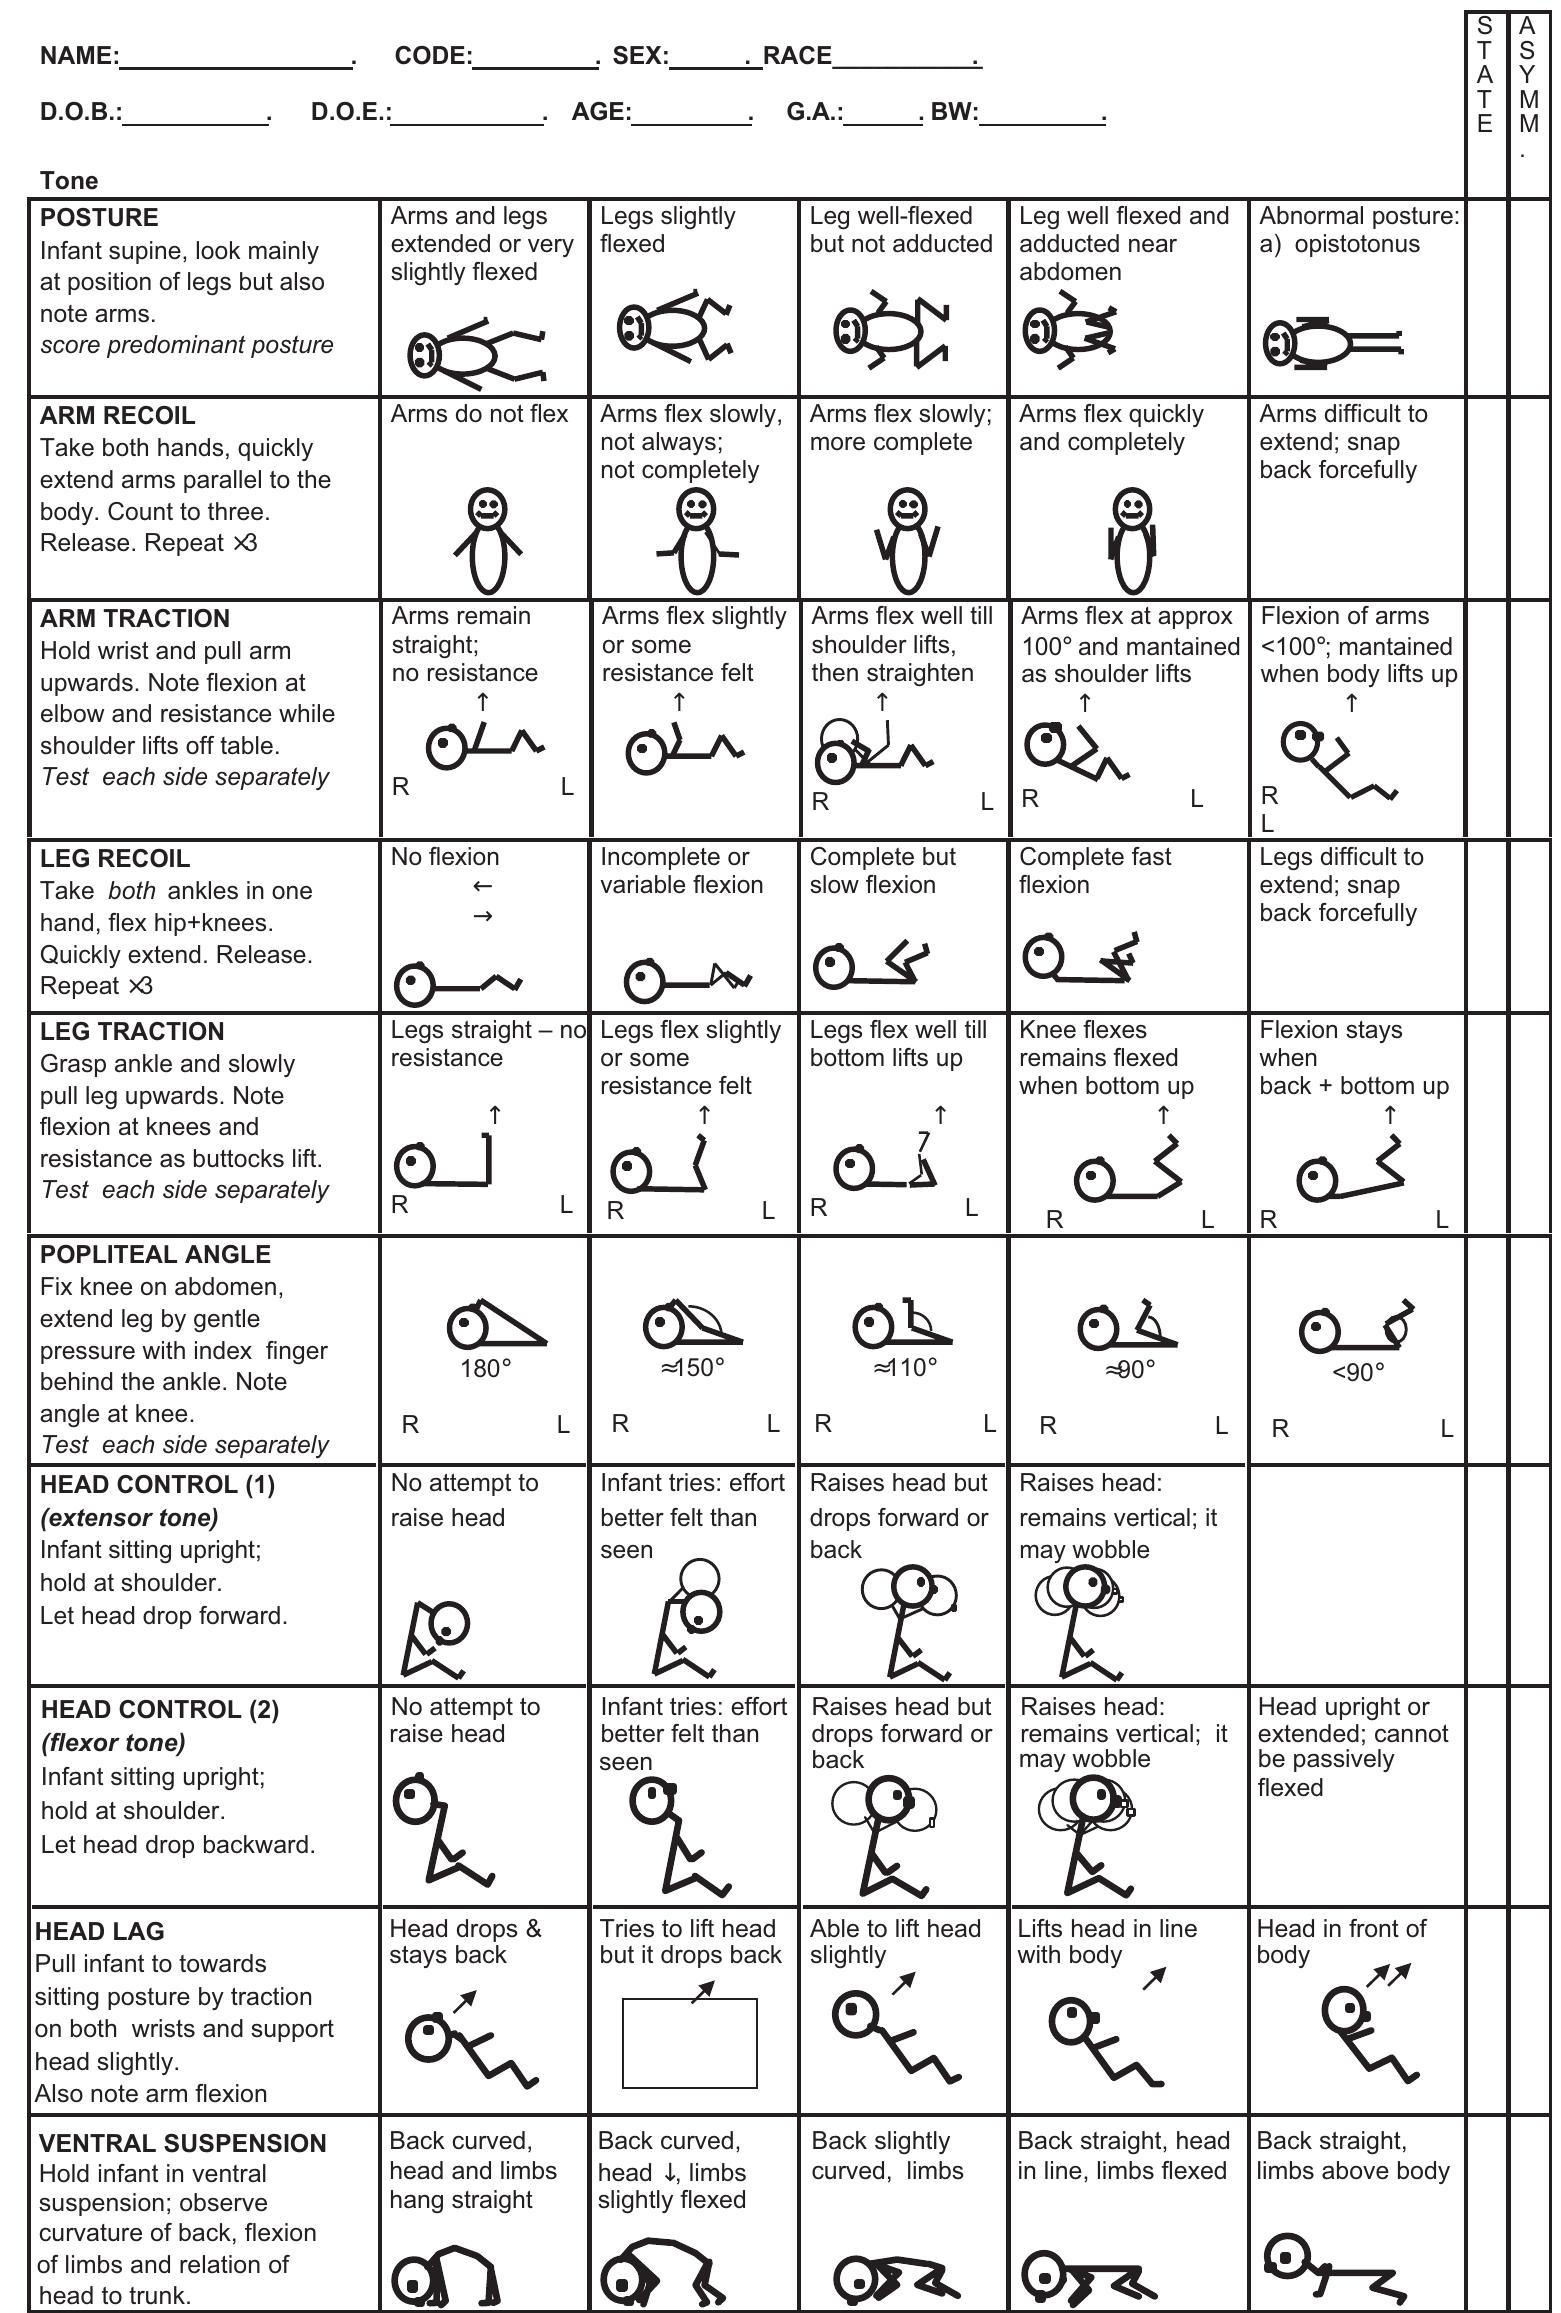
Motor tone is where most people make mistakes. You assess both posture and resistance to passive movement. A term newborn should have flexed limbs with moderate resistance. If the legs feel like a ragdoll with almost no flexor tone, hypotonia is present and warrants further workup. If the limbs are stiff and extend rigidly, hypertonia or early signs of upper motor neuron involvement may be present.
Reflexes come next. The Moro (startle) reflex, grasp reflex, tonic neck reflex, plantar reflex, and stepping reflex are the core set. Each has a specific age window. The Moro reflex typically integrates between 3 and 6 months. The grasp reflex fades around 3 to 4 months. The stepping reflex usually disappears by 2 months. If these reflexes persist beyond their expected integration window, that's clinically significant. If they're absent at birth in a term infant, that's also significant and usually triggers a search for central nervous system depression, spinal cord injury, or peripheral neuropathy.
Primitive reflexes are just one piece. You also need to observe spontaneous movement patterns. Normal newborns have irregular, asymmetric movements that are not stereotyped. Repetitive, stereotyped movements — especially rhythmic jerking confined to one body region — could represent neonatal seizures, which are frequently subtle and often misidentified as normal newborn jitteriness.
I spent about four years on a neonatology rotation doing these assessments daily, and here's something the textbooks don't emphasize enough: state of arousal completely changes your findings. A baby who is in a deep sleep state will have muted reflexes and appear hypotonic. A baby who is in an active sleep or crying state will have exaggerated reflex responses. If you only assess a newborn in one state, you're getting incomplete data. I learned to do an initial screen when the infant was quiet-alert, then re-check reflexes if the state shifted during the exam. That single habit caught two cases of mild hypoxic-ischemic encephalopathy that would have been dismissed as "normal variant" otherwise.
Common Pitfalls And What Actually Misses Things
The biggest error I see is conflating jitteriness with seizures. Jitteriness in newborns is common, especially in the first 48 hours. It responds to gentle flexion or containment. Seizures do not. They persist despite restraint and are often accompanied by autonomic changes like apnea or oxygen desaturation. A former attending of mine used to say the trick is to gently hold the affected limb — if the shaking stops, it's jitteriness. If it keeps going, you order an EEG.
Another pitfall is not accounting for gestational age. A 32-week preterm infant will have different reflex patterns than a 40-week term infant. The grasp reflex, for example, is weaker and less coordinated in preterms. Using term norms on a preterm baby leads to false-positive findings about abnormal tone or reflexes. I've seen premature infants incorrectly labeled with developmental concerns because someone ran a term-infant screening protocol on them without adjustment.
The Brazelton NBAS adds behavioral observation to the reflex-based screening. It covers habituation, self-regulation, social capacity, and motor organization. It takes longer — about 20 to 30 minutes — but it picks up subtle behavioral abnormalities that pure reflex screening misses. One specific case I remember: a term infant who passed every reflex screen perfectly but scored poorly on habituation and state regulation on the NBAS. Further evaluation revealed early metabolic derangement that wasn't yet showing up in standard labs. The behavioral screen flagged it first.
Practical Workflow For A Complete Assessment
Get the Full Details
Figure 2 - The neurological examination of the newborn baby
Start with observation before touching the baby. Note the spontaneous position, skin color, breathing pattern, and whether the infant is alert. Then proceed from head to toe in a consistent order so you don't skip items under pressure. Document each reflex as present, absent, symmetric, or asymmetric. Note the infant's state during each segment of the exam.
For hospital discharge screenings, a abbreviated version covering consciousness, cranial nerves, tone, and the five key reflexes is standard. That takes three to five minutes per infant. For a comprehensive developmental neurological assessment in a specialty clinic, you're looking at 20 to 40 minutes with repeat testing over multiple visits to track trajectory.
The Nelson form is widely available through medical supply catalogs and professional organizations. Many hospitals have it integrated into their electronic health record systems. The NBAS manual and scoring guide are published and can be obtained through developmental psychology and pediatrics publishers. For preterm assessments, the PIBAS protocol is accessible through neonatal research networks and professional neonatology organizations.
I keep a laminated quick-reference card in my chart pocket because the reflex integration timelines are easy to mix up under workload pressure. The specific windows matter — a tonic neck reflex that hasn't integrated by 7 months is different from one that's still present at 3 months. Context determines significance.
When The Assessment Falls Short
A bedside neurological screen is a screening tool, not a diagnostic one. It identifies concerns that need further evaluation. It does not replace neuroimaging, EEG monitoring, metabolic testing, or genetic consultation when indicated. A normal screen does not guarantee normal neurodevelopment. A baby with a typical newborn exam can still later present with cerebral palsy, developmental delay, or epilepsy. The screen is a snapshot, not a forecast.
The main limitation is operator dependence. Two clinicians can give different tone grades on the same infant. Reflex grading has inter-rater variability that is well-documented in the literature. This is why standardized protocols and repetition matter. Doing the assessment once and calling it definitive is where mistakes happen.
When I encounter an abnormal finding that doesn't fit a clear pattern — asymmetric reflexes with no obvious birth trauma, persistent hypotonia with otherwise normal appearance, seizures that don't match typical neonatal seizure semiology — I move to imaging and consultation rather than waiting for the next scheduled assessment. Early intervention pathways exist for exactly these scenarios, and delaying them based on the hope that a re-check will change the result wastes time that matters.
The assessment itself is straightforward. The interpretation requires experience and awareness of what normal variation looks like across different gestational ages, states of arousal, and clinical contexts.
Gallery Neurological Assessment Of Newborn
Hammersmith Neonatal Assessment Guide | PDF | Anatomical Terms Of ...
The Neurological Examination in the Critically Unwell Newborn Infant: A ...
Neurological Examination of an infant | PDF
Neuro, Pediatric nursing, Neurological assessment