Working With Neuromuscular Junction Physiology in Practice
Most people learn this stuff in a single lecture and then forget it until they need it for an exam. The actual mechanics of how a motor neuron talks to a muscle fiber are more fiddly than the textbook diagrams make them look. I spent a couple years doing electrophysiology work on isolated muscle preparations, and the gap between what you read about the neuromuscular junction and what you actually see on an oscilloscope is wide enough to be frustrating. Let me walk through how this actually works and where people tend to go wrong.Neuromuscular Junction Physiology: What Actually Happens Step by Step
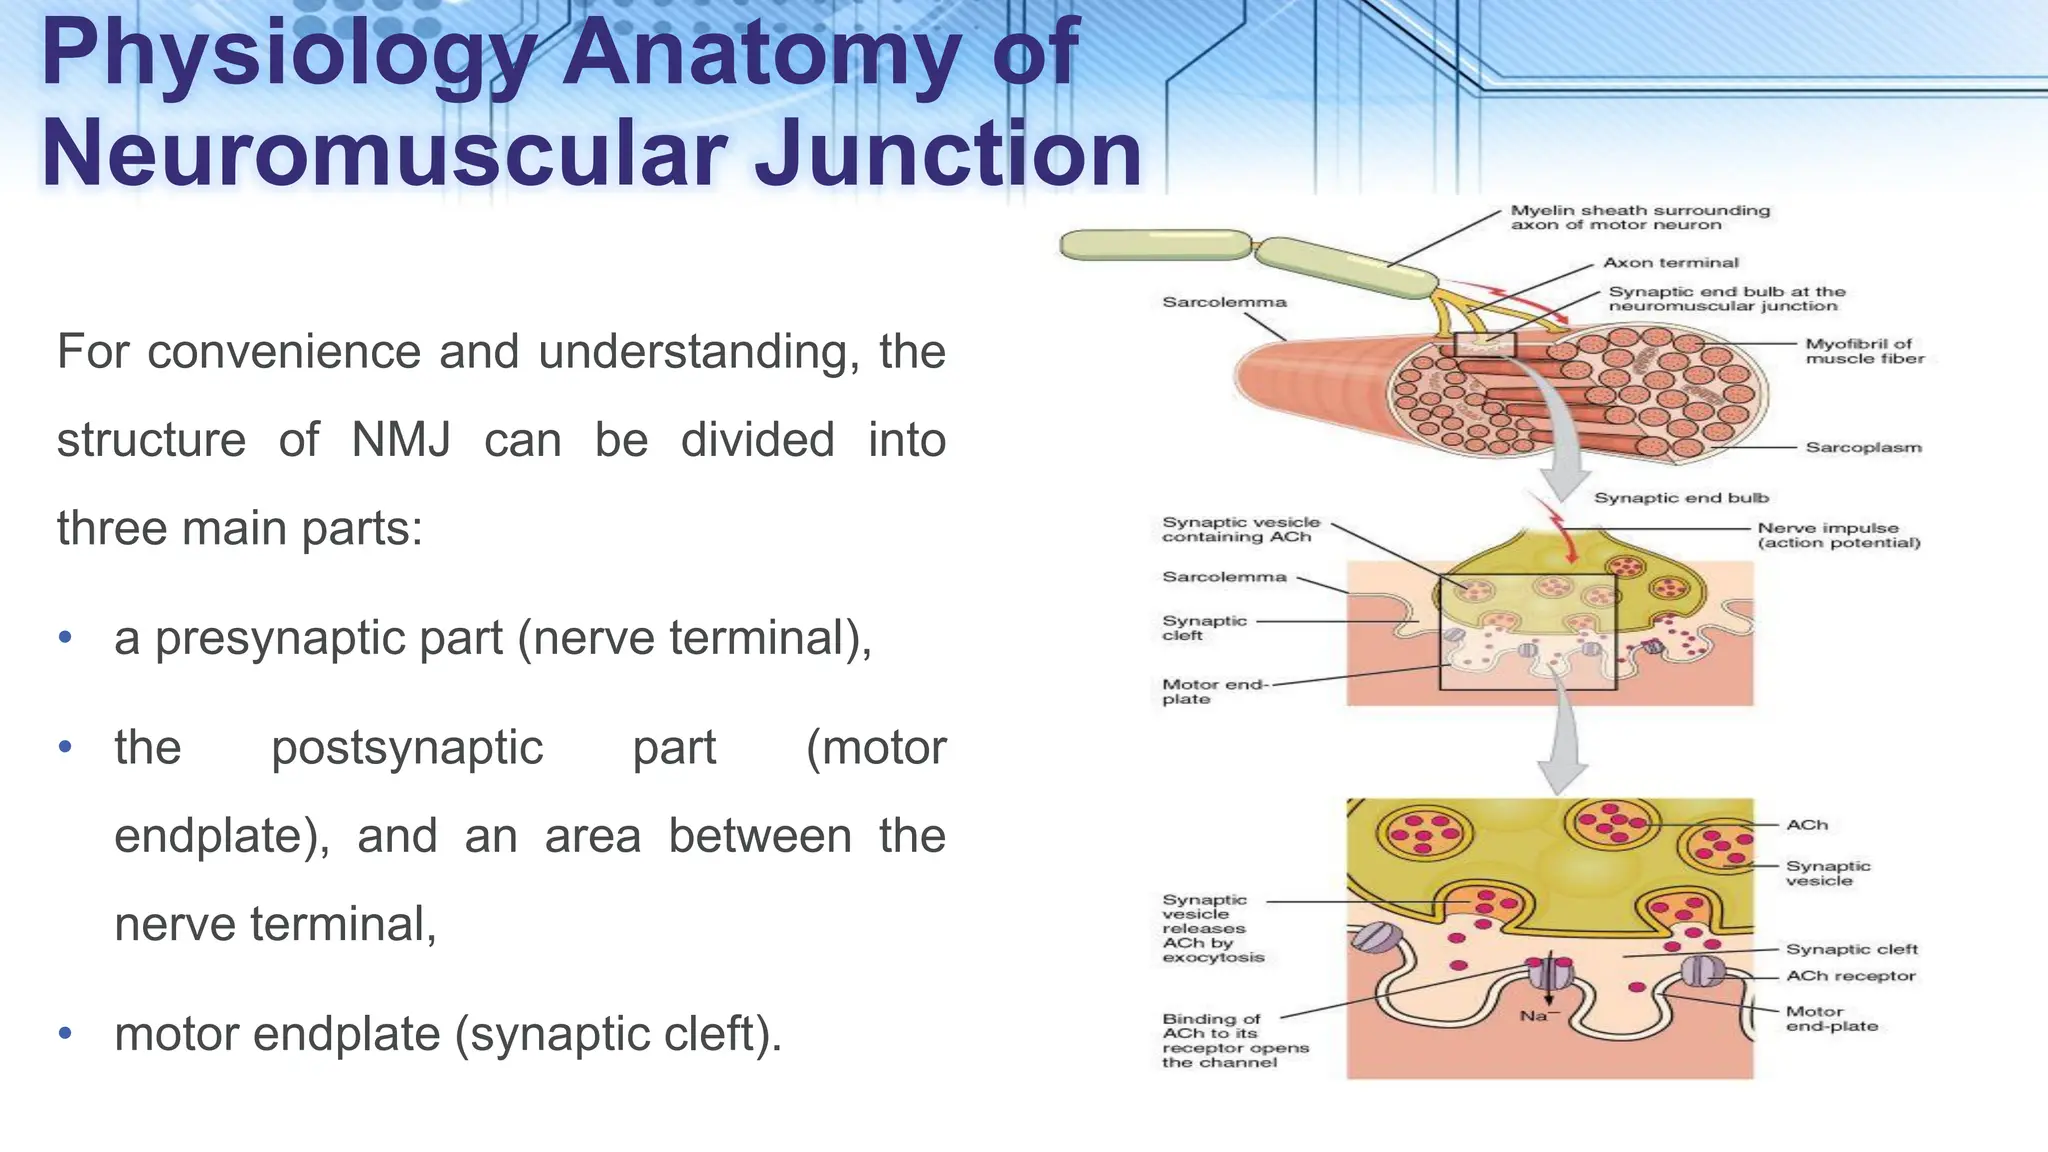
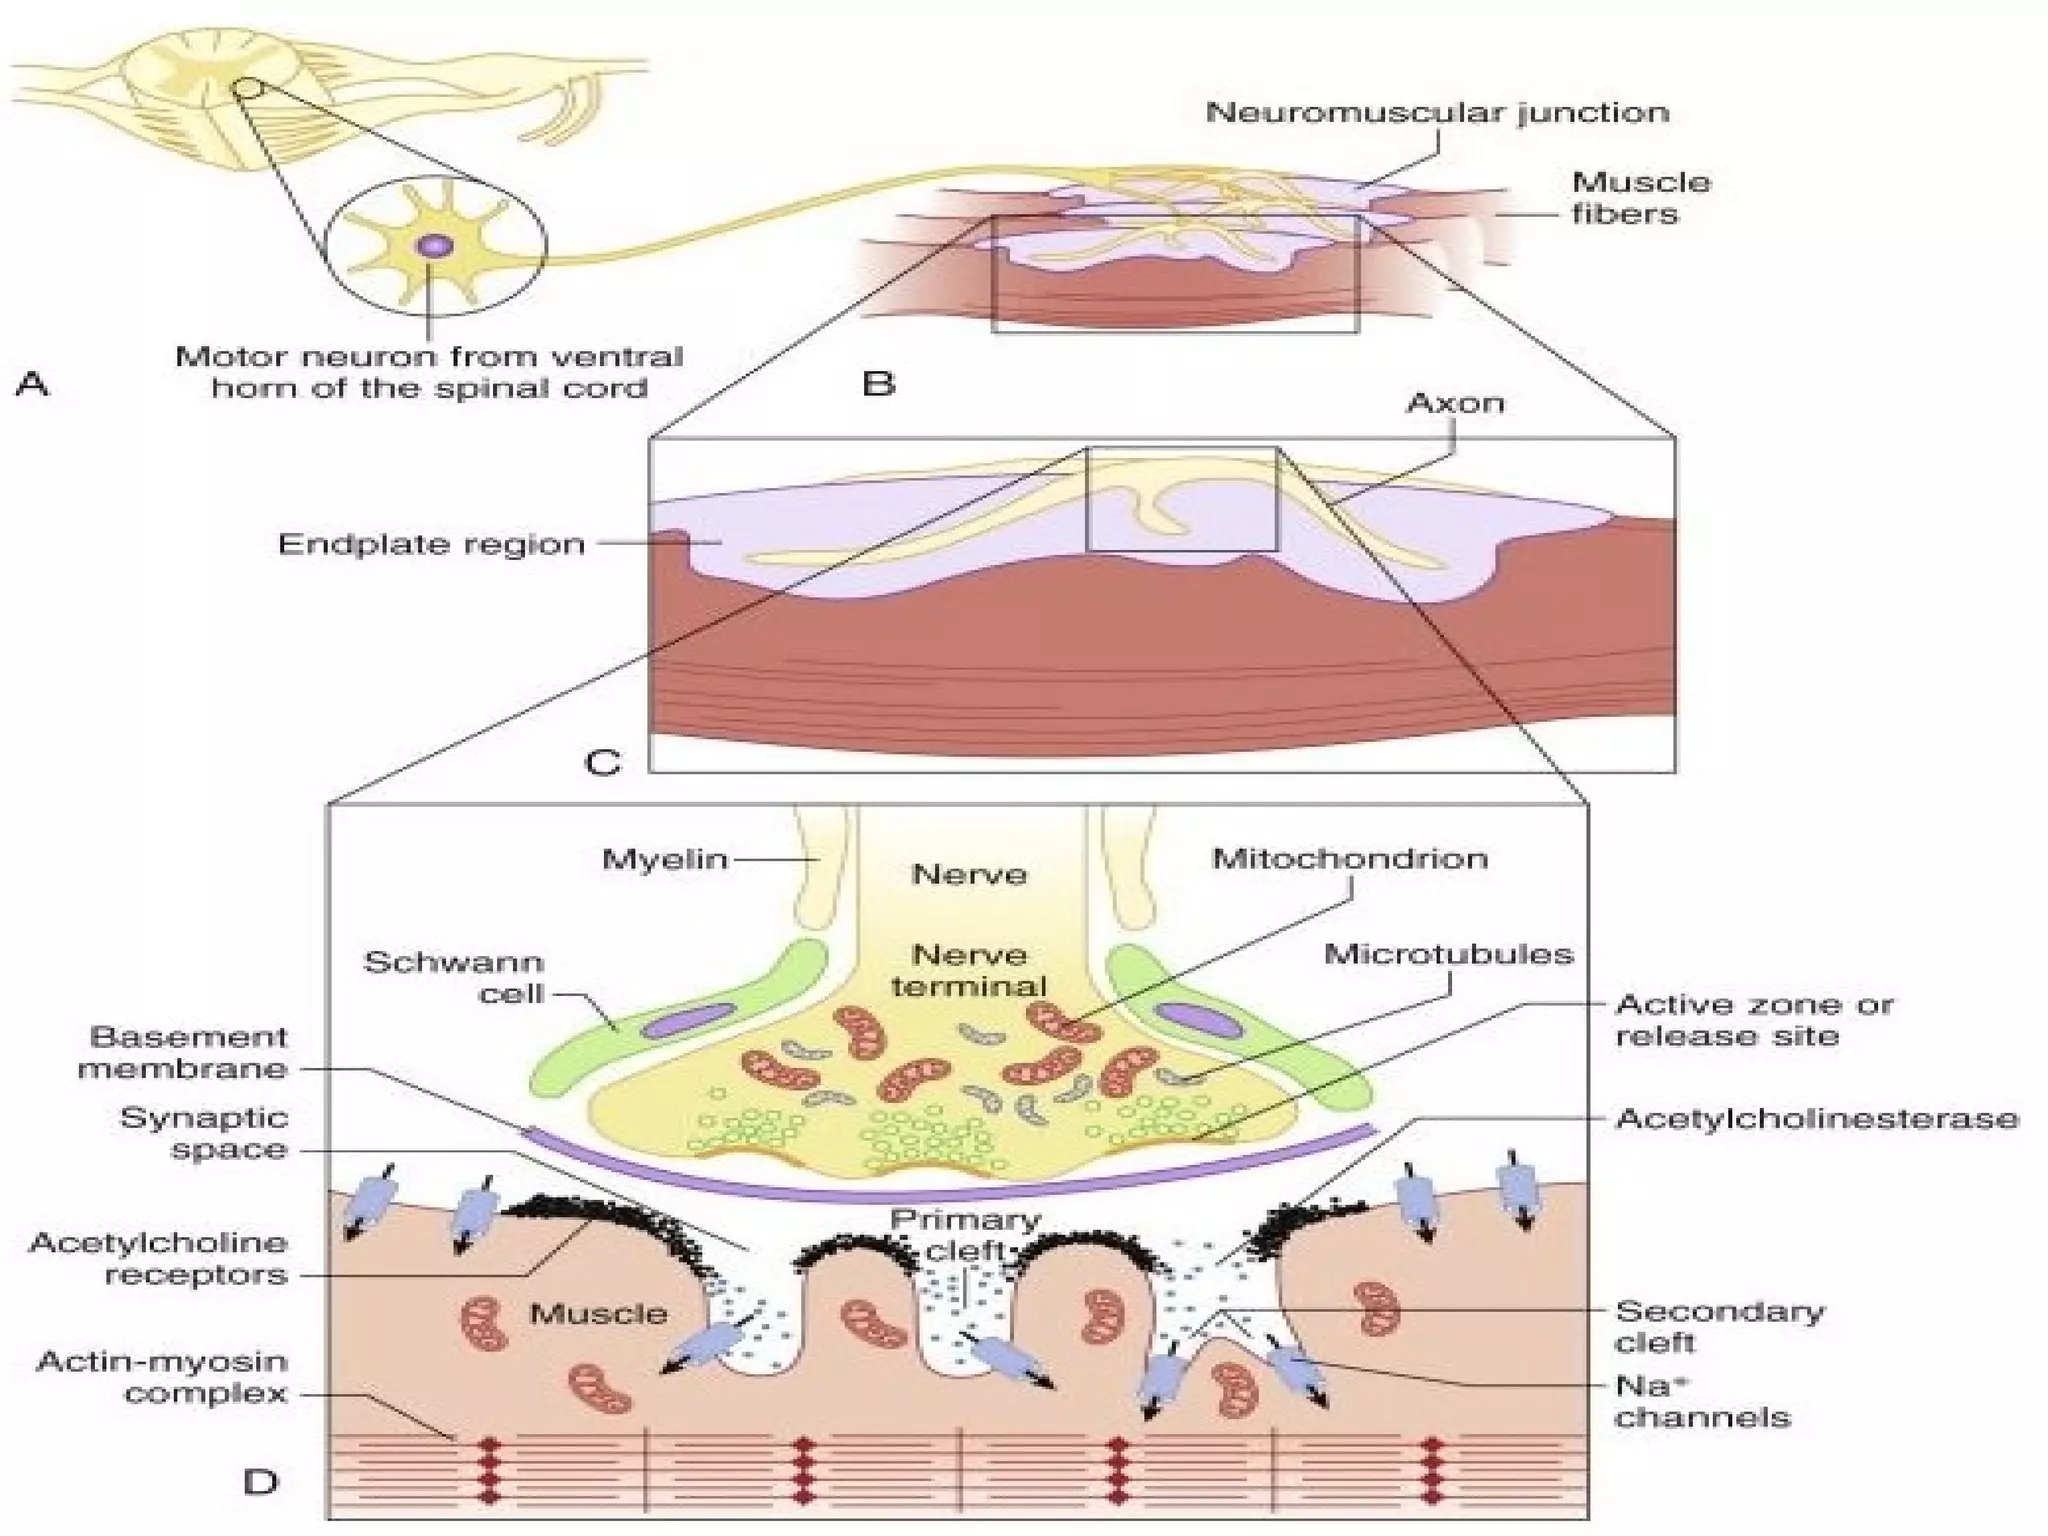
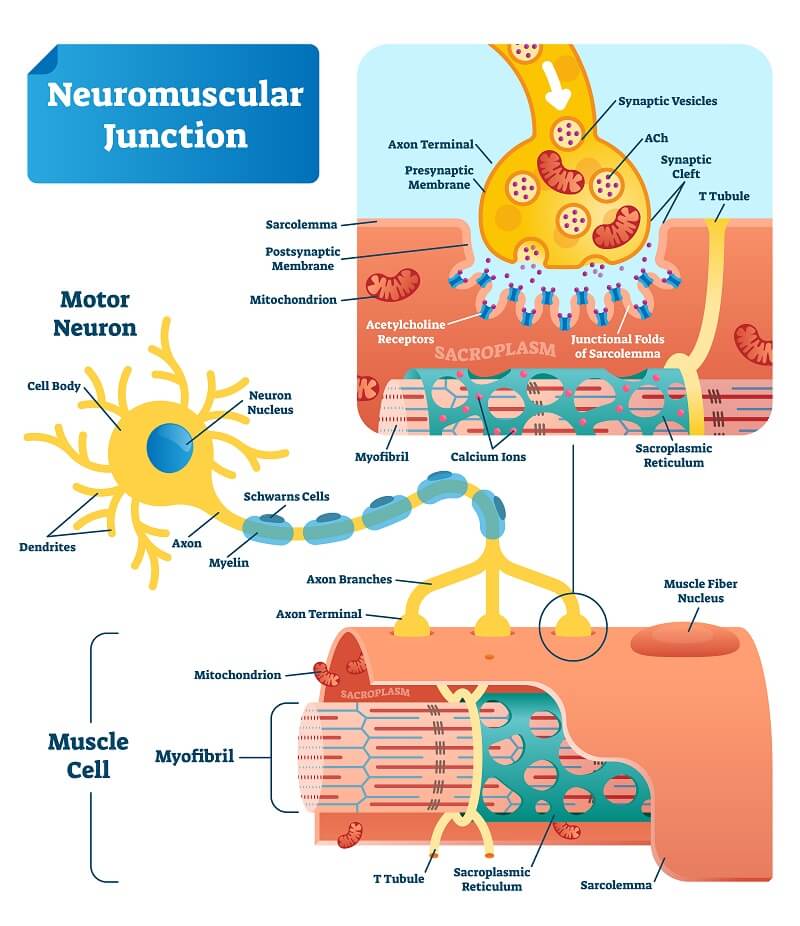
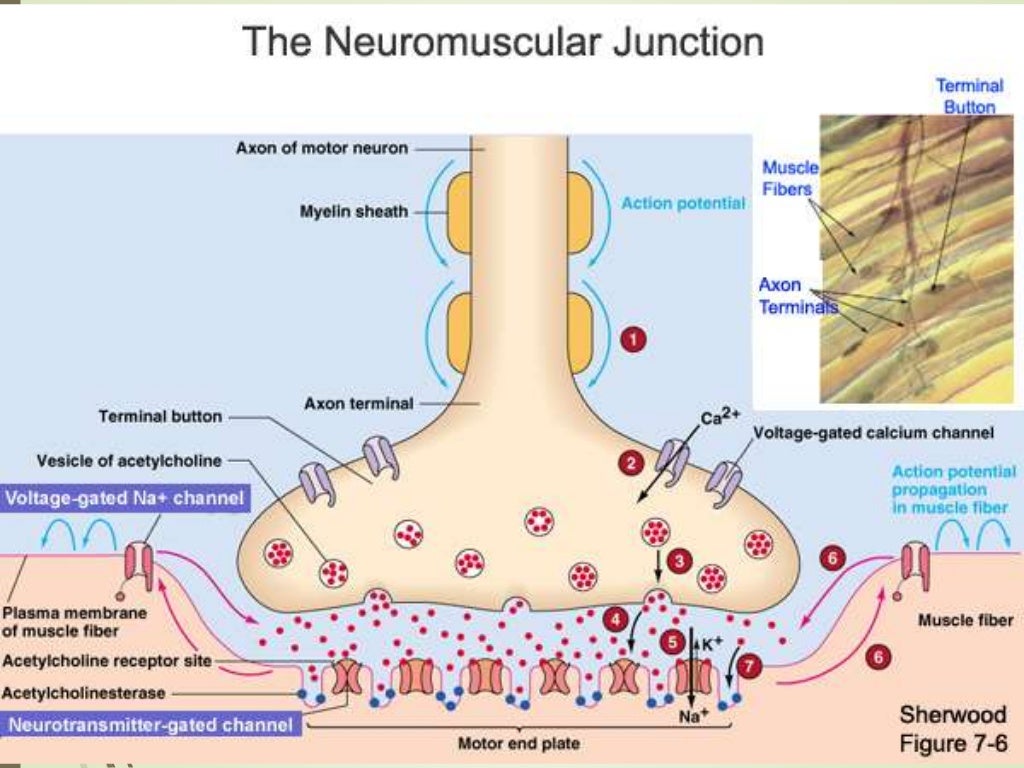
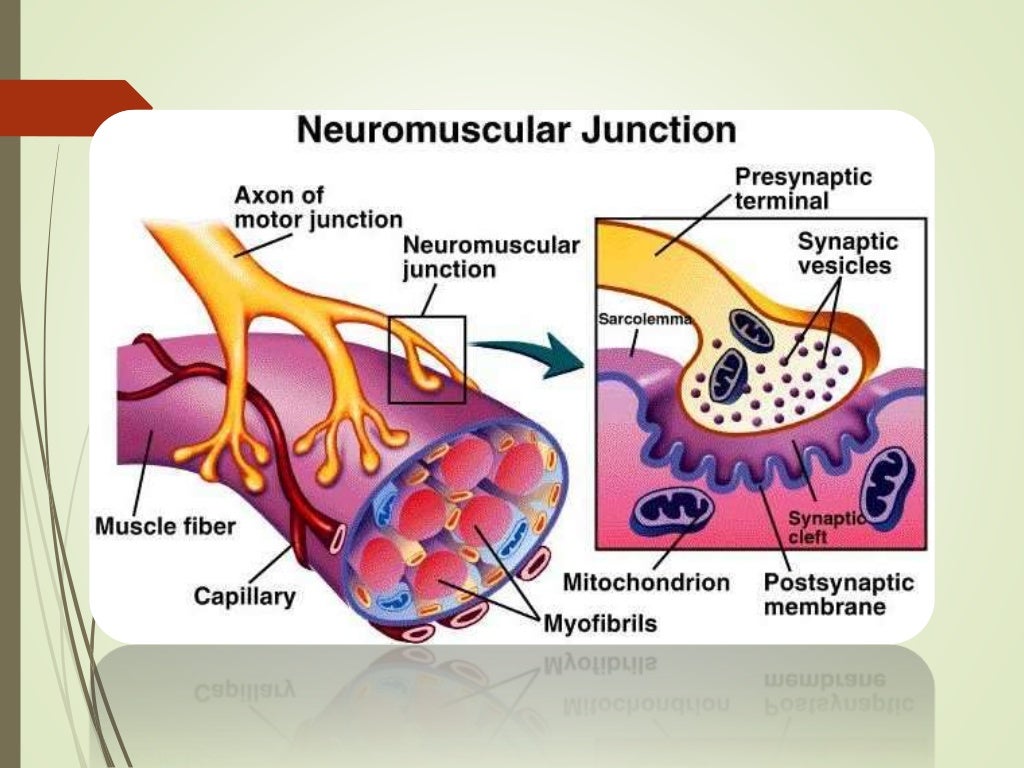
An action potential arrives at the motor neuron terminal. Voltage-gated calcium channels open. Calcium rushes in because the concentration gradient is steep. Synaptic vesicles containing acetylcholine fuse with the presynaptic membrane and release their contents into the synaptic cleft. Acetylcholine binds to nicotinic receptors on the motor end plate. Those receptors are ligand-gated ion channels that let sodium in and potassium out, with sodium winning, so the end plate depolarizes. If the depolarization hits threshold, a muscle action potential fires and propagates along the sarcolemma. That triggers calcium release from the sarcopl reticulum and contraction follows. That is the sequence. The parts people miss are the ones that are easy to overlook because they are fast or small. The end plate potential itself is always suprathreshold under normal conditions. It is not a graded affair that sometimes works and sometimes does not. A single quantum of acetylcholine releases about 4,000 to 5,000 molecules and produces a miniature end plate potential of roughly 0.5 to 1 millivolts. The full response involves thousands of quanta released almost simultaneously, producing an end plate potential in the range of 70 to 80 millivolts. There is a huge safety factor built into this system. A normal neuromuscular transmission will fire a muscle action potential even if you block roughly half of the available acetylcholine receptors. The reason that safety factor matters is because it explains a lot of clinical and experimental confusion. When someone tests for neuromuscular blockade, small changes in receptor availability may not produce obvious effects until you push past that threshold. That is why drugs like rocuronium or succinylcholine have such steep dose-response curves near the clinically relevant range. A tiny increase in blockade can go from barely noticeable to complete paralysis very quickly.
The Timing Pieces That Matter More Than You Might Think
The entire process from action potential arrival to muscle fiber depolarization takes about half a millisecond. The refractory period at the junction is essentially nonexistent because acetylcholinesterase breaks down the neurotransmitter within milliseconds of release. This is what allows the junction to support high-frequency firing without desynchronization. But that speed comes with a vulnerability. If you are recording from a preparation and your signals look noisy or inconsistent, the first thing I checked was the temperature. Acetylcholinesterase activity drops significantly below 37 degrees Celsius. In my own work, I once spent three days troubleshooting what I thought was a degradation problem in my muscle preparation. The real issue was that the bath perfusion system was running about four degrees too cold. Once I adjusted that, the responses normalized within an hour. Repetitive stimulation reveals different layers of the system. At low frequencies, each stimulus produces a clean end plate potential. As you increase the frequency, calcium accumulates in the presynaptic terminal. More calcium means more vesicle release per impulse. This is called facilitation and it peaks around 50 to 100 hertz. Push higher and you get depression because the readily releasable pool of vesicles starts to run thin. In a lab setting, watching this transition on a trace is one of the most informative things you can do to assess junction health.
Common Mistakes and Where the Textbook Falls Short
The biggest issue I see people run into is treating the neuromuscular junction as a simple on-off switch. It is not. The junction is a modulatory synapse in every practical sense. Presynaptic autoreceptors, particularly muscarinic M1 and beta-adrenergic receptors, can tune release probability up or down depending on the physiological context. Exercise increases extracellular potassium, which can enhance release. Fatigue changes the ionic environment in ways that subtly alter transmission even before the muscle itself tires. Another pitfall is misunderstanding how blocking agents work. Curare and its derivatives compete with acetylcholine at the receptor level. They are competitive antagonists, which means their effect can be overcome by increasing acetylcholine concentration. This is exactly why neostigmine reverses non-depolarizing blockade. It inhibits acetylcholinesterase, raising acetylcholine levels in the cleft, which outcompetes the blocking drug. But this strategy fails completely against depolarizing agents like succinylcholine. Succinylcholine activates the receptor and holds it open. More acetylcholine just means more persistent depolarization and worse blockade. I have seen this distinction glossed over in too many study guides, and it costs people points on exams and confusion in clinical settings.
Get the Full Details
Decoding the Endplate Potential
When you record an end plate potential directly, you get a local depolarization that decays exponentially with distance from the junction. The spatial decay constant is roughly 1 to 2 millimeters in skeletal muscle. This means the junction must be positioned strategically along the fiber, usually near the center, to ensure the local current reaches threshold along the sarcolemma. If you are working with muscle strips in an experiment, cutting too close to the junction region can damage the end plate and produce artifacts that look like reduced transmission when the junction is simply structurally compromised. The quantal content, which is the number of vesicles released per impulse, typically ranges from 50 to 200 in healthy adult mammalian neuromuscular junctions. This number is not fixed. It changes with development, with disease, and with pharmacological intervention. In myopathies like myasthenia gravis, the quantal content may appear normal initially because the safety factor masks the receptor loss. Only when receptor density drops below a critical point does the end plate potential fall below threshold and transmission fails. This is why early-stage myasthenia can present with fatigability rather than constant weakness. The junction works fine at rest but fails under repetitive use when the safety margin erodes.
What This Means for Practical Applications
If you are studying this for an exam, focus on the sequence and the safety factor. Those two concepts explain almost everything else. If you are working in a lab, learn to distinguish presynaptic from postsynaptic dysfunction. Presynaptic problems typically show reduced quantal content and abnormal response to high-frequency stimulation. Postsynaptic problems show reduced amplitude of the end plate potential with a relatively normal response to repetition until fatigue sets in. Botulinum toxin targets the presynaptic side by cleaving SNARE proteins and preventing vesicle fusion. This is why the effects last for weeks. The nerve has to grow new terminal branches and form new release sites. Anticholinesterase drugs target the cleft itself,ing the action of whatever acetylcholine is already being released. They help in myasthenia gravis but do nothing for presynaptic disorders like Lambert-Eaton syndrome, where the problem is voltage-gated calcium channel dysfunction. The neuromuscular junction remains one of the best-understood synapses in the body, but that understanding came from decades of careful experimentation, not from reading a single textbook chapter. The details that separate a superficial knowledge from a working one are in the timing, the safety margins, and the ability to recognize when a system is compensating versus when it is failing. Most people never get to that level because they stop at the basic sequence. The good news is that once you see past the diagram, the system makes a lot more sense and a lot more of the clinical material clicks into place.