The actual mechanics of trigger point work
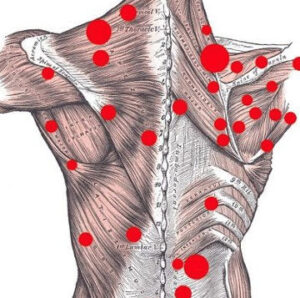
I used to think you just pressed hard until the pain went away. That approach wasted half my session time and left clients more sore than when they arrived. The real mechanism involves sustained isometric pressure applied directly into the taut band of muscle tissue until a local twitch response or release happens. You hold, you wait, you monitor the tissue change, you move on. Roughly 30 to 90 seconds per point depending on depth and fiber density. This is the formal name for the method. The "neuromuscular" part matters because trigger points aren't just knots. They're hyperirritable spots in skeletal muscle that sit within a palpable taut band and refer pain to predictable distant zones. Pressing on a trigger point in your upper trapezius might produce sensations along your temple or behind your eye. That referred pain pattern is what separates a real trigger point from general muscle tightness or fascial adhesions. The theory behind why this works goes back to the saturated energy theory developed by Janet Travell and David Simons. The idea is that trigger points maintain a contracted state because the sarcomeres within that region can't relax due to excessive acetylcholine release at the neuromuscular junction. Sustained pressure mechanically interrupts that cycle. You're not stretching the muscle. You're not breaking up scar tissue the way deep friction massage claims to do. You're applying enough load to force the localized contraction to release. The tissue then undergoes a brief inflammatory response which is why the area stays tender for a day or two after treatment.
Here is the practical breakdown of how to actually locate and treat a trigger point without wasting time or causing unnecessary damage. Palpation comes first and it takes practice. Use your fingertip or the heel of your hand, not your nail bed. Press perpendicular to the muscle fibers while slowly rolling the tissue between your fingers and the underlying bone or fascia. A trigger point feels like a small, distinct nodule that is noticeably firmer than the surrounding tissue. It may twitch under your finger when you press into it. That local twitch response is a reliable confirmation sign. Not every tight spot is a trigger point. Most tightness is just general hypertonicity and it responds better to stretching and loading than to direct pressure. Once you identify the point, apply sustained pressure at roughly 70 to 80 percent of the client's tolerance. That means they should feel significant discomfort but not pain that causes them to brace, hold their breath, or pull away. If they flinch, you are pushing too hard and the muscle will guard against you. Hold that pressure for 30 to 90 seconds. Do not rub. Do not glide. Just hold. You will feel the tissue soften and the taut band gradually decrease in tension. Sometimes you will see or feel a visible ripple as the fiber releases. Once the release happens, move to the next point. Do not spend five minutes on a single trigger point. Over-treating one area causes more inflammation than it resolves.
I ran into a specific edge case a few years ago that nearly made me quit this work entirely. A client came in with what looked like a textbook trigger point in the levator scapulae. I pressed into it, held for about 45 seconds, and instead of releasing, the entire upper shoulder girdle went rigid. The patient reported a sharp electric sensation shooting down the arm into the small finger. I stopped immediately and reassessed. That wasn't a trigger point. It was a peripheral nerve entrapment, likely at the suprascapular notch, presenting with secondary muscle guarding that felt exactly like a trigger point on superficial palpation. I had pressed directly on or near an irritated nerve and made things significantly worse. The workaround was simple once I recognized the pattern. I switched to distal work on the scalenes and the pectoralis minor, used gentle nerve gliding techniques instead of direct pressure, and referred the client for imaging. The nerve issue resolved in about three weeks. The shoulder never needed a single direct trigger point treatment. That experience taught me something important about differential diagnosis. Not every painful nodule is a myofascial trigger point. A trigger point should produce a characteristic referred pain pattern that matches known maps. If the sensation is sharp, burning, or follows a dermatomal distribution, you are likely dealing with neuropathic involvement. If the area is hot to the touch, red, or swollen, you are dealing with inflammation that direct pressure will aggravate. Deep vein thrombosis in the calf can present as a painful band that feels suspiciously like a gastrocnemius trigger point. Pressing on that could be catastrophic. Contraindications matter more than technique in a lot of cases. Common pitfalls that beginners consistently make include treating too many points in one session, using rebound pressure instead of sustained hold, and ignoring the post-treatment care. A typical safe limit is four to six points per session for most people. More than that and the cumulative inflammatory load becomes counterproductive. Rebound pressure, where you press, release, and press again rapidly, keeps the muscle in a defensive state. Sustained pressure is the key variable. Post-treatment, the affected muscle should be gently loaded through its full range of motion within 24 hours. Doing nothing after treatment often means the trigger point returns within a week because the underlying motor endplate dysfunction hasn't been retrained.
Get the Full Details

Another thing most guides don't mention is that trigger points in postural muscles behave differently than those in phasic muscles. A trigger point in the sternocleidomastoid, which holds your head up all day, will often persist until the postural load changes. You can release it perfectly and it will come back within days if the person still hunches over a desk for eight hours. The work is necessary but not sufficient. The same applies to gluteus medius trigger points in people who stand with their weight shifted to one hip. The point won't stay gone until the standing habit changes. Telling clients to just "relax more" is useless advice. You need specific movement retraining or ergonomic adjustments or the therapy is just a temporary bandage. For self-treatment, tools like a tennis ball or a dedicated myofascial release ball work fine for large muscle groups. Position the point between the ball and a wall or the floor. Lean into it with controlled body weight. Hold for the same 30 to 90 second window. The problem with self-treatment is that you cannot precisely palpate the taut band. You are guessing at location and depth. This is fine for maintenance on big muscles like the quads and glutes. It is unreliable for smaller deeper structures like the suboccipitals or the piriformis. A partner or trained therapist makes a measurable difference for those areas. The evidence base for this work is mixed but leaning positive for specific conditions. Trigger point dry needling shows stronger effect sizes than manual pressure alone for myofascial pain syndrome according to systematic reviews published in the last decade. However, dry needling requires clinical training and carries higher risk. For the general population, sustained manual pressure combined with corrective exercise remains the most practical and safest approach. There is no credible evidence that trigger point therapy helps with visceral referred pain patterns or that it can resolve chronic headaches caused by structural issues like cervical disc pathology. Be careful with claims made by practitioners who promise cures for migraines, fibromyalgia, or chronic fatigue through trigger point work alone. Those conditions require multidimensional management and direct pressure on muscle bands is at best a supportive intervention.
The timeline for meaningful improvement varies. Acute trigger points from a recent injury or overloaded session often resolve within two to four treatments spaced three to four days apart. Chronic trigger points that have been present for months or years may require six to twelve sessions before the referred pain patterns stop recurring. If you are not seeing any reduction in referred symptoms after four sessions, you are either missing the actual source tissue or the diagnosis is incorrect. Continuing to press harder into the same spot will not fix that. Reassessment is the correct move. I still use this technique regularly but I apply it more selectively than I did ten years ago. I check for nerve involvement first. I limit direct pressure to confirmed myofascial trigger points with clear referral patterns. I combine it with strength work for the treated muscle within 48 hours. And I accept that some points simply will not stay gone without addressing the mechanical load that created them. The method is useful. It is not a cure-all. Treat it that way and it delivers consistent results.