EEG-Based Assessment in Clinical Neuropsychiatry
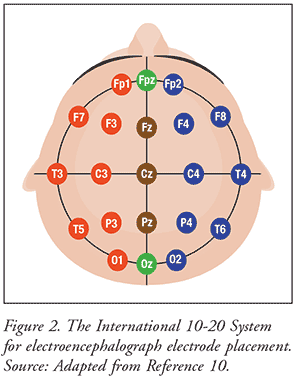
I've spent the last eight years working with quantitative EEG systems in outpatient clinics, mostly covering ADHD, mood disorders, and treatment-resistant anxiety. The hardware has gotten cheaper, but the signal processing side is still where most people get it wrong. I'm going to walk through how a proper assessment pipeline actually runs, what the data looks like when it's clean versus when it's garbage, and the things that trip people up. The core idea is straightforward: record resting-state EEG, extract frequency-domain features, compare them against a normative database, and use the deviations to inform clinical decision-making. What most vendors don't tell you is that the "deviation" metric depends heavily on how the reference population was scaled. Some databases are age-banded in five-year increments, others in decades. The difference matters when you're looking at theta/beta ratios in a 17-year-old versus a 42-year-old. A proper system captures at least 20 channels following the international 10-20 placement scheme, with impedance checks before every recording. I've seen too many clinics skip the impedance verification and then spend 45 minutes wondering why the frontal channels look like noise. Set your gain appropriately, use a 1-second artifact rejection window, and make sure the ground electrode is on the forehead, not dangling somewhere on the arm.
What the features actually represent Alpha peak frequency is the most stable single metric in the entire system. If it's shifted right in someone with depression, that usually means reduced cortical inhibition. If it's shifted left with elevated theta, you're looking at possible attentional deficits or early neurodegenerative change. These patterns aren't diagnostic on their own, but they give you a directional anchor when you're sitting across from a patient who's been misdiagnosed three times already. Connectivity measures like coherence and phase-locking value tell you about functional networks. Default mode network disruption shows up consistently in ADHD, and you can see it without doing a full connectivity analysis. Just look at the FCz-Cz coherence in the alpha band. If it's above the 90th percentile, the patient likely has poor task-negative network suppression during cognitive tasks.
Setting Up the Recording Environment
The room matters more than the amplifier. Fluorescent lights at 60 hertz will introduce noise that looks exactly like muscle artifact. Turn them off or switch to LED drivers with proper filtering. The patient needs to sit in a chair that doesn't vibrate, away from windows with air conditioning units cycling on and off. I had a case last spring where every recording from a particular clinic showed a 12 hertz oscillation that we couldn't explain until someone noticed the building's HVAC system was right behind the EEG room wall. Recording duration should be at least three minutes of eyes-closed resting state, followed by two minutes of eyes-open. If you're doing a full LORETA analysis or source localization, go for five minutes minimum. Shorter recordings give you frequency estimates with wide confidence intervals, and the normative comparisons become meaningless at that point. Before the patient sits down, explain what's going to happen. Anxiety changes frontal alpha asymmetry in ways that look identical to clinical depression. I don't do resting state recordings until the patient has been sitting quietly for at least two minutes after I've attached the electrodes. The first minute is always contaminated by placement discomfort and adjustment anxiety.
Get the Full Details

Signal Processing and Artifact Removal
Here's where the real work happens. Raw EEG needs filtering before any feature extraction. Bandpass between 0.5 and 45 hertz is standard, but the high-frequency cutoff depends on your research question. If you're studying gamma activity, 45 hertz cuts off everything interesting. If you're looking at alpha and theta, keep it conservative. Notch filtering is necessary in most clinical environments, but I prefer regression-based line noise removal over simple notches. Notches introduce phase distortion and can create artificial spectral peaks at the fundamental frequency and its harmonics. I run a clean line noise regression using reference channels placed near the patient, then apply the correction to all recording channels. Artifact rejection strategies
Eye blinks and saccades are the easiest to handle. The VEOG channel picks them up directly, and you can regress them out or mark the epochs and exclude them. Muscle artifact is harder. Frontal EMF contamination often looks like high-frequency beta elevation, and novices frequently misinterpret it as true beta activity. Check the Fp1-Fp2 ratio. If the "beta" shows up equally in both frontal poles and correlates with jaw tension, it's muscle, not brain. I use an automated pipeline with manual review. The software flags epochs with amplitude exceeding 100 microvolts or frequency content outside the expected bands, but I still watch every rejection. Automated systems miss slow drifts and electrode pops that humans catch immediately. After artifact removal, verify that you have at least 60 percent of the original recording time remaining. Less than that, and you should repeat the session.
Interpreting the Output Data
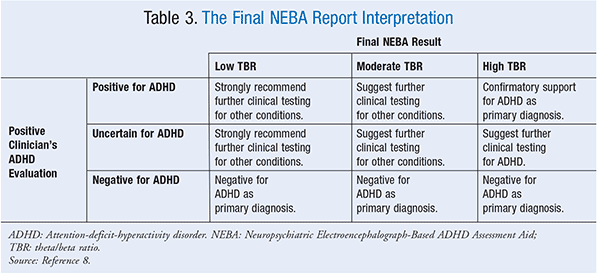
The Z-score maps are useful but they lie to you if you don't understand the underlying distribution. A Z-score of plus or minus 2 means two standard deviations from the normative mean, but that assumes normality. EEG power distributions are often log-normal or skewed, especially in clinical populations. Check the kurtosis and skewness values in the normative database documentation. If they're not reported, treat the Z-scores as approximate at best. Theta/beta ratios gained popularity through the ADDvantage protocol, and they got oversold. Yes, elevated theta/beta correlates with ADHD symptoms in some studies. Yes, it also correlates with fatigue, drowsiness, and poor sleep quality. A single ratio tells you almost nothing in isolation. I always look at the raw theta and beta absolute power, the normalization percentage, and the topographic distribution before making any interpretation. Common misinterpretations
Posterior alpha reactivity during eyes-open fixation is normal. If the alpha drops by more than 50 percent during visual engagement, that's called alpha blocking and it's a sign of intact visual cortex function. When people see reduced alpha blocking, they assume pathology. Sometimes the patient just wasn't looking at the fixation point, or the eyes-open recording was too short. Verify the recording conditions before drawing conclusions. Frontal midline theta elevation during mental arithmetic is expected. It reflects working memory engagement, not pathology. The problem is that many assessment systems don't distinguish between resting state and active task contexts. Make sure you're comparing like with like. Resting state theta should be evaluated against resting state norms, not against norms collected during cognitive tasks.
Integration With Clinical Decision-Making
EEG assessment doesn't replace clinical interview or standardized rating scales. It supplements them. I use the data to refine hypotheses about treatment response, track medication effects over time, and identify comorbid conditions that might explain partial treatment response. A patient with bipolar disorder and comorbid ADHD will show different qEEG patterns than one with unipolar depression and ADHD, even when the behavioral symptoms overlap significantly. Medication effects on EEG are real and measurable. SSRIs tend to increase alpha power and shift peak frequency rightward. Stimulants reduce theta and beta absolute power, particularly in frontal regions. If you're comparing a medication-naive baseline to a medicated follow-up, expect shifts that reflect pharmacology rather than disease progression. Document current medications in every report. When EEG data is unhelpful
The system fails in several predictable scenarios. Severe motion artifact from agitation or parkinsonian tremor makes most channels unusable. Skin conditions or heavy scalp hair can prevent adequate electrode contact regardless of preparation technique. Some patients have artifact patterns that no amount of preprocessing can clean adequately, and in those cases, the effort produces more noise than signal. I've stopped trying to salvage recordings from patients on certain antipsychotic combinations. The drug-induced movement and metabolic changes create artifact patterns that survive every rejection algorithm I've tested. In those situations, switching to a different assessment modality or scheduling a separate session when medication levels are stable gives better results than pushing through with corrupted data.
Practical Workflow Recommendations
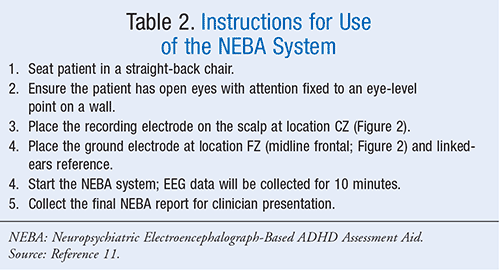
Start with a standardized checklist. Impedance check, reference electrode verification, ground placement, pre-recording patient instruction, two-minute acclimation period, three-minute eyes-closed, two-minute eyes-open, optional task blocks if indicated. Document everything. The report should include recording conditions, artifact rejection rate, and a note about any deviations from the standard protocol. Save the raw data alongside the processed output. You'll need it when a clinician asks a question you couldn't answer from the summary statistics alone. I've had cases where the automated analysis flagged something as abnormal, but reviewing the raw epochs showed the "abnormality" was actually a brief period of wakefulness mixed with drowsiness, not a pathological pattern. Update your normative database regularly. Age and possibly gender stratification matters, and the population characteristics of the reference sample affect how your Z-scores map to clinical reality. If you're using a database collected five or more years ago with a different demographic profile, the comparisons might not reflect current population norms. Check the publication dates and sampling methods of whatever reference set you're relying on.
The technology is mature enough for clinical use when operated by someone who understands both the signal processing and the neurophysiology behind it. Cut corners on either side, and the output looks impressive but tells you nothing useful. I've reviewed reports from systems that produced beautiful color-coded heatmaps while the underlying recordings were contaminated with line noise and muscle artifact throughout. The maps looked professional. The data was worthless.