Understanding Your Own Mind Through The Sense Of Agency
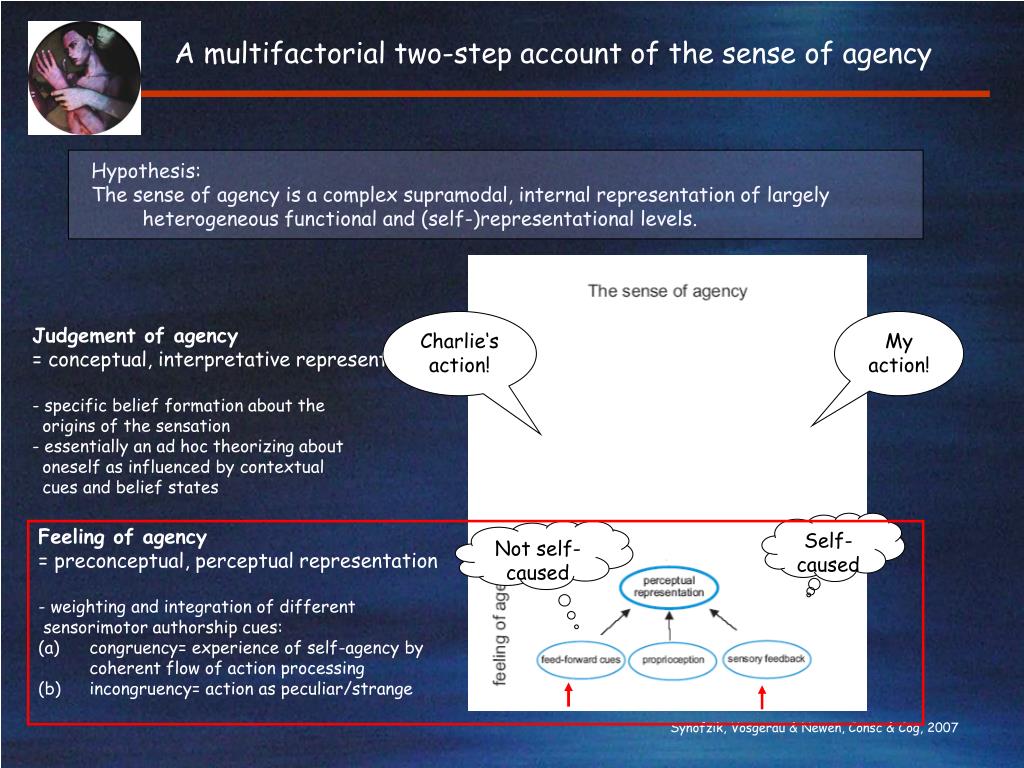
The sense of agency is the feeling that you are the one causing your actions. It sounds simple until you realize the brain constructs this feeling independently from your conscious awareness. Most of the time it works fine. Sometimes it breaks in ways that are diagnostically interesting. Researchers typically use task-based paradigms. The most common is the temporal binding task where participants press a button to produce a tone and then estimate when the tone occurred. When people feel agency, they perceive the outcome as occurring earlier than it actually did. This compression of time is one of the reliable markers. Another standard measure is the intentional binding effect, which shows up as a perceived shift in both the action and its outcome moving closer together in time. Then there are clinical assessments. Patients with schizophrenia often report reduced sense of agency, especially regarding their own thoughts being inserted by external forces. Conversely, some movement disorders like alien hand syndrome involve a pathological over-attribution of agency to a limb the patient no longer recognizes as their own. The neuropsychology here gets messy fast because the brain areas involved overlap significantly with those responsible for motor planning and sensory prediction.
I've spent considerable time working with these assessments in a clinical research setting. One edge case that keeps coming up involves patients with lesions in the right inferior parietal lobule. Standard agency tasks often give ambiguous results with this population because the lesion disrupts both the forward model used for prediction and the comparison process that generates the feeling of agency. The workaround I settled on was using a modified version of the press-trigger task with a variable delay manipulation instead of relying on the standard temporal estimation protocol. By systematically varying the stimulus onset asynchrony between the keypress and the auditory feedback, you can map out the binding window for each individual patient rather than assuming a group norm applies. It takes longer but it's more reliable for this particular population.
How The Brain Constructs Agency
The dominant framework is the comparator model, originally proposed by Wolpert and colleagues. In this model, when you decide to move, your motor cortex sends a copy of the command outward through an efference copy. This copy goes to a sensory prediction area where it is compared against the incoming sensory feedback. When the predicted and actual feedback match, the brain tags the action as self-generated. That tagging is what you experience as the sense of agency. Key regions involved include the premotor cortex, which holds the forward model, the posterior parietal cortex, which performs the comparison, and the cerebellum, which refines the predictions over time. The dorsolateral prefrontal cortex contributes to the conscious acknowledgment that you initiated the action. Damage to any of these pathways can produce deficits, but the pattern of deficit depends on which part of the pipeline is disrupted. A counter-intuitive finding from recent work by Chris Frith's group is that the sense of agency does not require conscious intent in the way most people assume. You can feel agency over actions you did not deliberately plan, provided the sensory outcome matches your internal prediction. This explains why habitual behaviors like typing or driving often carry a strong sense of agency even though you were not consciously deciding each movement. It also explains why forced compliance situations where someone else is physically moving your limb can temporarily suppress the feeling of agency even when your muscles are producing the movement.
Get the Full Details

Another thing beginners consistently miss is that agency is graded, not binary. It is not a question of whether you feel agency or not. It is a matter of how strongly you feel it, and the strength varies across different action types, different sensory modalities, and across different psychiatric conditions. A patient might report full agency over voluntary movements but dramatically reduced agency over vocalizations, which points to a specific disruption in the prediction pathway for that modality rather than a global deficit.
Assessment And Interpretation Pitfalls
Temporal binding tasks are widely used but they measure something different depending on how they are administered. Some versions ask participants to estimate the time of the tone. Others ask them to estimate the time of the keypress. These yield different results and should not be treated interchangeably. The direction of the temporal shift also flips depending on which endpoint you ask about, so mixing up the two during data analysis will corrupt your dataset entirely. The constant error method versus the threshold method in timing tasks produces systematically different values. Researchers sometimes compare their numbers against published literature without realizing the methodological mismatch. This happens more often than it should. In clinical populations, motivation and comprehension issues can masquerade as agency deficits. A patient who answers slowly on a temporal estimation task might have a processing speed problem rather than a true agency disruption. Including a control condition with passive stimulation where the tone plays without the participant pressing anything is essential for ruling out response bias. Without that control, you cannot tell whether a reduced binding effect reflects a genuine agency deficit or simply a participant who is disengaged or motor-impaired.
One practical limitation worth noting: the cerebellar contribution to agency predictions means that patients with cerebellar degeneration tend to show abnormal agency judgments even when their cortical planning areas are intact. This is not always obvious at first glance because their motor execution may appear normal. If you are testing a patient with unexplained agency disturbances and the standard paradigms come back unremarkable, screening for cerebellar involvement should be on the list. There are no universal normative values for these tasks because baseline binding effects vary considerably across age groups and cultural contexts. What looks abnormal in one sample might fall well within range in another. Building your own baseline using healthy controls tested on the identical protocol is the most reliable approach whenever feasible.

Practical Applications And Limitations
The most clinically useful application right now is in monitoring treatment response in schizophrenia spectrum disorders. Changes in the size of the intentional binding effect have been shown to track with positive symptom severity, which makes it a potential biomarker for antipsychotic efficacy. The effect is not strong enough to serve as a standalone diagnostic tool, but combined with other measures it adds something independent of standard clinical interviews. In movement disorders, the sense of agency assessment can help differentiate psychogenic movement disorders from organic ones. Patients with functional neurological disorder sometimes show a dissociation between reported lack of agency and preserved motor performance, whereas patients with corticobasal degeneration typically show a different profile of agency disruption tied to specific limb representation breakdown. The distinction matters because the management approaches diverge sharply. The main bottleneck for widespread clinical adoption remains standardization. There is no single agreed-upon protocol, no FDA-cleared device, and no widely accepted scoring manual. Most laboratories build their own task software or modify existing open-source implementations. This means results are not directly portable between sites, which limits the usefulness of multi-center studies. Until someone funds a proper standardization effort, you work with what you have and document your methodology exhaustively.
For researchers looking to get started, open-source implementations of the temporal binding task are available on platforms like Pavlovian and PsychoPy. The code is generally straightforward to adapt. The harder part is getting enough control data to establish local norms before you attempt to interpret patient data. Rushing into clinical applications without that foundation is the most common mistake I see.