What This Worksheet Actually Does
A Neuroscience Of Addiction Worksheet is a structured tool that maps the neural mechanisms underlying addictive behaviors onto a fillable format. It breaks down the dopamine reward pathway, habit loops, and stress system involvement so clinicians, students, and researchers can document observations systematically. The idea is straightforward: you take someone's behavioral data, their self-reports, and any available neuroimaging or biomarker results, and you cross-reference them against known neuroscience models of addiction. The output is a written profile that explains which circuits are likely dysregulated and what that means for treatment planning. I've used these in clinical settings and academic supervisions for years. They aren't magic, but they force you to stop guessing and start writing things down in a framework that actually connects behavior to biology.Using a Neuroscience Of Addiction Worksheet in Practice
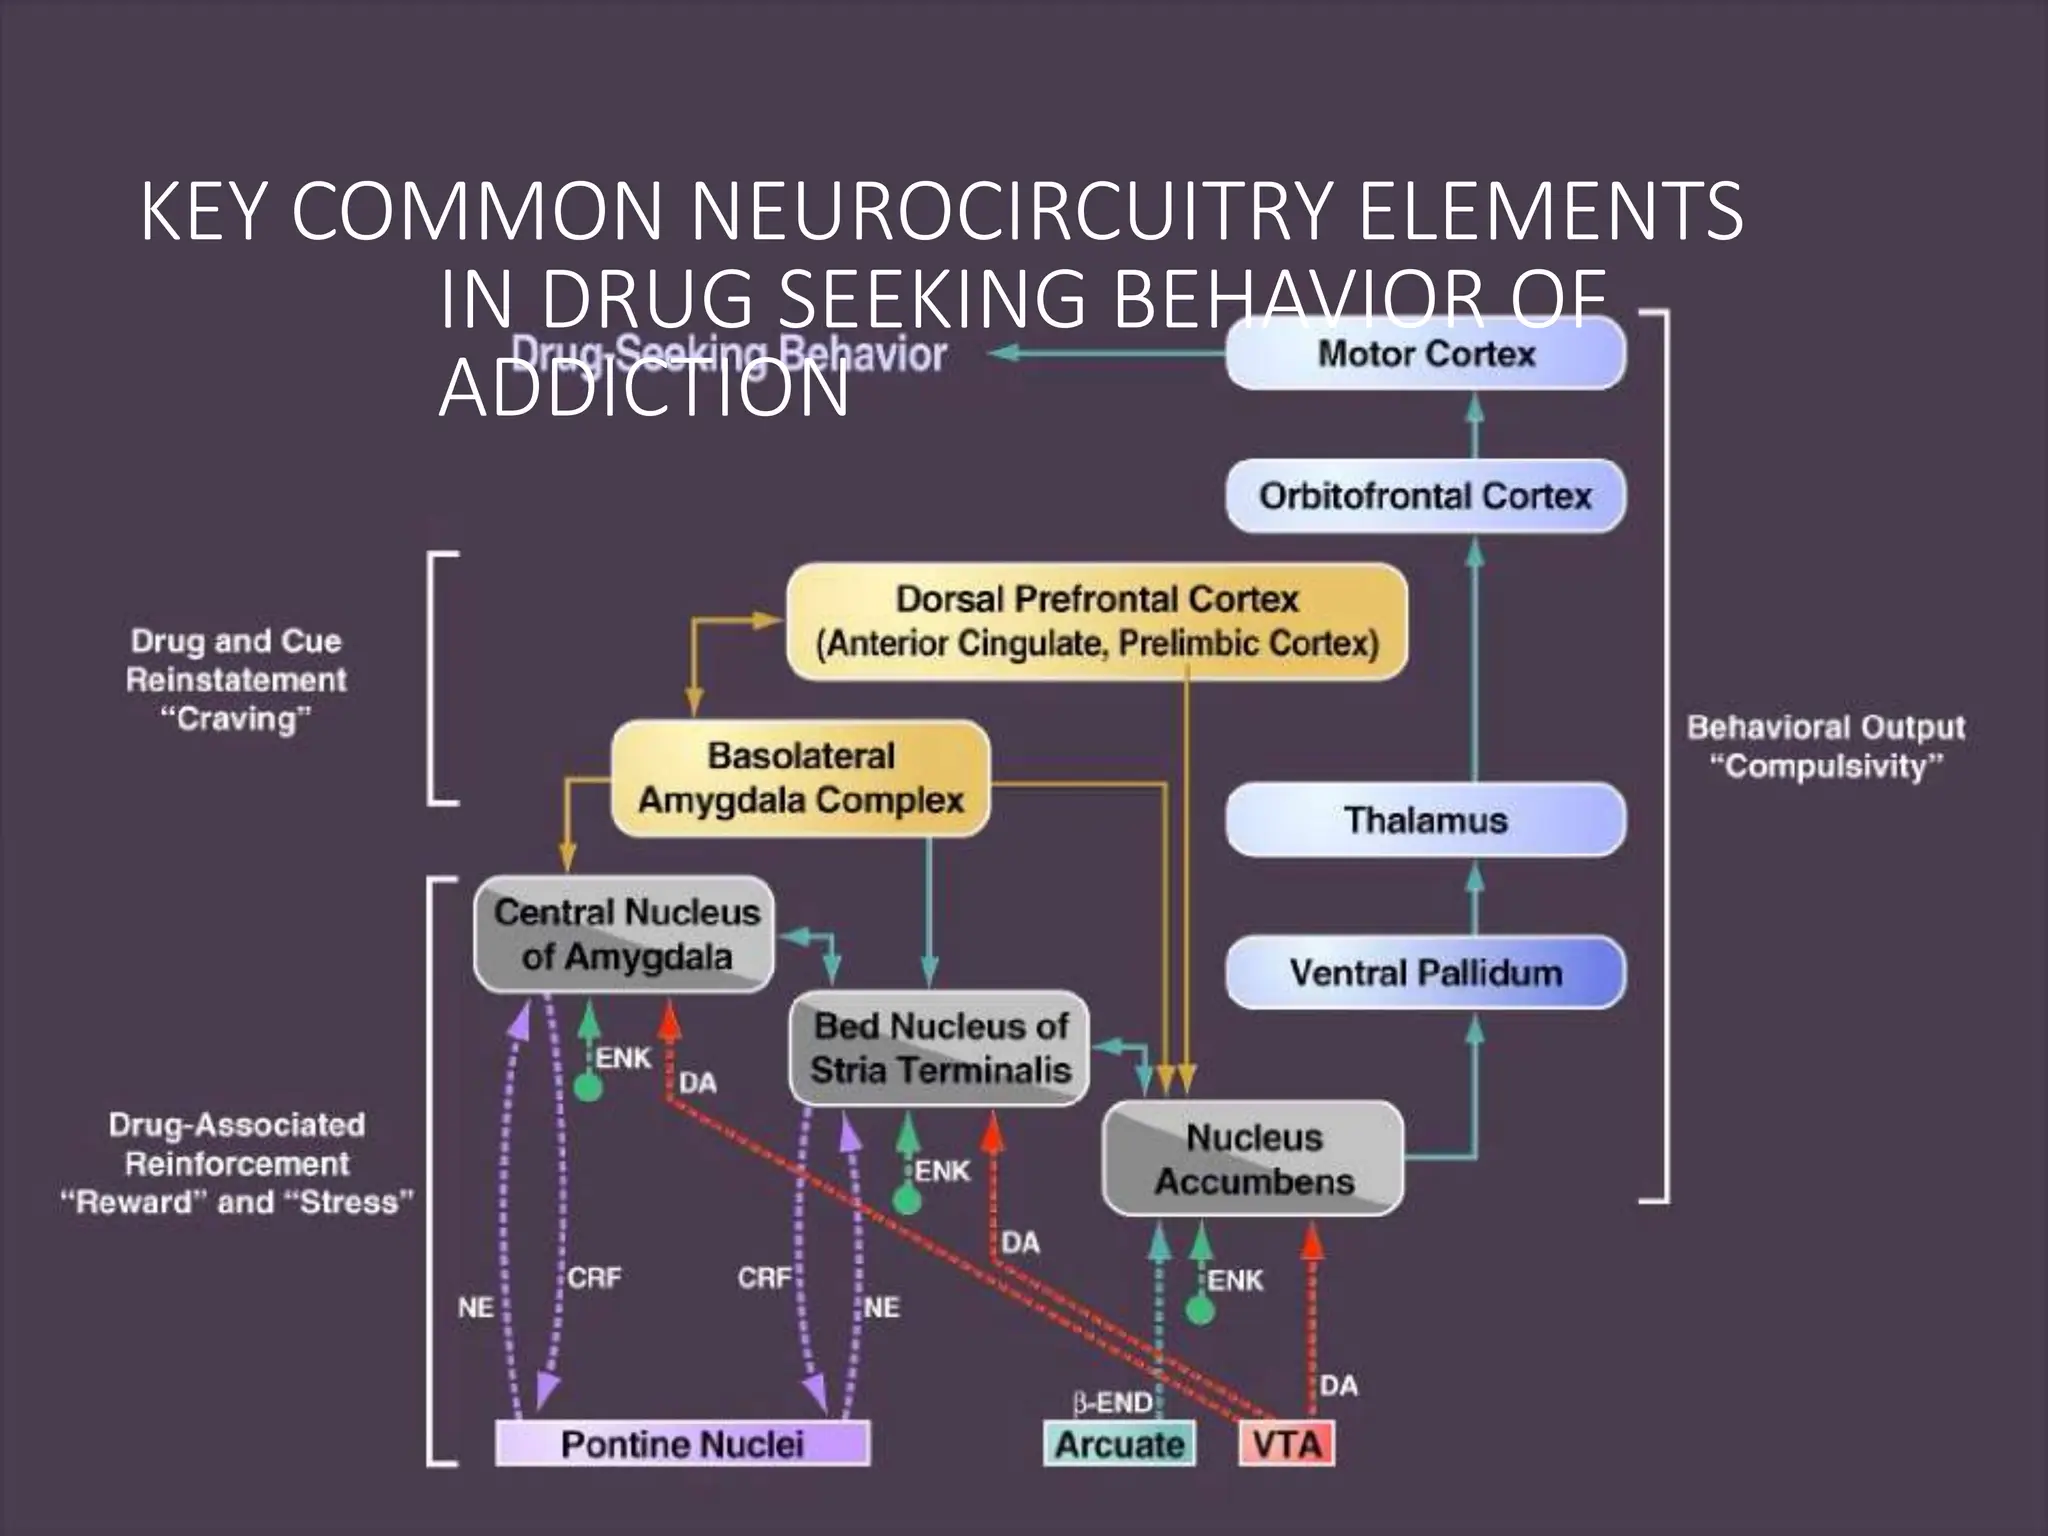
Here's how I approach it when I sit down with one. Start by gathering the subject's timeline: when did the substance use or compulsive behavior begin, what triggers it, and how does withdrawal present neurologically. Record this on the left side of the worksheet. Then move to the right side and map each reported behavior to a specific neural mechanism. Cravings connect to the nucleus accumbens and ventral tegmental area. Impulsivity maps to the prefrontal cortex, especially the dorsolateral region. Stress-induced relapse involves the amygdala and the HPA axis. You're not diagnosing anything here. You're creating a hypothesis-driven chart that you can revise as new information comes in. The worksheet works best when you don't rush it. I typically spend 20 to 30 minutes on the initial mapping, then come back 48 hours later to refine it once more data has accumulated. The first pass is always incomplete. That's fine.
Common Mistakes People Make
The biggest problem I see is people treating the worksheet as a checkbox exercise. They fill in the boxes, check off dopamine and prefrontal cortex, and call it done. That's not how you use this tool. The value comes from the connections you draw between the boxes, not the boxes themselves. Another frequent error is ignoring the negative reinforcement circuit. Everyone focuses on the reward pathway, but the extended amygdala's role in the aversive state that drives continued use during withdrawal is where most relapse predictions actually break down. If your worksheet doesn't account for the shift from positive to negative reinforcement, it's missing half the picture. About two years ago I was working with a client who had a clean history on paper. No family history of substance use, early onset of behavioral control, strong social support. The standard risk factors were all absent. But she was stuck in a compulsive pattern around prescription stimulants that didn't fit any textbook model. Her worksheet kept coming back looking normal, which was wrong. I couldn't figure out why until I reviewed her EEG data, which showed elevated theta waves in the frontal regions during cue exposure tasks. That pointed to a different neural profile than the classic reward-circuit dysfunction. The workaround was simple but time-consuming: I added a column to my worksheet specifically for atypical neural markers and created a secondary mapping layer that connected those markers to treatment implications rather than the standard addiction framework. It took me another three sessions to rebuild her profile properly, but it ultimately led to a different treatment approach that actually worked for her. The lesson here is that the worksheet needs to be flexible enough to accommodate outliers, and most commercial templates I've seen don't build in that flexibility.
What This Tool Can't Do
Let's be honest about the limitations. A Neuroscience Of Addiction Worksheet will never replace a comprehensive clinical assessment. It's a supplementary document, not a diagnostic instrument. It also assumes you have access to enough baseline information to make meaningful neural mappings, which isn't always the case in underfunded clinics or fast-turnaround settings. In those environments, you're filling boxes with guesswork, and that's worse than useless because it creates false confidence. I've seen it happen. The worksheet gives the impression of rigor without delivering it. Another limitation is the static nature of the format. Addiction neurobiology changes over time. The brain adapts. A worksheet created at the beginning of treatment can become outdated within months, sometimes weeks, if the person's neurochemistry shifts significantly due to medication or sustained abstinence. I recommend updating these documents at least every 90 days for active cases, and immediately if there's a relapse or a change in pharmacological treatment.
Get the Full Details

Getting Started
If you want to build your own template, start with these sections: behavioral timeline, trigger inventory, neural circuit mapping, reinforcement type classification, and treatment alignment notes. That's the core. Everything else is optional depending on your use case. There are downloadable versions circulating in academic and clinical communities. Look for ones that include the extended amygdala and stress system components as separate mapping areas, since those are where most simplified templates fall short. The field has been moving toward integrating these worksheets with digital tracking tools. There are now apps that sync patient-reported cravings and triggers to a neural mapping interface in real time. It's not perfect yet, but it's closer to what clinicians actually need than the paper-based versions that dominated the last decade. If you're working in an academic setting, the paper format is still fine. For clinical practice, look into the digital hybrids.