What Actually Changed in Hip Replacement Around 2022
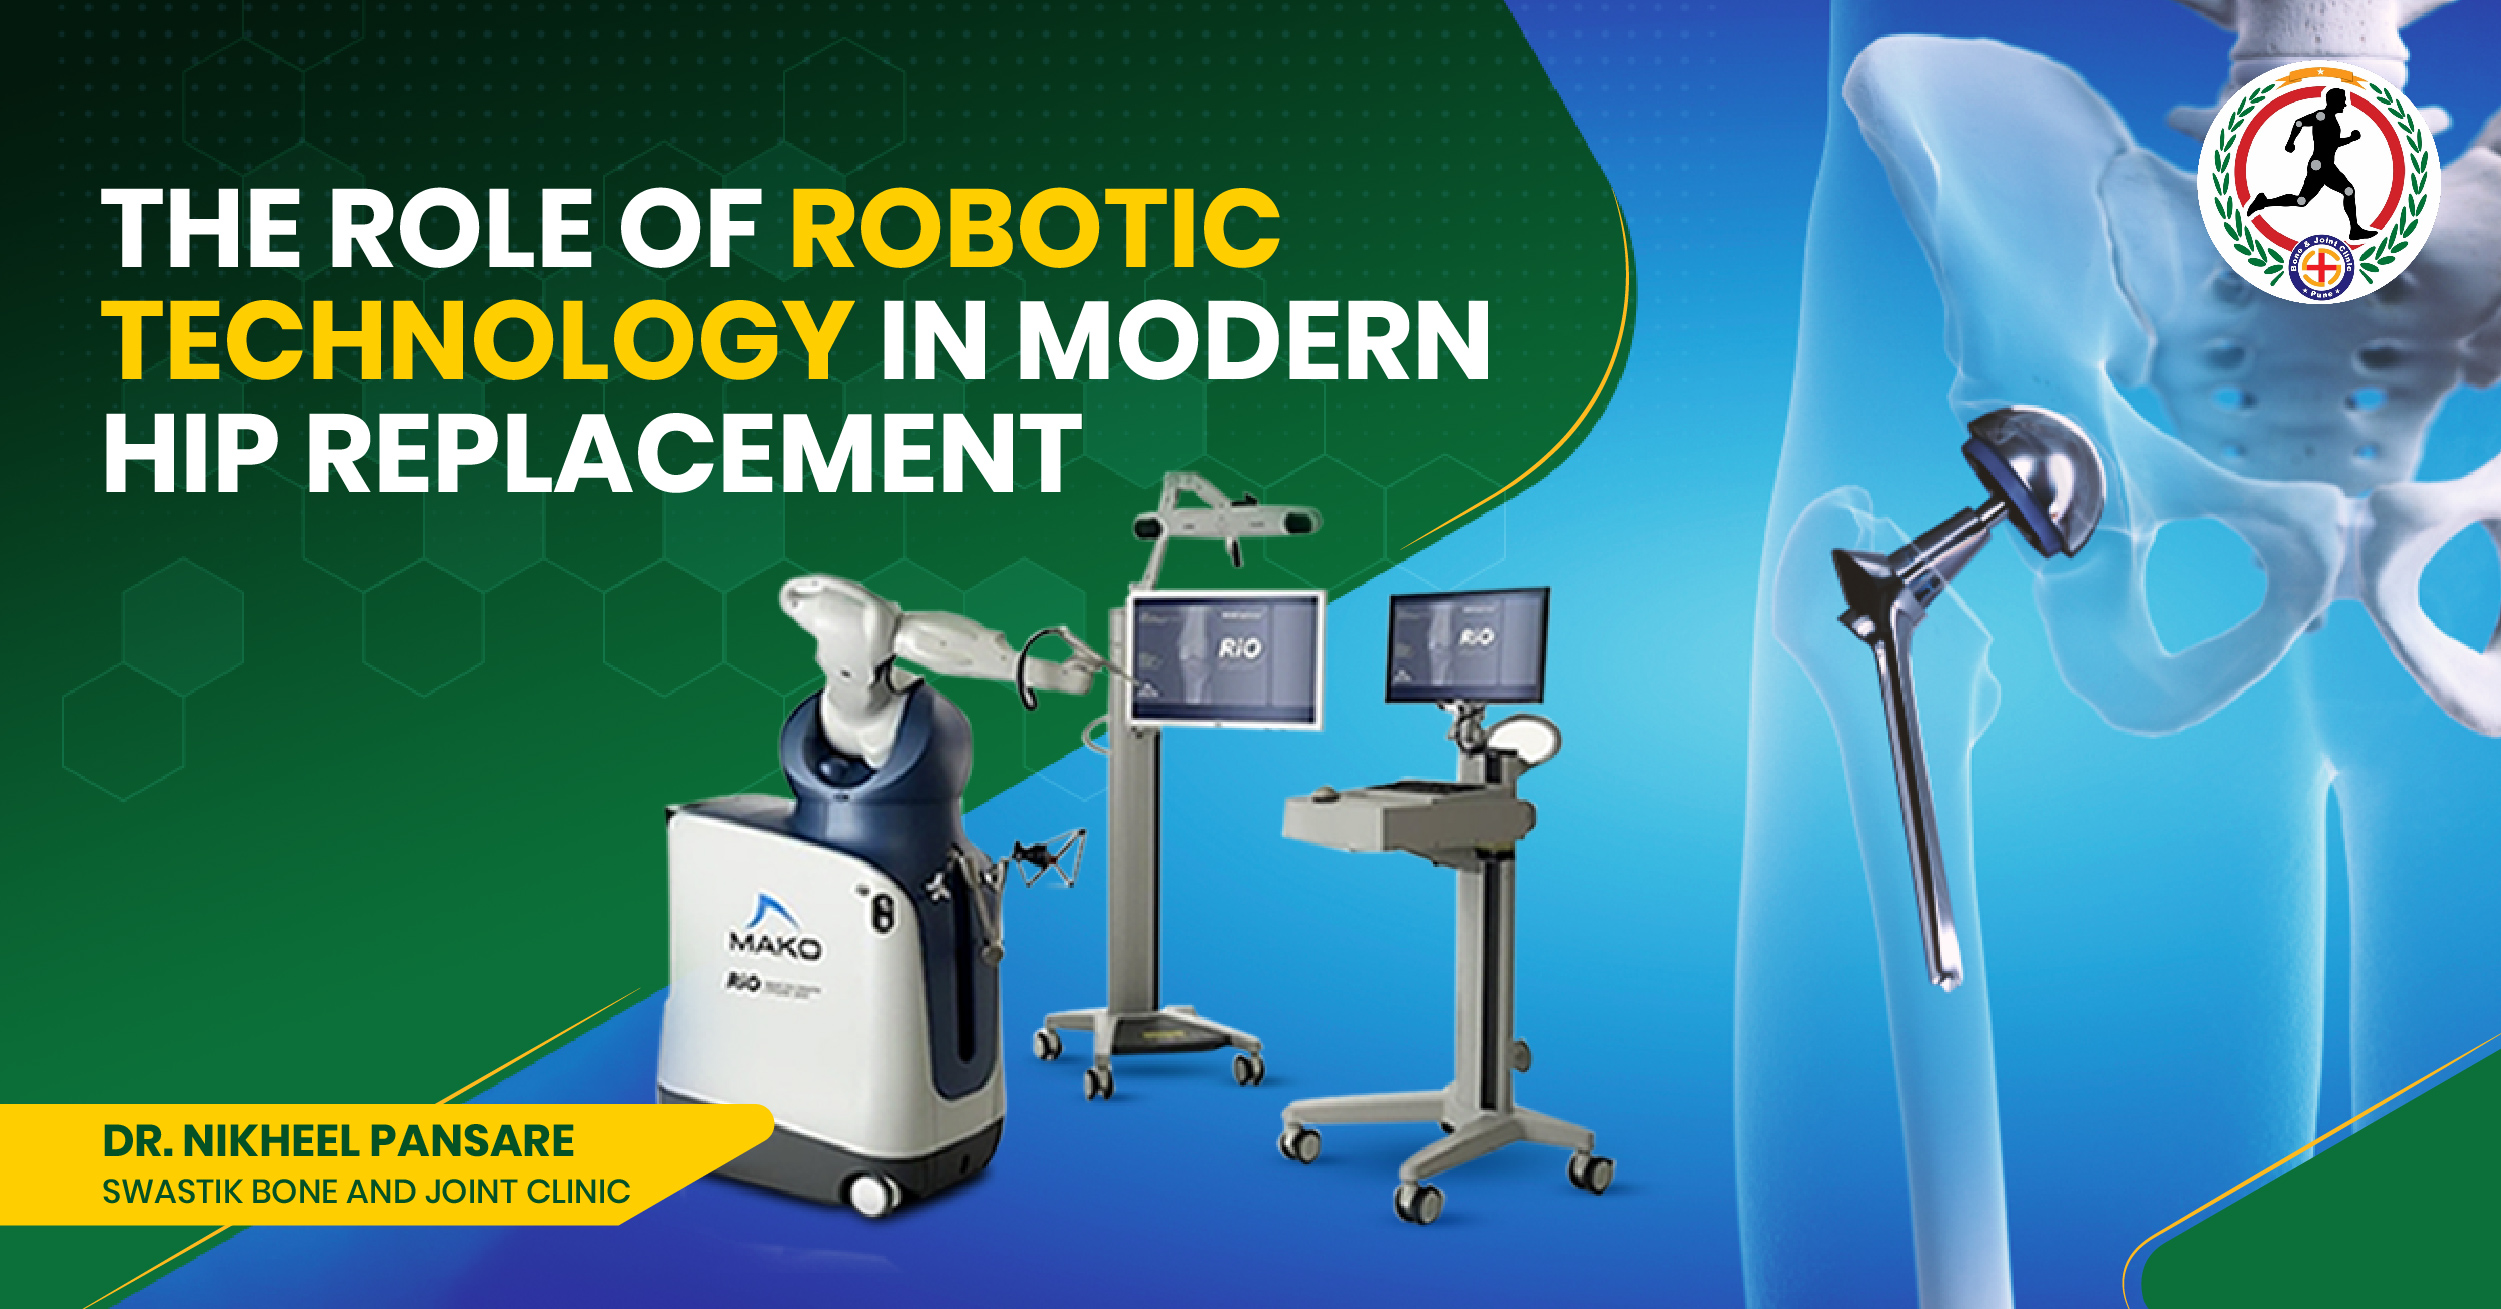
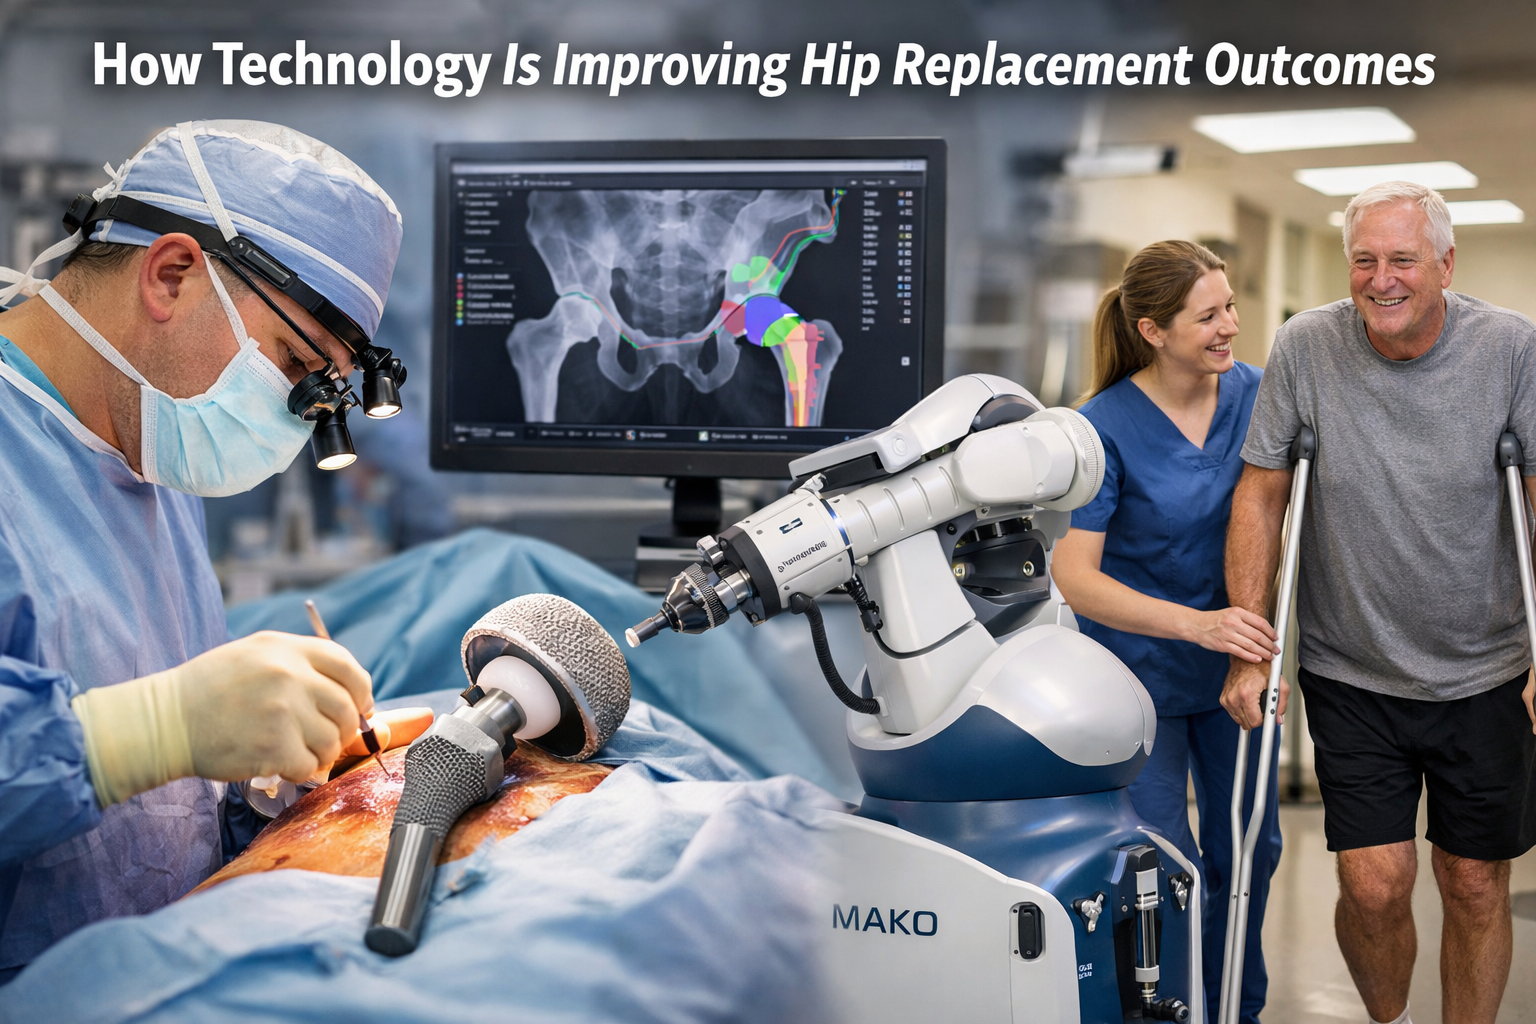
The big shift wasn't a single invention. It was a convergence of things that had been floating around for years finally landing in standard practice. Robot-assisted systems became more affordable and easier to use. 3D printed implants moved from experimental to routine for complex cases. Bearing surfaces got cleaner. Software got sharper. None of it is magic. It just works better than it did five years ago. If you're looking at this because you or someone you know is facing a hip replacement, start by understanding what the different implant options actually mean for your specific anatomy. The technology is there to help, but it's not a substitute for a surgeon who understands biomechanics and has done enough of these to recognize when something is about to go wrong. Robot-assisted systems, primarily Stryker's Mako platform, were the headline in 2022. The idea is straightforward: you get a CT scan, the software builds a 3D model of your hip, and during surgery the robot guides the bone preparation. The surgeon still does the work. The robot just prevents the saw from going where it shouldn't. In practice, this usually means more accurate component positioning, which matters because a few degrees of error can change leg length and stability enough to cause a dislocation later.
The other major thread was 3D printed porous titanium implants. These have a trabecular structure that mimics real bone. Bone grows into the pores. That's called osseointegration. Standard smooth implants don't do this as well. The result should be a more durable fixation, especially in younger patients or people with lower bone density where a standard press-fit might loosen over time. The catch is cost and availability. Not every hospital has these, and insurance doesn't always cover them for standard cases. Bearing surfaces also got a refresh. Ceramic-on-ceramic has been around forever but was always expensive and carried a small risk of squeaking. In 2022, the newer generations of ceramic are significantly quieter and less prone to that issue. Ceramic-on-polyethylene remains the workhorse for most patients because it's proven and cheap. Cross-linked polyethylene continues to improve, too, with oxidation rates dropping each generation.
How the Surgery Actually Works Now
I'll walk through the robot-assisted pathway since that's where most of the visible change happened. You get pre-op imaging, usually a CT scan specifically for surgical planning. This isn't the same as a standard X-ray. The CT data feeds into the planning software where the surgeon sets things like cup angle, leg length restoration, and femoral stem size before you ever go into the OR. During surgery, the patient is positioned, and the robot's tracking array is attached. The system registers your anatomy by having the surgeon move the hip through its range of motion. Then the bone preparation begins. The robotic arm constrains the saw to the planned cuts. If you try to cut outside the planned zone, the machine resists. It's not autonomous. The surgeon controls every move and can override at any time. This typically adds about 15 to 20 minutes to the procedure compared to a fully manual approach. Some surgeons love this. Others find it slows them down unnecessarily for straightforward cases. Your mileage will vary based on who you're seeing and how much experience they have with the system.
Get the Full Details

For non-robotic cases, the improvements are more subtle. Better instrument sets, improved cementing techniques, and more anatomical stem designs. Don't sleep on these. A well-executed traditional approach by an experienced surgeon often beats a robotic approach by someone still learning the system.
A Specific Problem I Ran Into
One thing nobody talks about enough is how pre-op planning software can fail when patients have unusual anatomy. I dealt with a case last year where the patient had a severe developmental dysplasia correction from childhood surgery. The CT-based plan kept wanting to place the cup in a position that would have been mechanically unstable once implanted. The software didn't account for the scar tissue and altered anatomy from the prior procedure. We ended up abandoning the robotic plan and going manual, using intraoperative navigation as a backup rather than full robotic guidance. It took longer but was safer. Always ask your surgeon what happens if the technology doesn't cooperate. Their answer tells you more about their experience than their willingness to use the robot. The biggest misconception is that newer technology equals better outcomes. It doesn't automatically. A 2022 study tracking over 10,000 hip replacements found that surgeon volume was a far stronger predictor of success than whether they used robotics or not. High-volume surgeons using conventional techniques outperformed low-volume surgeons using the latest robotic systems. Pick your surgeon first. The technology is secondary. Another thing people overlook is the role of soft tissue management. All this talk about implants and robots and bearings, but the muscles and tendons around your hip matter enormously for recovery and function. Minimally invasive approaches are supposed to preserve more tissue. In practice, some surgeons use a small incision and still do significant soft tissue disruption because they're comfortable with their approach. Ask your surgeon directly about which muscles they split or detach and why. Their answer should be specific and honest.
The Downsides Nobody Highlights
Robot-assisted surgery requires a CT scan. That means additional radiation exposure, though it's relatively low. More importantly, it adds cost. The per-case expense for robotics can run several thousand dollars on top of the procedure itself. Insurance coverage varies wildly. Some plans cover it. Some classify it as experimental. Get that sorted before you schedule anything. 3D printed implants have a longer lead time because they're often custom-ordered. If you need surgery soon, you might not be able to use one. There's also a theoretical concern about long-term outcomes with custom implants, since there's less real-world data compared to off-the-shelf designs. They're promising, but they're not proven over decades the way standard implants are. Newer ceramic bearings are quieter but more expensive. For older patients or those with lower activity levels, the squeak risk was never a meaningful problem anyway, so the upgrade provides limited practical benefit. You're mostly paying for a marginal improvement in a scenario where that marginal improvement may not matter to you.
What to Actually Ask Your Surgeon
How many of these do you do per year? What's your dislocation rate? Do you use robotics routinely or only for specific cases? What implant brand and type do you prefer and why? What happens if the robotic plan doesn't work intraoperatively? How do you handle soft tissue balancing? These questions are more useful than asking whether the hospital has the newest equipment. The answers will tell you whether your surgeon actually uses the technology thoughtfully or just has a shiny toy they want to play with. Recovery timelines have improved across the board but not because of implants. They improved because of better pain management protocols, earlier mobilization, and refined surgical techniques. Expect to be walking the same day or the next morning in most cases. Full recovery typically takes three to six months depending on your age, fitness, and the complexity of your case. Don't believe anyone who says you'll be back to normal in two weeks. That's not realistic for almost anyone. The technology in 2022 is genuinely better than it was a decade ago. It's not transformative. It's incremental. And incrementally better is still worth something, especially when you're the one going under the knife.