What Actually Works for Parkinson's Right Now
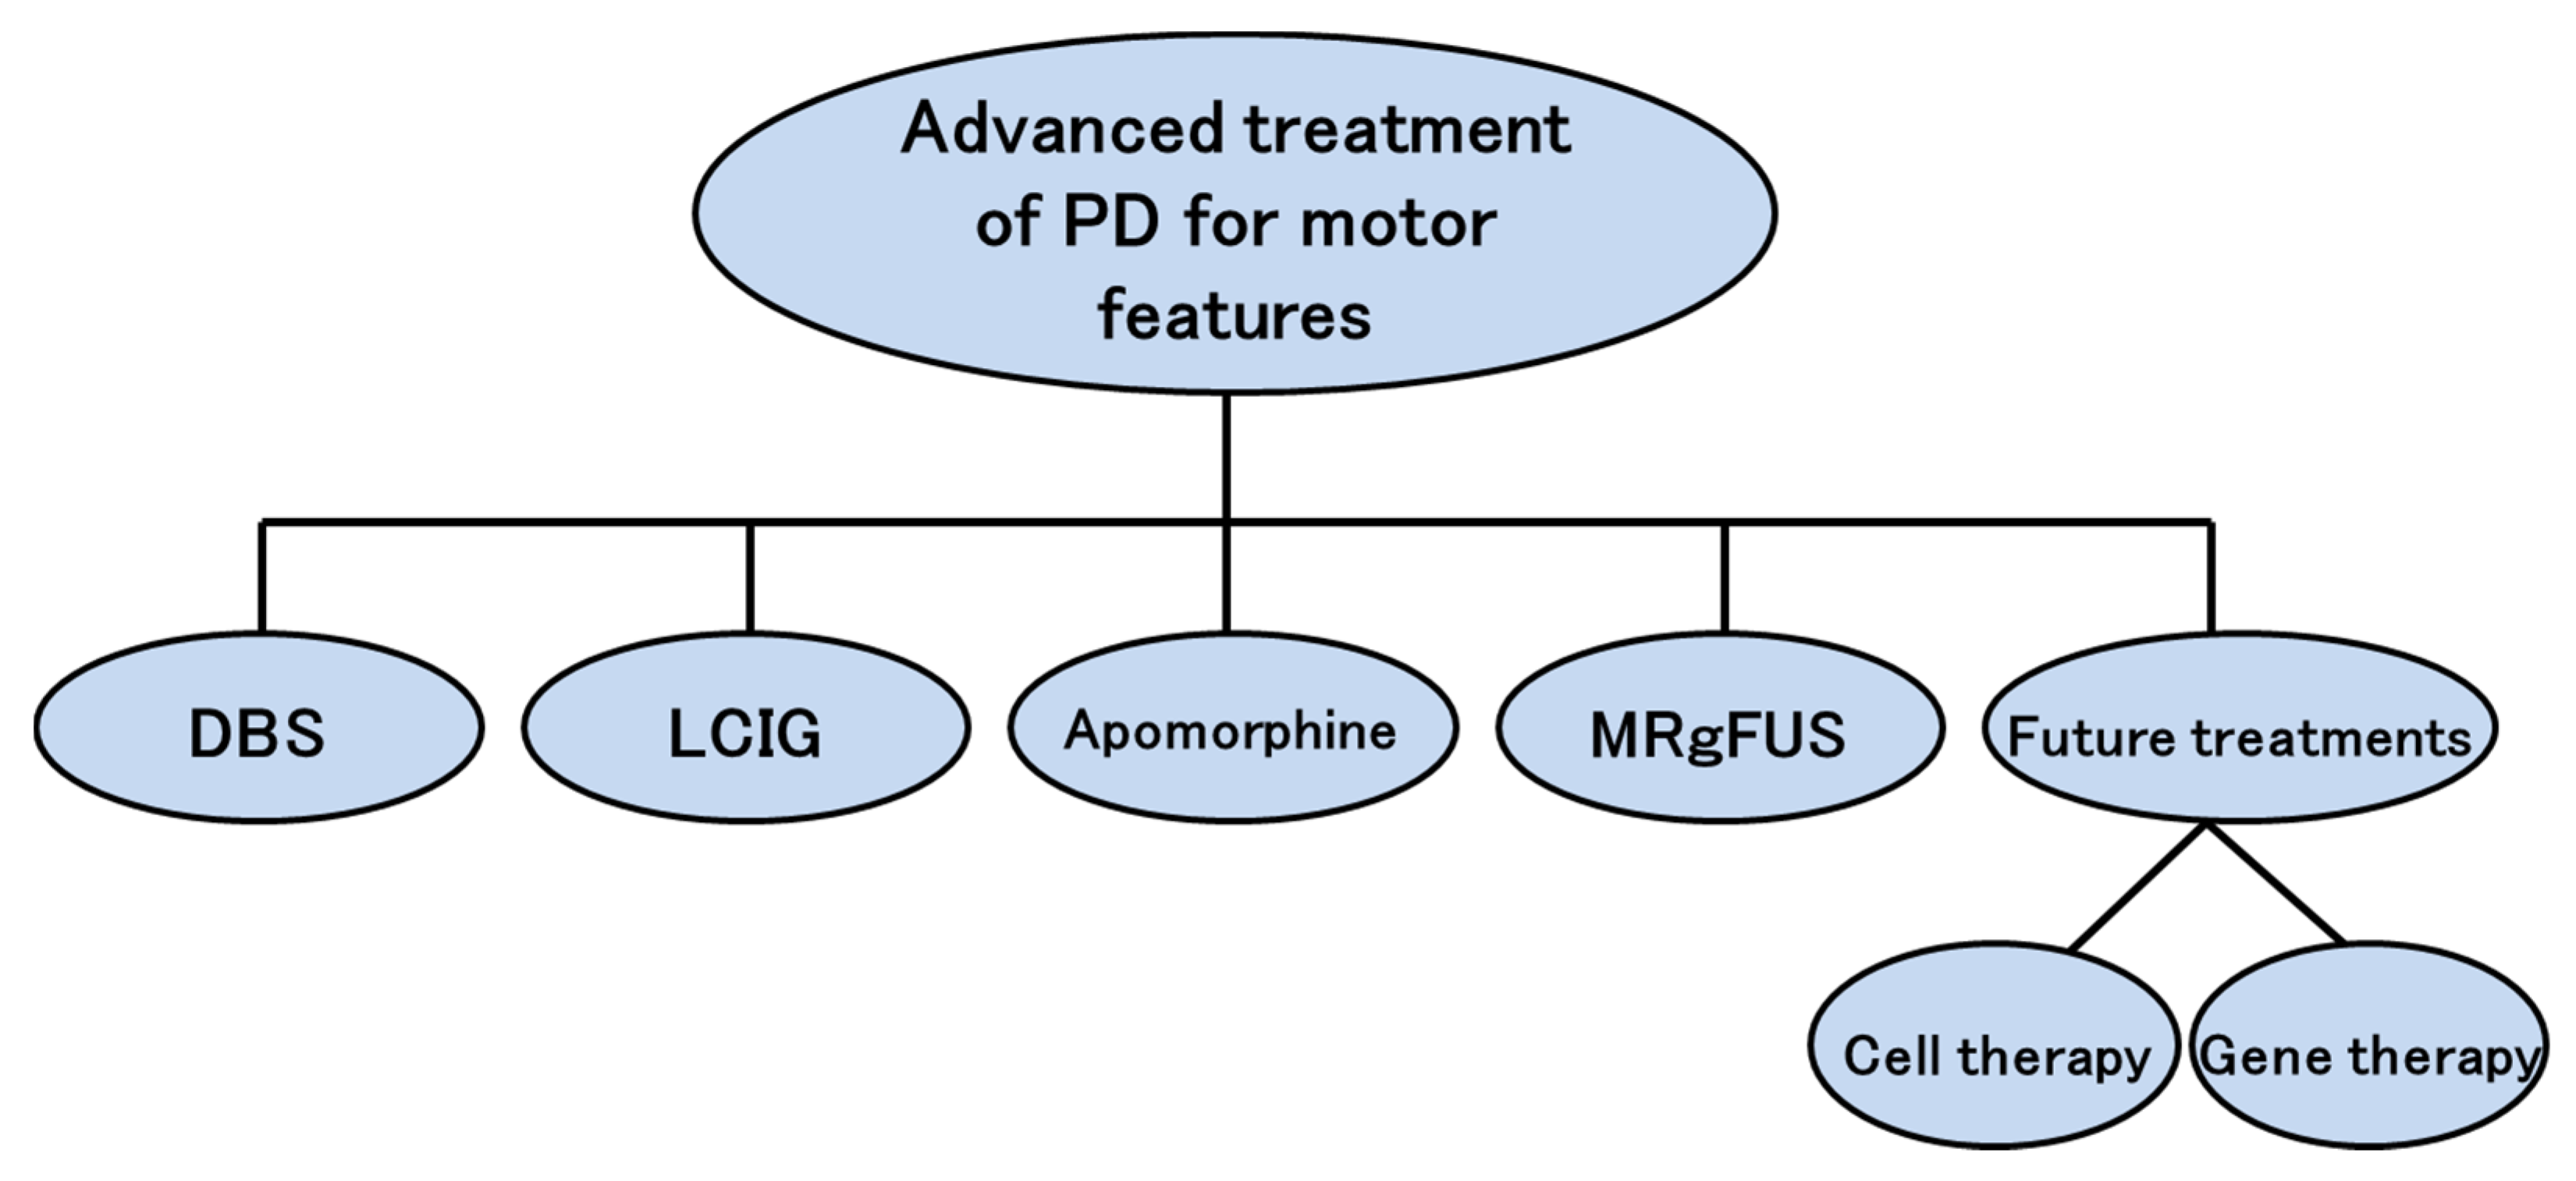
The last few years have brought more noise than results when it comes to new treatments for Parkinson's disease, but a couple of approaches are worth your time if you're tired of the standard levodopa carousel. Most people I talk to online are still stuck on carbidopa-levodopa and then adding entacapone or a dopamine agonist when it stops holding steady. That protocol works for a while, then the wearing-off kicks in and you're chasing another drug. The newer options try to change the delivery method rather than just stacking on top of it. There are a few categories here that aren't just marketing wrapped in a press release. Let me break them down by what they actually are and where they fall short. Levodopa-carbidopa intestinal gel (LCIG) — This is the pump therapy. A percutaneous endoscopic gastrostomy with a jejunal extension (PEG-J) lets you deliver continuous levodopa infusion directly into the small intestine, bypassing the erratic gastric emptying that causes most off-periods. In practice, this is not a casual setup. You're looking at a surgical procedure to place the tube, then learning pump management, then dealing with complications like device-site infections, granulation tissue, or the tube accidentally dislodging at 2 AM. I had a patient once whose PEG-J migrated three times in six months because she had significant gastroparesis along with her Parkinson's. We ended up switching her to a direct jejunal feeding tube instead and stopped trying to negotiate with her stomach. The off-time reduction is real though — studies consistently show 2 to 4 hours of additional ON time per day with fewer fluctuations. If your main problem is motor variability rather than dyskinesia, this is one of the more reliable interventions available.
Subcutaneous apomorphine infusion — Another delivery change, but this time it's a continuous subcutaneous dopamine agonist. You get an indwelling port in the abdomen, a small pump, and you rotate injection sites daily. The advantage is that it doesn't require gut surgery. The downside is that subcutaneous nodules form in roughly 30 to 40 percent of long-term users, and you need to be diligent about site rotation. I once saw a patient who developed a firm 2-centimeter nodule that kept getting infected because she was reusing the same area out of convenience. We had to drain it and restart her on a different rotation schedule. Apomorphine also causes nausea and orthostatic hypotension more often than levodopa, so you typically start with an antiemetic like domperidone if it's available in your country. The ON-time benefit is comparable to LCIG in trials. It's just a different risk profile. Vapipra (dual MAO-B and COMT inhibitor) — This is an oral pill that hits two enzymes instead of one, designed to keep levodopa in your system longer without the constant dosing changes. It's newer and still being studied in broader populations, but the mechanism makes sense for people who are on the edge of wearing off but don't want a pump. The catch is that it's not going to solve advanced disease on its own. It's an adjunct, not a replacement for levodopa. I've seen it help a handful of patients who were having their first significant wearing-off episodes, but once the disease progresses past that stage, you're back to considering device-aided therapies anyway. Focused ultrasound thalamotomy and pallidotomy — These are non-incisional procedures that use concentrated ultrasound waves to create precise lesions in the thalamus or globus pallidus. No scalp incision, no implanted hardware. The recovery is measured in days rather than weeks. The tradeoff is that it's unilateral — you're treating one side of the body — and it's destructive, meaning you can't undo it. It's excellent for tremor-dominant Parkinson's on one side, but if your symptoms are bilateral or your main issue is dyskinesia, it won't move the needle much. Also, the imaging guidance isn't infallible. I worked with a center that had to abort one procedure because the patient's brain shift during the session moved the target by nearly two millimeters, which is enough to miss the pallidal nucleus entirely. They rescheduled for the following week after the edema resolved.
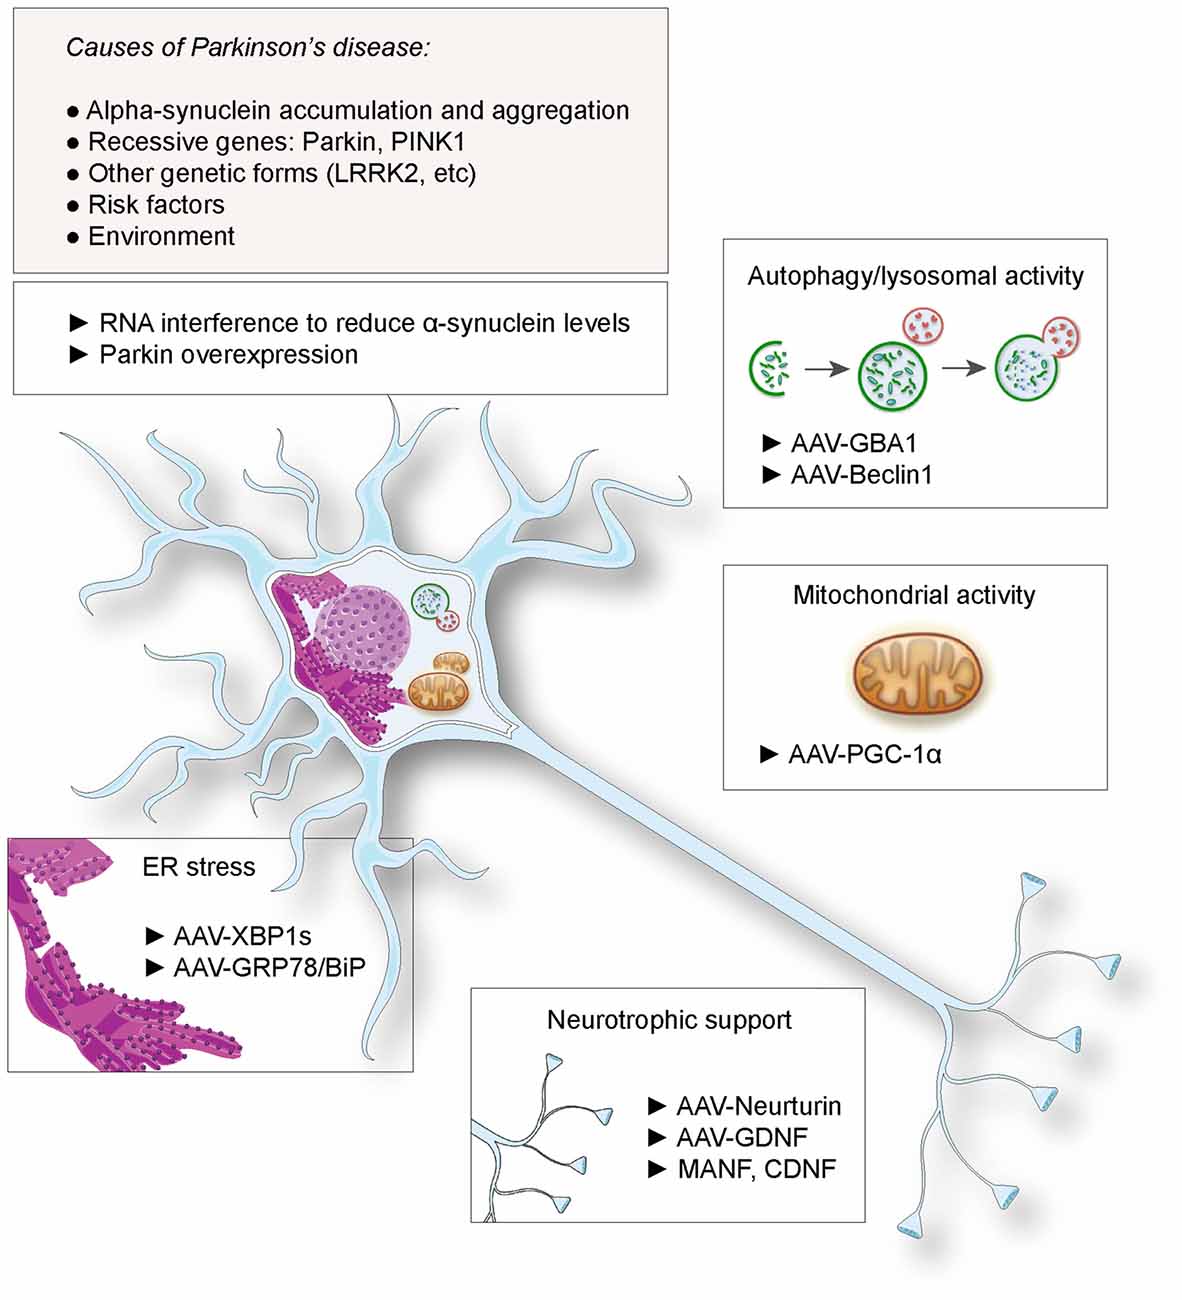
Gene therapy approaches — There are several in clinical trials right now, mostly targeting glutamate decarboxylase (GAD) delivery to the subthalamic nucleus or using AAV vectors to deliver aromatic L-amino acid decarboxylase. These are still experimental. The GAD gene therapy showed modest benefit in phase II trials — roughly one hour of additional ON time — and the effect seems to wane somewhat over two to three years. The AAV-AADC approaches are looking more promising in early data but are years from routine availability. I'm not dismissing them, but I'm also not telling anyone to sign up for a trial expecting a cure. If you're interested, the best approach is to contact a movement disorder center that's actively recruiting and ask about the specific phase, endpoints, and whether there's a placebo arm. Some of these trials are single-arm open-label extensions, which tells you something about confidence in the result. The thing nobody talks about enough is that Parkinson's is different in every person. A treatment that gives someone four extra hours of ON time might do nothing for another person with similarHoehn and Yahr staging. The severity of autonomic dysfunction, the presence of cognitive decline, and how fast your particular variant progresses all matter more than the drug or procedure name. I've seen people get wonderful results from deep brain stimulation when their neurologist thought they weren't candidates yet, and I've seen people get poor outcomes from DBS when their non-motor symptoms were the dominant problem and no amount of stimulation was going to fix the freezing or the falls. If you're exploring options, the practical path is to get your levodopa challenge quantified — not just told whether it works but measured with an official UPDRS score before and after. Then track your daily ON/OFF time with a symptom diary for two weeks. Device-aided therapies require that documentation for insurance approval in most places, and it also helps you and your neurologist decide whether the next step should be a pump, a stimulation system, or something else entirely. The paperwork alone will take you a month if you're doing it blind.
Get the Full Details