Let's Talk About Estimating How Old a Newborn Actually Is
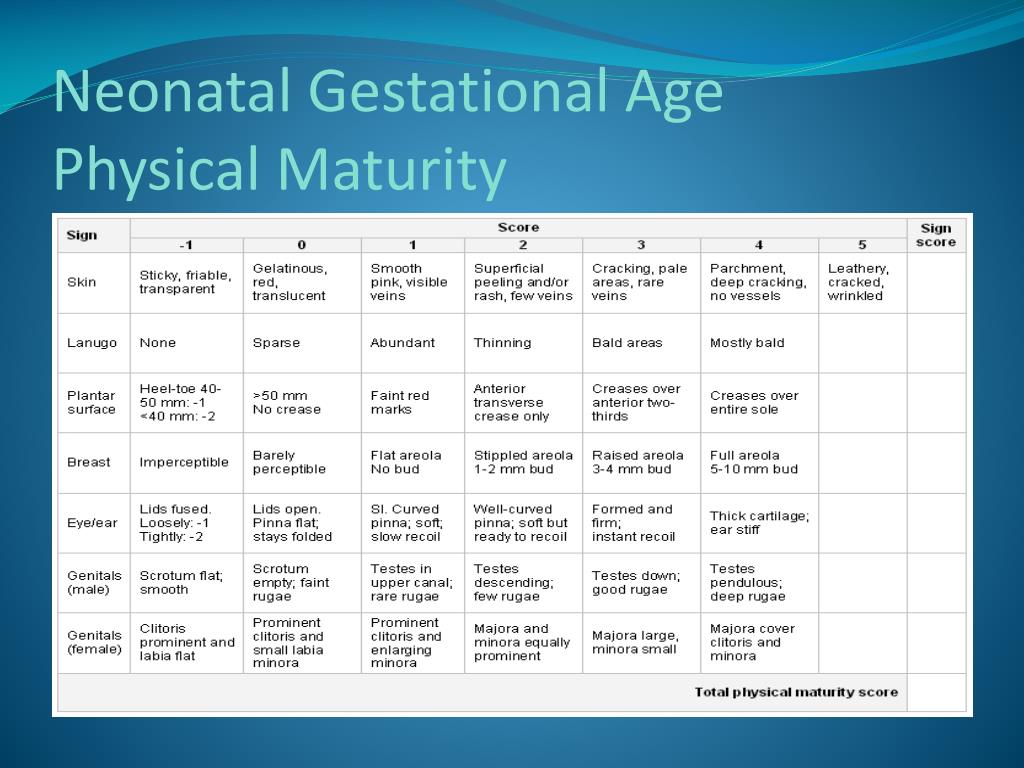
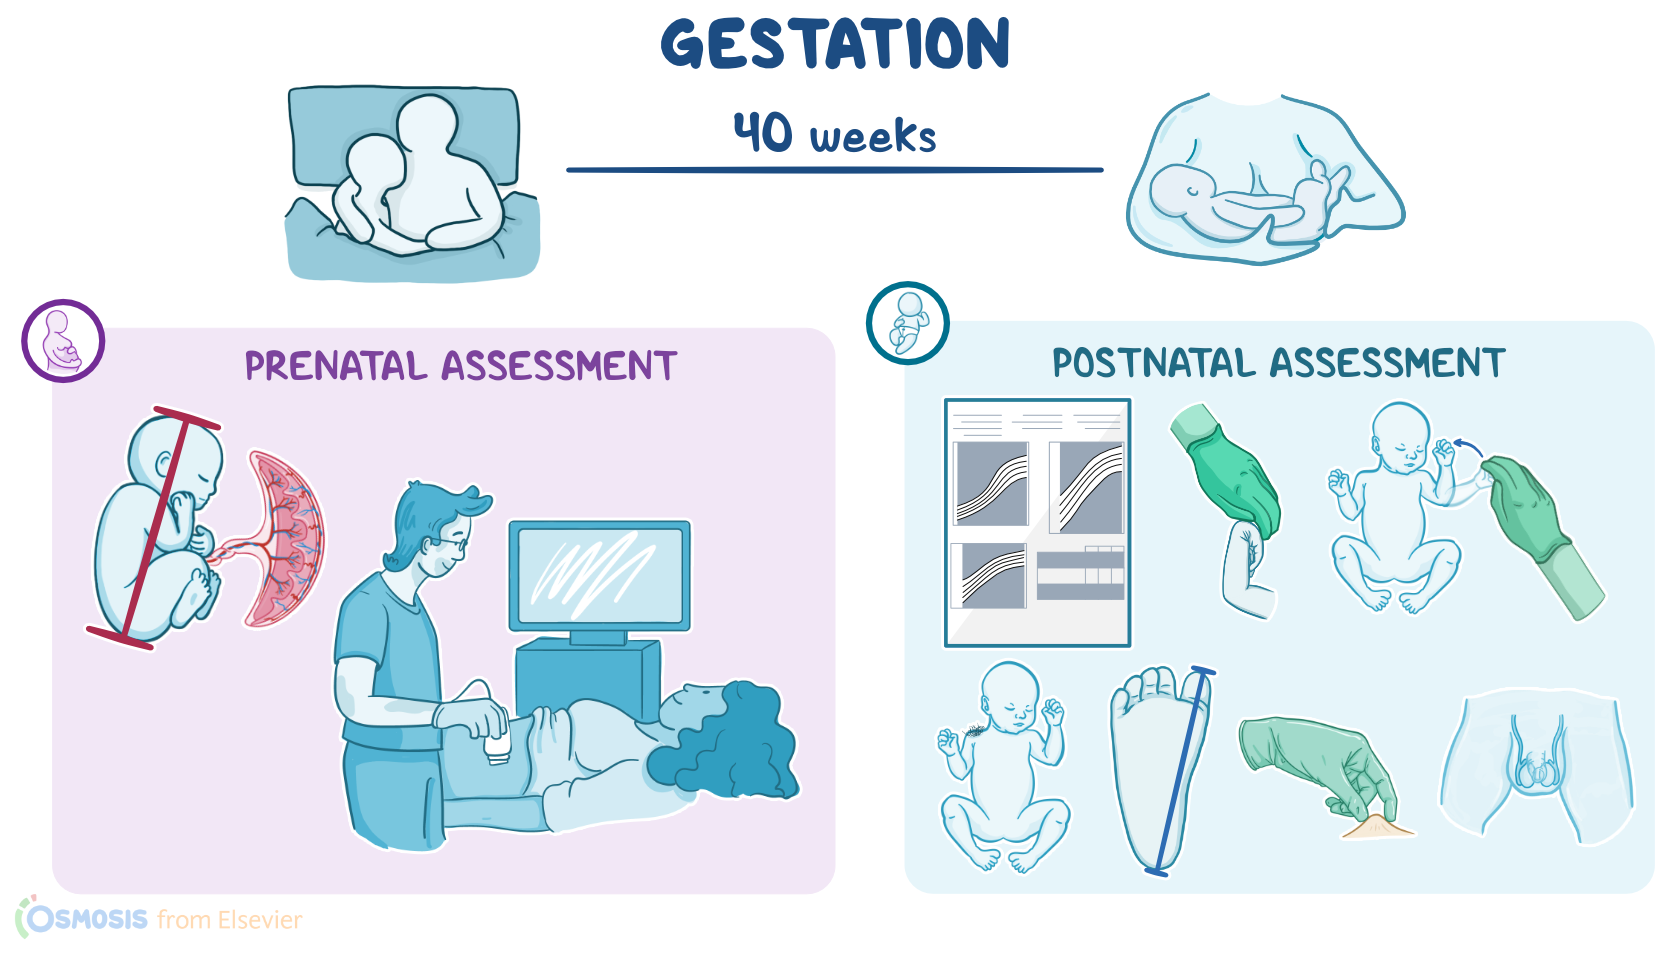
There are two ways to figure out gestational age, and they are not interchangeable. One relies on dates. The other relies on what the baby looks like when it arrives. Most people mess this up because they treat them like they produce the same number. They don't. The Ballard Score is the physical exam method. It was developed by Dr. Jeanne L. Ballard in 1979 and updated from the original New Ballard Score. You look at six neuromuscular maturity signs and six physical maturity signs, assign a score to each, and add them up. The total maps to a gestational age in weeks. The neuromuscular ones include things like posture, square window, arm recoil, popliteal angle, scarf sign, and heel to ear. The physical ones cover skin texture, lanugo, plantar creases, breast tissue, eyes and ears, and genitals. Each category gets a score from minus 2 to plus 5, and the summed score translates roughly from 24 weeks to 44 weeks.
Why Newborn Gestational Age Assessment Still Matters in Practice
The reason this exists at all is that dating pregnancies by last menstrual period is unreliable. A lot of people have irregular cycles. Some don't know the date. Some ovulate early or late. When you only have a missed-period estimate, you can be off by a week or more. That matters when you are deciding whether a tiny preterm infant needs surfactant, whether a post-term baby has placental insufficiency, or whether a baby labeled preterm actually has a growth restriction because the dates are wrong. I ran into a case a few years ago where the ultrasound dated a pregnancy at 36 weeks based on a first-trimester scan, but the Ballard Score on the delivered infant read 32 weeks. The mother had bleeding in the second trimester and stopped having routine prenatal visits. The ultrasound technician had measured the biparietal diameter without accounting for the fact that this was a small-for-gestational-age fetus. The physical exam told a different story. I recalculated using the plantar crease and genital maturity specifically, which tend to lag less in growth-restricted babies, and confirmed the 32-week reading. We changed the NICU care plan accordingly. If we had trusted the date alone, we would have under-treated a truly preterm infant.
The Practical Workflow
Assess the baby within the first 12 hours of life. After that, the body changes. Skin starts desquamating. Vernix dries off. The neuromuscular tone shifts. You lose accuracy fast. I usually do the exam in two passes: neuromuscular first while the baby is quiet, then physical while I am positioning for the heels-to-ear test. Do not assess immediately after a difficult delivery. An infant who just had forceps extraction or significant resuscitation may have altered muscle tone. Wait until the baby stabilizes. I typically wait 30 to 60 minutes if the resuscitation was lengthy. The score will be more reliable. Here is the thing most people skip: document each item separately. Don't just write a total score. Record the plantar crease grade, the breast tissue grade, the skin texture. If someone questions the gestational age later, those individual items are what matter. A total score of 2 can come from many different combinations, and some combinations are less reliable than others.
Get the Full Details

Common Pitfalls
The biggest error source is the square window test. If the infant's wrist is stiff from hypocalcemia or I've pressed too hard on the dorsal side, the angle looks smaller than it should be, and the score drops. I always support the forearm fully and apply gentle, steady pressure toward the palm. Never force it. The heel-to-ear maneuver is another minefield. I have seen it done aggressively enough to cause bruising on the occiput. That is unnecessary. The infant's head should rest on the table, and you gently draw the heel toward the ear. If the leg won't go past the chin, note the limit. Don't push further. Post-mature infants with peeling skin can throw off the skin texture score entirely. I tend to weight the neuromuscular signs more heavily in those cases, since post-maturity skin changes are predictable and the neuromuscular system matures on a tighter schedule.
When the Ballard Score Fails
Let me be blunt about the limitations. The Ballard Score has a margin of error of roughly plus or minus two weeks. In a 28-week preterm infant, that means you could be off by a full week. That is clinically significant. For macrosomic infants, the score tends to overestimate gestational age because the physical maturity signs are inflated by excess subcutaneous tissue. For infants with intrauterine growth restriction, it can underestimate, though the neuromuscular components tend to hold up better than the physical ones. If you have a reliable first-trimester ultrasound, use it. First-trimester crown-rump length dating is accurate to within plus or minus five to seven days. After that, the accuracy degrades. Second-trimester dating is plus or minus ten to fourteen days. Third-trimester dating is useless for gestational age assignment because fetal size varies wildly at that point. I routinely see third-trimester estimated due dates that are off by three weeks compared to first-trimester scans. Believe the first-trimester scan every time. When ultrasound dating and the Ballard Score disagree by more than ten days, and you lack a first-trimester scan, I recommend repeating the physical exam on day two or three. Sometimes the initial assessment is compromised by delivery trauma, edema, or temperature instability. A repeat exam often converges closer to the true gestational age.
What the Numbers Actually Mean
A Ballard Score mapping to 34 weeks is not the same clinical situation as a baby dated at 34 weeks by a first-trimester ultrasound. The ultrasound-dated baby has a more precise estimate. The physically assessed baby has a range. When communicating with families, I phrase it as approximately 34 weeks, with a possible range of 32 to 36 weeks, rather than stating it as an exact number. That prevents unnecessary anxiety when follow-up evaluations shift the estimate slightly. For extremely preterm infants below 28 weeks, the Ballard Score becomes less discriminative. The neuromuscular differences between 24 and 27 weeks are subtle, and the physical signs overlap considerably. In these cases, I rely more heavily on the earliest available ultrasound and clinical judgment. No single tool solves this completely. The bottom line is that Newborn Gestational Age Assessment is a practical skill, not a theoretical exercise. The Ballard Score gives you a number, but the number comes with a confidence interval. Knowing when to trust it, when to question it, and when to fall back on earlier ultrasound data is what separates a reliable assessment from a guess.