What you need to know before you start
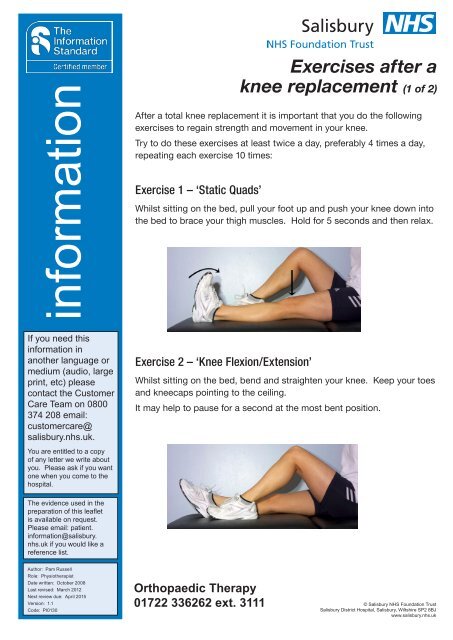
The NHS pre knee replacement exercises are a standard rehabilitation protocol given to patients awaiting total knee replacement surgery. The goal is straightforward: strengthen the muscles around the knee joint so recovery goes smoother and faster once the operation is done. Most patients get a leaflet from their hospital outpatient clinic, but the instructions are often vague. I have spent years helping people actually do these exercises correctly, and the gap between what the leaflet says and what actually works is pretty significant. You are not going to find a downloadable PDF with the full program because the NHS does not publish one centralized resource. What exists are scattered leaflets from different trust areas, each with slightly different recommendations. The core exercises are consistent though. Here is what you will typically be asked to do. Quad sets come first. Sit or lie down with your leg straight. Tighten the muscle on the top of your thigh by pressing the back of your knee into the surface. Hold for five to ten seconds, then relax. Repeat ten times per leg. That is it. It sounds too simple, which is why people skip it or do it wrong. The most common mistake is just pushing your knee down without actually engaging the quadriceps. You should feel the muscle harden just above your kneecap. If you do not feel that, you are not doing it right.
Straight leg raises are next. Lie on your back with one knee bent and the other leg straight. Tighten your thigh muscle on the straight leg, lift it about twelve inches off the ground, hold for three seconds, and lower it slowly. Do ten reps per leg. This builds the hip flexor and quadriceps strength needed for walking after surgery. The failure point here is bending the hips too much. Keep your pelvis flat against the floor. I had a patient once who kept arching her lower back during these, which completely neutralized the exercise and made her more uncomfortable. She was getting zero benefit from it. We switched her to a shorter range of motion with a towel rolled under her knee, which kept her spine neutral and actually activated the quads properly. Ankle pumps are trivial but important. Move your foot up and down through the full range of motion. This keeps blood circulating and reduces the risk of deep vein thrombosis while you are waiting for surgery. Do these every hour while awake. Nobody really argues about this one. Heel slides involve lying on your back and slowly bending your knee by sliding your heel toward your buttocks, then sliding it back out. Go only as far as is comfortable. Ten to fifteen reps. This maintains knee flexion range, which matters because stiff knees post-surgery lead to worse long-term outcomes. The tricky part is not forcing the range. If you have pre-existing stiffness from your arthritic knee, you might be able to bend it to ninety degrees or more already. That is fine. Do not try to push beyond that on purpose. The exercise is about maintaining what you have, not aggressively gaining new range before surgery.
Bridges build glute and hamstring strength. Lie on your back with both knees bent and feet flat on the floor. Lift your hips until your body forms a straight line from shoulders to knees. Hold briefly, lower slowly. Ten reps. Weak glutes are a common problem going into knee replacement and they make post-op physio significantly harder. Stronger glutes mean better hip control, which reduces strain on the new knee during walking and stair negotiation. Seated knee extensions are another standard one. Sit in a chair with your back straight. Straighten one leg out in front of you until it is parallel with the floor, hold for a few seconds, then lower it. Ten reps per leg. This specifically targets the quadriceps, which atrophy quickly when you are limping around because of knee pain. Resistance band work is sometimes included if your physiotherapist provides them. Standing lateral band walks target the hip abductors. Place a resistance band around your ankles or just above your knees, bend your knees slightly, and walk sideways for ten steps in each direction. This stabilizes the knee during movement and addresses a common weakness that people overlook until after surgery when it becomes a problem.
Get the Full Details

Why pre-hab matters more than people think
There is solid evidence that doing these exercises for at least two to six weeks before surgery leads to shorter hospital stays and better functional outcomes at three months post-op. The mechanism is simple. Your quadriceps and hip muscles are what you rely on for everything after knee replacement: getting out of bed, walking with a frame, climbing stairs, eventually walking without aids. If you go into surgery with weak legs, the first two weeks are brutal. You are already deconditioned, and the surgery makes it temporarily worse before it gets better. The problem is that knee pain itself makes it difficult to do the exercises consistently. People are in so much discomfort from their osteoarthritis that they avoid using the leg altogether. This creates a vicious cycle: pain leads to less use, which leads to weakness, which leads to more pain and worse function. Breaking that cycle before surgery gives you a real advantage.
A workaround I found useful
One edge case that does not get discussed enough is what happens when you cannot fully extend your knee. Some patients with advanced osteoarthritis develop a flexion contracture, meaning their knee cannot straighten completely. A standard quad set requires the leg to be straight, so if you cannot achieve full extension, the exercise becomes awkward and ineffective. The workaround is to do isometric quad contractions with the knee at whatever angle you can manage. Sit in a chair and press the back of your knee down into the seat while tightening your thigh muscle. Hold for five seconds. Repeat ten times. You are still activating the quad. It is not the same as a full straight-leg quad set, but it is meaningful activation and better than nothing. I ran into this with a patient who had a ten-degree flexion contracture. We spent three weeks doing these modified quad contractions before surgery, and on the day of the operation, his quad activation was significantly better than I expected given his pre-op condition.
What the leaflets leave out
The NHS leaflets rarely mention that you should be doing these exercises daily, not just when you remember. The physiological benefit is dose-dependent. Once a week will not do much. Twenty minutes a day, five to six days a week, is the effective range. Consistency matters more than intensity. You are not trying to push yourself to exhaustion. You are trying to maintain and gradually build strength without aggravating your knee. Another thing most leaflets omit is the importance of pain management timing. If you take your prescribed pain medication about thirty minutes before your exercise session, you can often do more with less discomfort. This is not a suggestion to increase your medication, just to coordinate it with your routine if your doctor has already prescribed something for this purpose.

Limitations and when this does not work
Pre-operative exercises are not a magic bullet. They will not reverse significant joint damage or delay the need for surgery. They also will not help much if you have severe cardiovascular deconditioning, cognitive impairment that prevents you from following instructions, or if you are unable to perform the movements due to another injury or condition. In those cases, the best you can do is what is physically possible and discuss alternatives with your orthopaedic team. Some patients find that certain exercises, particularly straight leg raises and seated knee extensions, actually increase their knee pain rather than helping. If an exercise consistently causes sharp or increasing pain, stop doing it and talk to your physiotherapist or GP. Pushing through pain is not a strategy here. The goal is maintenance and gentle strengthening, not rehabilitation of acute injury. There is also a time constraint. If your surgery is only a few weeks away, spending five to six weeks on pre-hab is unrealistic. In that case, even two weeks of consistent exercise is better than none, but the benefits will be proportionally smaller. The evidence for pre-hab is strongest in the four-to-six-week window before surgery.
Where to find the actual materials
The NHS does not have a single universal document. Your hospital trust will typically provide you with a leaflet at your pre-assessment appointment. Common trusts publish their own versions online. Search for your specific trust name plus "knee replacement pre-habilitation" or "pre-operative exercise programme." The Royal Free Hospital, Guy's and St Thomas', and the NHS Lothian all have their own patient education pages with exercise guidance. These tend to be more detailed than the generic leaflets you might get. If your trust has not given you anything, ask at your next appointment. You have a right to this information, and they should provide it. Sometimes the physiotherapy department can arrange a brief pre-op session where they walk you through the exercises in person, which is worth requesting if you are unsure about technique. The most important thing is to start before you get the official paperwork and to keep at it consistently. The exercises are not complicated, but most people do them inconsistently or incorrectly and then wonder why they are not seeing improvement going into surgery.



