What the Vanderbilt Actually Is and How It Gets Used in Schools
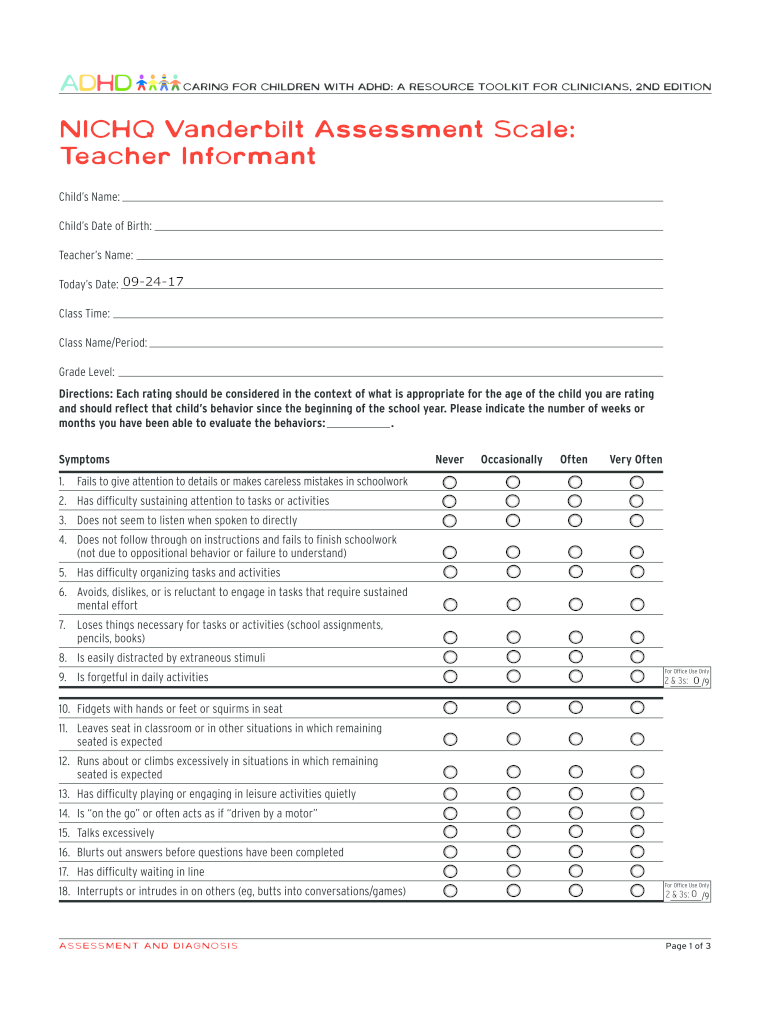
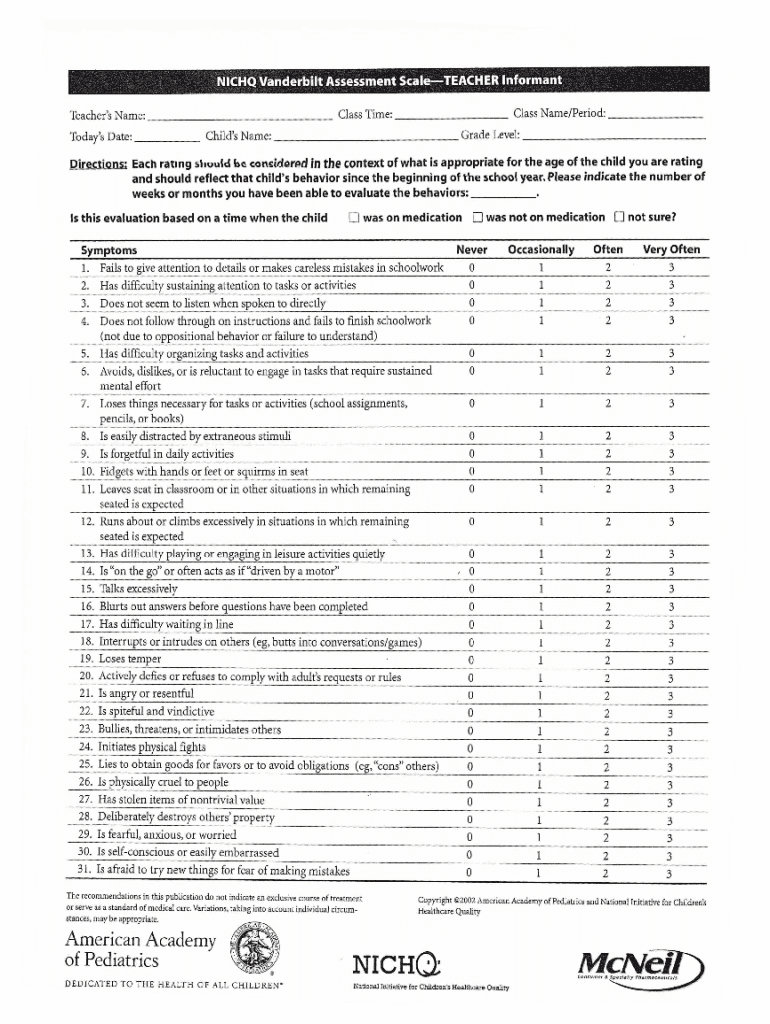
The Vanderbilt Assessment Scale is a behavioral rating tool designed to screen for ADHD and oppositional defiant disorder in children aged 6 to 18. The teacher version is one of two forms — the other being parent — and it serves as a first-line screening instrument rather than a standalone diagnostic. Schools across the U.S. use it routinely because it aligns with DSM criteria and can be administered in about ten minutes. It does not diagnose anything on its own, which is a distinction that gets blurred in practice more often than it should. The Nichq Vanderbilt Assessment Scale Teacher form is available as a free downloadable PDF from the National Institute for Health and Wellness or directly through the Vanderbilt University website. The teacher fills it out based on observed behavior over the past thirty days. There are nine questions mapped to DSM-IV symptoms of inattention, six mapped to hyperactivity-impulsivity, and five additional items that assess impairment across school, social, and family settings. If a teacher marks two or more items in a domain as more than once per month, the child flags positive for that domain. The impairment section requires at least one item rated as somewhat or very much of a problem in two or more settings for the screen to be considered clinically significant. I have filled these out myself and reviewed thousands of them in school psychology practice. The form is straightforward but there are enough edge cases that people mess them up. Here is the one that trips most people up: the impairment section asks about problems in multiple settings — school, home, and social. A child can score positive on the symptom scales and still not meet threshold if they only show impairment at school. Some districts want both symptom and impairment; others accept symptom-only for referral purposes. You need to know which standard your school uses before you hand this to parents or a psychologist, because it changes whether the form gets flagged for follow-up.
Another thing nobody talks about enough is the timeframe. The form asks about behavior over the past thirty days, but the instructions do not emphasize that enough. I had a case where a parent submitted a teacher form that only covered the prior two weeks because the child had just transferred mid-month. The scores looked borderline on the surface, but the limited window made them unreliable. I asked the teacher to complete a fresh form covering a full thirty days, and the second round of responses changed the clinical picture entirely. The kid's symptoms were situational, not pervasive. The scoring itself is not hard, but the interpretation requires nuance. The symptom questions use a Likert scale: not at all, a little, medium, lots. The impairment questions use a three-point scale: not a problem, somewhat a problem, very much a problem. A common mistake is treating medium and lots as equivalent when they are not. Medium means it happens sometimes. Lots means it happens frequently. For ADHD screening, DSM alignment expects the higher end of frequency, so flagging only medium responses as positive inflates false positives. In my experience, this error shows up most often with teachers who want to be helpful and over-flag. They mark medium on several items and then wonder why the district psychologist sends the referral back. One counter-intuitive point: the Vanderbilt is most useful when used longitudinally. A single administration gives you a snapshot. If you administer it quarterly — which some schools do — you can track whether behaviors are improving with intervention or staying stable. The form is sensitive enough to detect meaningful change over three-month intervals, especially when combined with classroom-based behavior logs. I used a system where the homeroom teacher completed the Vanderbilt every trimester while also tracking specific target behaviors on a simple frequency chart. The triangulation made the data far more credible during IEP meetings. Without the daily log, the Vanderbilt scores were just numbers. With the log, you had a narrative that backed them up.
There are limitations you need to accept. The form was normed on a predominantly White, middle-class population in the late 1990s. Cultural bias is a real concern, particularly for multilingual students or children from different socioeconomic backgrounds. A teacher who is unfamiliar with a student's cultural context may misinterpret norms. A child who is quiet in class because of language barriers might look inattentive to someone who does not know the child's home situation. I have seen referrals go forward on the back of a Vanderbilt form where the real issue was English language acquisition, not ADHD. The workaround is simple: pair the form with an observation, a language history interview, and input from bilingual staff before treating a positive screen as sufficient evidence for special education evaluation. The Vanderbilt also does not account for anxiety, trauma, or learning disabilities, which can present with overlapping symptoms. If a child has been through recent disruption at home — a divorce, a move, a death in the family — the form will likely reflect that in elevated scores. This does not mean the data is useless. It means the data needs context. I always recommend adding a brief anecdotal section when submitting the form to a psychologist or evaluation team. Three or four lines about what the child is actually doing in class, not just whether they are fidgeting, makes the difference between a form that gets processed and one that gets requested for clarification. For teachers looking to use this regularly, here is the practical workflow. Download the latest version from the official Vanderbilt site or the NICHD website. Print copies for each student you need to rate, or enter responses digitally if your school uses a platform like IQ+ or Turnitin that supports it. Review the student's behavior over the past thirty days before filling it out — do not rely on recent memory alone. Be specific in your ratings. "A little" and "medium" carry different weights. Score the impairment section honestly, even if you feel pressure to minimize. Submit the form with a brief note about any recent contextual changes affecting the child. Keep a copy for your records. That is it.
Get the Full Details
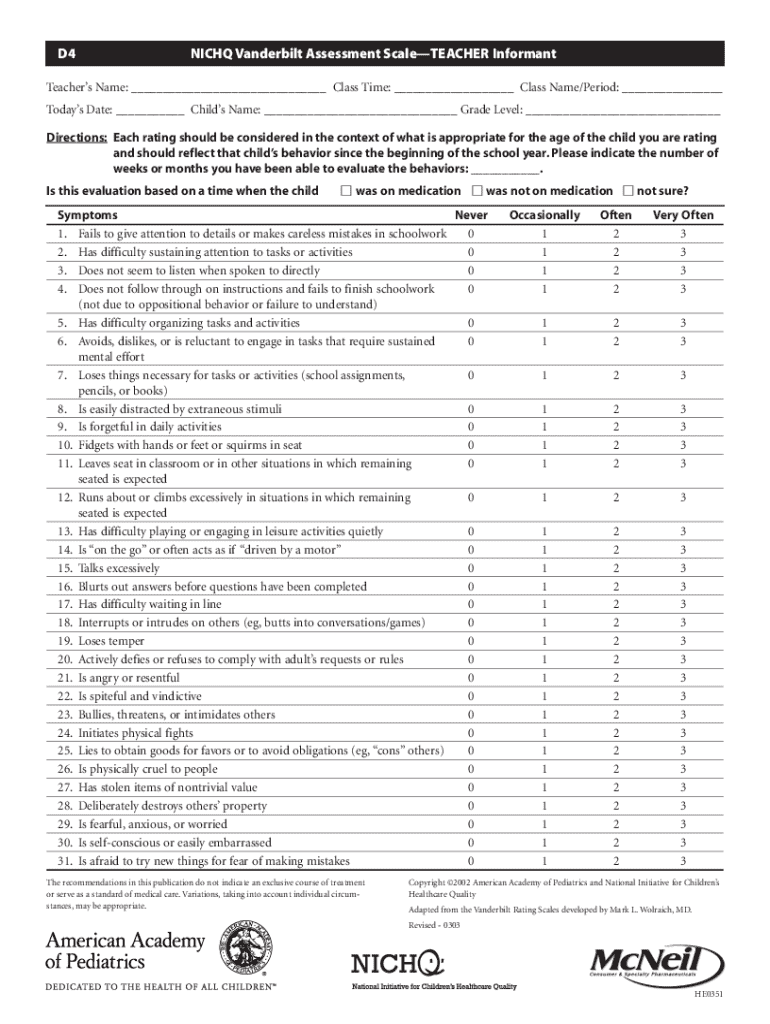
If you need the link, the primary download is hosted at vanderbiltheadstart.org under the Assessment Tools section, and the NIH maintains an archived copy at nichq.org. Both are free. The official Vanderbilt University Psychiatry department also publishes updated instruction sheets periodically, so check for those if your district requires current documentation. The form is widely adopted because it works well for its intended purpose: quick, DSM-aligned screening. It is not comprehensive. It is not diagnostic. It is not a substitute for a full psychoeducational evaluation. When used correctly, with proper context and follow-up, it catches kids who need help earlier than they would otherwise be identified. When used carelessly, it generates referrals that collapse under scrutiny and wastes everyone's time. The difference is in how carefully you fill it out and what you do with the results.