How Nicotine Patch Placement Actually Works
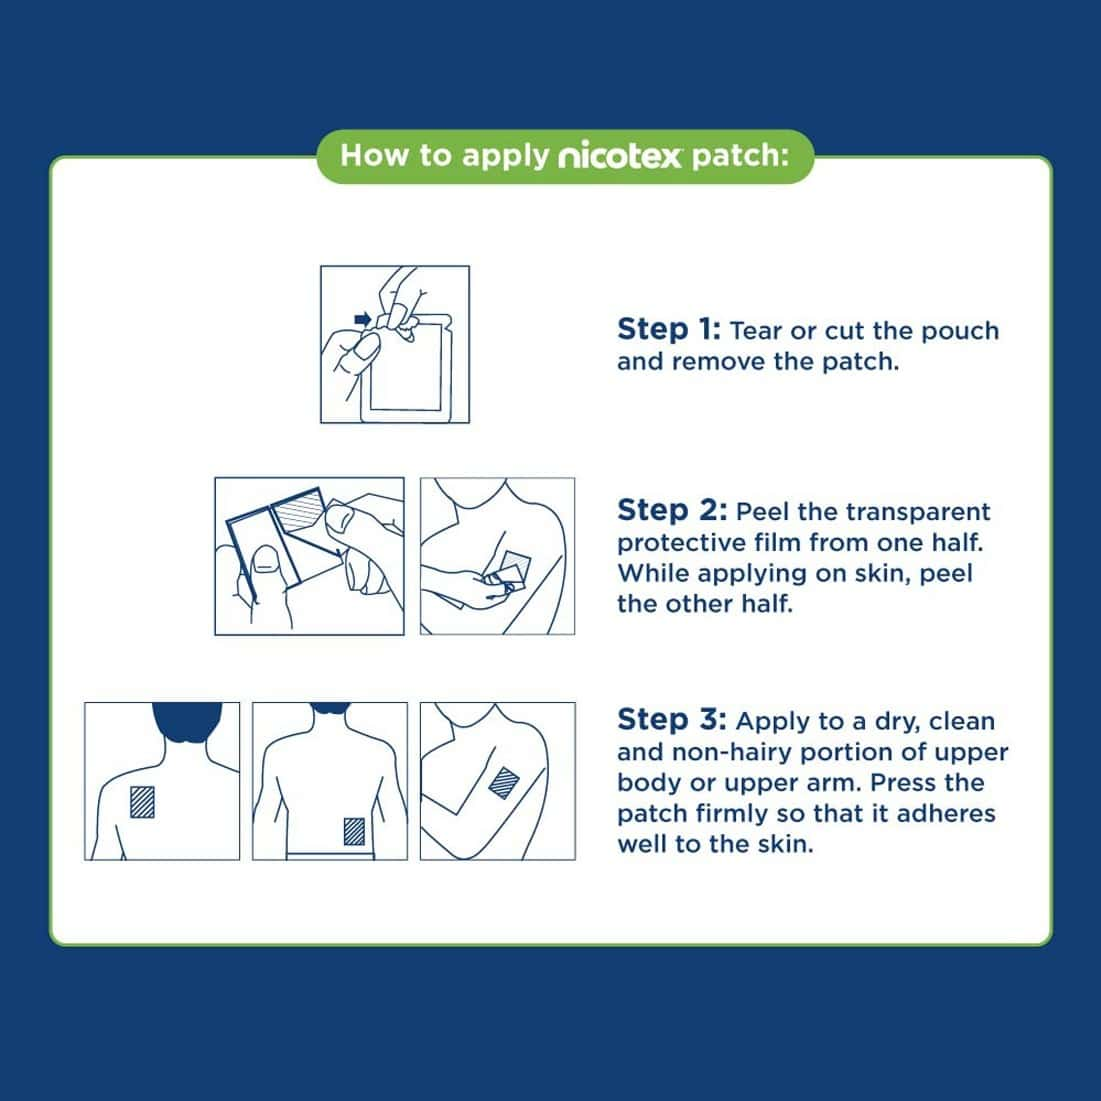
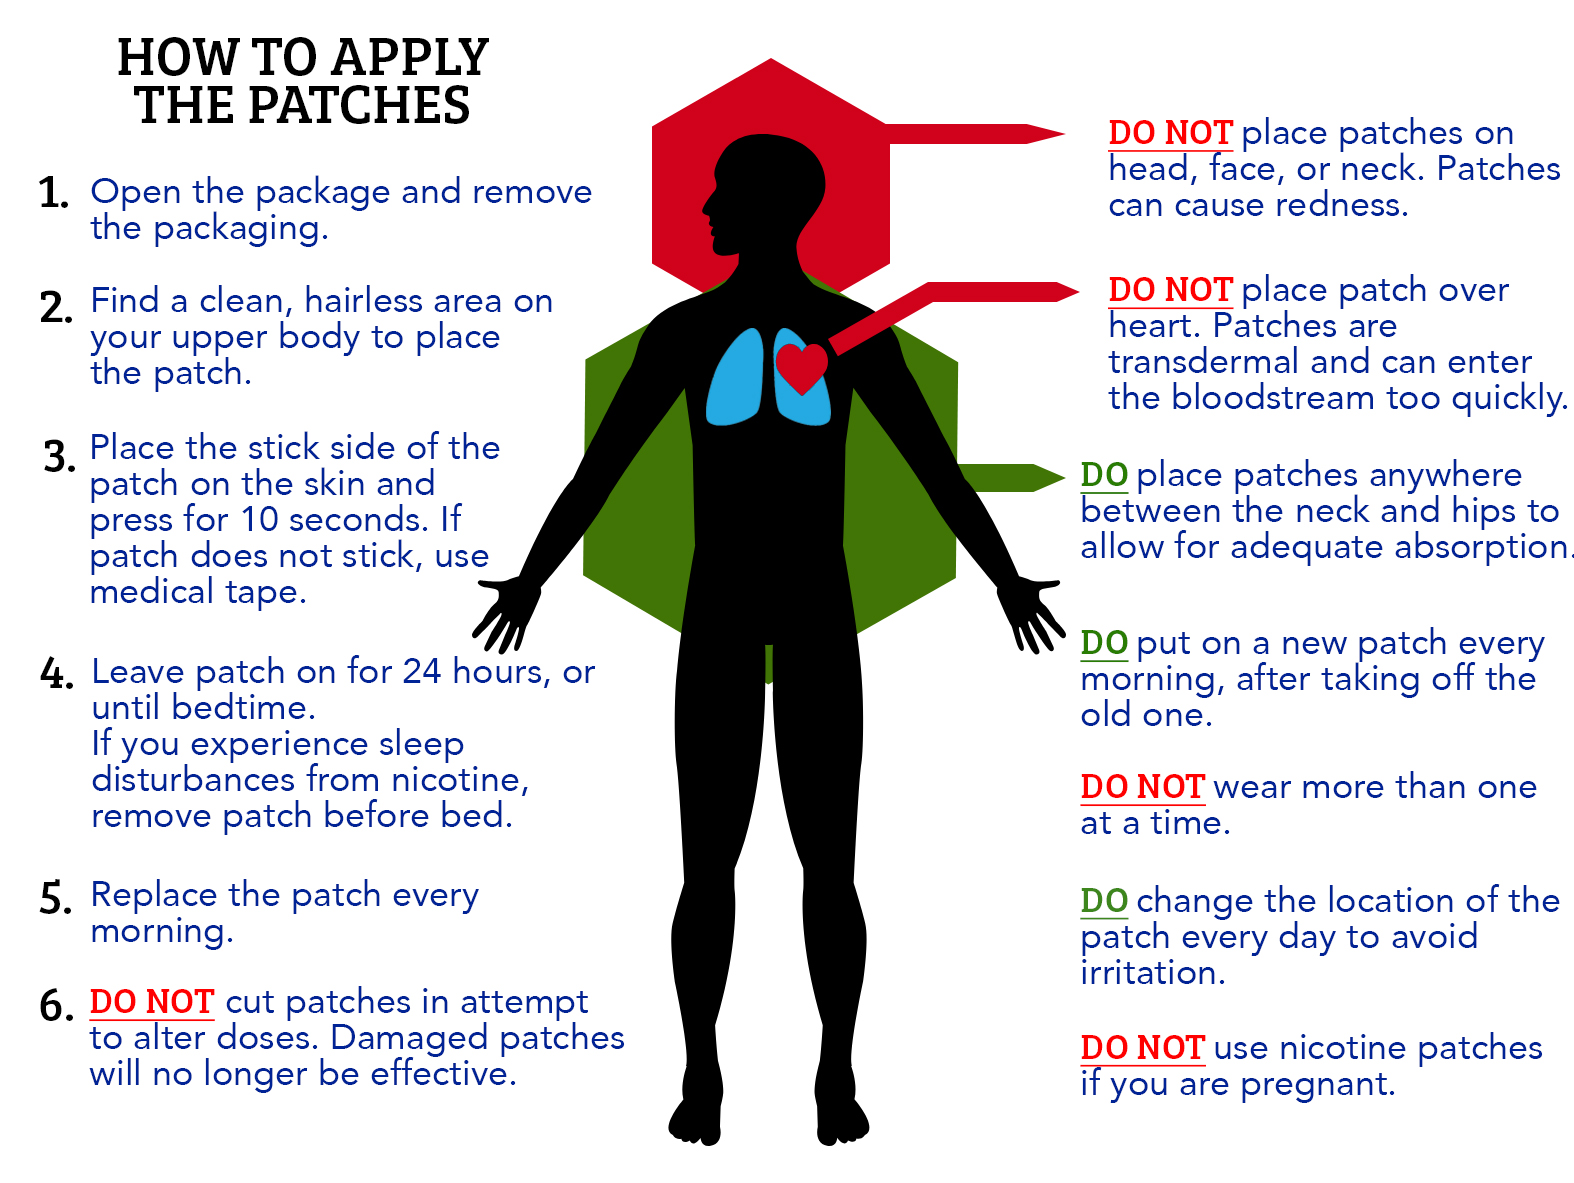
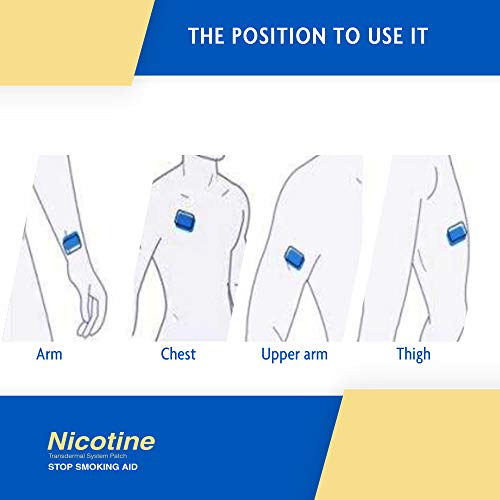
Most people slap a patch wherever their arm happens to be clean and hope for the best. That approach works sometimes. It also causes half the complaints I see in clinics. The placement matters more than the dosage number printed on the box. A Nicotine Patch Placement Diagram maps out the approved application zones and shows where you should rotate sites between applications. The diagram exists because nicotine transdermal delivery is affected by skin thickness, blood flow, and local irritation. Put the patch in the same spot day after day and absorption becomes inconsistent. Skin reaction builds up. You either get too much nicotine from irritated skin or too little from calloused tissue.The standard approved sites are the upper arm, shoulder, chest, and lower back. Some diagrams also include the hip area. These are regions with relatively consistent subcutaneous fat and steady dermal blood flow. The inner forearm and areas near joints are excluded because movement and skin thickness variation disrupt the adhesive seal and alter release rates unpredictably.
Reading a Nicotine Patch Placement Diagram Correctly
A typical diagram shows a human outline with shaded zones marked for application. Rotation is the key concept. You apply the next patch to a different zone than the previous one. If today's patch is on the left upper arm, tomorrow goes on the right shoulder or the lower back. The diagram usually includes a rotation schedule or at minimum a note about site rotation. The patches themselves come in fixed dose tiers. Common ones are 7mg, 14mg, and 21mg for the higher strength brands. Dosing is typically stepped down over 6 to 8 weeks. Week one gets the highest dose. Week three drops to medium. Week five drops to low. Some patients stay on the lowest dose for another two weeks before stopping completely. Others taper faster. The diagram doesn't tell you about dosing schedules. It only tells you where the patch goes.I've seen people confuse patch placement with timing instructions. They look at the diagram and think it covers duration, dosing, and application simultaneously. It doesn't. Application site is the only variable the diagram addresses. Everything else comes from the prescribing information or your clinician's guidance. Mixing those up leads to early removal, skipped days, or applying two patches to compensate for perceived weak effect. That last one is dangerous and more common than you'd expect.
Why Rotation Prevents Contact Dermatitis
Adhesive contact dermatitis from nicotine patches is one of the most frequent side effects. It shows up as redness, itching, and sometimes blistering at the application site. The reaction is to the adhesive matrix and occasionally to the nicotine itself. Either way, reapplying to the same skin area compounds the inflammation. Inflamed skin has altered permeability. Nicotine absorption spikes unpredictably. You might feel dizzy or nauseated from a localized dose surge while the rest of your body is still adjusting. Rotating sites gives each area at least 48 to 72 hours of recovery between applications. Most diagrams recommend a minimum interval of one full day between applications on the same general region. That means if you used the left upper arm on Monday, don't use that same arm again until Wednesday at the earliest. Move to the right shoulder or lower back in the meantime.The rotation pattern isn't arbitrary. Upper arm to opposite upper arm to lower back to chest creates roughly equidistant application points. This minimizes the chance of overlapping irritation zones. I once had a patient who applied patches to the same spot every day for two weeks because she couldn't reach the other side comfortably. She developed a second-degree contact dermatitis with weeping and crusting. She stopped the patch entirely and went cold turkey instead of rotating sites. Both outcomes were avoidable with basic rotation.
Get the Full Details

What the Diagram Doesn't Show You
A placement diagram will not tell you about skin preparation. Clean, dry, hair-free skin is required for proper adhesion. Lotions, oils, and sweat prevent the adhesive from bonding. Hair on the application site reduces contact surface area and can cause premature peeling. Shaving the area before application is fine, but don't apply the patch to freshly shaved skin. Micro-cuts and irritation from shaving compromise the seal and increase local absorption sharply. Diagram clarity is another issue. Some manufacturers produce diagrams that are too small or use vague shading. Others omit the rotation sequence entirely. If your patch packaging doesn't include a clear diagram, you can find replacement guides from major manufacturers online. The instructions are essentially identical across brands because the approved sites are standardized. What varies is the adhesive composition and the nicotine release profile, which affects how long the patch stays adhered and how strongly it irritates sensitive skin.I ran into a specific problem last year with a patient using a generic brand whose diagram printed misaligned. The shaded zone for the upper arm was shifted inward toward the armpit area. Someone applying by that diagram would place the patch too close to the axillary region, where skin folds and movement degrade adhesion within hours. The workaround was straightforward: ignore the misprinted diagram and use the brand's text instructions instead, which listed the correct landmarks. I also had him use a medical-grade skin barrier wipe before application and an adhesive overlay strip to keep the edges sealed. That combination held the patch in place for the full 16 to 24 hours regardless of the diagram quality.
Common Mistakes That Undermine the Whole System
Applying two patches at once to boost effect is the most serious error. A dual-patch scenario can deliver 42mg of nicotine in a single session, which pushes blood nicotine levels into toxic range. Symptoms include severe nausea, vomiting, tachycardia, hypertension, and in extreme cases seizures. This is not theoretical. Emergency departments see these cases regularly during peak quit-attempt periods in January. Removing the patch early because of local irritation is another frequent mistake. People think taking it off for a few hours will let the skin heal. It does not. It fragments the dosing schedule and triggers withdrawal symptoms that make quitting harder. The correct approach is to rotate to a new site and treat the irritation with topical hydrocortisone 1% cream applied after patch removal. Oral antihistamines help with itching. If the reaction is severe with blistering, discontinue the patch and switch to a non-transdermal nicotine replacement form like gum or lozenges.Some patients apply the patch to the abdomen or waistline because they think it's a neutral area. The diagram explicitly excludes the torso below the chest. Abdominal skin has higher variability in thickness and blood flow, and the area is subject to compression from clothing and belts. Compression increases local temperature and alters nicotine diffusion. You get uneven delivery and a higher risk of the patch sliding off entirely.
When Placement Strategy Fails Completely
No diagram or rotation schedule solves every problem. Some patients have allergic reactions to the adhesive regardless of where they place the patch. Others have skin conditions like psoriasis or eczema that make any transdermal application risky. Patients with significant peripheral vascular disease may have reduced dermal blood flow in the recommended sites, which slows nicotine absorption below therapeutic levels. In those cases, the patch simply doesn't work well enough, and a different delivery method is necessary. I've also seen patients with very high body fat percentages experience inconsistent absorption from upper arm application. The subcutaneous layer can be so thick that the dermal capillary network doesn't pick up nicotine efficiently. These patients often report feeling no effect from the standard dose. Switching to a chest or shoulder site sometimes helps because those areas have denser vascularization relative to subcutaneous depth. If that doesn't resolve it, transdermal delivery is the wrong route entirely.The limitation here is real. Transdermal patches have a fixed absorption ceiling and a fixed onset time of roughly one to two hours. If your withdrawal symptoms peak quickly and intensely, the patch's slow drip won't catch up. Combining a patch with a fast-acting NRT like gum or a lozenge for breakthrough cravings is the standard workaround. The diagram still applies to the patch placement. The fast-acting component operates independently.
Practical Steps for Daily Use
Pick your application site based on the diagram's approved zones. Clean the area with water and let it dry completely. Do not use alcohol wipes routinely. They dry the skin and can cause stinging, which some people mistake for a nicotine reaction. Press the patch firmly with the palm of your hand for ten to fifteen seconds. Make sure the edges are fully adhered. Showering, swimming, and light exercise do not dislodge a properly applied patch. Heavy friction from tight clothing or backpack straps can. Remove the old patch before applying the new one at a different site. Fold the old patch in half with the sticky sides together and dispose of it safely. Used patches still contain significant nicotine residue. Keeping them accessible around children or pets is a genuine hazard. The CDC estimates that thousands of pediatric exposure cases involve used nicotine patches annually.The entire process from removal to new application takes about three minutes. The diagram guidance reduces decision fatigue because you already know the approved zones and the rotation pattern. What it doesn't reduce is the need to monitor for irritation, inconsistent effect, or adhesive failure. Those require judgment, not a diagram. If you're applying correctly and still struggling with placement issues, the problem is likely with the product formulation, not the site selection. Switching brands or switching to a different NRT format is the practical next step.