NIH Stroke Scale Cheat Sheet
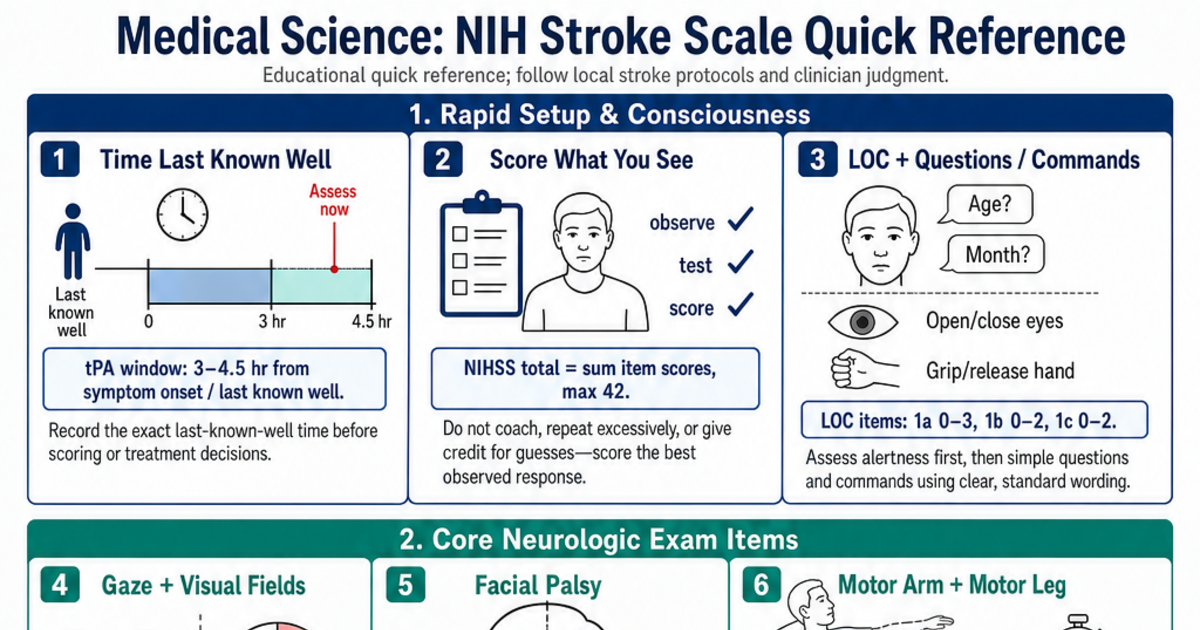
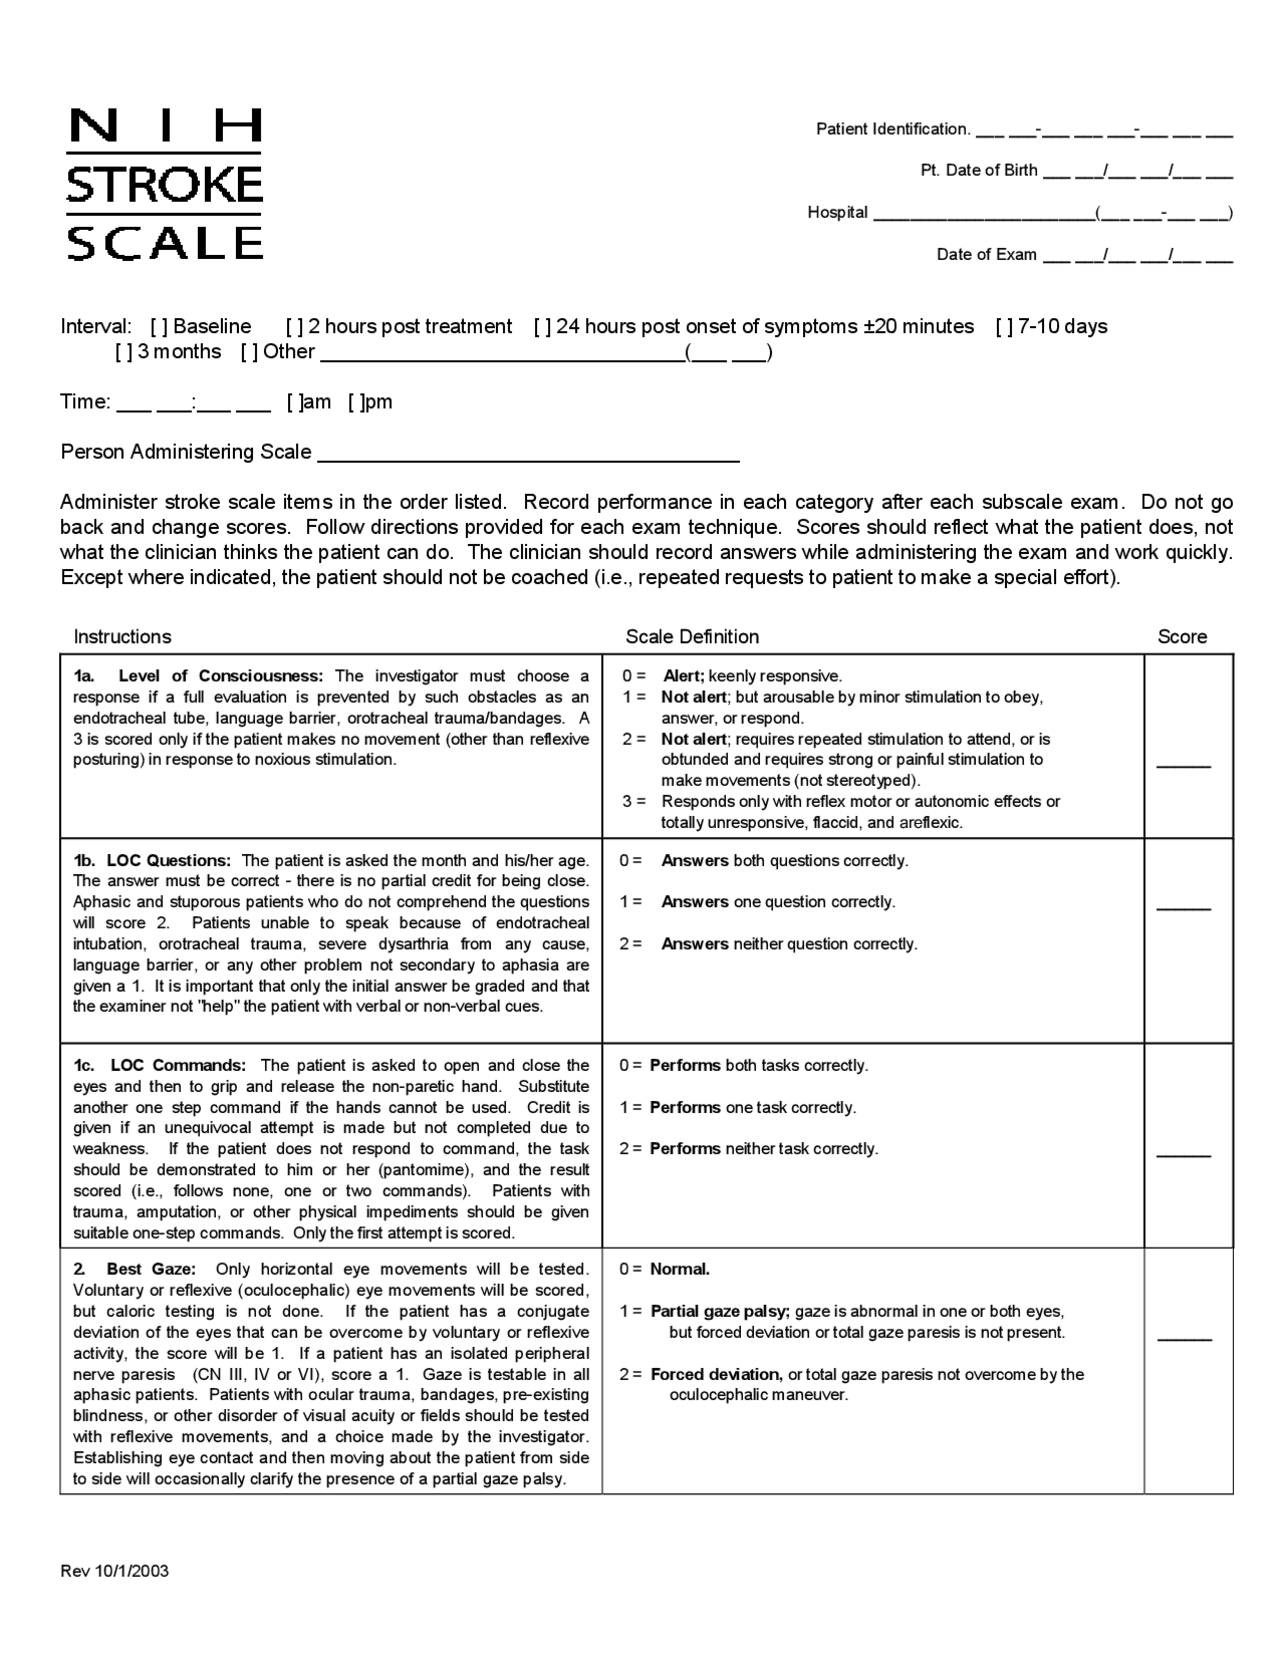
The NIH Stroke Scale is an 11-item assessment tool used in acute stroke evaluation. It scores neurological deficit from 0 to 42, with higher numbers indicating more severe impairment. Most people encounter it in emergency departments, stroke units, or during paramedic transport. If you are a clinician, you will use it regularly. If you are a student or trainee, you will be tested on it constantly. Here is the breakdown of each item and the scoring: 1a. Level of Consciousness (LOC) - Question: Asked two questions: What month is it? How old are you? Score 0 for correct answers, 1 for one wrong answer, 2 for both wrong. A coma or severe aphasia that prevents answering scores a 2.
1b. Level of Consciousness (LOC) - Commands: Asked to open/close eyes and grip/release a non-paretic hand. Score 0 for both correct, 1 for one correct, 2 for neither. Patients who are intubated, paralyzed by neuromuscular blockade, or have severe facial trauma should be noted but still scored on eye-opening if possible. 1c. Level of Consciousness (Locomotor): This has been removed in the 2018 revision. Do not score this if you are using an older version by accident. Mixing versions mid-assessment is a common error that throws off your total score. 2. Best Gaze: Horizontal eye movements. Score 0 for normal, 1 for partial gaze palsy, 2 for complete gaze palsy. With a unilateral cerebral lesion, eyes typically deviate toward the side of the lesion and away from the hemiparetic side. Brainstem strokes cause the opposite pattern. If you miss this, you might mislocalize the lesion entirely.
3. Fields (Visual): Confrontation visual field testing. Score 0 for no deficits, 1 for partial hemianopia, 2 for complete hemianopia, 3 for bilateral blindness. Patients who are confused or uncooperative may fail this for non-neurological reasons. I once had a patient who appeared blind on confrontation testing but was actually just refusing to look because of severe anxiety and agitation from a hypoglycemic episode. Correct glucose and retest. 4. Facial Palsy: Ask the patient to show teeth and raise eyebrows. Score 0 for symmetric, 1 for minor/flattened nasolabial fold, 2 for partial lower facial paralysis, 3 for complete paralysis of upper and lower face. Bell's palsy involves the entire half of the face including the forehead. A middle cerebral artery stroke typically spares the upper face because of bilateral cortical innervation to the frontalis muscle. This distinction matters for localization. 5. Motor Arm (Left and Right): Hold arms extended at 90 degrees (sitting) or 45 degrees (supine) for 10 seconds. Score 0 for no drift, 1 for drift but not hitting surface, 2 for hitting surface before 10 seconds, 3 for no effort against gravity, 4 for no movement at all. Documentation must specify the angle and duration. I have seen nurses and residents count to five instead of ten, which artificially inflates the score.
Get the Full Details

6. Motor Leg (Left and Right): Same scoring as the arm but legs are held at 30 degrees for 5 seconds. Again, timing errors here are common. Using a watch with a second hand or your phone timer removes that variable. 7. Limb Ataxia: Finger-nose-finger and heel-shin tests. Score 0 for absent, 1 for present in one limb, 2 for present in two or more limbs. This is assessed only if weakness is not severe enough to prevent movement. Ataxia from cerebellar stroke is different from ataxia from proprioceptive loss. The former is cerebellar; the latter is sensory ataxia and scores differently. 8. Sensory: Pinprick testing of the face, arm, and leg. Score 0 for normal, 1 for mild/moderate reduction, 2 for severe/complete loss. Stuporous or comatose patients who cannot cooperate should be documented as unable to test rather than scored as normal. A score of 0 for lack of response is wrong.
9. Best Language (Aphasia): Naming items, reading sentences, and describing a picture. Score 0 for no aphasia, 1 for mild/moderate aphasia, 2 for severe aphasia, 3 for mucous membrane or intubated/untestable. Severe aphasia from a large MCA stroke looks very different from mild aphasia. Don't underestimate the testing burden with a full sentence repetition task and picture description. If the patient is too agitated, note it and move on. 10. Dysarthria: Reading or repeating words. Score 0 for normal, 1 for mild/moderate dysarthria, 2 for severe or unintelligible. A patient who is aphasic may also have dysarthria. Test speech production when possible. Pure dysarthria without aphasia points toward brainstem or bilateral hemispheric involvement. Pure aphasia without dysarthria is usually a left hemisphere cortical stroke. 11. Extinction and Inattention (Neglect): Visual, tactile, auditory, or spatial inattention. Score 0 for none, 1 for abnormal, 2 for severe or complete. Neglect is often missed in right hemisphere strokes, especially when the patient is not blatantly ignoring one side. Sequential single-stimulus testing is more sensitive than simultaneous bilateral stimulation for detecting mild neglect. I learned this the hard way after scoring a patient as zero on neglect and later confirming a right MCA stroke with diffusion-weighted imaging that showed a significant parietal infarct.
The total possible score is 42. Any score above 4 generally indicates a stroke that could benefit from reperfusion therapy, though the exact threshold depends on the clinical scenario and treatment window. Scores of 0 to 4 suggest minor or no stroke symptoms. Scores above 20 indicate a large vessel occlusion until proven otherwise. The biggest practical problem with the NIH Stroke Scale is inter-rater variability. Two clinicians can assess the same patient and get different scores, particularly on the LOC questions, facial palsy, and language items. Standardized training and practice reduce this significantly. The American Heart Association and American Stroke Association offer free online NIHSS certification courses that are worth completing if your institution requires it. Another issue is timing. The scale should be administered at specific intervals - usually on presentation, at 24 hours, and at discharge or before transfer. Frequent re-assessment is necessary but also exhausting. I have seen nurses skip the 24-hour re-assessment because the patient was stable. A stable NIHSS does not mean a stable brain. Silent deterioration happens, especially with evolving infarcts and vasogenic edema.

If you want a quick reference document, the official NIHSS form and scoring sheet is available for free download from the National Institute of Neurological Disorders and Stroke (NINDS) website. Many hospital systems also print their own condensed pocket cards. Search for "NINDS NIH Stroke Scale official form" and you will find the PDF directly. Some stroke networks also provide laminated wall charts for rapid bedside reference. The scale has limitations that matter in practice. It was designed for hemisphere strokes, not brainstem strokes. Posterior circulation strokes tend to have lower NIHSS scores relative to the actual clinical severity, which can delay thrombectomy consideration. A patient with basilar artery occlusion might present with mostly ataxia and dysarthria and score in the teens while harboring a life-threatening lesion. The BANANA rule - Bilateral deficits, Ataxia, Nausea/vomiting, Neck pain, and Abnormal oculosensory - helps flag posterior circulation events that the NIHSS alone may underrepresent. Sedated, intubated, or encephalopathic patients are difficult to score accurately. Document the reason for incomplete assessment rather than guessing. The NIHSS does not account for eye opening in patients who are comatose from metabolic causes rather than structural ones. Distinguishing between these etiologies is not what the scale was built for.
For documentation purposes, record each item score individually, not just the total. A total of 6 could mean mild arm weakness on the right with no other findings, or it could mean complete hemiplegia on one side with moderate aphasia. The pattern matters more than the number when communicating with the stroke team or deciding on thrombolysis eligibility.