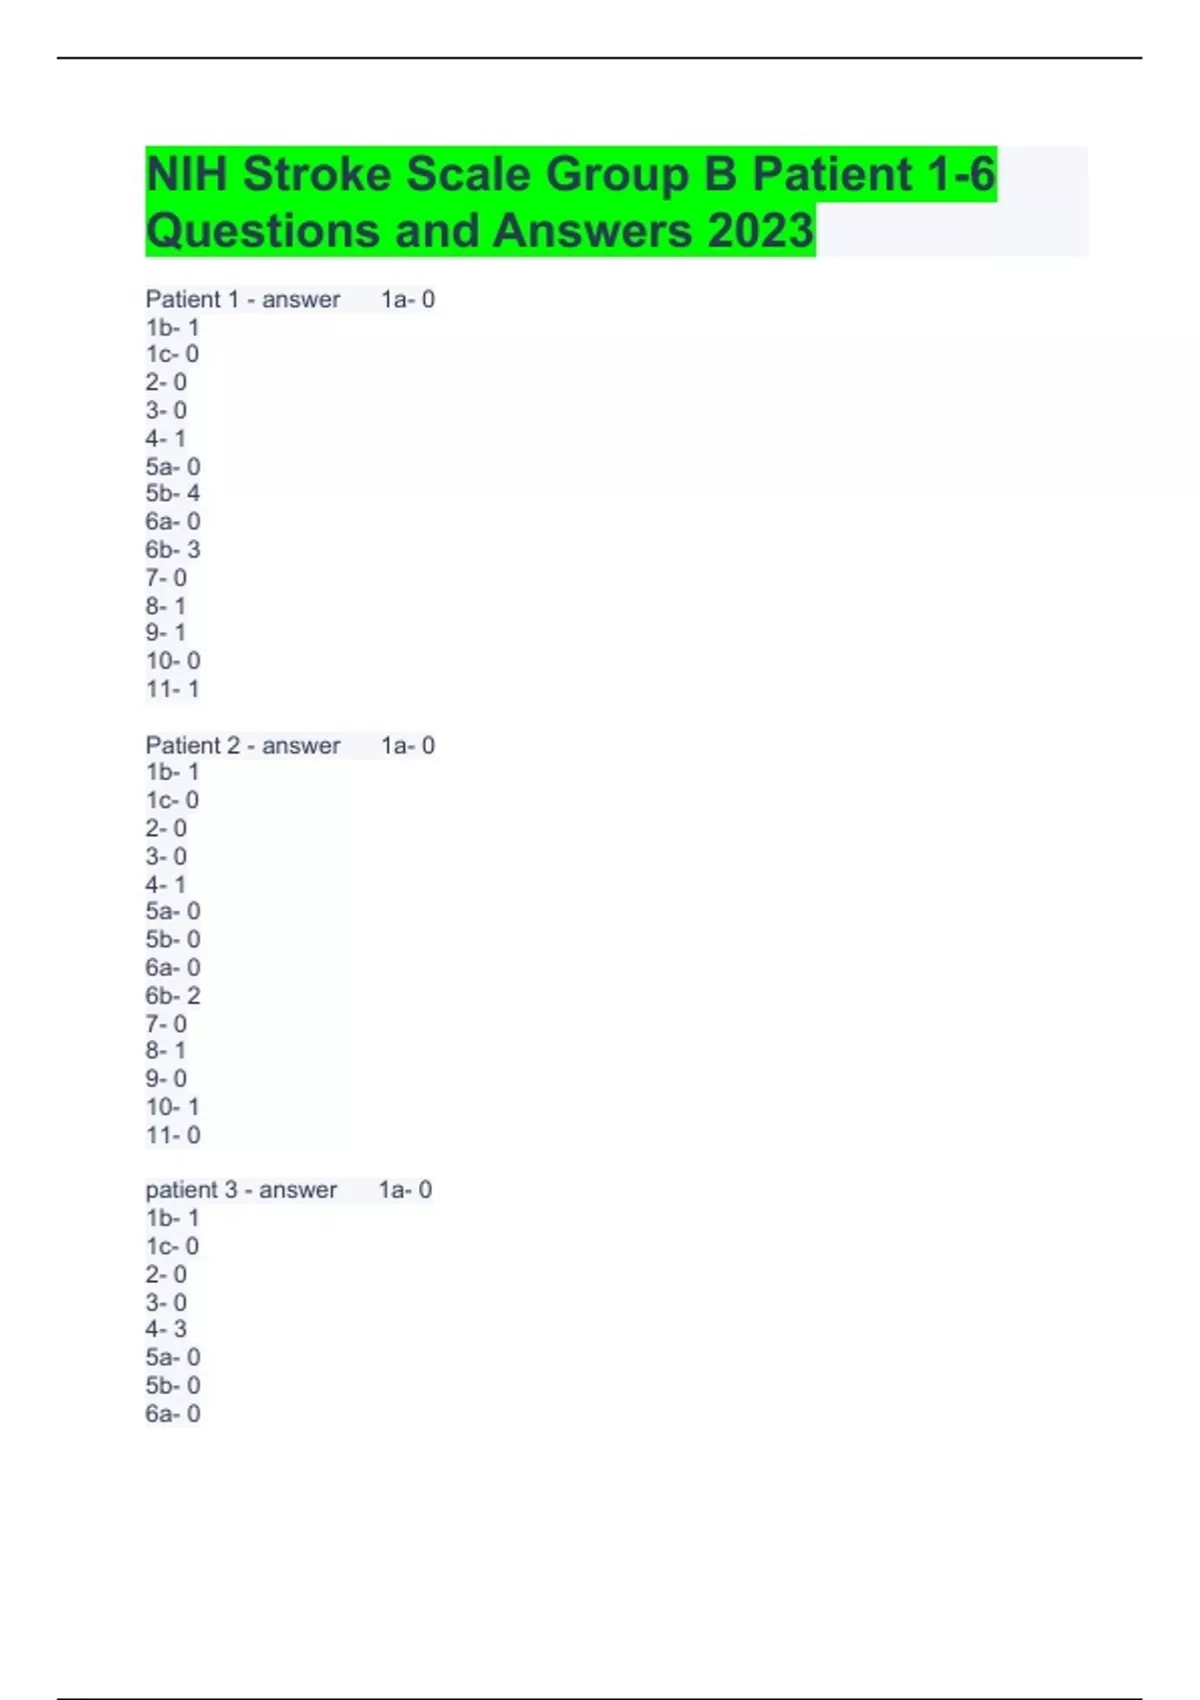
Understanding the NIHSS Group B Items
The NIHSS (National Institutes of Health Stroke Scale) is a 15-item scoring system used to assess stroke severity. It's broken into sections, and Group B generally covers items 6 through 11 — the motor, coordination, sensory, language, and cognitive domains. These are the items most people struggle with, both in testing and in scoring. Here's what falls under Group B and how to score each item correctly: Item 6 — Limb Ataxia: Tested via finger-to-nose and heel-to-shin. Score 0 if absent, 1 if present in one limb, 2 if present in two or more limbs. Note: ataxia must be out of proportion to sensory loss or weakness. I once saw a nurse score a patient as 2 on limb ataxia when the patient simply had poor proprioception from a diabetic neuropathy. The patient wasn't actually ataxic — just couldn't feel where their feet were. Worth rechecking before locking in a score.
Item 7 — Sensory: Tests response to pinprick. Score 0 for normal, 1 for reduced sensation (not absent), 2 for absent. The key distinction between 1 and 2 is whether the patient reports any sensation at all. Mild reduction gets a 1. Complete numbness gets a 2. A common mistake: patients who are slightly drowsy may not respond consistently, but that doesn't mean sensation is absent — try again with a clearer alert state if possible. Item 8 — Best Language: This is the aphasia battery — naming objects, reading, and answering questions. Score 0 = no aphasia, 1 = mild to moderate, 2 = severe aphasia, 3 = mucal or profound. If the patient is intubated, score this as 1 unless you can reasonably assess comprehension. Intubated patients often have expressive aphasia but can nod or blink to confirm comprehension, so don't automatically default to 3 without checking. Item 9 — Dysarthria: Assessed through clear speech production, usually by having the patient repeat phrases. Score 0 for normal, 1 for mild to moderate, 2 for severe or absent. This is frequently missed because raters conflate dysarthria with aphasia. They're different. A patient who can name objects and follow commands but slurs everything has isolated dysarthria — score the language item as 0 and the dysarthria as 1 or 2 depending on clarity. I've seen this scored wrong enough times that I now explicitly check comprehension before scoring language.
Item 10 — Extinction and Inattention (Neglect): This one is subjective and often under-tested. You're looking for hemineglect — does the patient ignore one side of space? Scored via bilateral stimulation tests. Score 0 for normal, 1 for mild to moderate neglect, 2 for severe. The trap here: many raters skip this entirely because it's quick and easy to miss, especially in awake, cooperative patients who compensate. A formal assessment includes visual field testing and sensory comparison on both sides simultaneously. I started doing a simple dual-tactile stimulation test — touching both arms at once — and caught neglect in three patients over six months who would have otherwise scored 0 here.
Get the Full Details

Scoring Nuances That Matter in Practice
Group B is where most scoring errors happen. Items 8 and 9 get conflated. Item 10 gets skipped. Item 6 and 7 get confused with weakness rather than ataxia or sensory loss. The scale assumes a trained rater, and honestly, most acute care settings don't have the time or staffing to guarantee proper calibration across every shift. One more thing nobody emphasizes enough: NIHSS scores change over time, and a patient who improves between assessments should be re-scored accurately, not defaulted to a prior number. I've seen charts where the score stayed at 12 across three assessments simply because the first rater never updated it after the second exam showed clear improvement. That's a documentation failure, not a clinical one, but it affects treatment decisions and outcomes tracking. If you're looking for an answer key or practice sheet for Group B, search for the official AHA/ASA NIHSS scoring chart. Many institutions use their own printable versions, but the source should always trace back to the original validated scale. Don't rely on secondary summaries — they sometimes mislabel the severity thresholds.




