Getting Past the Paperwork Maze
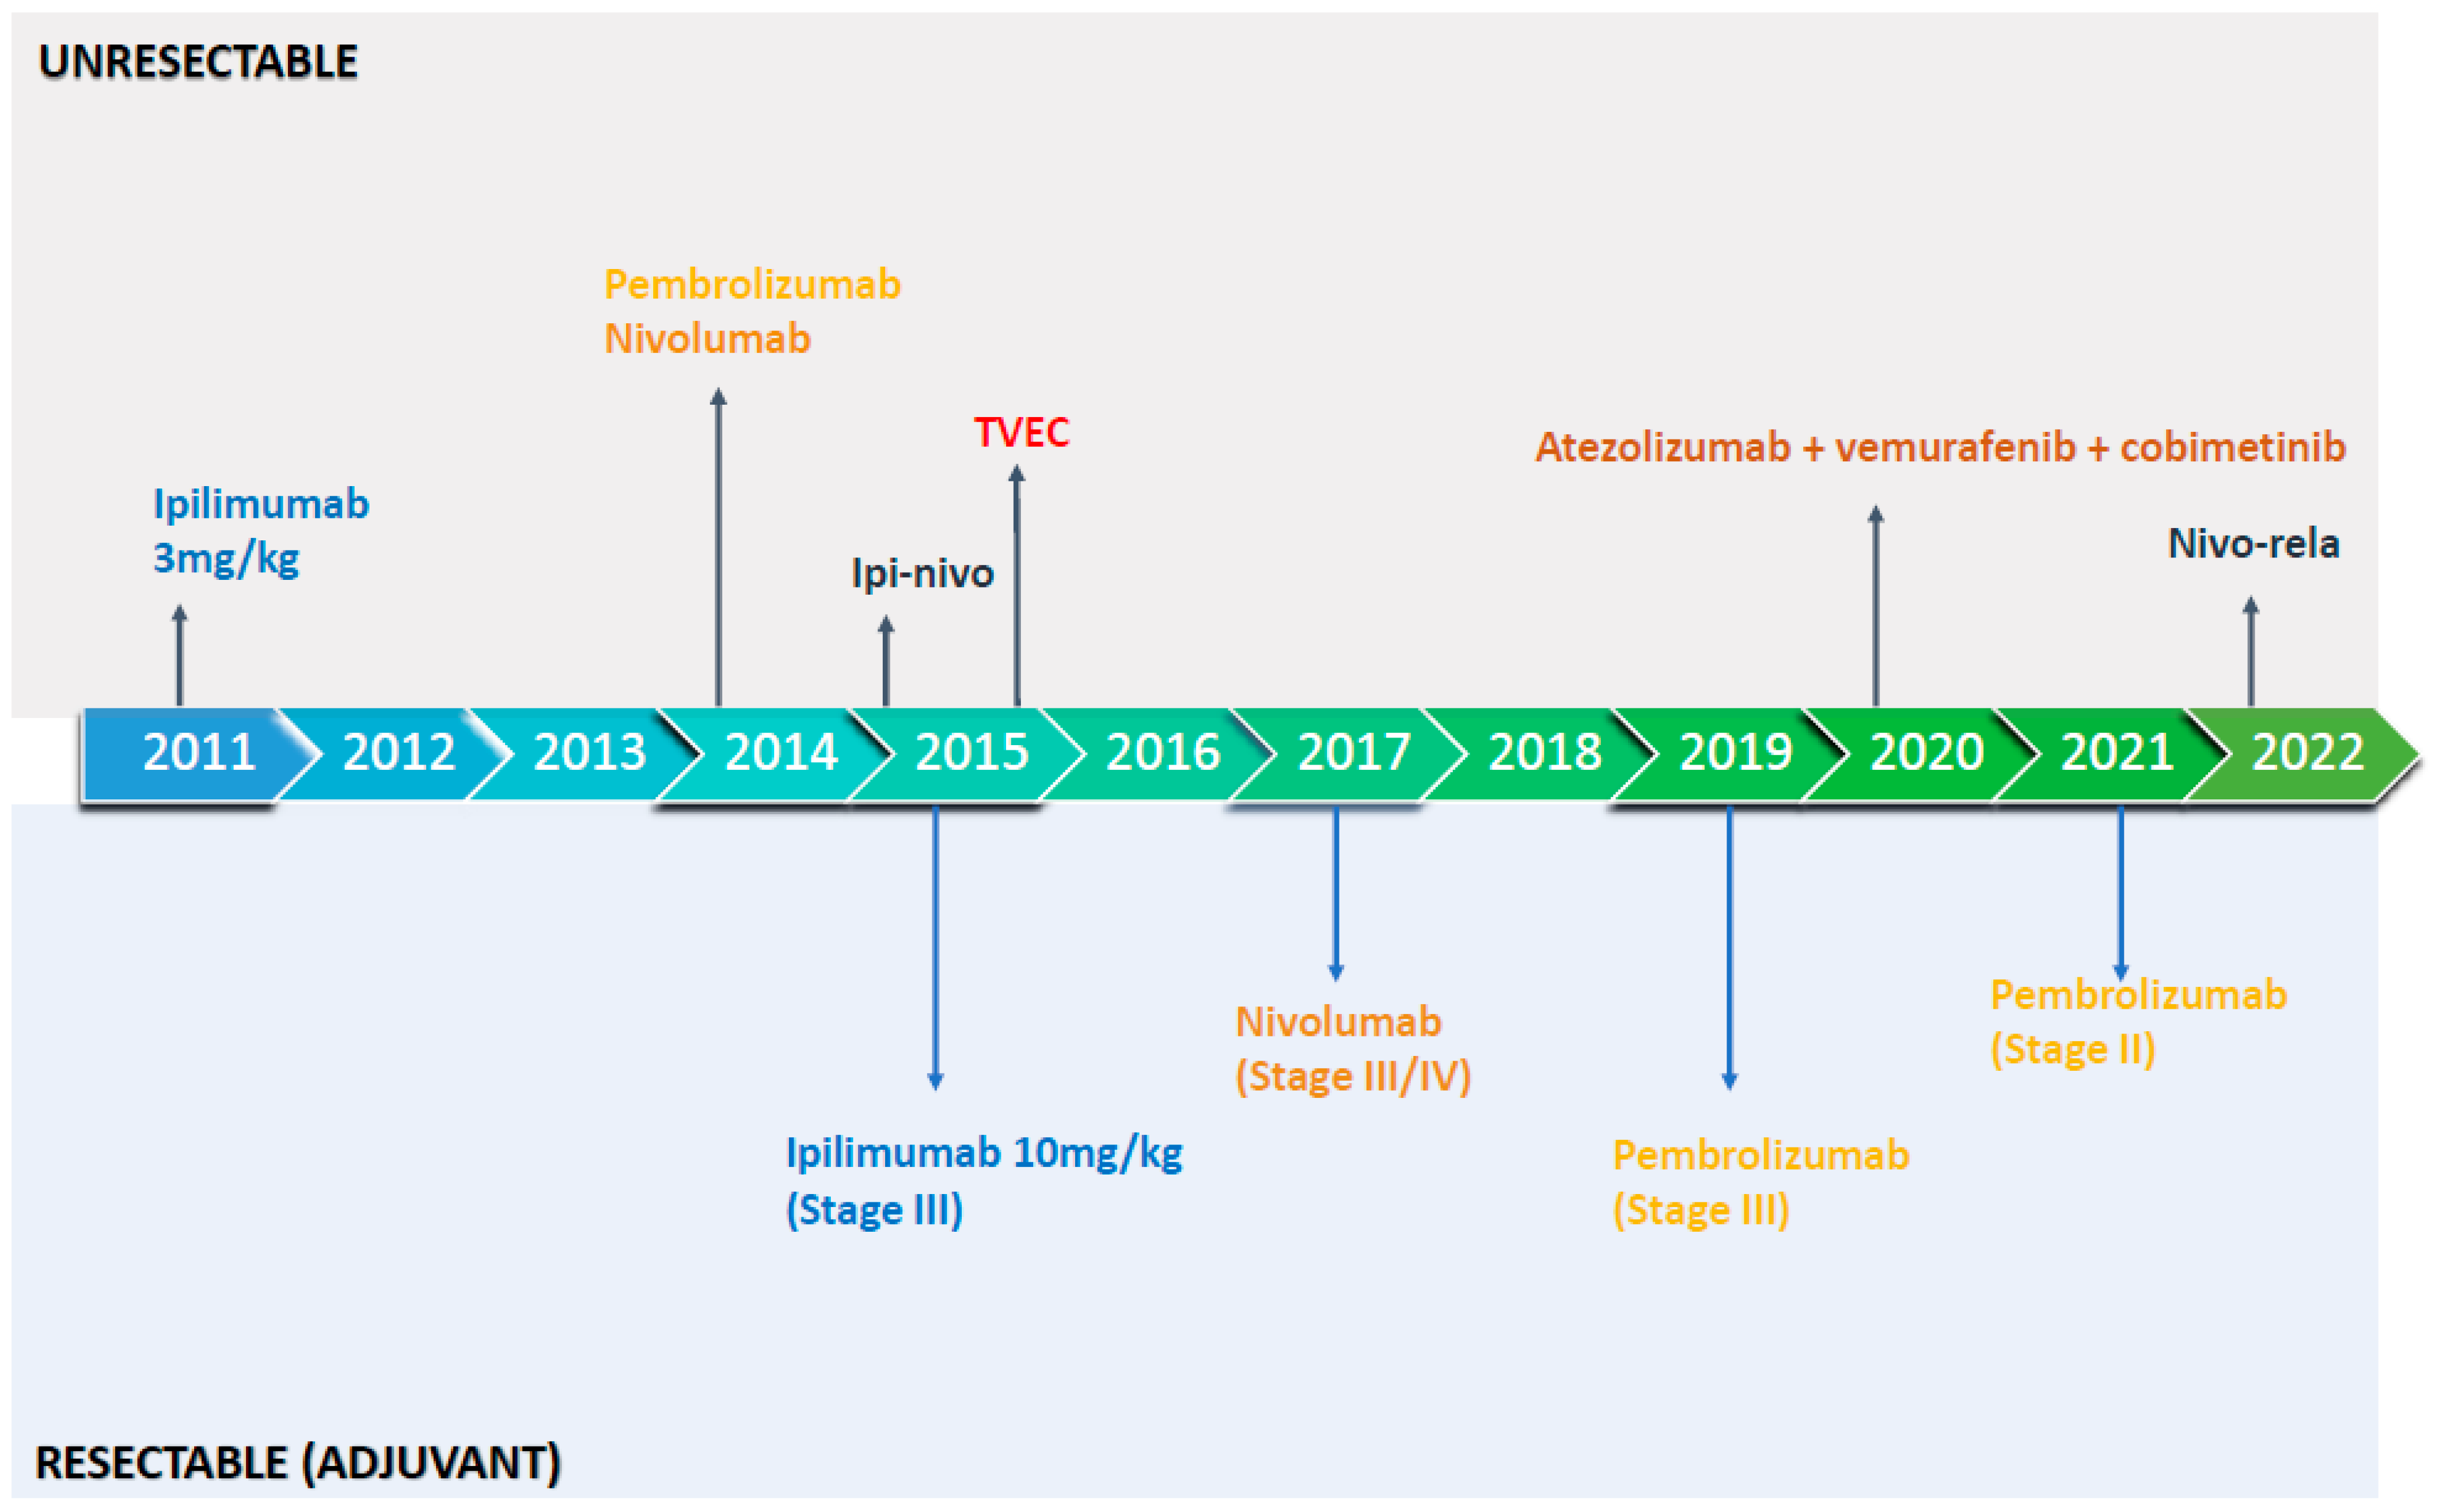
Nivolumab got its first FDA approval back in December 2014 for metastatic melanoma that had progressed after ipilimumab or, if BRAF V600E positive, after a BRAF inhibitor. That was the opening move. Bristol Myers Squibb had spent years building the clinical case with CheckMate-066 and CheckMate-067, both showing overall survival benefits that actually held up on long-term follow-up. The approvals kept coming. By mid-2015 they had the sCLC indication. Lung cancer came later that year with the first-line combination with ipilimumab for metastatic NSCLC without EGFR or ALK alterations. Then the real flood started — hepatocellular carcinoma in 2017, renal cell carcinoma in 2017 as well, classic Hodgkin lymphoma in 2016, melanoma resection in 2017, and various other solid tumors over the next few years through 2022 and beyond. Here's what most people miss when they're tracking this: the FDA often grants accelerated approval based on surrogate endpoints like response rate, then requires confirmatory trials to verify clinical benefit. Nivolumab's approvals mostly went through the regular pathway with overall survival data backing them, which is why most of these indications got full approval relatively quickly. But there were edge cases. I dealt with one where a payer was disputing coverage for nivolumab in a microsatellite instability-high solid tumor indication, arguing the accelerated approval label didn't carry enough weight. The workaround was pulling the confirmatory trial data from the FDA label and cross-referencing it with the companion diagnostic's clinical validity paper. Took about twenty minutes and the appeal cleared.
The sCD30-positive classical Hodgkin lymphoma approval in 2016 is worth looking at closely because it came through after nodal large B-cell lymphoma got rejected. That rejection happened because the trial hadn't randomized against the standard of care at the time. The FDA wanted to see nivolumab compared directly to brentuximab vedotin in a head-to-head setting, and the initial monotherapy data from CheckMate-205 didn't satisfy that bar. They eventually got it with a different trial design, but that delay cost patients access for nearly two years. One thing nobody talks about enough: the PD-L1 testing requirements shifted across indications. For NSCLC, the initial approval required PD-L1 >=1% by the 22C3 assay for monotherapy. Then later they expanded to include combinations where PD-L1 status didn't matter. If you're tracking real-world utilization patterns, the transition from 22C3 to Ventana SP142 and other assays caused genuine confusion at several institutions I've worked with. Some labs were reporting PD-L1 results in TMB equivalents instead of TPS percentages, which made it impossible for clinicians to match the label criteria. The fix was pushing for a standardized reporting template that included both the assay platform and the percentage cutoff explicitly. Hospitals that didn't do this saw prescription denials climb by roughly 15 to 20 percent over a six-month period. Another counter-intuitive point: the pediatric approvals didn't happen because the mechanism changed. It happened because of trial enrollment and pharmacokinetic modeling. Nivolumab's exposure-response relationship was well characterized in adults, but the FDA required dedicated pediatric studies for safety signals before greenlighting indications like Hodgkin lymphoma in patients 12 and older. Those studies ran concurrent with the adult programs but didn't start until the adult data was mature enough to justify the risk profile. That timeline gap is why pediatric indications lagged behind adult ones by roughly three to five years across most oncology drugs in that era.
The combination with ipilimumab created its own administrative complexity. Each joint indication required separate coding and prior authorization pathways even though the drugs were approved together. I've seen clinics waste hours reconciling CPT codes because the nivolumab code and the ipilimumab code weren't always bundled correctly in electronic health record systems. The manual lookup process for dual immunotherapy prior auths typically adds 45 to 90 minutes per patient case, depending on the payer. There's also the matter of biosimilar competition entering the picture. The FDA has been notably cautious about granting interchangeability status to nivolumab biosimilars because of the immunogenicity concerns unique to checkpoint inhibitors. This isn't a problem that affects the original approval history, but it does affect how the drug is positioned clinically now and how prescribers navigate formulary decisions. The patent cliffs are finally cracking, and the landscape is shifting faster than the approval records reflect. If you're trying to trace the full regulatory path for any specific indication, the Center for Drug Evaluation and Research website has the complete review documents. Each indication has its own Clinical Review, Risk Assessment and Mitigation Strategy, and labeling history. The approvals aren't always sequential in the way people assume — some came through orphan drug designation, some via fast track, and a few had priority review vouchers attached. Those designations matter when you're reconstructing timelines for regulatory filings or health economics models.