What actually goes wrong when homologous chromosomes refuse to separate
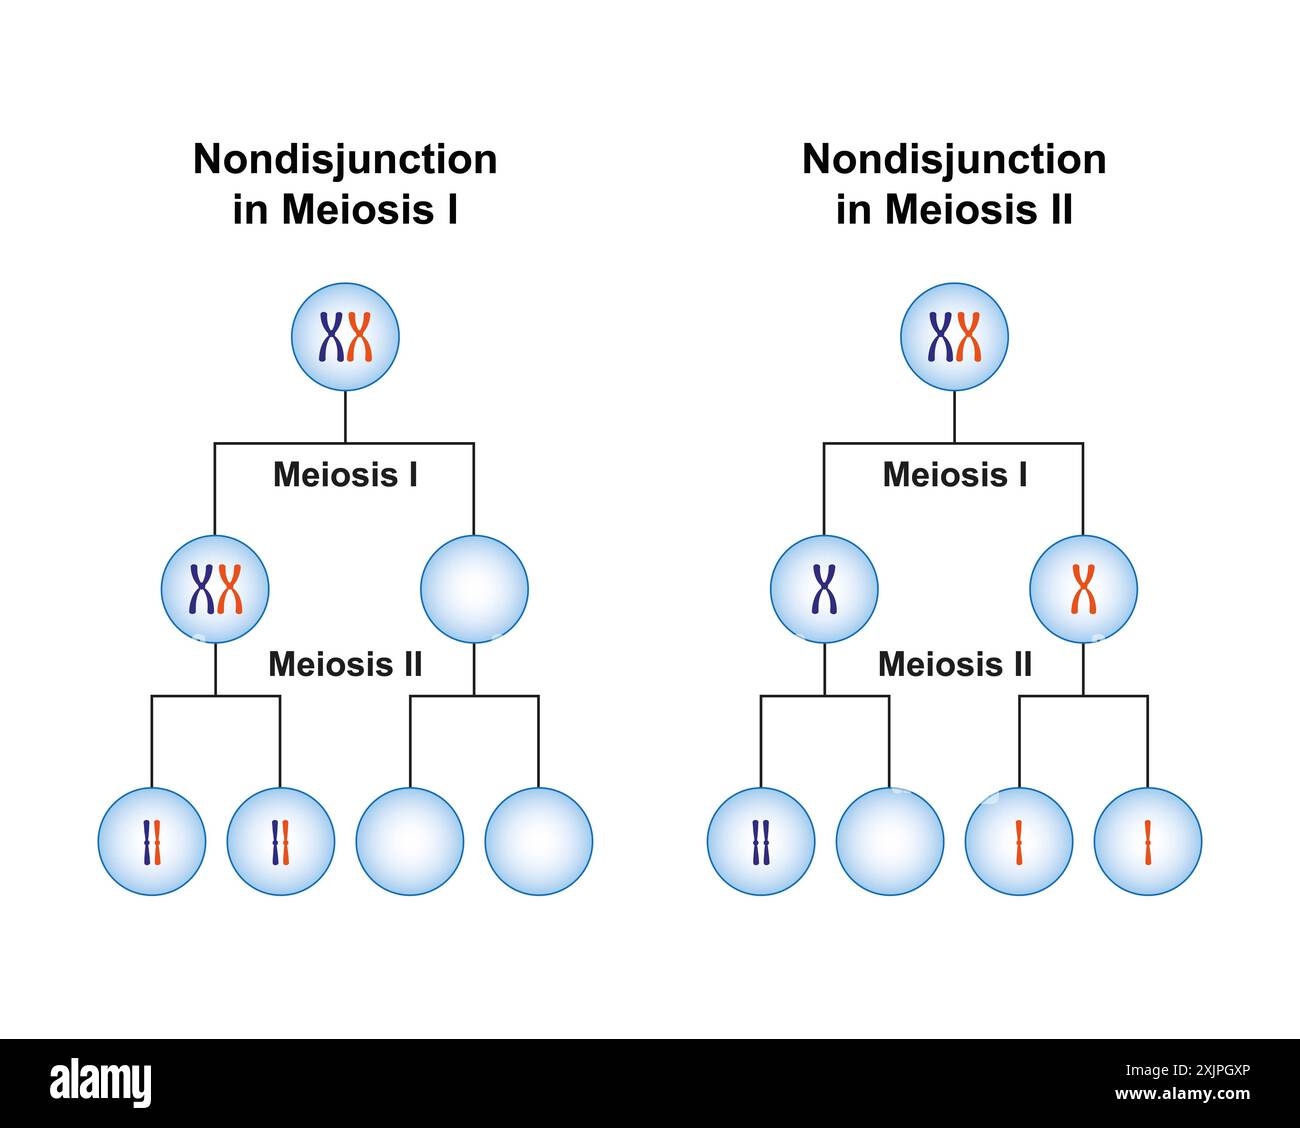
I spent three semesters watching undergrads struggle with the same diagram over and over. They could draw meiosis perfectly on paper but never understood what happens when the mechanics break down. The first thing you need to know is that non disjunction in meiosis 1 is fundamentally different from non disjunction in meiosis 2, and getting that distinction wrong will cost you points on any exam or clinical reasoning exercise. During normal meiosis 1, homologous chromosomes pair up during prophase 1, form chiasmata, and then segregate to opposite poles during anaphase 1. Non disjunction happens when those homologous pairs fail to separate. Instead of one cell getting both chromosomes of a pair and the other getting neither, you end up with two cells that have n+1 chromosomes and two cells that have n-1 chromosomes after the full meiotic process completes. That n+1 and n-1 distribution is the signature you look for. The key difference from meiosis 2 non disjunction matters a lot clinically. In meiosis 1 non disjunction, both daughter cells from the first division are already abnormal. In meiosis 2 non disjunction, you get two normal haploid cells and two abnormal ones. That distinction changes how you trace the origin of conditions like trisomy 21 back to either the maternal or paternal side using polymorphic markers.
I ran into this exact problem when a student brought me a pedigree analysis where the trisomy chromosome came from the father. She was convinced it had to be maternal because maternal non disjunction is far more common, especially with advanced maternal age. The data showed the extra chromosome 21 was paternal in origin. What happened was the father had a meiosis 1 non disjunction event for chromosome 21, producing a sperm with two copies of chromosome 21 instead of one. When that sperm fertilized a normal egg, the result was trisomy 21. The father had no known risk factors. This is the part that trips people up repeatedly. Paternal meiosis 1 errors are less common than maternal ones but they do occur and they follow the same mechanistic rules. The practical way to confirm which meiotic division went wrong is through linkage analysis using microsatellite markers or single nucleotide polymorphisms on the affected chromosome. You compare the child's genotype with both parents. If the child has three alleles at a locus where each parent should contribute only one, and two of those alleles come from the same parent, you can determine whether the error was in meiosis 1 or meiosis 2 by looking at whether the two inherited alleles from that parent are identical by descent or genetically distinct. In meiosis 1 non disjunction, the two alleles from the same parent will typically be different because recombination has occurred between them. In meiosis 2 non disjunction, the two alleles will often be identical because they are copies of the same recombinant chromosome. This linkage analysis approach takes about two to three weeks from sample collection to results in a standard clinical genetics lab. It's not something you can rush without compromising accuracy. The alternative approaches like quantitative PCR or FISH on stretched chromosomes are faster but they don't tell you which parental division failed with the same level of confidence.
The molecular mechanism behind the failure itself usually involves the cohesin complex. Cohesin holds sister chromatids together from S phase through to anaphase. During meiosis 1, cohesin along the chromosome arms needs to be cleaved so homologs can separate, but cohesin at the centromere must be protected. Shugoshin protein provides that protection. When Shugoshin function declines, particularly in older oocytes, the centromeric cohesin degrades prematurely and homologs can't maintain their bivalent structure properly. This is one of the primary reasons maternal non disjunction rates increase significantly after age 35. The literature around this is extensive but the practical takeaway is straightforward: oogonia are arrested in prophase 1 from fetal development until ovulation, and that arrest can last decades. Cohesin doesn't last that long without degradation. I've also seen cases where the spindle assembly checkpoint fails to catch the misaligned chromosomes. Normally the checkpoint halts anaphase onset if any chromosome isn't properly attached to spindle microtubules from both poles. When the checkpoint is compromised, cells proceed with unattached or incorrectly attached chromosomes and non disjunction follows. This checkpoint weakness appears to be more common in oocytes than in spermatocytes, which may explain part of the maternal bias in meiosis 1 errors. There's a misconception that all cases of trisomy result from meiosis 1 non disjunction. That's not true. Robertsonian translocations can cause trisomy without any non disjunction event at all. A parent who carries a balanced Robertsonian translocation between chromosomes 14 and 21 can produce gametes that, when combined with a normal gamete, yield a child with trisomy 21. The chromosome count in that case is 46 but one chromosome is a fused 14;21 Robertsonian chromosome and there are three copies of the long arm of chromosome 21. Distinguishing between true trisomy 21 from non disjunction and translocation Down syndrome matters because the recurrence risk is completely different. For true meiosis 1 non disjunction, the recurrence risk is about 1 percent above the maternal age-related baseline. For a Robertsonian translocation carrier parent, the risk can be as high as 10 to 15 percent depending on which parent is the carrier.
Get the Full Details
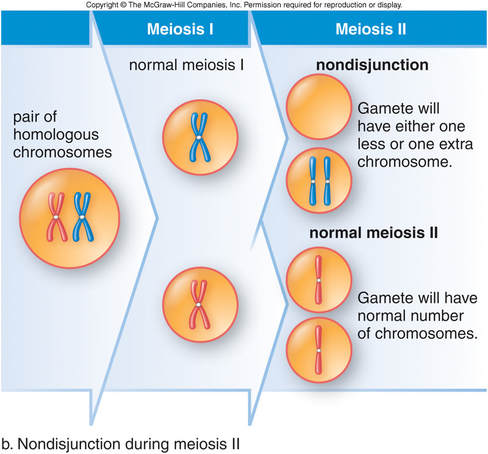
Mosaicism is another edge case that people regularly miss. If non disjunction occurs during a mitotic division in the early embryo rather than during meiosis, you get mosaic Down syndrome where some cells are trisomic and others are normal. The clinical presentation can be milder depending on the proportion and distribution of trisomic cells. Karyotyping from multiple tissue types like blood and buccal cells is necessary to detect mosaicism. A single blood sample might show only 5 percent trisomic cells and miss the diagnosis entirely if you're not looking carefully. When you're studying this for an exam, the most efficient approach is to draw out the chromosome configurations at each stage. Start with a diploid cell containing one pair of homologous chromosomes. Show the replication resulting in two sister chromatids per homolog. Show crossing over. Then draw the two possible outcomes: normal segregation where homologs go to opposite poles, and non disjunction where both homologs go to the same pole. Trace through meiosis 2 from each outcome. This visual method takes about five minutes and cements the concept better than any amount of rereading. The clinical applications extend beyond diagnosis. Prenatal screening programs use maternal serum markers like AFP, hCG, estriol, and inhibin A as part of the quad screen to estimate the risk of trisomy 21 and trisomy 18. These are screening tests not diagnostic tests. An abnormal result leads to offering either cell-free DNA testing or invasive diagnostic procedures like amniocentesis or CVS. Cell-free DNA testing detects fragments of placental DNA circulating in maternal blood and can identify trisomies with sensitivity above 99 percent for trisomy 21. It's a screening test that approaches diagnostic accuracy but still requires confirmation through amniocentesis or CVS before any irreversible decisions are made.
I remember working with a lab report where the nuchal translucency measurement was borderline elevated but the serum screen was low risk. The patient was anxious and wanted certainty. We recommended cell-free DNA testing which came back high risk for trisomy 21. Amniocentesis confirmed trisomy 21. This cascade of testing is standard but it's emotionally taxing for patients and each step adds time and cost. The whole pathway from initial screening to confirmed diagnosis typically spans three to six weeks depending on lab turnaround times and whether repeat procedures are needed. Another thing that comes up frequently is the difference between complete and partial monosomy. Non disjunction produces complete monosomy when an entire chromosome is missing from a gamete. Complete monosomy is generally not viable in humans except for monosomy X which causes Turner syndrome. Most autosomal monosomies result in spontaneous miscarriage very early in pregnancy, often before the woman knows she is pregnant. This is why viable live births with monosomy are so rare compared to trisomy. The body filters out the most severe chromosomal imbalances through pregnancy loss. Autopolyploidy and allopolyploidy are theoretical outcomes of complete non disjunction across all chromosome pairs but they are extraordinarily rare in humans. They do occur commonly in plants and can be exploited in agriculture. In humans, triploidy (69 chromosomes) usually results from dispermy where two sperm fertilize one egg or from a diploid gamete. Triploidy is lethal in most cases and results in miscarriage or stillbirth. Some liveborn infants with triploidy survive only hours to days. The mechanism here is different from single chromosome non disjunction but the principle of failed chromosome separation is the same.
If you're reviewing this material, focus on the segregation patterns and practice predicting the chromosomal content of each resulting gamete. Draw it out. Use colored pencils to track which chromosome came from which parent. This makes the pattern obvious within a few attempts. The underlying biology is complex but the arithmetic of chromosome counting is straightforward once you internalize what happens at each division. The broader implications involve genetic counseling, prenatal care, and understanding the biological constraints of human reproduction. Advanced maternal age is the single biggest known risk factor because of the cohesin degradation issue I mentioned. But paternal age also contributes at a lower level. Spermatogonial stem cells divide continuously throughout life and each division carries a small risk of segregation errors. The paternal contribution to non disjunction events is understudied but it exists and it matters for accurate risk assessment.