Understanding Non Keratinized Stratified Epithelium in Practice
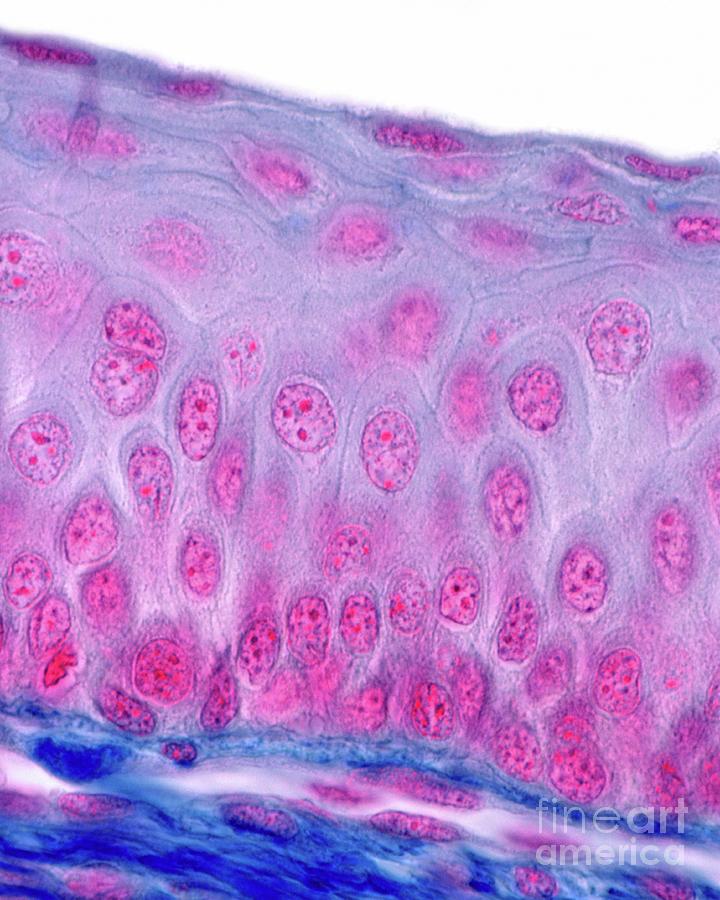
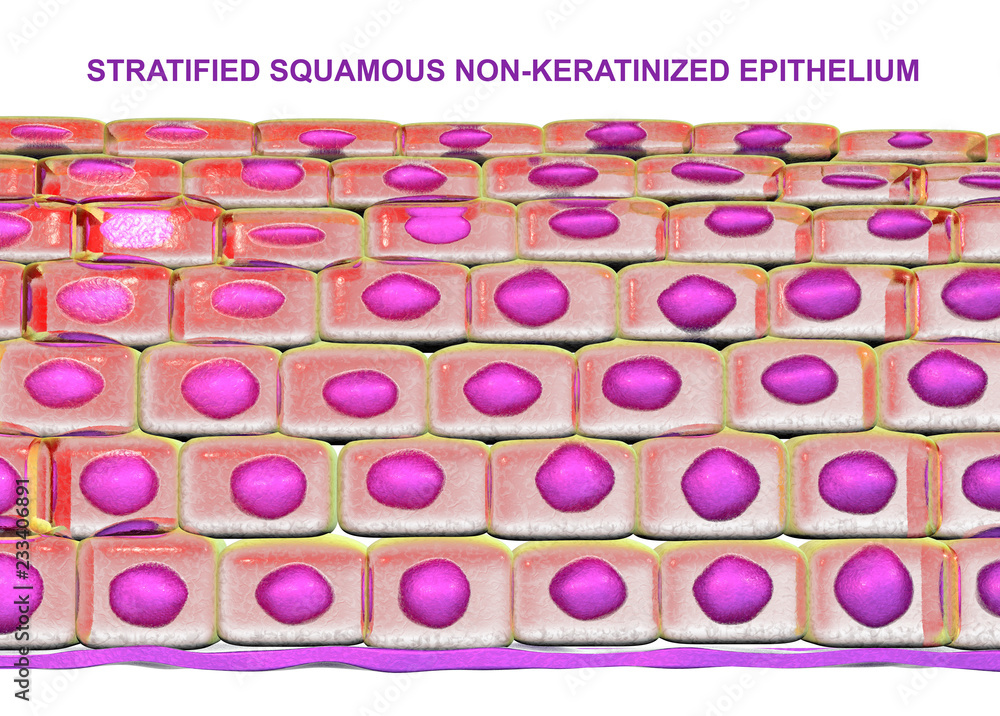
If you are studying histology or working in pathology, you will run into non keratinized stratified epithelium pretty quickly. It shows up in the mouth, esophagus, vagina, and cornea. The basic idea is simple enough, but there are details that matter once you actually look at a slide under the microscope or try to interpret biopsy results. The tissue consists of multiple layers of cells stacked on top of each other. The bottom layers contain cuboidal to columnar cells actively dividing. As they push upward, the cells flatten out into squamous shapes. Unlike the keratinized version found on your skin, these surface cells never fill with keratin protein and die off. They stay alive, just flat and dense-packed. That means the surface stays moist and flexible instead of turning into a dry, protective crust.
Non Keratinized Stratified Epithelium: What You Need to Know
When I was a grad student running through H&E stained sections, the first thing tripped me up was distinguishing non keratinized stratified squamous epithelium from other multi-layered tissues. A poorly cut section can make it look like something entirely different, especially if the plane of section is oblique rather than perpendicular to the basement membrane. I spent an entire afternoon convinced a esophageal biopsy was showing dysplasia until I realized the tangential cut was compressing the layers into an illusion. The workaround was straightforward: re-scan the slide at a different focus plane and look for the characteristic basal cell row anchored to the basement membrane. If you see a clear basal layer with uniform small dark nuclei transitioning upward into increasingly flattened cells, you are looking at the right tissue. No need to overthink it. One counter-intuitive point most textbooks gloss over is that the number of cell layers does not reliably indicate the degree of protection or function. Some descriptions imply that more layers equal tougher tissue, but that is not really accurate. The esophagus and the vagina both have non keratinized stratified epithelium, and yet their mechanical demands are quite different. What actually matters is the presence of intercellular bridges, the thickness of the cytoplasm in the intermediate layers, and whether glycogen accumulation is occurring, particularly in the vaginal epithelium where glycogen-rich superficial cells feed the lactobacilli flora. Beginners often miss the glycogen detail because PAS staining is not always performed on routine sections, leaving them confused about why some samples look paler than others. Another nuance worth noting is the behavior of this tissue under stress. Non keratinized stratified epithelium can undergo parakeratosis when irritated or inflamed, meaning the superficial cells retain their nuclei even as they begin to keratinize. This is common in the oral cavity, especially around sites of chronic friction or chemical irritation. If you see nuclei persisting in the topmost layers, do not automatically call it dysplasia. Check the clinical context first. I had a case where a patient's denture was causing chronic trauma, and the mucosa showed exactly this pattern. Removing the denture and waiting two weeks resolved the changes entirely. Calling it pre-malignant without that history would have been a serious error.
The basement membrane in this tissue type is also worth paying attention to. It is typically intact and well-defined, but in inflammatory conditions or early neoplastic processes, you can get disruption that is easy to miss at low magnification. Scanning at 10x gives you the lay of the land, but switching to 40x on the basal region will reveal irregularities that change the entire interpretation. I usually mark suspicious zones on the slide with a pencil before going to high power so I do not lose my place when switching objectives. There are also limitations to keep in mind. Non keratinized stratified epithelium is not suited for environments that demand waterproofing or significant abrasion resistance. The skin's keratinized variant exists for exactly that reason. If you encounter this tissue type in an unexpected location during a biopsy, the first question should be whether metaplasia has occurred. Chronic irritation can cause a shift from one epithelial type to another, and recognizing that shift is often more clinically useful than simply identifying the tissue itself. For practical study purposes, the best approach is to compare side by side. Put a section of oral mucosa next to a section of skin and a section of esophagus. Note the differences in surface appearance, nuclear retention, and overall thickness. The variations become obvious after you have seen maybe ten slides, but before that, everything blurs together. I found that drawing the layers from memory after each observation helped cement the distinctions faster than any amount of re-reading. It is a tedious method, but it works, and it takes less time than you might expect, probably twenty minutes per session for about a week of results that actually stick.
Get the Full Details