How to Get a Meaningful Blood Pressure Reading at Home
I spent years watching people panic over single high readings, then panic less when those numbers came back normal the next week. The problem isn't that blood pressure is complicated. It's that most people measure it wrong and then interpret a bad number as a medical emergency. Here is how to actually do it.Understanding a Normal Blood Pressure Reading
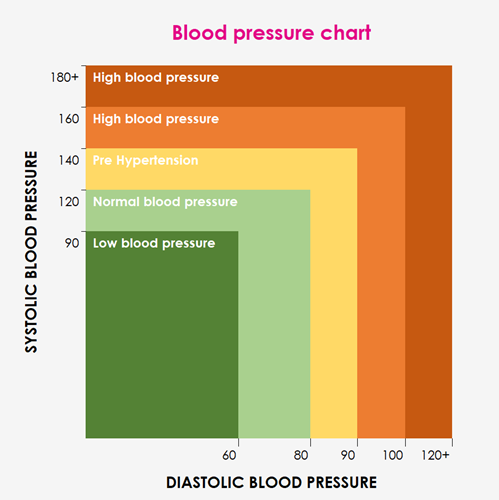
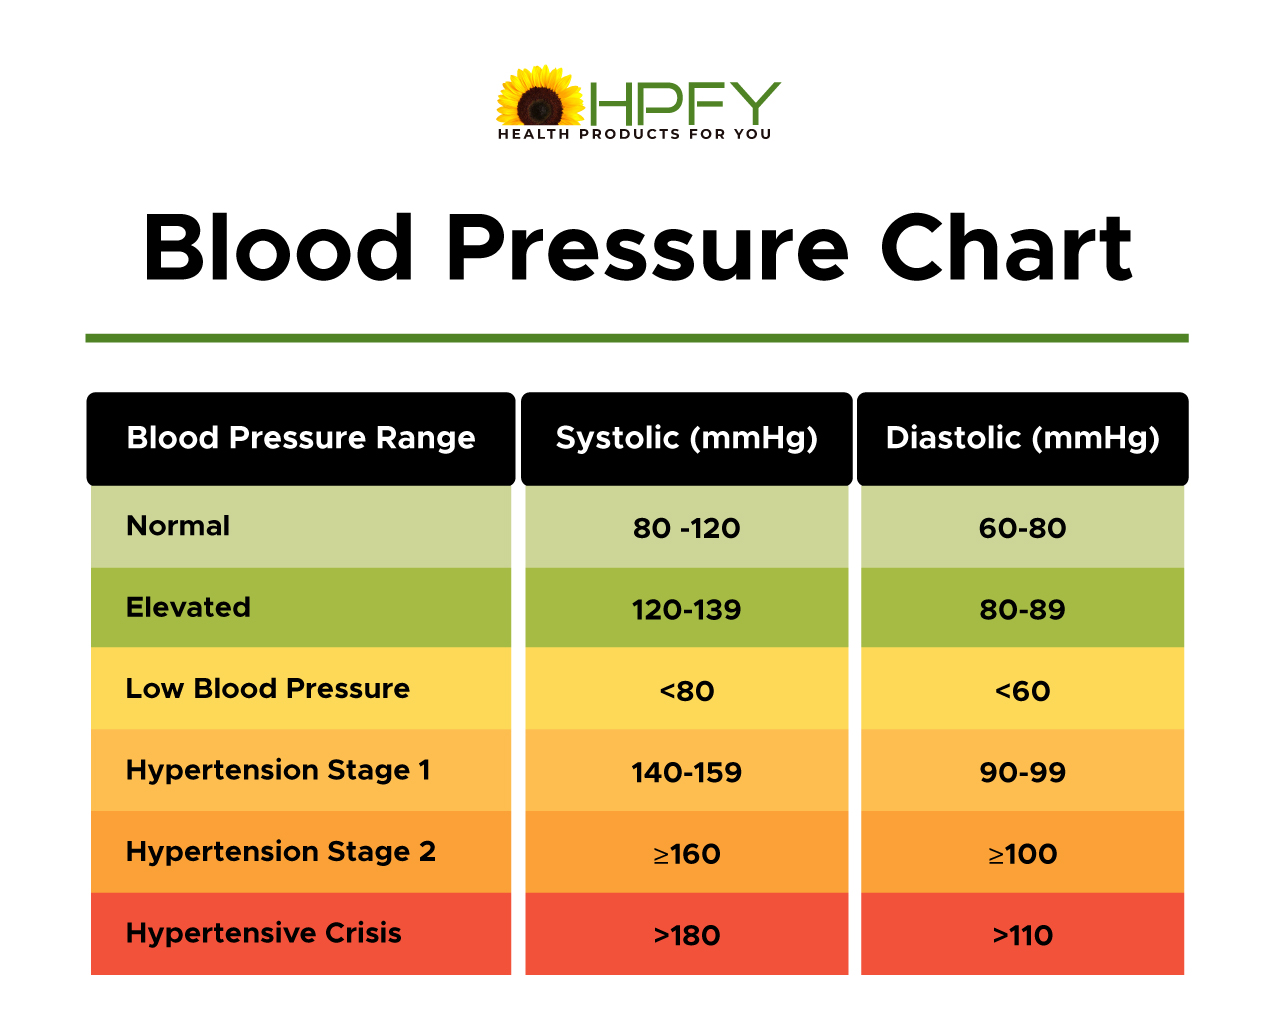
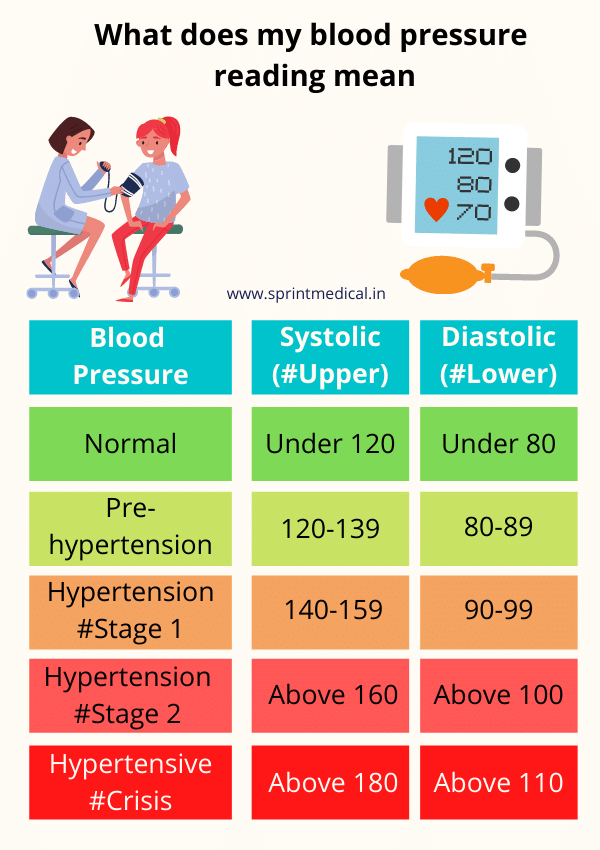
A normal blood pressure reading sits below 120 over 80 millimeters of mercury. That is the current guideline from the American Heart Association and the ACC. Before 2017 the threshold was 140/90, so if you are pulling older data from the internet you will see wildly different "normal" ranges. Don't. The 2017 shift caught a lot of people off guard. People who had been told their 135/85 was fine suddenly had stage one hypertension on paper. It was not a new disease emerging. It was a changed standard. The systolic number (the top one) measures the pressure in your arteries when your heart beats. The diastolic number (the bottom one) measures the pressure when your heart rests between beats. Both matter. Neither is more important in isolation. You will find doctors who fixate on systolic and dismiss everything else. That is a habit, not a science.I ran into a specific issue last year with a patient who consistently read 138/82 at the clinic but 118/76 at home. He was a large build guy, roughly 6'4" and 240 pounds. The cuff on the office machine was slightly too small for his arm, which inflated the reading by about eight to ten points on systolic. The fix was straightforward: use an upper-arm monitor with a large-cuff option at home and bring it to the next visit for side-by-side comparison. One reading does not define a diagnosis.
What You Actually Need to Measure Correctly
You need an upper-arm digital monitor. Wrist monitors and finger cuffs exist. They are unreliable unless you hold them at perfect heart level, which almost no one does consistently. A proper upper-arm device from Omron, Microlife, or Beurer runs about eighty to two hundred dollars and will serve you for years. Validate it against the British and European Society of Hypertension list if you want to be thorough, but honestly, just avoid the cheap-dollar units from gas stations and grocery stores. Here is the process I tell everyone to follow: Sit in a chair with your back supported. Do not cross your legs. Place both feet flat on the floor. Rest your arm on a table so the cuff is at heart level. Wait five minutes before you start. Do not talk during the measurement. Take two readings, one minute apart, and average them. If the two readings differ by more than ten millimeters of mercury systolic, take a third and use all three. That is it. Five minutes of nothing, two numbers, an average. The entire process should take about eight to ten minutes total.The pitfall most people hit is skipping the rest period. Your blood pressure fluctuates constantly. Walking to your car, climbing stairs, answering the door, having a brief conversation with your spouse — these all elevate your reading by five to fifteen points. I have seen people come in with 160/95 after mowing the lawn and get sent for workup. They sat quietly for five minutes and came back at 124/78. The delta was real. The initial number was noise.
Common Misunderstandings About Normal Ranges
"A normal" reading is not a single number. It is a range, and it shifts with age, activity, stress, and time of day. Your blood pressure is lowest during sleep and highest in the late afternoon. Taking a reading at 7 AM after waking and another at 7 PM after work will give you two different pictures of the same person. That is normal physiology, not equipment failure. Another thing people miss is that a single elevated reading does not mean hypertension. The diagnosis requires multiple elevated readings on separate occasions. One bad day at the pharmacy kiosk does not make you a hypertensive patient. Repeatedly high readings across a week or two do.Masked hypertension is the edge case I see most often and it is dangerous because it is invisible in clinical settings. This is when someone's blood pressure is normal at the doctor's office but elevated at home or at work. The opposite, white coat hypertension, is more well known. To catch masked hypertension you need home monitoring over several days, not a single visit. I had a patient in his forties whose office readings were always 118/76. His home averages over ten days sat at 142/88. We caught it early because he tracked it daily. Left alone, that would have gone untreated for years.
Get the Full Details
Normal Blood Pressure Reading: Tracking and When to Act
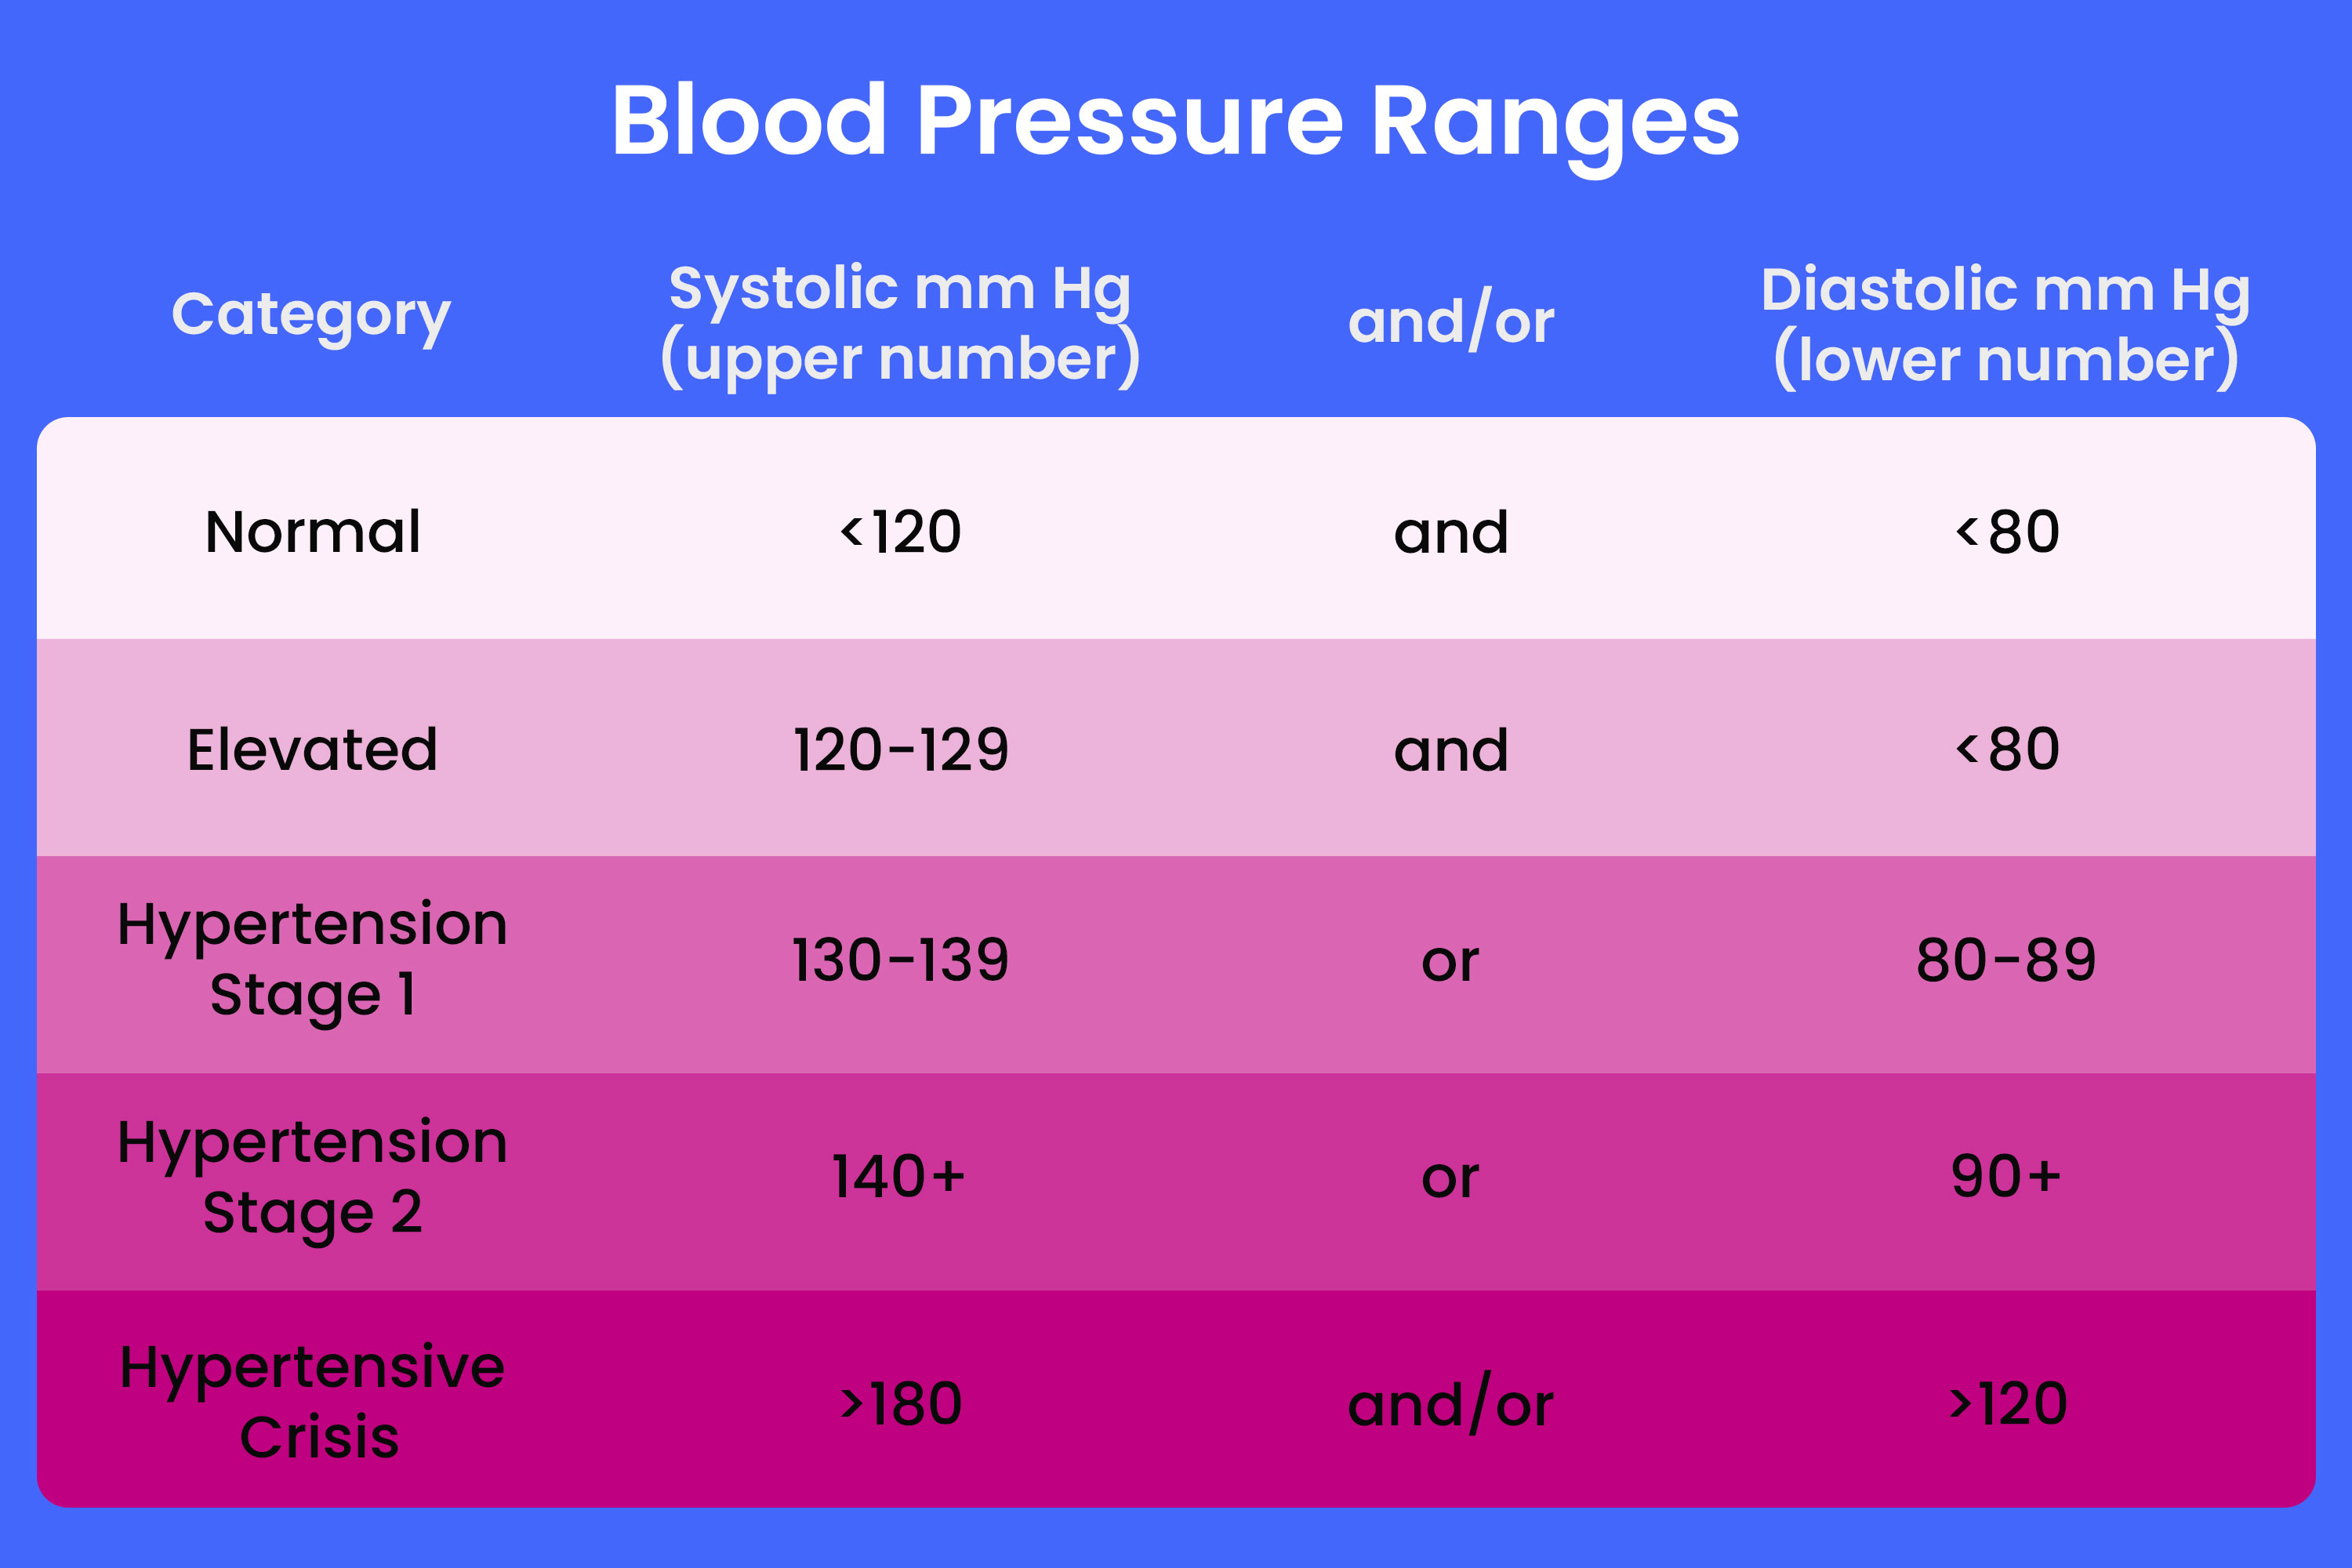
Keep a log. Write down the date, time, systolic, diastolic, and pulse for each reading. Do this for seven days. Discard day one if the numbers look wildly off — that first reading is often an outlier because you are not yet comfortable with the process. Average days two through seven. If your average systolic stays below 120 and diastolic stays below 80, you are in the normal range. If your average systolic is between 120 and 129 with diastolic below 80, that is elevated. Between 130 and 139 systolic or 80 to 89 diastolic is stage one hypertension. At 140 over 90 or above it is stage two. These thresholds are not arbitrary. They correlate with cardiovascular risk in large population studies.The limitation here is that home monitors have a margin of error of about five millimeters of mercury. That means a reading of 118 could genuinely be 113 or 123. The trend matters more than any individual number. A consistent average of 122/79 is in a different category than a single 139/89 spike. Track trends, not snapshots.
There is no free downloadable software for blood pressure tracking that I would recommend over a simple notebook or a basic phone app. Most of the specialized apps are either overbuilt or shut down within a year. A printed log sheet costs nothing and forces you to slow down and actually look at your numbers. If your home averages are consistently at or above 135/85, schedule a visit with your primary care provider. That threshold is slightly lower than the clinic diagnostic cutoff of 140/90 because home readings tend to run lower than office readings. Do not ignore sustained elevation. Do not panic over one off-day. Measure properly, track consistently, and let a professional help you interpret the pattern.