Reading a Cervical Spine Radiograph Like It Should Be Read
Most people learn the ABCs of cervical spine X-ray interpretation in a single lecture and then never revisit the actual anatomy until they are forced to. I have been doing this long enough that I can spot a normal study in about thirty seconds and still find something worth noting after that. The trick is not memorizing a checklist but building a real spatial map of the region in your head. A normal cervical spine X-ray is not one image but a set of projections, each answering a different question. The standard series includes the lateral, AP, and open-mouth odontoid views. You may also see oblique films if the referring clinician suspects nerve root impingement. Each projection has its own normal and its own failure modes, which means a result labeled "normal" only carries weight when all the relevant views are actually present and technically adequate.
What a Normal Cervical Spine X Ray Looks Like
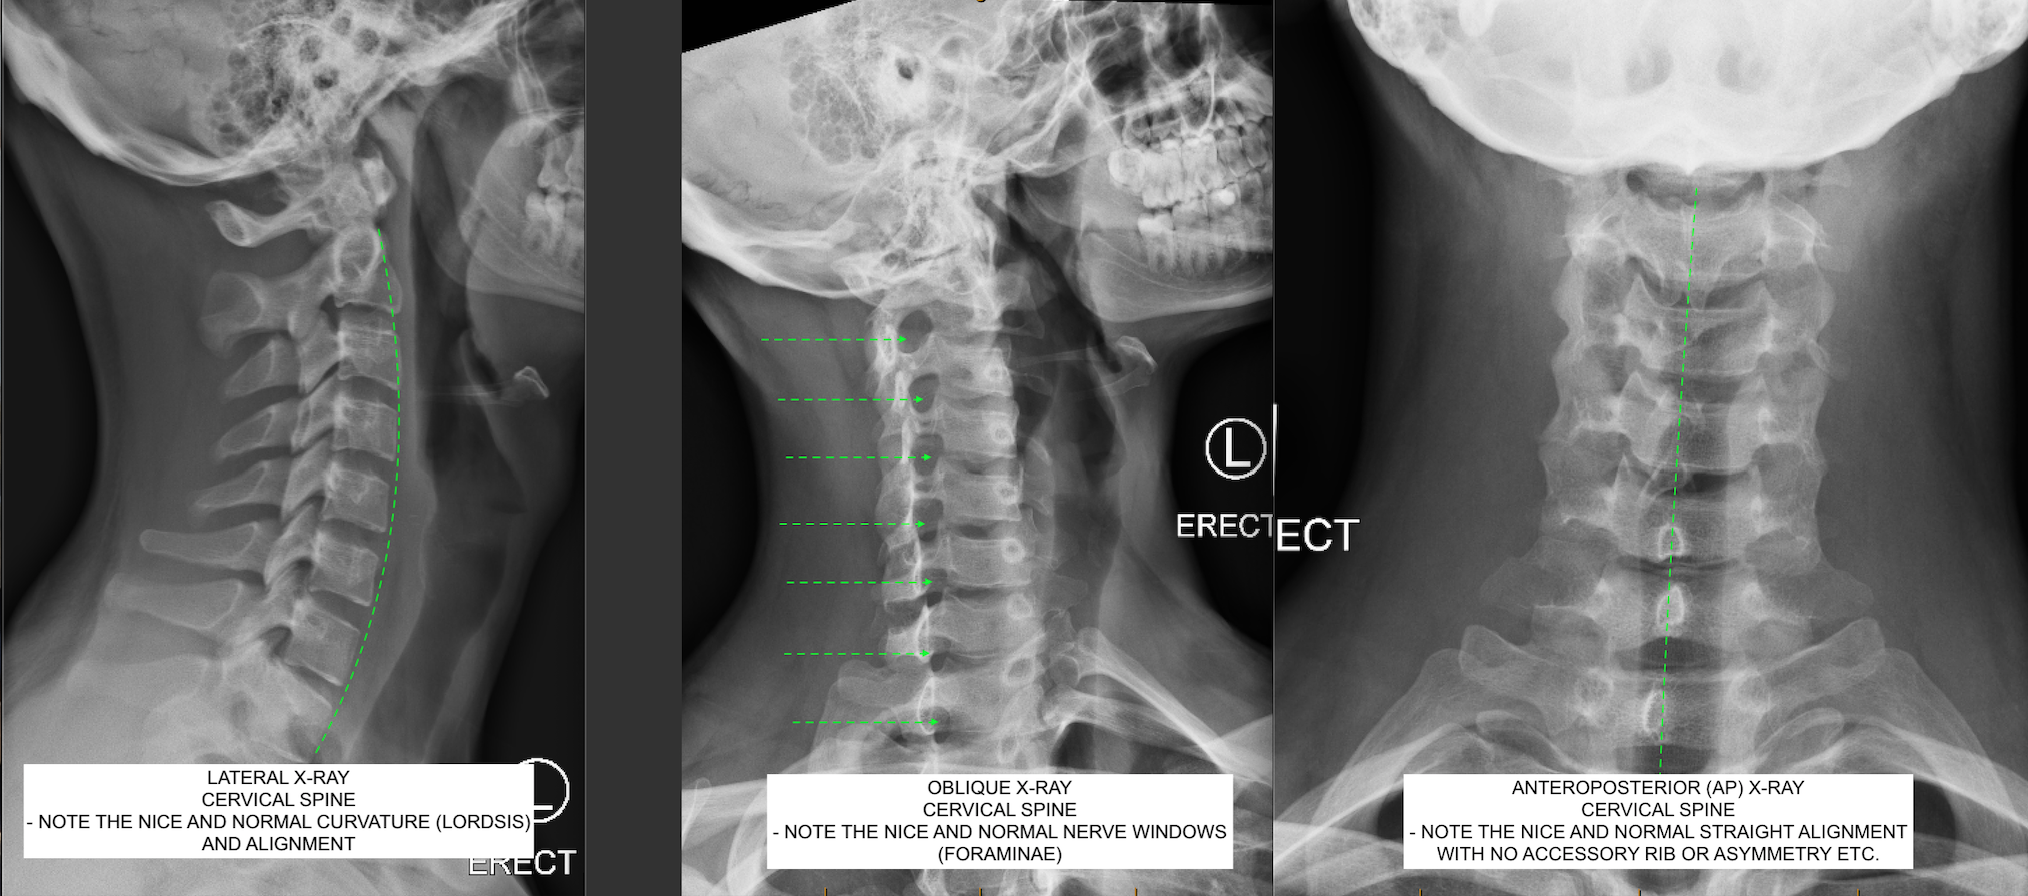
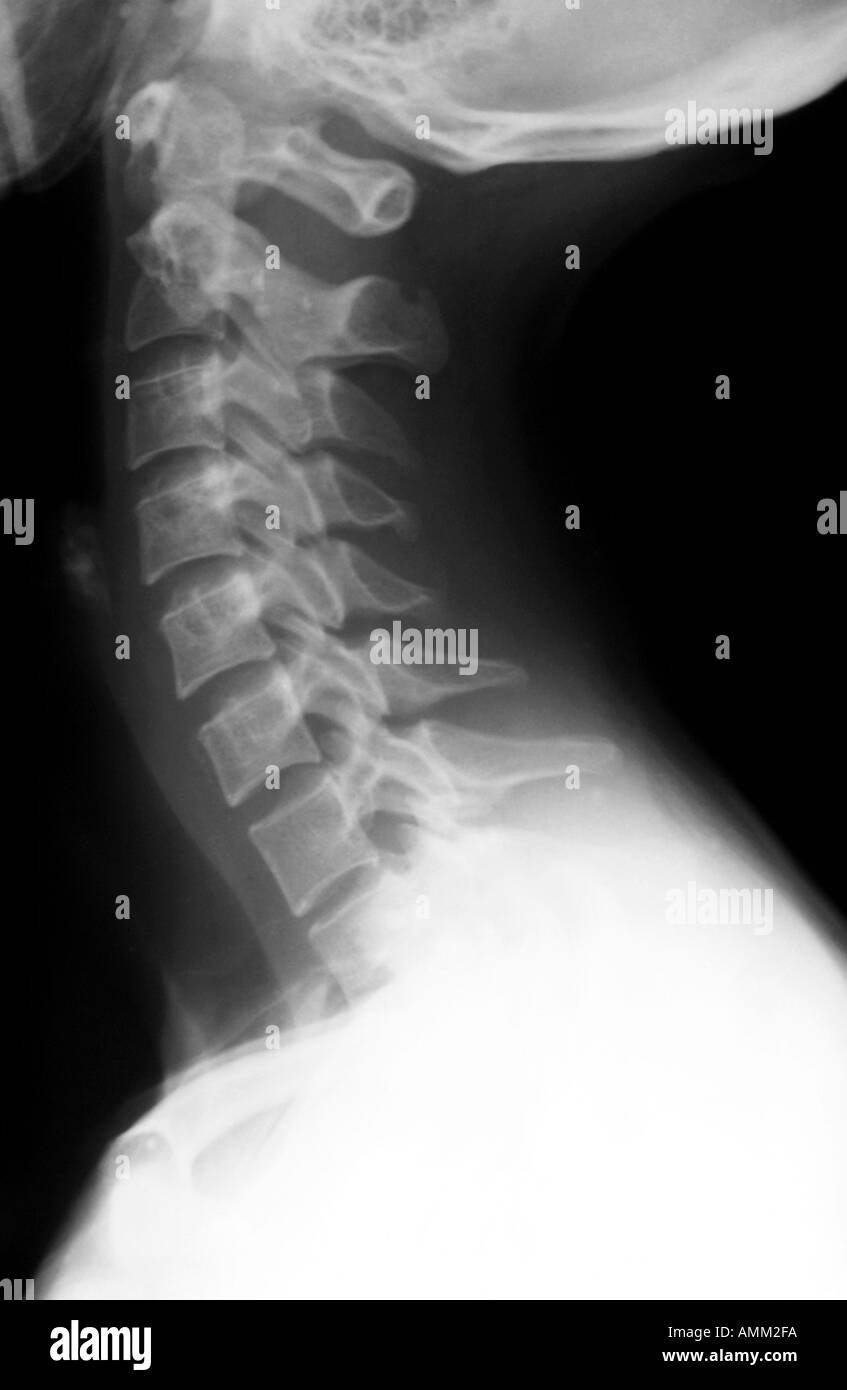
Start with the lateral view because it tells you the most per unit of time. You are looking at the cervical spine from C1 through T1 or T2, ideally with the posterior elements, vertebral bodies, and the prevertebral soft tissues all visible. The seven cervical vertebrae should stack with roughly uniform disc heights. The lordotic curve is convex anteriorly and should be smooth without abrupt angulation. Four alignment lines run along the anterior and posterior aspects of the vertebral bodies. The anterior longitudinal line traces the anterior margins. The posterior longitudinal line traces the posterior margins. The spinolaminar line connects the bases of the spinous processes where they meet the laminae. The posterior arch line follows the anterior margin of the spinous processes. In a normal study these lines are smooth. Any step-off, especially at C5-C6 or C6-C7, warrants a closer look before you call it routine. The three posterior joints form a second alignment system. The articular pillars, the lateral masses, and the facet joints should mirror each other without narrowing or subluxation. The disc spaces maintain their height, and you should be able to trace the intervertebral foramina without them looking collapsed. The dens sits centered within the lateral masses of C1, with equal spacing on both sides. That space is roughly three millimeters in adults and up to five millimeters in children before the transverse ligament is fully developed.
Soft tissue matters as much as bone on the lateral film. The prevertebral space at C2 should be less than seven millimeters, and at C6 it should be less than twenty-two millimeters. Above the clavicles, the retropharyngeal space should not bulge. If it does, you are dealing with something other than a simple strain, and the differential widens quickly. The AP view checks what the lateral view cannot. The pedicles should be symmetric. The lateral masses should be equidistant from the spinous processes. The foramina show as radiolucent ovals along the lateral margins. The spinous processes in the lower cervical spine point downward and should not be obscured by the mandible or the shoulders. If the shoulders are dragging over C7, that is a positioning problem, not a diagnosis. The open-mouth odontoid view isolates C1 and C2. The dens should be midline. The atlanto-dental interval is the key measurement here. Anything over three millimeters in an adult suggests transverse ligament injury. The lateral masses of C1 should not overhang C2 asymmetrically. Rotation will make one side look wider than the other, and that is often mistaken for pathology by anyone who has not checked the spinous process alignment first.
Get the Full Details

I once spent twenty minutes chasing a suspected C2 fracture on a lateral film from a night shift trauma call. The patient was a fifty-four-year-old male who fell from standing. The alignment looked clean, but there was a faint radiolucent line just anterior to the spinolaminar junction at C2. I flagged it as indeterminate and moved on. Two days later the same patient returned with worsening neck pain and a repeat imaging study. The CT showed a hangman-type fracture with approximately four millimeters of displacement that the initial lateral film had almost completely missed. The problem was not that the fracture was invisible; it was that I had not accounted for the fact that the patient's head was rotated slightly to the right, which masked the fracture line against the dens. I went back and measured the atlanto-dental interval again on the original images and noted the rotation in the report. That case changed how I handle every subsequent cervical spine X-ray where even minor rotation is present. I now measure the interval first, before anything else, and I do not accept a study as adequate unless the spinous processes are roughly equidistant from the lateral masses.
The Technical Requirements Behind an Actually Useful Study
A radiograph is only as good as the acquisition, and the cervical spine is unforgiving about positioning. The lateral view requires the patient to be upright with the shoulders depressed and the head neutral. The beam should be angled slightly caudad in most adults to clear the mandible from C1 and C2. If the shoulder girdle is obscuring C7, a swimmer's view helps, though that technique introduces its own variability and is harder to standardize across different technologists. Exposure factors matter more than most residents appreciate. The cervical spine requires a relatively high kVp range, usually between eighty and ninety, with milliampere-seconds adjusted to keep the noise floor down. An underexposed cervical film looks clear until you zoom in on the pars interarticularis and realize you cannot see past the soft tissue noise. I have seen studies rejected for inadequate penetration that only needed a 10 percent exposure increase, which is a trivial adjustment on any modern unit. Film or detector position determines whether you actually capture C7-T1. If the lower cervical spine disappears into the shoulders, you do not have a complete study regardless of how well C2 through C6 looks. This is one of the most common reasons for inconclusive reports, and it is entirely preventable. Depressing the shoulders with sandbags or having the patient take a deep breath and hold it usually does the trick.
Counter-Intuitive Points Beginners Miss
One thing that does not get emphasized enough is that the normal cervical spine is not a straight column. Pseudosubluxation of C2 on C3 occurs in up to fifteen percent of normal children and sometimes in adults with ligamentous laxity. It appears as a forward slip of two to three millimeters on the lateral view, but the posterior elements remain aligned. If you read that as a traumatic subluxation, you are not being careful enough. Check the spinolaminar line. If it is smooth, it is pseudosubluxation, not fracture-dislocation. Another commonly overlooked point is that the normal variation in disc height is larger than most textbooks suggest. C5-C6 is typically taller than C6-C7 even in healthy individuals. Comparing adjacent levels against each other is more reliable than comparing absolute measurements against a chart value. The age-related loss of lordosis is also frequently overcalled. A patient who is in pain will guard their neck and appear straight on the film. That is not structural kyphosis. Repeat the view with a gentle chin lift and you often see the curve reappear. The AP view is also dismissed too readily. It is the only projection that shows the lateral mass width clearly, and asymmetry in lateral mass distance from the midline is the earliest sign of a rotational injury. You will miss a C1 burst fracture pattern on a lateral view alone if you are not comparing the overhang of C1 on C2 in the open-mouth projection.
When the X-Ray Is Not Enough
Cervical spine radiography has hard limits. It is a two-dimensional projection of a complex three-dimensional structure. Overlapping anatomy means certain fractures simply do not show. You cannot reliably assess the spinal cord, the discs, or the neural foramina beyond indirect signs. A patient with radiculopathy and a normal X-ray does not have a normal cervical spine. They have a normal bony contour on plain film, which is a different statement entirely. CT is the appropriate next step when you need to exclude a fracture in a high-risk mechanism, when the X-ray is technically inadequate, or when you suspect a ligamentous injury that would not be visible on plain film. MRI is required when neurological deficit is present without clear bony explanation, or when you need to evaluate the cord itself. No amount of X-ray expertise replaces these modalities when the clinical scenario demands it. I also do not recommend using plain films as a screening tool for asymptomatic patients. The prevalence of degenerative findings in the asymptomatic cervical spine is high, and reporting incidental spondylosis on a screening study generates more follow-up imaging than it prevents. I have seen the cycle play out multiple times.
Practical Workflow for a Routine Normal Cervical Spine X Ray Review
I review in a fixed sequence so I do not skip views or jump between findings arbitrarily. First, I confirm the study is complete: lateral, AP, and open-mouth views present and labeled correctly. I check the patient's name, date, and side markers before I look at anything else. Then I assess technical adequacy: rotation, penetration, and inclusion of C7-T1. I note any limitation in the report if the study falls short. Next I go to the lateral view. Alignment lines first. Then disc spaces. Then soft tissues. Then the posterior elements and facets. I measure the atlanto-dental interval if the odontoid view is available and compare it to my mental baseline. On the AP view I check symmetry, lateral mass distance, and foramina. On the open-mouth view I verify dens centrality and the atlanto-dental interval a second time. If everything is within normal limits, I state exactly what is normal. I do not say "unremarkable" and move on. I specify the levels assessed, note that alignment is preserved, and confirm no acute abnormality is identified. If there is a mild degenerative finding, I describe it precisely and note that it is within expected limits for the patient's age rather than calling it normal or abnormal without qualification.
A normal cervical spine X-ray is a useful clinical document when it is complete, technically adequate, and interpreted with awareness of its limitations. It rules out many acute processes but confirms almost nothing about soft tissue pathology. Treat it accordingly and the reports you write will be sharper than most.