The Pulse Oximeter Problem
Most people pick up a pulse oximeter, stick it on their finger, and treat whatever number appears as gospel. The problem is that machine doesn't actually measure oxygen content. It measures the percentage of hemoglobin binding sites occupied by oxygen versus the ones available, and it does that by shining two wavelengths of light through your fingertip and comparing how much gets absorbed. That math has blind spots. I spent years on surgical floors and later in critical care units, where we ran pulse oximeters on everything from neonates to end-of-life patients. The readings were rarely wrong in isolation, but they were frequently misinterpreted, and that distinction matters a lot.
Understanding Normal Oxygen Saturation By Age
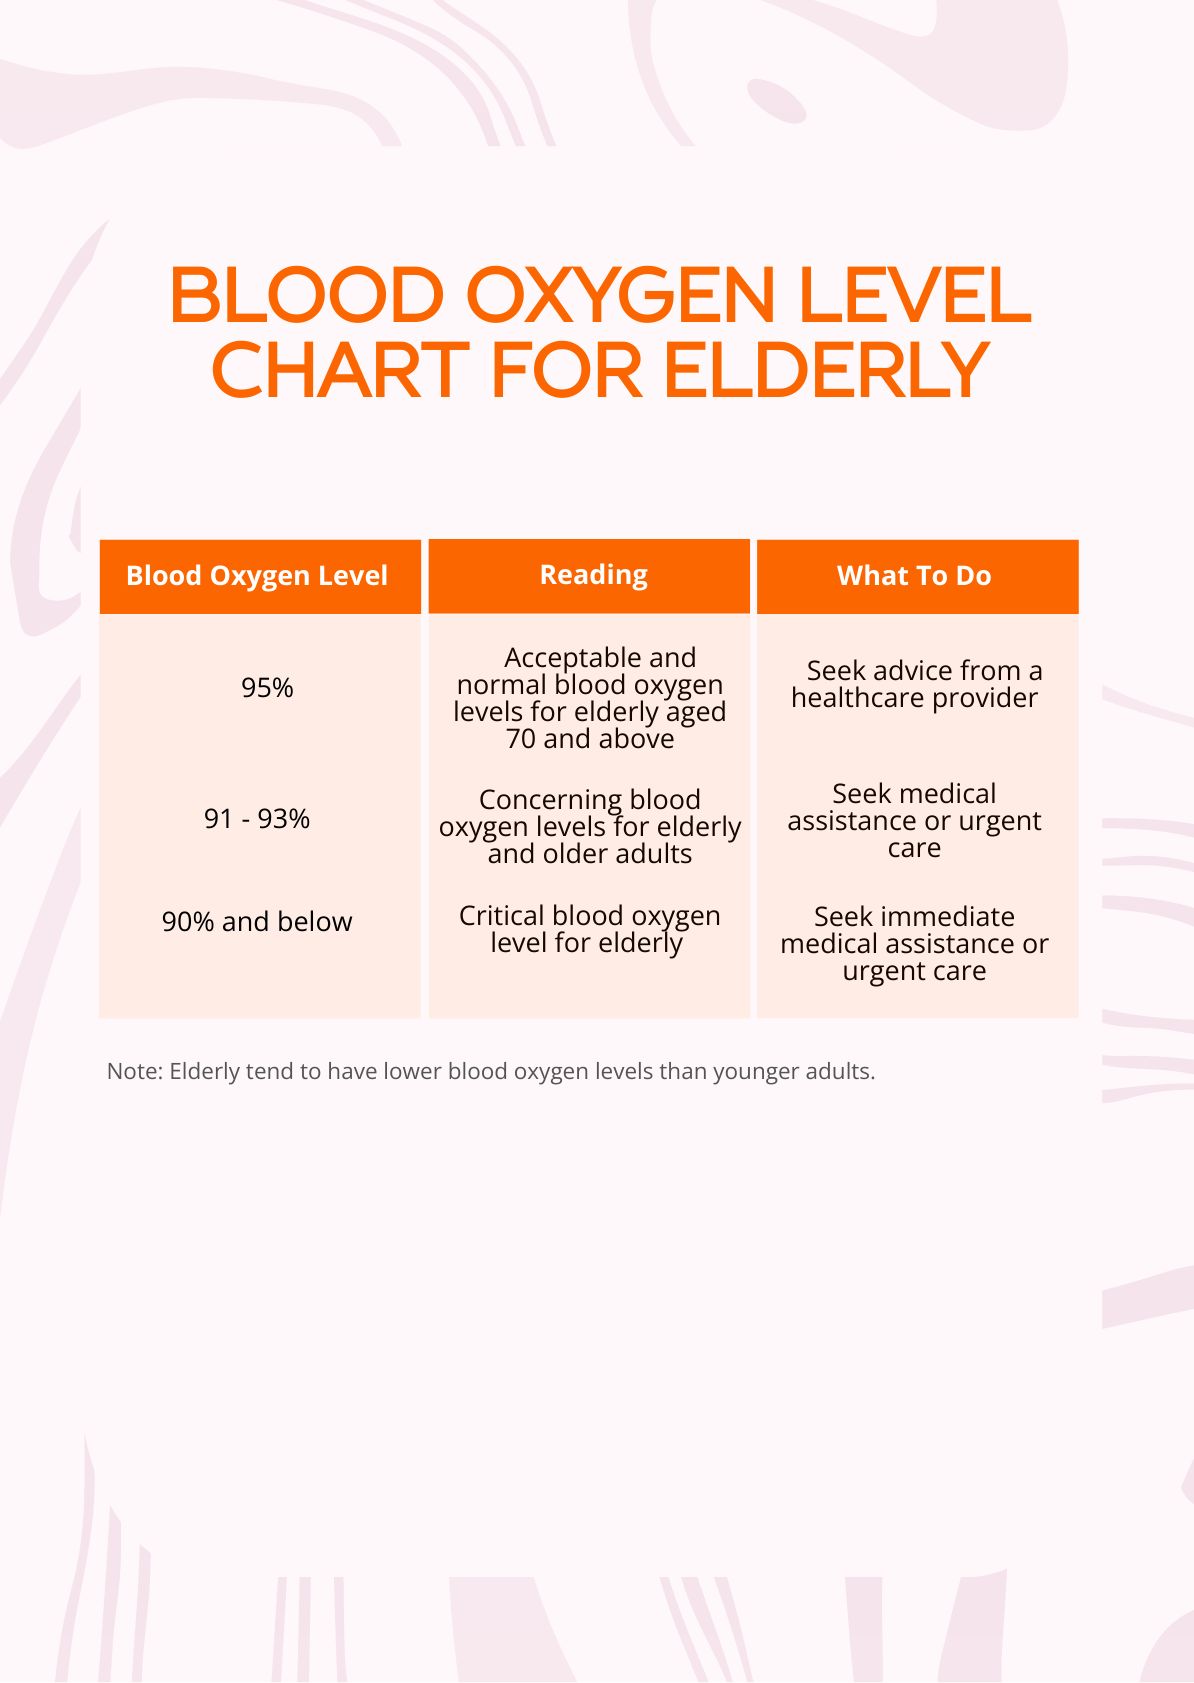
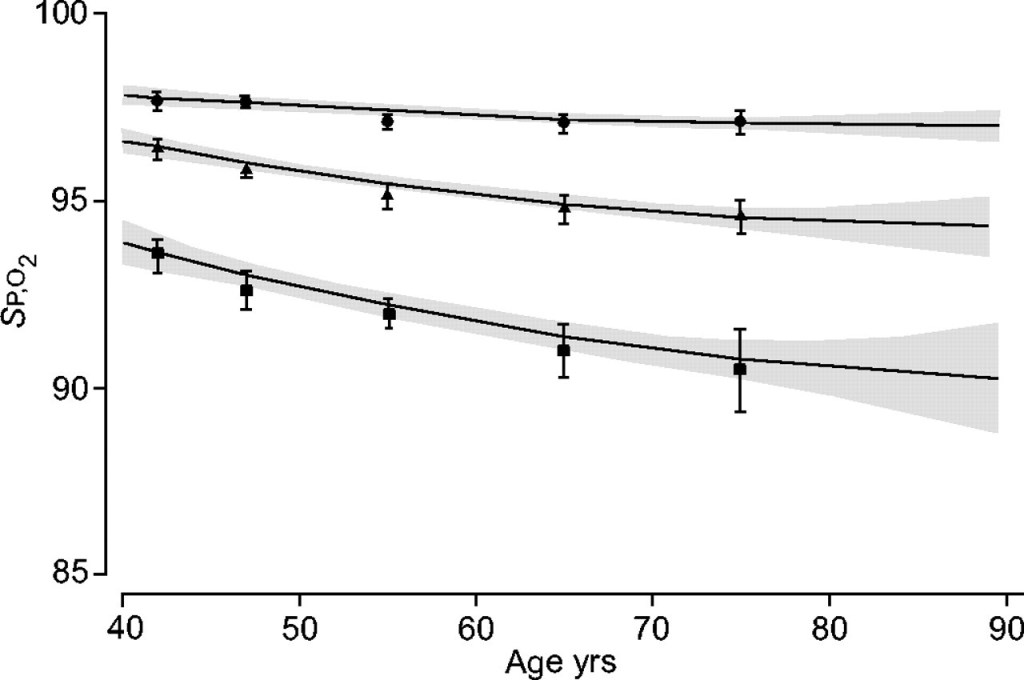
Healthy oxygen saturation, measured as SpO2, follows a fairly narrow band for most of adulthood. The reference ranges shift slightly depending on who you're measuring and under what conditions. For newborns in the first hours after birth, saturations start lower and climb gradually over the first day or two. By the time they're a week old, a normal range sits around 95 to 100 percent. Infants and young children hold steady in that same 95 to 100 window. Adults from roughly 18 through 65 maintain 95 to 100 percent at sea level. Once you hit older adulthood, particularly past 70, a saturation in the low to mid 90s isn't automatically alarming, especially if the person has chronic lung conditions, but it's worth tracking over time rather than treating a single reading as a crisis. The formula behind the device is the ratio of oxyhemoglobin to total measurable hemoglobin, expressed as a percentage. Most consumer and clinical pulse oximeters have an accuracy rating of plus or minus 2 percent between 70 and 100 percent saturation. That sounds precise until you're looking at a reading of 93 and trying to decide whether the person needs intervention or just needs a warmer hand.
What Actually Affects the Reading
Poor peripheral perfusion is the most common culprit for a deceptively low or unstable reading. When someone's hands are cold, their body shunts blood away from the extremities. The oximeter can't get a clean signal and either displays an error or gives you a number that has nothing to do with actual arterial oxygenation. I had a patient in the ICU whose saturation would read 88 percent on the left index finger, then 97 percent on the earlobe probe. The earlobe was warmer and better perfused. The real answer was somewhere closer to the higher number, though we confirmed with an arterial blood gas draw because the clinical picture didn't quite match. Nail polish, especially dark colors like black, blue, and deep red, can absorb the infrared light the device relies on and skew readings downward by several percentage points. Acrylic or gel extensions do the same thing. I worked a shift where a surgeon was frustrated by a supposedly dropping saturation on a post-op patient, only to discover she'd painted her nails a deep purple. We moved the probe to an bare finger and got an immediate jump to 98 percent. Movement artifact is another constant headache. Shivering, tremors from Parkinson's, or even restless legs will cause the sensor to misinterpret motion as signal. Modern devices have motion-tolerance algorithms, but they're not perfect. If the waveform on the display looks jagged or irregular, the number is unreliable regardless of what it says.
Get the Full Details

Edge Cases Where the Device Lies
Carbon monoxide poisoning is the classic scenario where pulse oximetry fails dangerously. Carboxyhemoglobin absorbs light at nearly the same wavelength as oxyhemoglobin, so the device reads CO-bound hemoglobin as if it were carrying oxygen. A patient could have a functional oxygen saturation well below 80 percent and the pulse oximeter would display 98 percent. There's no workaround with a standard two-wavelength device. You need a co-oximeter, which uses four or more wavelengths, to get an arterial blood gas that actually distinguishes the hemoglobin species. I encountered this during a winter flu season when a patient presented with headache and confusion, saturations of 99 percent on the monitor, and normal lung sounds. The ABG told a completely different story, and the CO-oximetry result confirmed significant carbon monoxide exposure from a faulty furnace. The pulse oximeter reading would have sent that person home. Anemia presents a different kind of trap. A patient can be severely anemic with a hemoglobin of 7 or 8 and still maintain a perfectly normal SpO2 of 97 percent. The saturation tells you nothing about total oxygen content because it doesn't account for how much hemoglobin is actually present. Oxygen content depends on both saturation and hemoglobin concentration. That's why we never treat the number alone. A hemoglobin of 7 with 97 percent saturation delivers far less oxygen to tissues than a hemoglobin of 14 with the same saturation, even though the pulse oximeter can't tell the difference. methemoglobinemia, whether from certain medications like dapsone or benzocaine sprays, causes the pulse oximeter to trend toward 85 percent regardless of the true saturation. It's a predictable artifact that seasoned clinicians learn to spot because the reading won't improve with supplemental oxygen and the patient may have a cyanotic appearance that seems disproportionate to the oxygen number.
Practical Interpretation
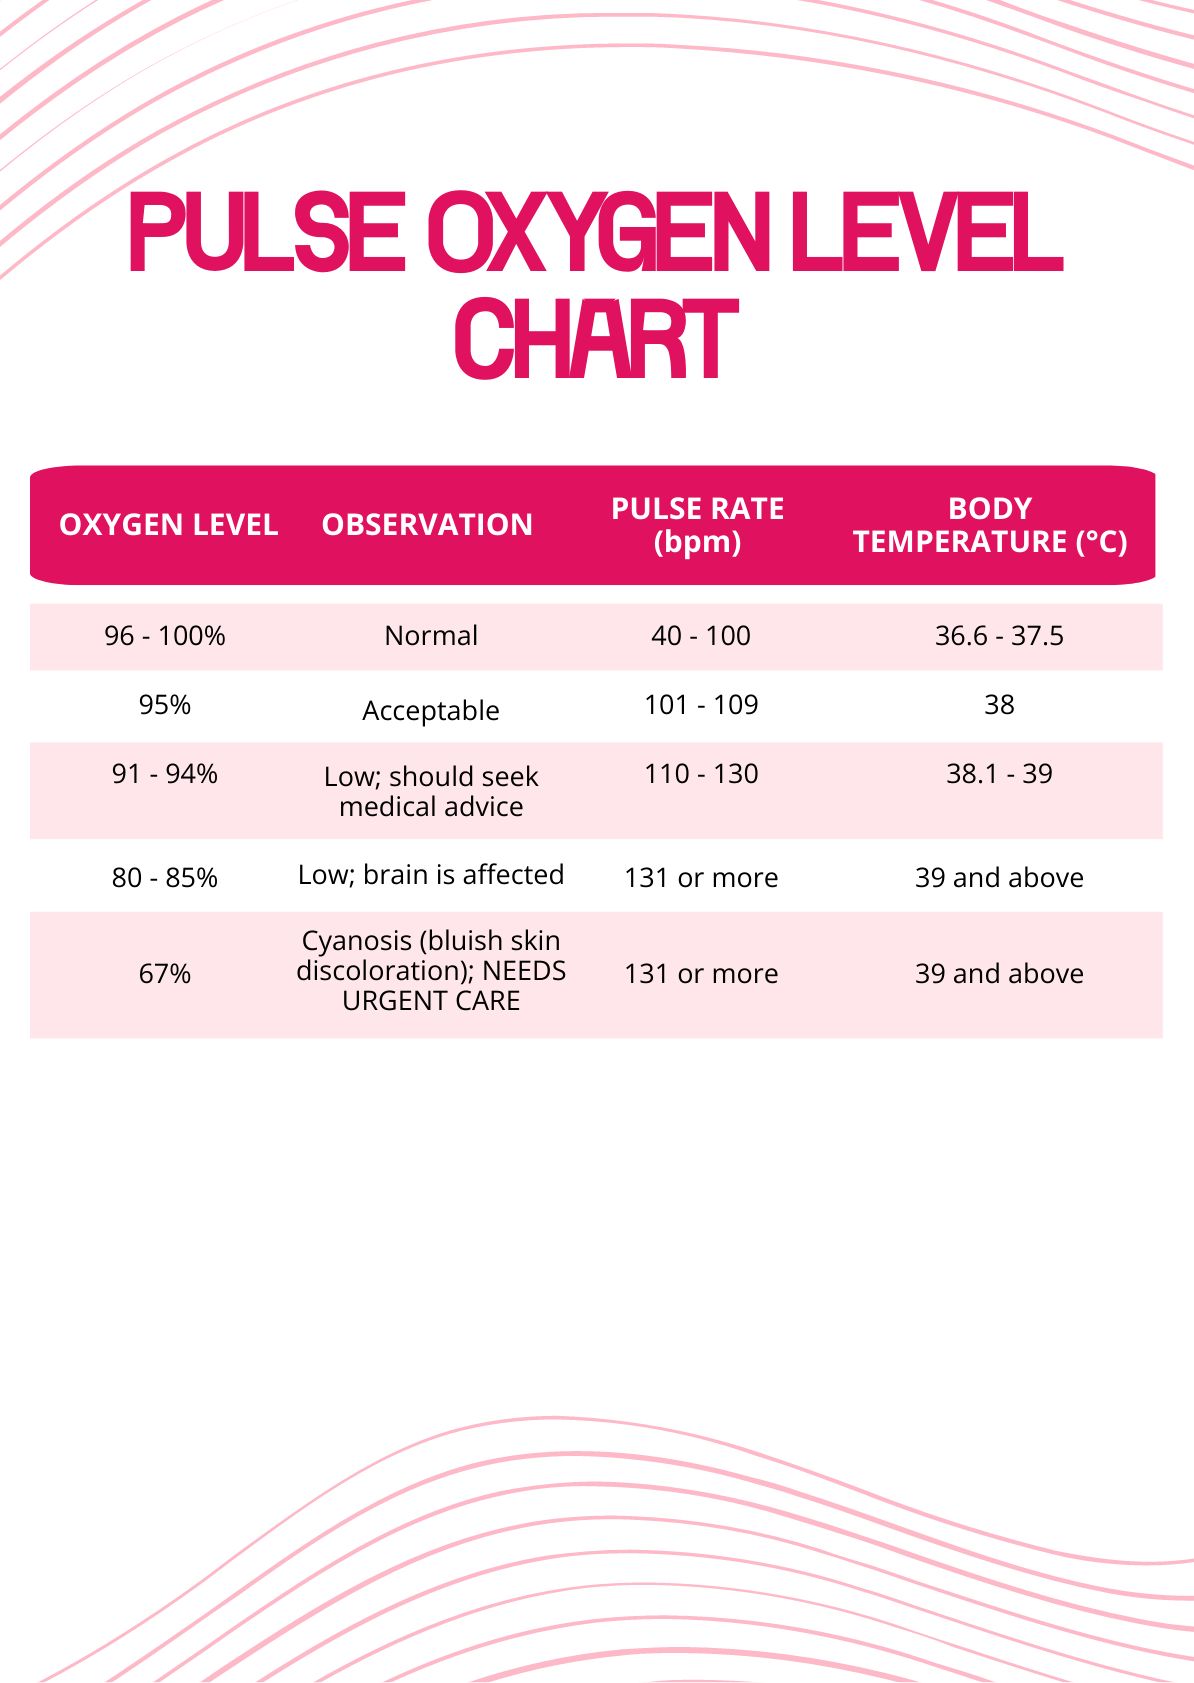
For a healthy adult at sea level, anything above 95 percent is normal. Between 91 and 94 percent warrants attention and monitoring, especially if it's a new drop from the person's baseline. Below 90 percent is generally the threshold where supplemental oxygen is considered, but that decision always depends on the clinical context. A patient with advanced COPD who chronically runs in the low 90s is in a different category than a previously healthy person who just dropped to 89 percent. Altitude changes the baseline. At higher elevations, the partial pressure of oxygen in the air is lower, so saturation naturally sits a few points below sea-level norms. Someone living at 6,000 feet might normally read in the high 90s rather than the mid-to-upper 90s, and that's expected, not pathological. The real utility of pulse oximetry isn't the single number. It's the trend. A saturation dropping from 98 to 94 over three hours is clinically significant. A saturation that oscillates between 94 and 96 while the person is sleeping is usually noise. Watch the waveform, not just the display. Most devices show a plethysmographic wave alongside the number. A strong, regular wave means you can trust the reading. A flat or chaotic trace means you should move the probe or find another measurement method.
When to Trust It and When Not To
Pulse oximetry is excellent for screening and continuous monitoring in stable patients. It's terrible for diagnosing the cause of hypoxemia. It can't tell you whether low oxygen is from shunting, ventilation-perfusion mismatch, diffusion impairment, or hypoventilation. For that, you need an arterial blood gas, chest imaging, and clinical assessment. The oximeter is a vital sign, not a diagnosis. Consumer-grade devices vary widely in accuracy. Many cheap finger probes from online marketplaces haven't been validated against clinical standards. If you're using one for personal health tracking, compare it against a clinical reading when possible. Place your home device on your finger while someone checks you with a medical-grade unit, and note the difference. A consistent two to three point offset is normal. A ten-point gap means the device needs replacing. I've also seen people become obsessed with hitting 100 percent and start Supplementing oxygen unnecessarily because they think any number below that is deficient. Healthy lungs at sea level routinely produce saturations in the high 90s, and 97 or 98 is fine. Pursuing 100 percent is chasing an artifact of optimal conditions, not a health target.
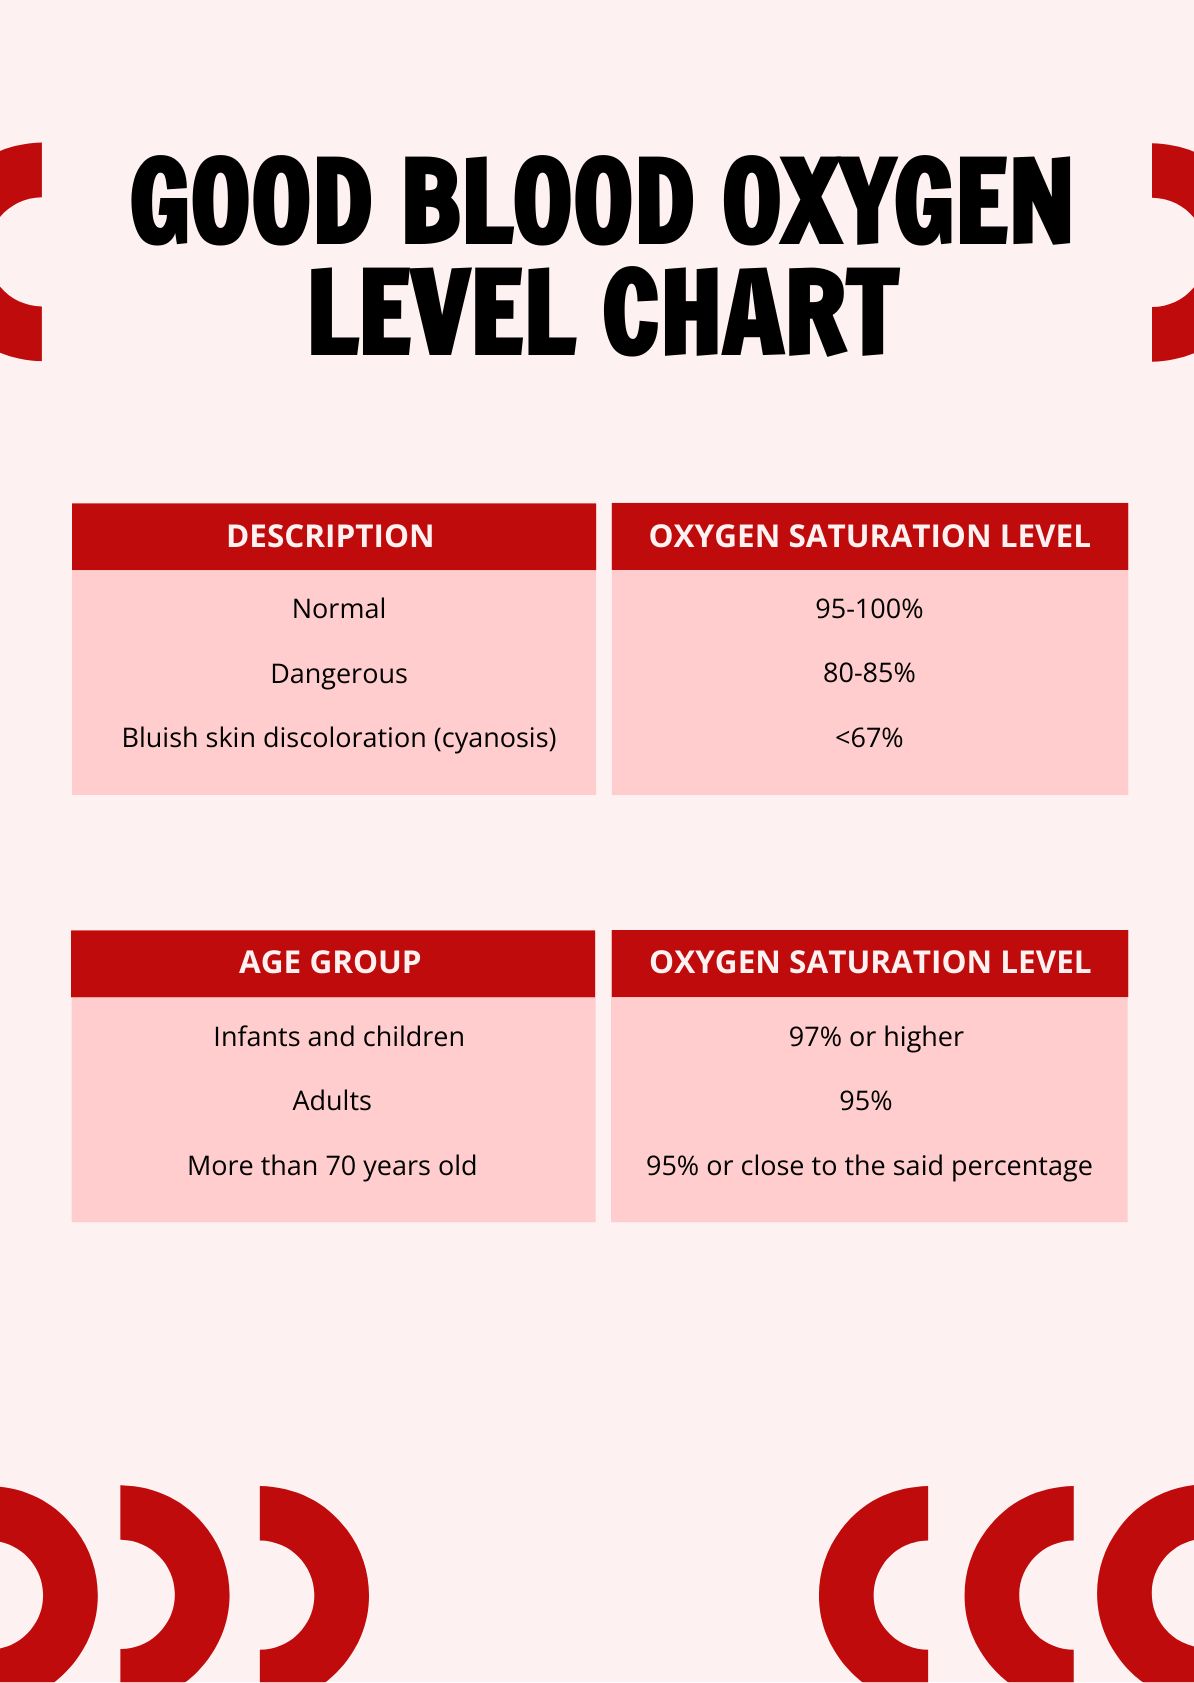
The bottom line is that Normal Oxygen Saturation By Age gives you a framework, but the framework only works when you understand what the device actually measures and what it deliberately ignores. The number on the screen is a piece of data, not the whole picture. Treat it that way and you'll avoid most of the mistakes people make with it.