Reading a Chest X-ray Without Losing Your Mind
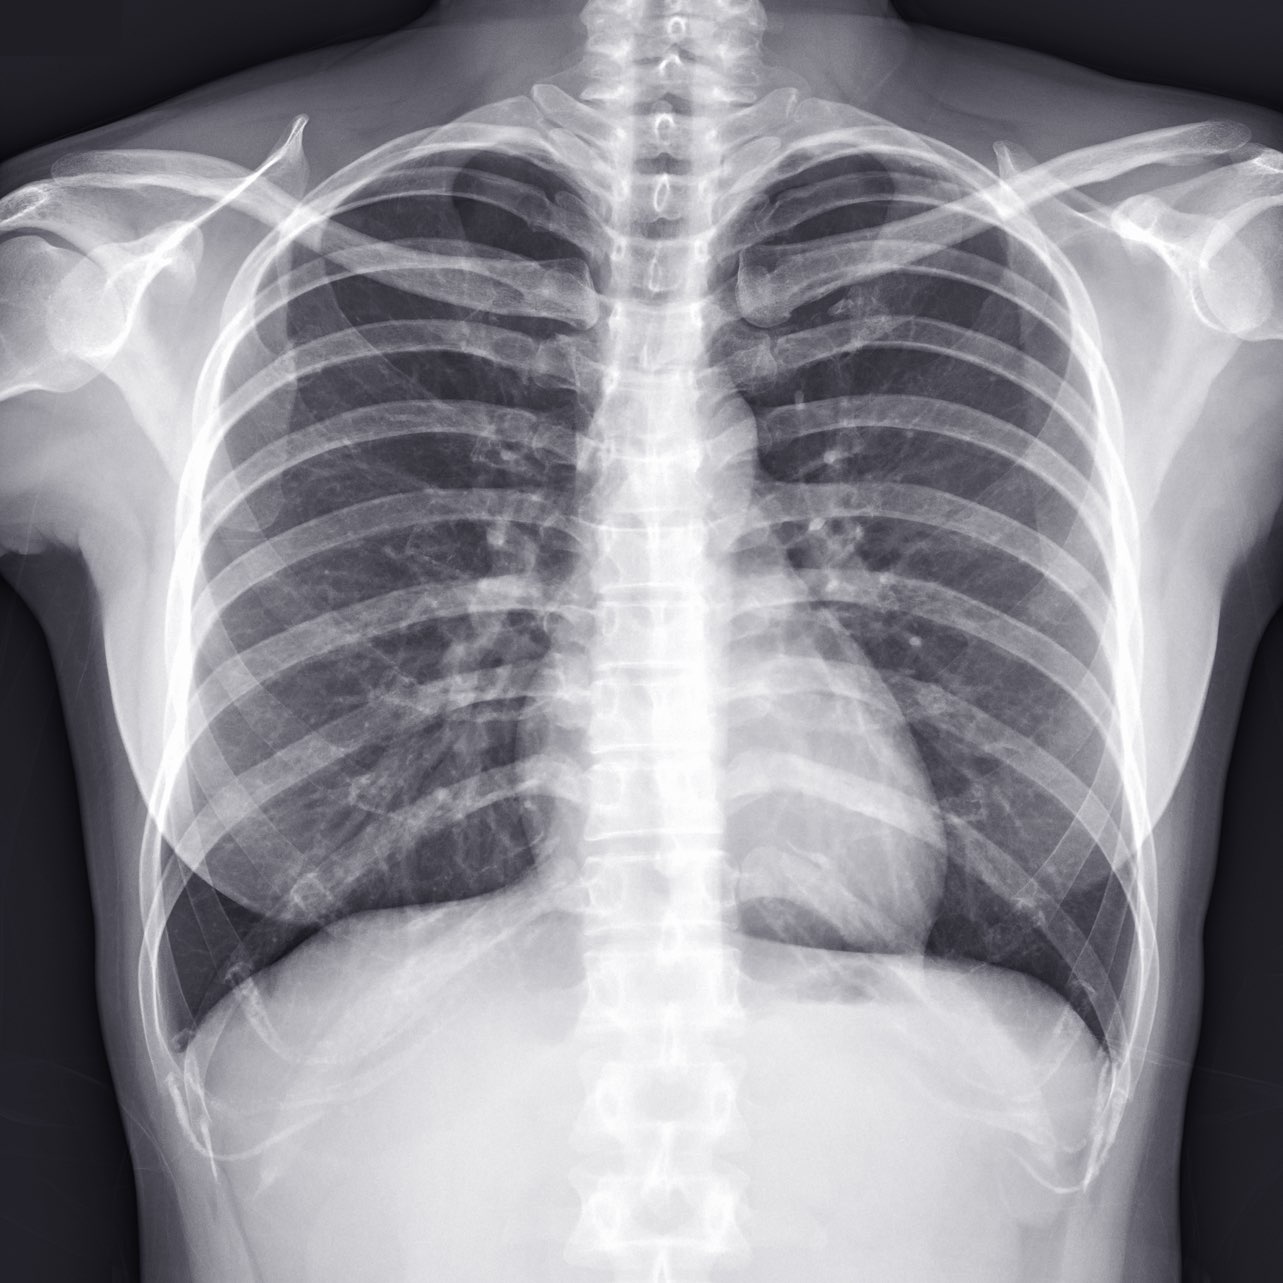
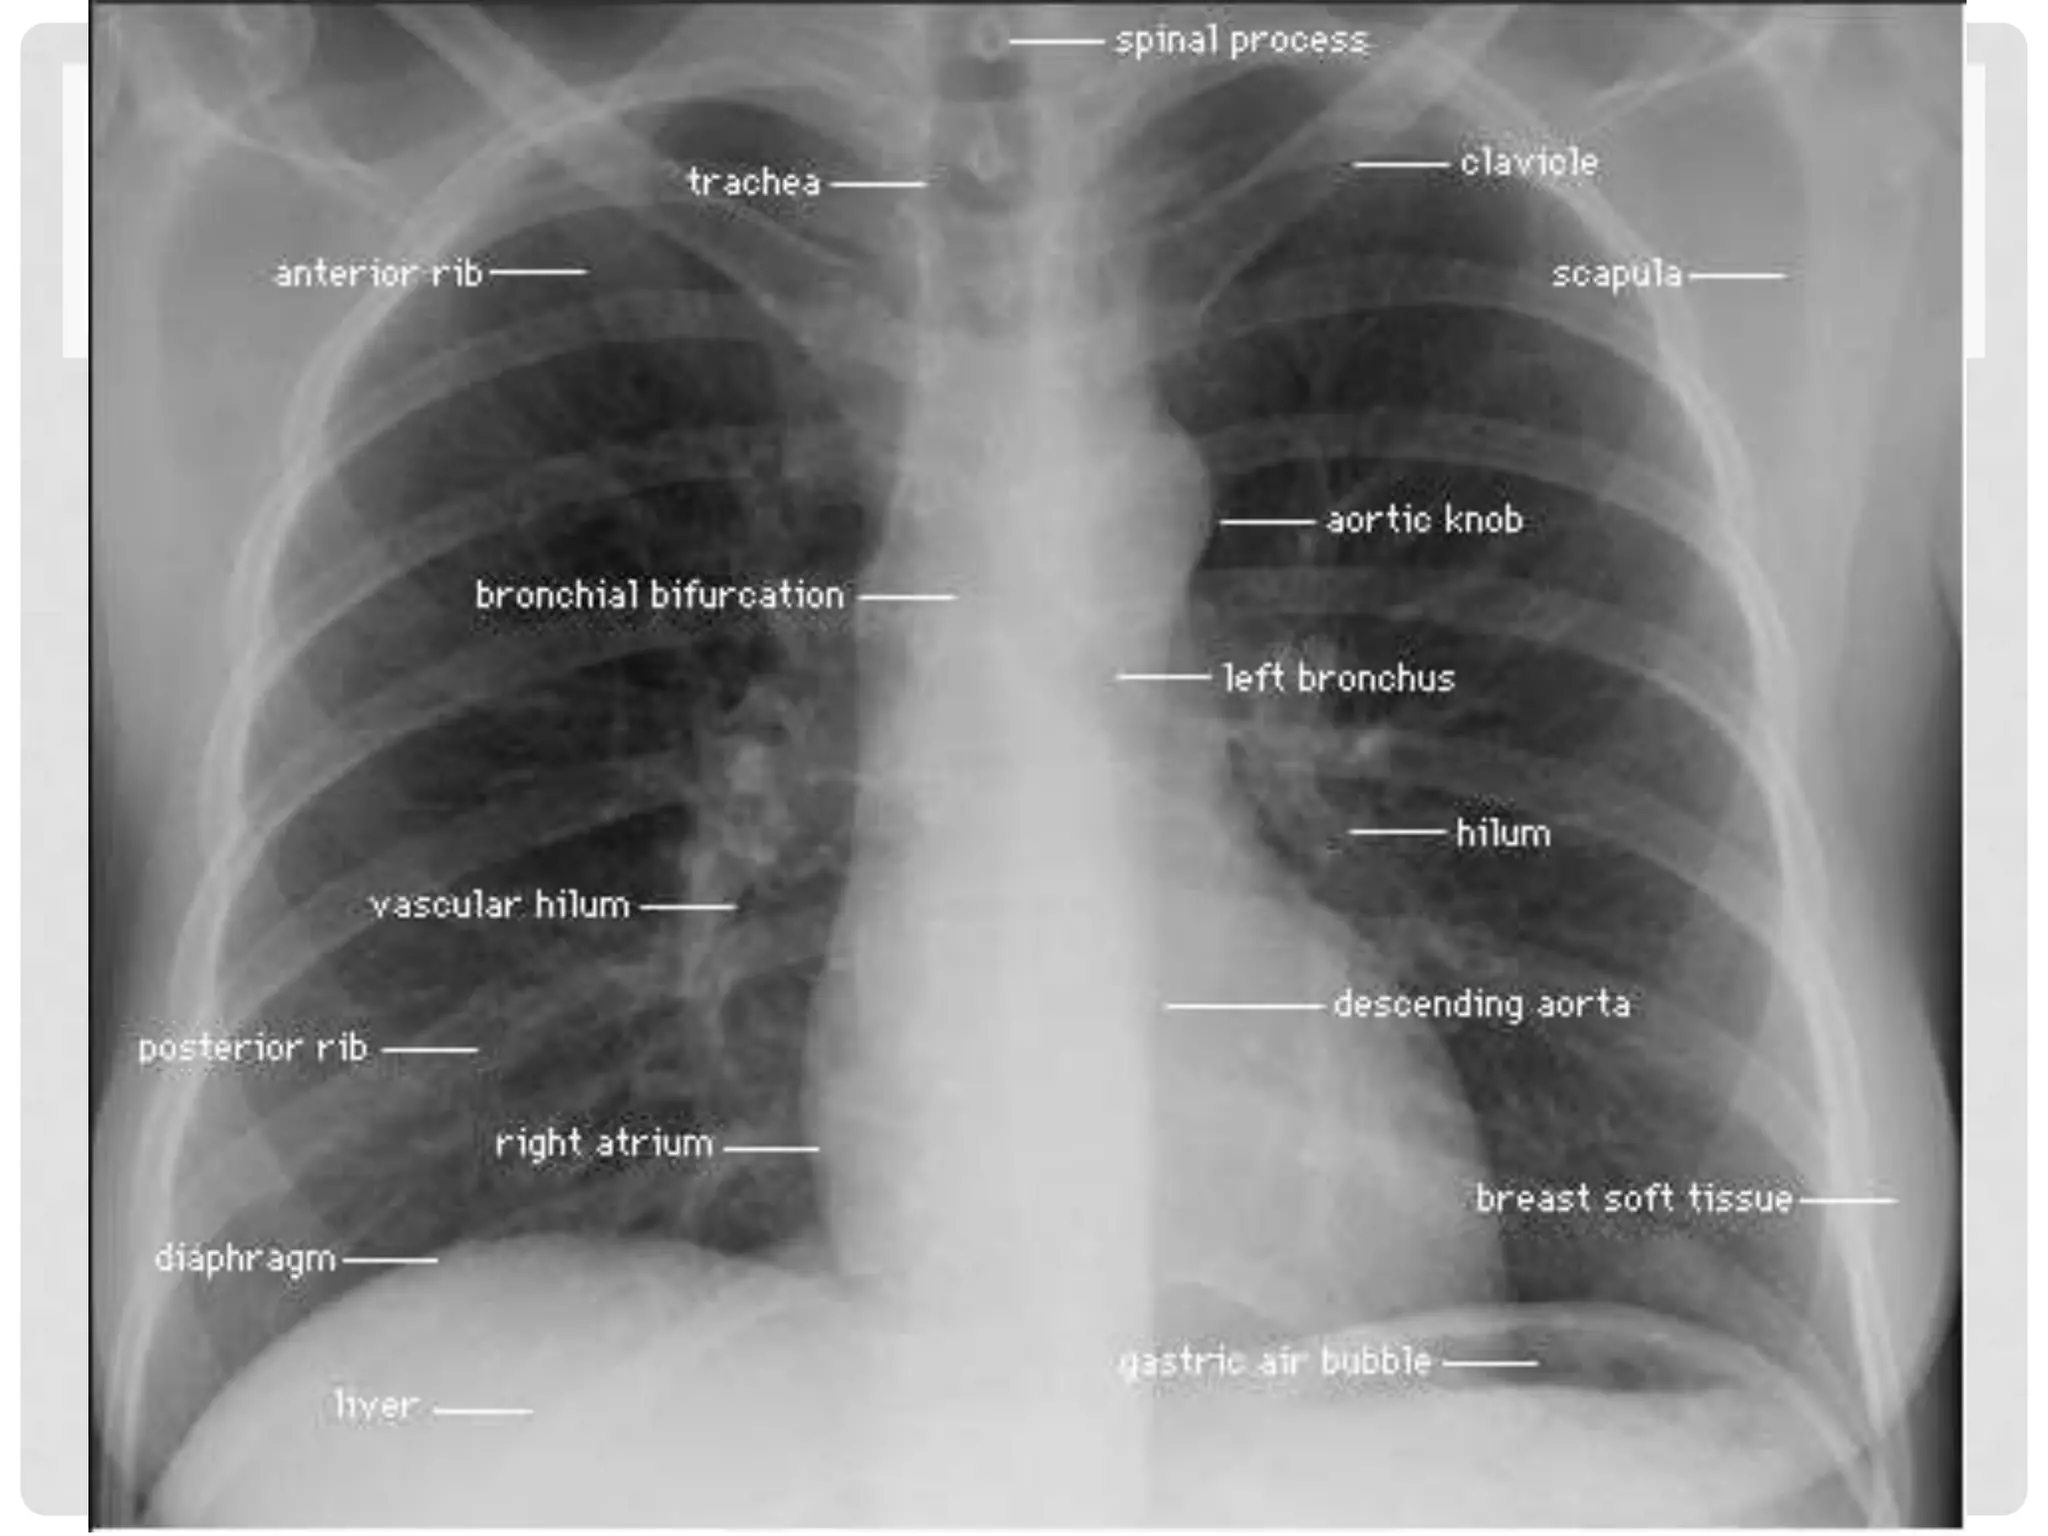
The biggest mistake people make when learning to read a normal chest radiograph is trying to memorize every single structure before they understand the overall picture. You end up staring at the lung apices for twenty seconds while the pneumothorax on the opposite side completely passes you by. It happened to me. I had this habit of checking the left heart border first because I kept missing that one. Eventually I just started working through it in a fixed sequence and stopped second-guessing myself. A normal PA chest X-ray has a few non-negotiables. The lungs should be clear and dark, with the vascular markings fading as they extend peripherally. The costophrenic angles have to be sharp on both sides — that's the first place fluid hides. The heart size is considered normal when the cardiothoracic ratio is under 0.5, but only on a properly inspirated PA film. The trachea sits midline. The diaphragm domes higher on the right because the liver pushes up against it. Those are the basics, and anything outside that range needs an explanation. Here's the thing most tutorials skip. The mediastinum isn't one uniform shadow. It has distinct contours. The aortic knuckle should be visible on the left upper border. The pulmonary artery segment sits just below that and may be slightly prominent in younger people and that doesn't necessarily mean anything. The left heart border is formed by the left ventricle. The right heart border is the superior vena cava above and the right atrium below. Knowing which structure forms each border tells you where to look when something looks enlarged.
I remember one case where a patient came in with a "normal" chest X-ray reading, but they were clearly short of breath. Turns out the film was taken in AP portable position, not PA, and the heart looked borderline enlarged purely because of magnification from the shorter source-to-detector distance. The radiologist had flagged it as suspicious and the cardiologist was already ordering an echo. We retried it as a proper PA upright and the cardiac silhouette normalized completely. Portable films exaggerate heart size by roughly fifteen to twenty percent compared to a standard PA view. That margin is enough to throw off an inexperienced reader. The diaphragm deserves more attention than it gets. On a normal film, the right hemidiaphragm sits slightly higher than the left. If the right side drops below the tenth posterior rib on a fully inspirated film, that's abnormal. But here's a practical trick I use. Ask the patient to take a deeper breath if the inspiration looks shallow. Count the anterior ribs. You should see about seven to nine anterior ribs above the diaphragm on a good inspiratory effort. Fewer than that and the whole film gets harder to trust because structures get crowded and the heart appears larger than it is. Bony structures matter too. The clavicles should be equidistant from the spinous processes, which tells you the patient wasn't rotated. If one clavicle looks larger or closer to the midline than the other, the patient was rotated and that rotation can mimic pathology. A rotated trachea looks deviated. It isn't. The gastric air bubble should be visible under the left hemidiaphragm. Its absence isn't an emergency, but it's worth noting if you're evaluating the left lower zone.
Hard-Won Details That Actually Matter
The spine sign is something I wish everyone learned on day one. Look at the thoracic vertebrae through the heart shadow. On a normal film, the vertebral bodies should get progressively darker as you go down, matching the density of the adjacent lung. If a lower thoracic vertebra becomes whiter instead of darker, that's a retrocardiac opacity — usually left lower lobe consolidation. It catches pneumonia that would otherwise hide behind the heart. I caught a missed lingular pneumonia this way once. The patient was treated for bronchitis for two weeks before someone finally looked at the spine sign properly. Nipple shadows trip people up constantly. They appear as paired rounded densities at approximately the fourth or fifth anterior intercostal space. The trick is checking if they're present on both sides at roughly the same level. They're usually symmetrical and have a consistent shape. If you're unsure, you can place radiopaque nipple markers on the next film. Or you can just check the lateral view — they won't be there because they're projected over the anterior chest wall on the PA. The hila deserve a moment. Both hila should sit at roughly the same level, with the left slightly higher due to the aortic arch. The left hilum is formed mainly by the descending pulmonary artery. The right hilum is formed by the right pulmonary artery crossing over the bronchus. If one hilum looks denser or larger, that needs investigation. But asymmetry alone isn't diagnostic. I've seen perfectly normal patients with a slightly more prominent left hilum simply because of how the pulmonary artery courses around the left main bronchus in their particular anatomy.
Get the Full Details
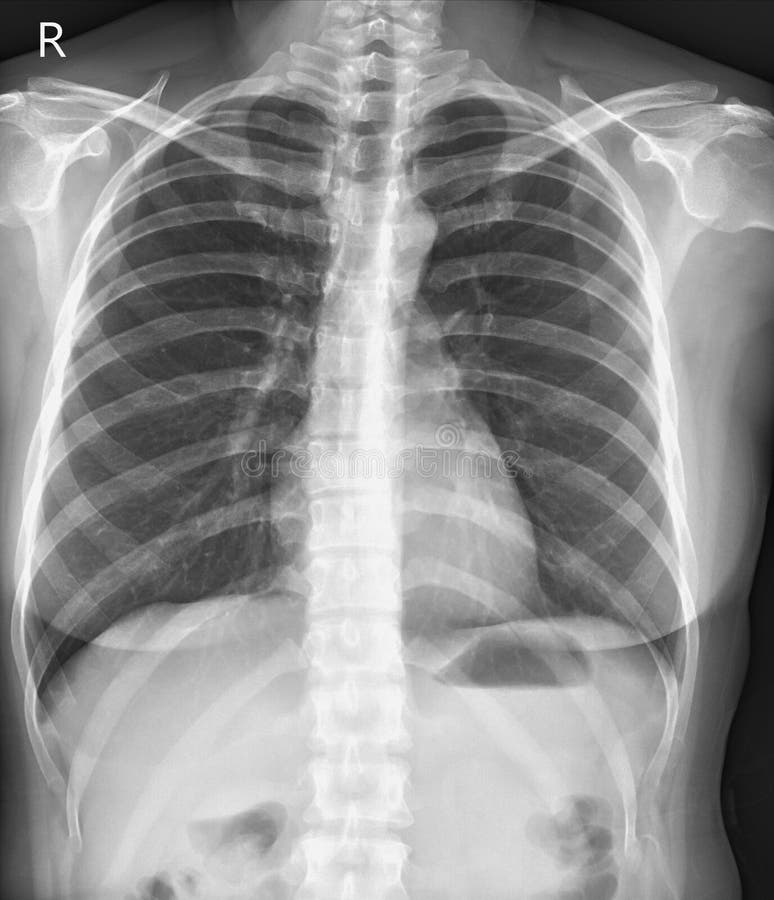
Lung volumes are another area where beginners waste time. A normal lung on a good PA film should fill most of the hemithorax. Hyperinflation flattens the diaphragm and makes the heart look thin and vertical. That's what COPD does. But mild hyperinflation is also normal in tall, thin individuals. Don't overcall it. Just note it and move on. Conversely, low lung volumes make the pulmonary markings look more crowded and the heart look bigger. This is extremely common in postoperative patients or anyone who couldn't take a full breath during the exposure. There's a subtlety with the azygos vein that people miss. It runs along the right aspect of the trachea and arches over the right main bronchus before entering the superior vena cava. On a normal film, you might see a faint vertical line in the right paratracheal region. If it becomes prominent and rounded, that's azygos fissure or azygos vein distension, which can happen in right heart failure. It's a small sign but it's specific when you know to look for it.
Where This Approach Breaks Down
A standard PA chest radiograph has real limitations and you need to accept them upfront. It's a two-dimensional projection of three-dimensional structures. Anything behind the heart, behind the diaphragm, or superimposed on the mediastinum can be completely hidden. Subtle nodules under a millimeter won't show up. Early interstitial disease might not be visible until it's more advanced. The sensitivity for detecting small pleural effusions is roughly fifty percent on an upright film — you need at least two hundred to three hundred milliliters of fluid before it blunts the costophrenic angle visibly. If you suspect pathology that a chest X-ray might miss, a CT scan is the obvious next step. It picks up things the plain film simply cannot resolve. But I've seen too many healthy people get ordered CTs after a radiographer flagged a suspicious nodule on an X-ray that turned out to be a confluence of normal vascular markings. The chain of unnecessary imaging is real and costly. That's why spending time learning what's actually normal matters more than memorizing every rare abnormality. The lateral view adds information but it's frequently omitted in emergency settings because it takes extra time and the patient often can't cooperate fully. A poor-quality lateral is worse than useless because it introduces artifacts that look pathological. I've seen subpleural lines on bad laterals that everyone assumed were fibrosis until a repeat film showed it was just patient movement during exposure.
In critically ill patients, portable AP films are the norm and they introduce a whole set of confounding factors. The heart is magnified. The lung volumes are low. Lines and tubes are everywhere and they create overlapping densities that clutter the image. Reading a normal portable film requires more experience than reading a standard PA because the baseline for normal shifts. What looks abnormal on a portable might be perfectly normal for that positioning. Context matters more than the image itself.

Practical Workflow That Saves Time
My routine is brute force and boring because boring works. I check patient identity first. Then I assess the technical quality — rotation, inspiration, exposure, penetration. If the spine is visible behind the heart, the exposure is adequate. If the exposure is poor, I note it and I don't overinterpret. Then I scan systematically: apices, lung fields, costophrenic angles, heart borders, mediastinum, diaphragm, bones, soft tissues, lines and tubes. I do it in that order every time. It takes about ninety seconds on a normal film and three to four minutes if something catches my eye. The trick is training your eye to reject the normal quickly so you can focus on the abnormal. A normal film should be almost boring to read. If you find yourself spending a long time declaring something normal, you're probably missing something. Normal doesn't require effort. Abnormal does. Let the abnormality pull your attention. When everything fits the expected pattern, you're done. I keep a mental checklist of the common misses: the apical pneumothorax that hides in the first two centimeters above the clavicle, the retrocardiac opacity that only shows on the lateral, the small subpulmonic effusion that mimics an elevated hemidiaphragm, and the free air under the diaphragm that looks like gastric bubble on the wrong side. These four items account for roughly half the serious misses I've encountered in practice. Knowing them keeps you honest.
If you want a reliable reference, the Radiopaedia chest X-ray articles are thorough and updated regularly. The RadPrimer module on chest imaging is useful for building the systematic approach without getting lost in rare conditions. For quick daily use, I refer to the CHEST blog and the Radiology Assistant website when I need a refresher on a specific finding. Those resources are practical rather than exhaustive, which is exactly what you need when you're working through a queue of films. Learning to read a chest X-ray well is less about knowing every disease and more about recognizing the normal pattern fast enough to spot when it breaks. The Normal Radiograph Of Chest isn't a checklist of facts. It's a baseline you build through repetition until it becomes automatic. Once that baseline is solid, abnormalities announce themselves. Until then you're just guessing and that's a dangerous game with patient outcomes hanging on it.