Why Memorizing Ranges Gets You In Trouble
The first thing I learned early on was that quoting numbers without context is dangerous. A heart rate of 110 in a six-month-old is normal. The same number in a seventy-year-old man with chest pain means something entirely different. The problem is that most reference materials present normal vital signs as fixed brackets, and that encourages people to treat them like cutoffs rather than starting points. I went through exactly this myself during my first year on call. A sixty-eight-year-old woman came in with what looked like a urinary tract infection. Her heart rate was 92, blood pressure 128 over 76, respiratory rate 18. Everything fell inside standard adult ranges. She sat there looking perfectly fine. Then she started sweating and her mentation changed slightly. I called it early sepsis before I had any real proof, and a attending who had been doing this for thirty years told me I was jumping the gun. Two hours later, her lactate came back at 4.2. My gut had been right even though the numbers looked normal. That's the thing about vital signs across all ages: the numbers are reference points, not verdicts. The real skill is knowing when a reading inside the normal range is actually a red flag.
What Normal Vital Signs For All Ages Actually Means
The concept is straightforward on paper but messy in practice. Normal ranges shift dramatically from birth through old age, and the shifts aren't linear. A baby's heart rate is nearly double an adult's. Respiratory rate drops steeply in the first year and then flattens out. Blood pressure climbs steadily with age, which is why a 110 over 70 might be perfectly healthy for a ten-year-old but concerning for someone in their seventies. The most useful framework I've found breaks things into three life stages: pediatric, adult, and geriatric. Within each stage there are sub-ranges that matter. Let me walk through the actual numbers and then explain where people usually go wrong.
The Numbers By Age Group
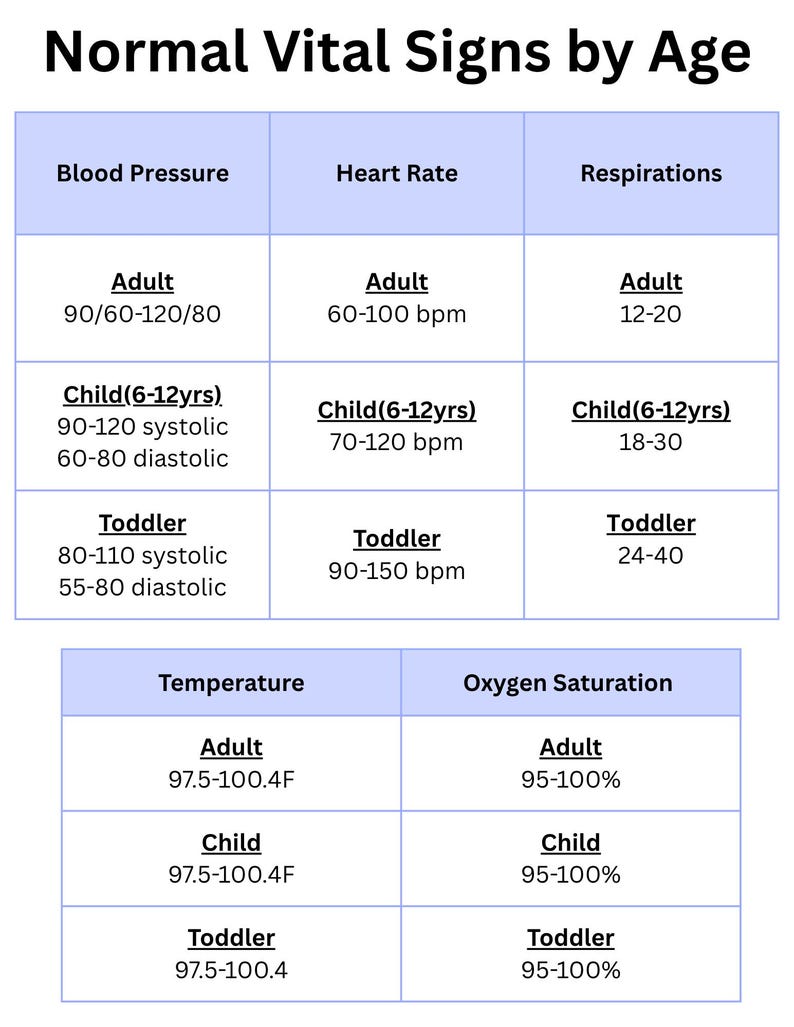
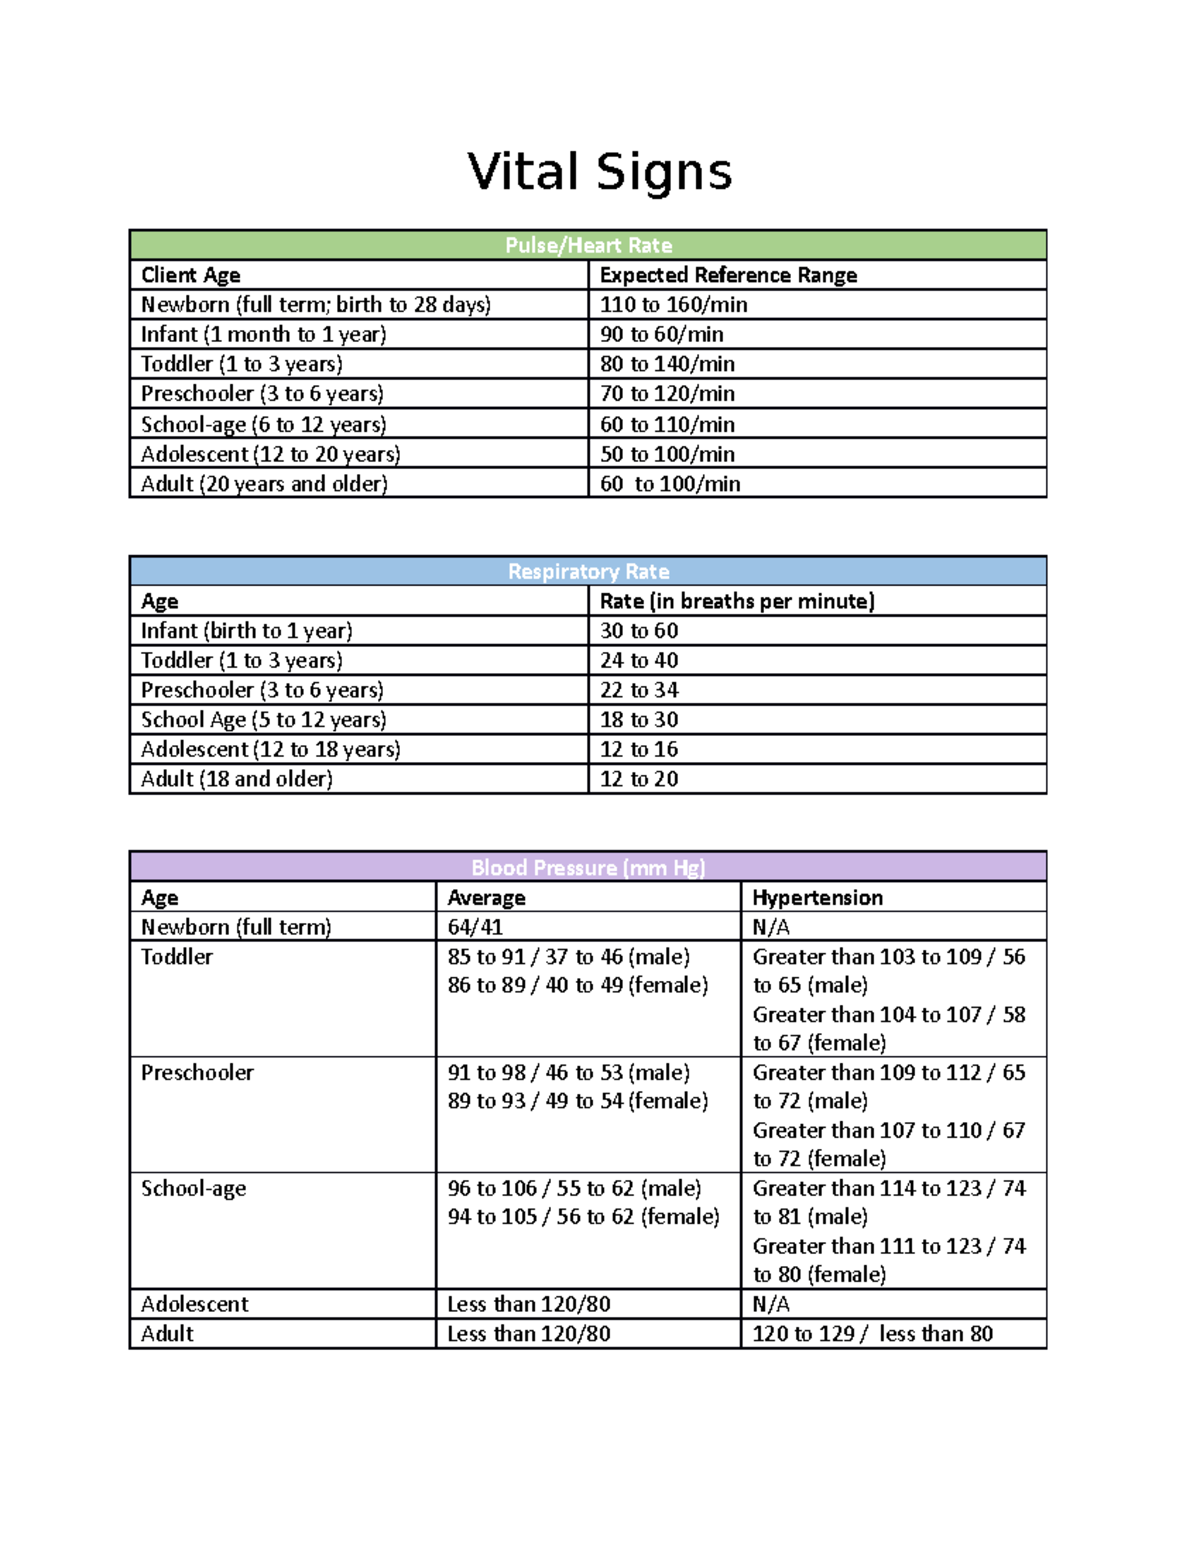
Heart rate is the biggest source of confusion, mostly because people treat adult ranges as universal. Here is what I actually use at the bedside: Temperature is another area where people miss nuances. The standard 98.6 Fahrenheit is an average, not a rule. Core body temperature runs lower in the evening, lower in older adults, and lower in bedbound patients. I once discharged an elderly man with a temperature of 99.1 because I was fixated on the textbook threshold of 100.4. He came back three days later with a hip fracture and pneumonia. His baseline temperature had always been around 97.8. A 1.3-degree rise was significant for him even though it was below the fever cutoff everyone memorizes. The biggest practical issue I run into is applying pediatric vital sign charts to adults and vice versa. It sounds obvious but it happens constantly. A heart rate of 105 in a healthy forty-year-old is technically sinus tachycardia but often just dehydration or anxiety. The same heart rate in a three-year-old is completely unremarkable. I keep a small card in my pocket with the pediatric ranges because I refuse to trust my memory for numbers under five years old. The stakes are higher with kids anyway.
Get the Full Details

Blood pressure interpretation is where most mistakes occur outside the ICU. The commonly cited formula for minimum systolic pressure in children over one year is 70 plus two times the age in years. So a four-year-old should have a systolic of at least 78. A twelve-year-old should be at least 94. Below those numbers, you start thinking about shock even if the child looks awake and responsive. Most clinicians underestimate hypotension in kids because they're applying adult thresholds. Respiratory rate is underrated and routinely ignored. It is one of the earliest indicators of deterioration in both adults and children. A respiratory rate of 24 in a trauma patient screaming in pain is different from a respiratory rate of 24 in a patient who is suddenly quiet and obtunded. Context matters more than the number itself. I check respiratory rate at every vitals check now, and I do not consider a full set complete without it. Too many monitors still omit it or default it to blank.
How I Actually Use These Ranges In Practice
I never look at a single vital sign in isolation. The whole point of tracking normal vital signs for all ages is to spot trends, not to check boxes. When I see a patient, I record the numbers and immediately ask myself whether they make sense for that person's age, baseline health, and current situation. If the answer is unclear, I repeat the measurement after five minutes and document the change. Trend data beats a single reading every time. For pediatric patients, I rely on the Pediatric Assessment Triangle before I even touch the monitor. Appearance, work of breathing, and circulation to the skin will tell me more in thirty seconds than a heart rate number. A child with a heart rate of 140 who is playing with a toy is not in distress. A child with a heart rate of 110 who is limp and pale is. The numbers alone would suggest the opposite, and that inversion is exactly how missed diagnoses happen. In geriatric patients, I adjust my expectations downward for many parameters. Blood pressure is often higher due to arterial stiffness. Heart rate may be lower from medications. Respiratory rate can be blunted by chronic lung disease. The trick is establishing what normal looks like for that individual patient. I ask about their baseline readings if they come in with a caregiver or family member present. If I cannot establish a baseline, I treat any deviation from standard ranges with more suspicion than I would in a younger patient.
A Practical Edge Case That Changed My Approach
Early in my career I treated a seventy-two-year-old man who presented with abdominal pain. His vitals were heart rate 88, blood pressure 132 over 78, respiratory rate 16, temperature 98.9. All normal by standard charts. I released him with a diagnosis of gastroenteritis and sent him home. He returned the next morning with a ruptured abdominal aortic aneurysm. His blood pressure had dropped from 132 systolic to 88 between visits, but that drop was masked because his baseline was chronically hypertensive around 160 over 90. He was in shock the entire time he was in my ED, and the standard vital sign ranges completely hid it from me. That case forced me to start checking for relative hypotension instead of absolute hypotension. Now I look at systolic blood pressure trends and compare them to known baselines whenever possible. A drop of 40 points in systolic pressure is clinically significant regardless of whether the final number falls inside a normal range. I flag this on every geriatric admission now, and I have stopped treating isolated normal readings as reassurance. It is a habit that took me three years to build and several near-misses to cement.

Limitations You Need To Accept
No set of vital sign ranges covers every situation. Athletes routinely have resting heart rates in the 40s and are completely healthy. Pregnant women run warmer with elevated heart rates and respiratory rates. Patients on beta-blockers will not mount a tachycardic response to hemorrhage or infection, which means their heart rate is an unreliable indicator of stress. Burn patients, septic patients, and those with autonomic dysfunction all behave outside standard expectations. The ranges are a screening tool, not a diagnostic tool. That is their purpose and their limitation. When the numbers fall outside the range, they trigger a deeper look. When the numbers fall inside the range but the clinical picture does not match, you still need to dig deeper. I have found that the patients who cause the most trouble are the ones who look fine but feel wrong, and whose vital signs refuse to betray the problem until it is too late. If you are studying this for an exam, memorize the ranges and understand the age adjustments. If you are working clinically, memorize the ranges and learn when to ignore them. Both skills are necessary. The reference material gets you through the test. The experience gets you through the shift.