What Actually Happens When You Inject Nause Fillers
Nose filler injection isn't magic. It's basic anatomical navigation with some very clear danger zones. I've done thousands of these and the ones that go wrong usually come down to one thing: not respecting what's underneath the skin. The nose has three main layers you're working through. The skin and subcutaneous fat on top, then the dense fibrous septum, then the underlying cartilage and bone structure. Between those layers sits a network of blood vessels that runs more or less predictably. If you hit one of them, you're dealing with ischemia or necrosis. That's not theoretical. I had a patient two years ago who came in after a practitioner injected into the dorsal artery just because they were rushing. She got a small patch of skin necrosis on the bridge. It healed, but left a visible depression I had to work around with a different product later. Took me six months to fully correct it.
Nose Anatomy For Filler Injection
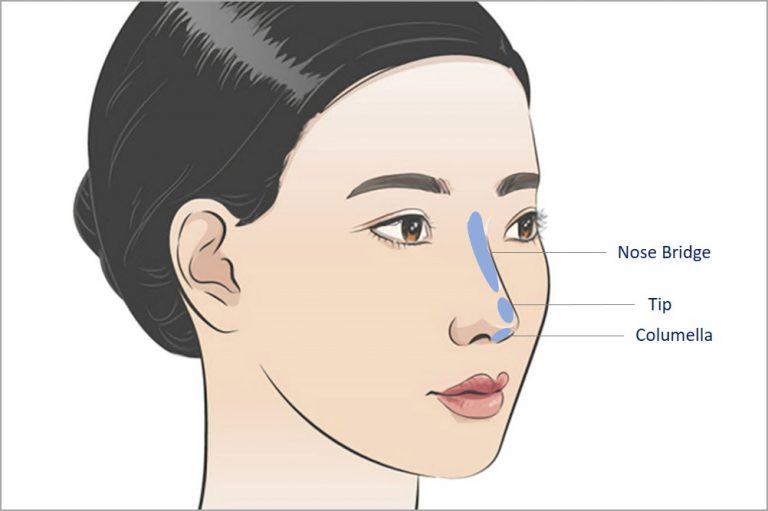
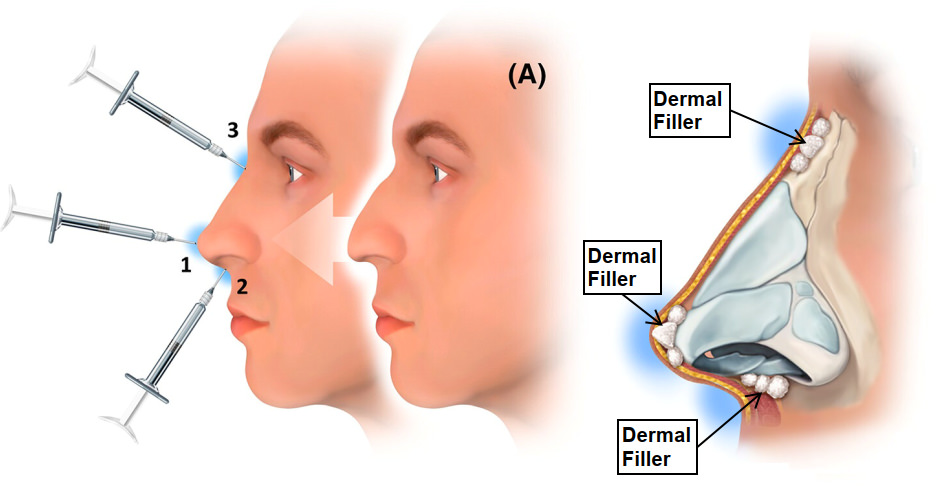
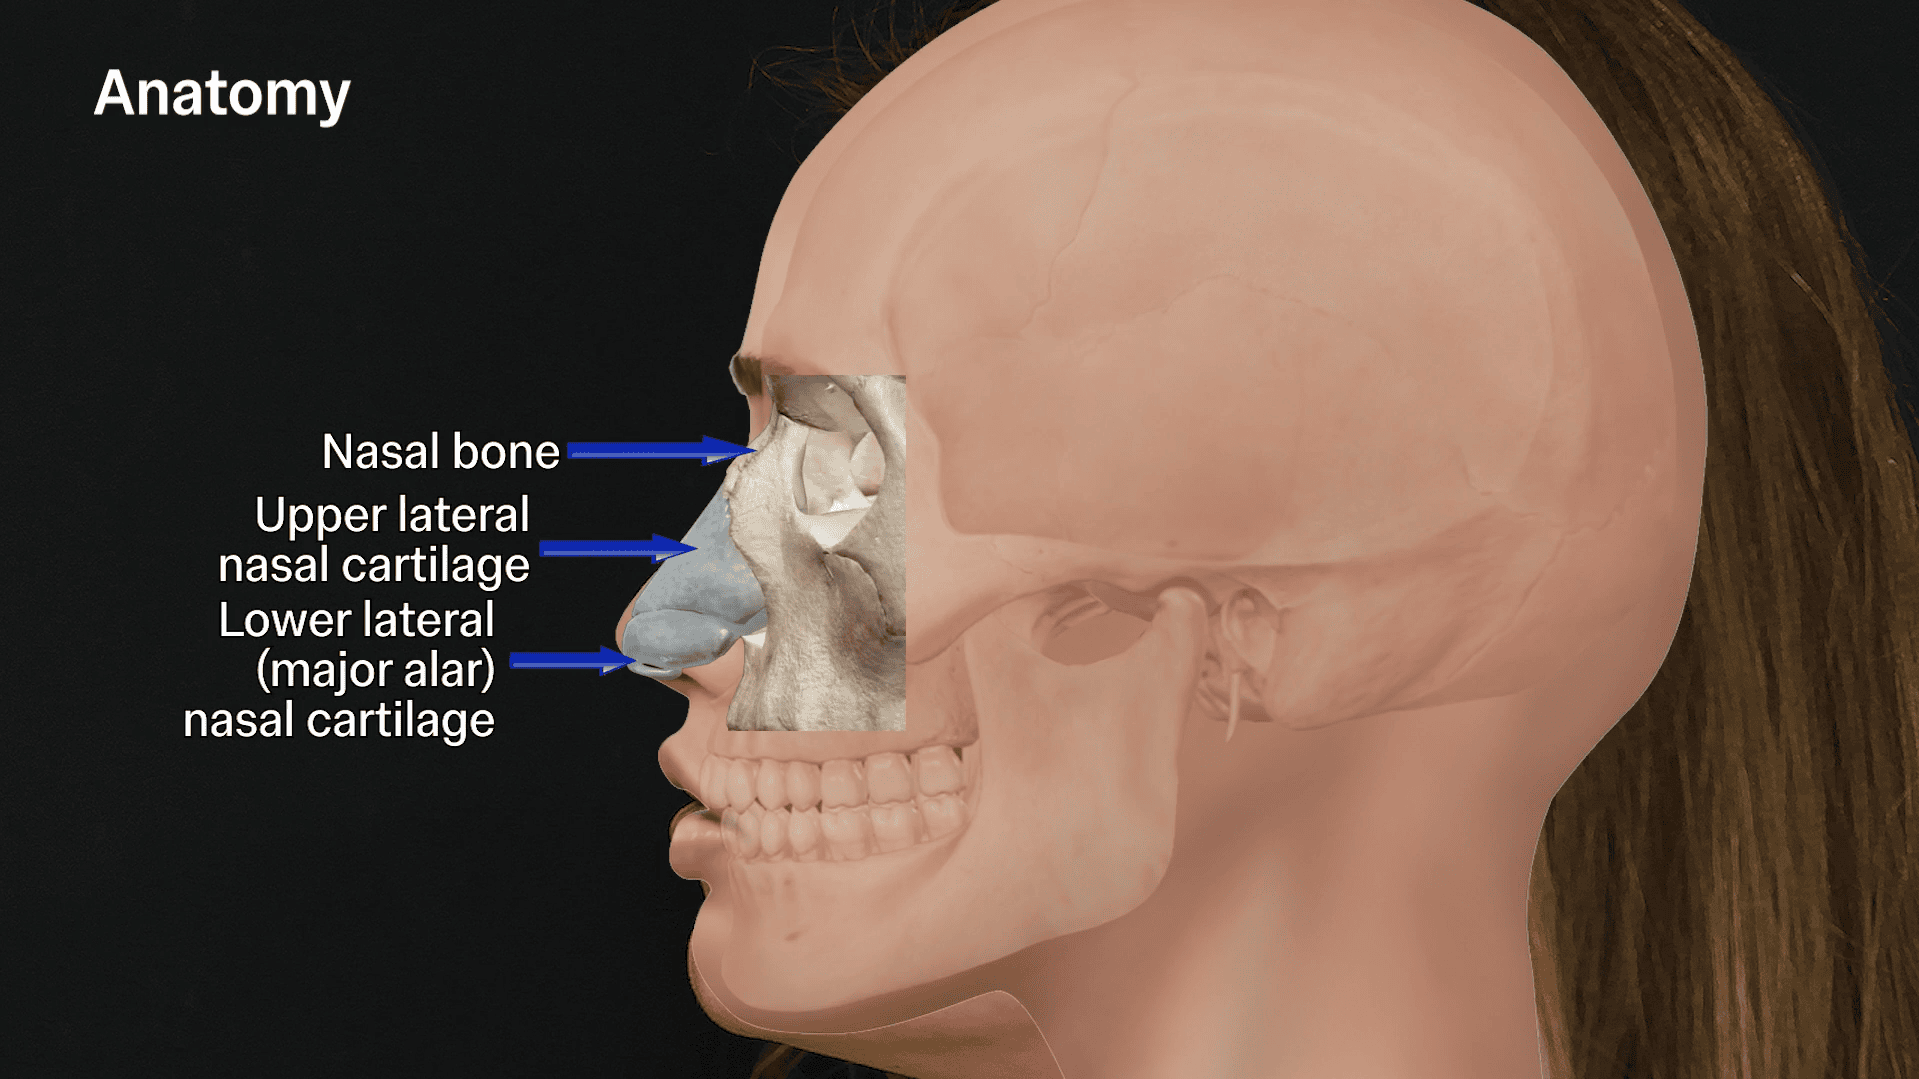
There's really only one plane that matters for most nasal fillers: the supraperiosteal plane, right on top of the bone and cartilage. That's where you want to be. Anything more superficial carries significantly higher risk. The infraorbital artery branches near the nasal root and runs down alongside the nose. The angular artery sits at the medial canthus. These are the real hazards. They don't move much, but they do vary slightly between people, which means you can't rely solely on surface landmarks. Here's something beginners always miss: the dorsum isn't a flat surface. It has a natural width variation. The upper third is bone, the lower two thirds is cartilage, and there's a transition zone right around the middle that feels different under the needle. If you're injecting through that transition zone without adjusting your angle, you'll create a subtle bump most people can't explain but everyone can see. I usually switch from a 27-gauge to a 30-gauge microcannula once I pass the bony dorsum and enter the cartilaginous area. It gives me more control and less trauma. The tip of the nose is another common mistake area. Practitioners tend to push too much filler there thinking it defines the shape. It doesn't. The tip has very thin skin and limited space. More than 0.1ml in the tip region usually creates a bulbous appearance no matter how skilled you are. I rarely use more than 0.05ml per side in the tip, and I almost never inject the very apex directly. Instead, I place small amounts along the alar rims and the supratip break area. That creates the illusion of tip projection without adding bulk where it shows up worst.
There's also the issue of product choice. Hyaluronic acid fillers are standard here, but not all of them behave the same. More viscous products like Juvéderm Volux or Restylane Lyft stay in place better on the dorsum. Softer products migrate. I once saw someone use a very soft filler on a thick-skinned patient and within three weeks the product had spread laterally into what looked like widened nostrils. The patient was angry, the nose looked wider, and we spent another session dissolving and repositioning. Don't cheap out on the product. The nose demands something with structural integrity. Dissolution is another factor most people don't think about until it's too late. If you mess up, hyaluronidase reverses it. But the enzyme doesn't discriminate between your fresh injection and the natural hyaluronic acid already in the tissue. I always tell patients to wait at least two weeks before any touch-up and to avoid dissolving within the first month unless there's a vascular emergency. I had a case where a practitioner dissolved too aggressively during a routine follow-up and the patient's own nasal structure lost some support. She ended up looking more deviated than before the original procedure. It was noticeable and difficult to reconstruct. Aspiration before injection still matters. A lot of younger practitioners treat it like a formality. It isn't. I aspirate on every pass. Yes, it adds about thirty seconds to the procedure. Yes, it's annoying. But in forty-plus procedures a year over several years, that thirty seconds has prevented complications. The dorsal nasal artery runs close enough to the surface in the upper third that a negative aspiration is your only warning before you hit it.
Get the Full Details

One thing nobody talks about enough: patient position during and immediately after injection. Most practitioners inject with the patient sitting upright, which is fine for assessment. But the filling dynamics change when they lie back. Blood flow redistributes. The filler settles differently. I typically complete the injection with the patient supine, assess the result sitting up, then have them lie down again for final micro-adjustments. It takes maybe five extra minutes and catches asymmetries you'd otherwise miss. The real limitation with nasal fillers is that they don't fix structural problems. They camouflage them. If someone has a significant septal deviation, filler on the bridge won't make the nose straight. It'll make it look fuller on one side and more crooked overall. Same with wide nasal bones. Filler adds volume, it doesn't reduce width. I turned away a patient last month because she wanted filler to narrow her nasal bridge. That's physically impossible with any injectable. We discussed surgical options instead. She went elsewhere and came back three weeks later with lateral widening she didn't expect. Not my call, but worth noting that the anatomy of the nose doesn't bend to what filler can accomplish. Learning proper nose anatomy for filler injection takes time. Books help. Ultrasound guidance helps more. I started using high-frequency ultrasound regularly about three years ago and it changed how I approach the procedure. You can see the vessels in real time now. It's not mandatory, but if you're doing this frequently, it's worth considering. The learning curve is steep and the equipment is expensive, but the safety margin is genuinely better.