Getting Through Drug Calculations Without Losing Your Mind
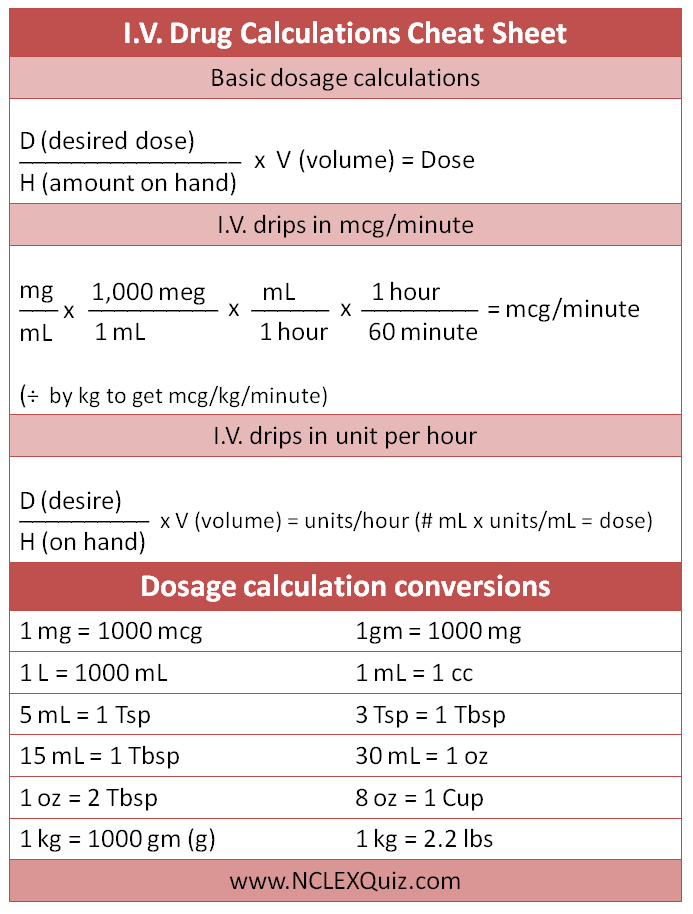
Drug calculations are one of those things every nursing student dreads until they realize the actual math is simpler than the anxiety around it. The problem is rarely the arithmetic. It is the pressure, the unfamiliar formats, and the fact that you are being asked to do it while your brain is still processing the fact that this is a real patient. When I first started clinicals, I would freeze at the Dosage Calculations Made Easy worksheets we were given because they presented everything as a wall of text. My workaround was to stop reading the paragraph and just extract three numbers: the order, the supply, and the question. Once I had those, everything else is just unit conversion. The most common formula you will use is the dosage formula: D over H times Q. D is the desired dose the doctor ordered, H is what the medication comes in, and Q is the quantity or volume that the medication is supplied in. Say a doctor orders 500 mg of amoxicillin and the vial says 250 mg per 5 mL. You divide 500 by 250, which gives you 2, then multiply by 5 mL, and the answer is 10 mL. That is it. The worksheet gets more complex when you add in weight-based dosing or pediatric calculations, but the skeleton stays the same.
I ran into a case recently where the order was written in grains and the supply was in milligrams. Grain is an old apothecary unit and it does not show up in most modern supplies, but it still appears on exams and occasionally in real practice. One grain equals 60 milligrams, sometimes 65 depending on the reference you use. My approach was to convert the ordered dose to milligrams first, then run the standard formula. Converting units before setting up the equation prevents you from mixing measurement systems, which is where most mistakes happen.
The Setup You Should Use Before You Start Any Problem
Write out the known values separately before you do any math. Create three lines on your scratch paper: order, supply, and question. This takes about ten seconds and it stops you from accidentally plugging the wrong number into the formula. I have seen students lose points because they read 250 mg as the ordered dose when it was actually the supply strength. Writing it down forces you to slow down enough to catch that mismatch. Pediatric dosing adds weight to the mix, and that is where the real mistakes happen. The formula stays the same, but now the desired dose is calculated from the patient weight and a per-kilogram rate. The order might say 15 mg per kg and the patient weighs 22 kg, so you calculate 330 mg as the total dose first, then run D over H times Q with that number. The trap is rounding too early. If you round the weight conversion or the per-kg dose before finishing the calculation, your final answer can be off by enough to matter clinically. Keep extra decimal places through the intermediate steps and round only at the end, and round to a practical measure for the final step, like the nearest tenth or hundredth depending on the route.
Get the Full Details
IV Flow Rates Are a Different Beast
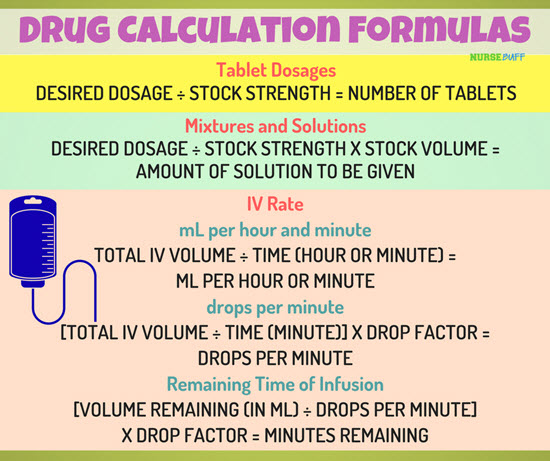
Drip rates use the same logic but with different units. The formula is volume divided by time, then multiplied by the drop factor if you are working with gravity infusion. Volume in milliliters, time in minutes, drop factor in drops per milliliter. If the order is 1000 mL over 8 hours and the tubing is 15 drops per mL, you divide 1000 by 480 minutes to get the flow in minutes, then multiply by 15. The result is about 31 drops per minute. The catch here is that not all IV sets are the same. Macro drip tubing runs at 10, 12, or 15 gtt per mL. Micro drip runs at 60 gtt per mL. Using the wrong drop factor is a common exam mistake and a rare but serious real-world risk. Always check the tubing packaging before you calculate.
What the Methods Actually Get Wrong
Most study guides and apps push the ratio-proportion method as the gold standard, and it works fine for basic problems. But when you are dealing with complex reconstitution steps or multi-step conversions, dimensional analysis tends to be more reliable. You set up a chain of fractions so that units cancel out until you are left with what you need. It takes longer to learn, but it leaves less room for setup errors under pressure. Another limitation is that no single method accounts for clinical judgment. The math might give you 4.7 mL, but if the syringe only measures in 0.1 mL increments and the medication is tightly dosed, you need to know when to round and when to flag it. Calculations made easy tutorials often skip that part entirely, and that gap is where confident students make mistakes.
A Practical Routine That Actually Cuts Time
When I was studying for my licensing exam, I stopped doing random practice sets and started timing myself. The average worksheet took me about 45 minutes unprocticed because I kept second-guessing my setup. Once I locked in the three-line format, my time dropped to roughly 12 to 15 minutes per set, and my accuracy improved because I was no longer re-reading the same paragraph three times to find the right number. Use a standardized format for every problem. Three lines, plug into the formula, convert units first if needed, calculate, check that the answer makes clinical sense, then write it down. If the answer comes out to 250 mL for a single intramuscular injection, something is wrong and you need to backtrack. That sanity check alone has saved me from repeating mistakes during practice tests.
Where the Approach Breaks Down
These methods assume you are working with standard adult doses and straightforward orders. They become less useful when you encounter high-alert medications with double-check requirements, compounding calculations for pharmacy-prepared doses, or electronic infusion pump programming that uses different rounding conventions. In those scenarios, the math is only half the problem. The other half is protocol and verification, which no worksheet can teach you. If you are looking for structured practice, searching for Nurse Drug Calculations Made Easy will pull up a lot of free worksheets and PDF collections. Look for ones that include weight-based problems, IV drip calculations, and unit conversions together. Avoid materials that only drill one type, because the exam and clinical practice mix them.
The Bottom Line Without the Wrap-Up
The work is straightforward once you separate the numbers from the text and stick to one consistent setup. The mistakes come from rushing the reading, mixing units, or ignoring the clinical reasonableness check. I have seen students who could crunch numbers fast still lose points because they did not write out the units at each step. Dimensional analysis solves that problem better than pure ratio-proportion for anything beyond the simplest case. Practice with mixed sets under timed conditions until the three-line format becomes automatic. Then move on to checking your answers against clinical reality, not just arithmetic correctness. That second layer is what actually keeps patients safe.