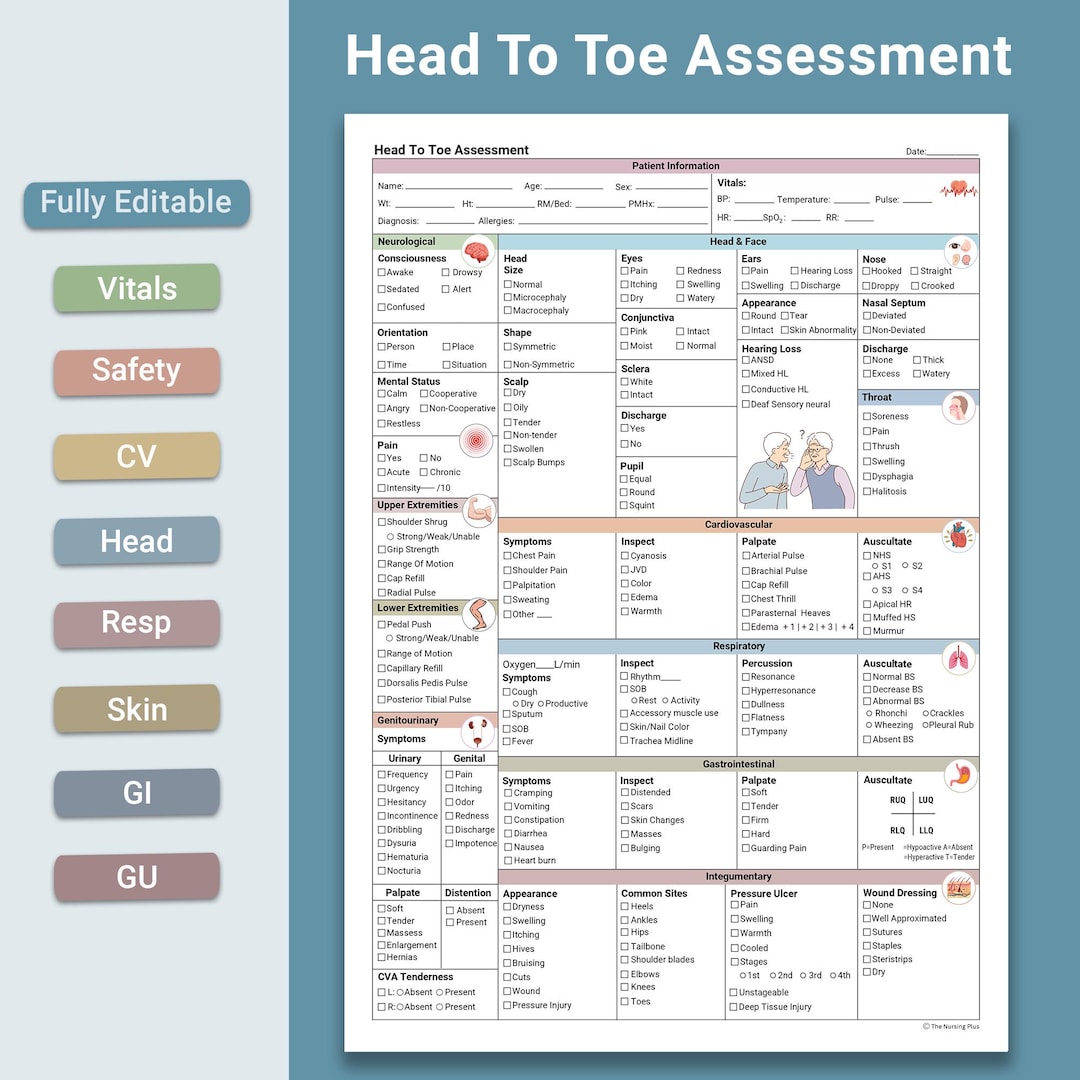
The Head To Toe Assessment is just documentation discipline
Most nursing students and new grads approach the head to toe assessment like they are filling out a form for the chart. They hit the boxes and move on. The problem is the assessment is only as good as what you actually observe, not what you write down. I have watched competent nurses document a normal neuro screen on a patient who was actively seizing five minutes later because they went through the motions without really looking. Here is the practical flow. Start with the patient's general appearance before you touch them. Posture, skin color, level of distress, speech patterns. Then move systematically from head down to feet. Inspect, palpate, auscultate, percuss where applicable. This is not a checklist. It is a clinical interview with your hands and ears.
Nurse Head To Toe Assessment sequence
Head and face: Pupils, extraocular movements, mucous membranes, fontanelle if infant, cranial nerves V through XII if the situation calls for it. Watch the face while you talk to the patient. Facial asymmetry during speech is an early sign of stroke that static inspection misses. Neck: Jugular venous pressure, carotid pulses, thyroid, lymph nodes, tracheal position. JVP is assessed at 30 to 45 degrees with the patient relaxed. I once charted a patient as euvoledmic because I only glanced at the neck without rolling them to the correct angle. The distended JVP was right there. I had missed a clear sign of right heart failure because I did not angle the bed properly. Chest and lungs: Inspection of symmetry, palpation for tenderness and crepitus, percussion, then auscultation of all eight lung fields. Do not skip the posterior bases. Pneumonia loves the bases. Remember that each lung has different lobe anatomy on the right versus the left, so your anterior and posterior listening points map to specific lobes.
Heart: Four areas. S1 and S2, rate, rhythm, murmurs, gallops. If you hear an S3, think volume overload in an older adult or peripartum cardiomyopathy in a postpartum patient. If you hear an S4, think stiff ventricle and hypertension. Abdomen: Inspection, auscultation before percussion and palpation. Bowel sounds in all four quadrants. Liver edge, spleen, any masses. Percussion for tympany versus dullness. Palpate light first, then deep. Do not press hard on a patient with rebound tenderness or you will make them guard and ruin the rest of the exam. Extremities: Pulses, capillary refill, edema, strength, sensation, joint range of motion. Compare sides. A 1+ pitting edema on one leg and 3+ on the other is a DVT until proven otherwise, not just fluid overload.
Get the Full Details

Neurological: Level of consciousness using AVPU or GCS, orientation, cranial nerves, motor strength, sensation, reflexes, gait if safe. The mini-mental state is not part of a standard head to toe. Stick to focused neuro screening. Skin and integument: Color, temperature, moisture, turgor, lesions, pressure injury risk areas. Turn the patient. Sacrum, heels, greater trochanters. I had a wound care consult for a stage 2 on the left heel that I had missed for three days because I never rolled that patient onto their left side during assessments. That one costs sleep. Time expectation: a full assessment on a stable patient runs about 20 to 40 minutes depending on complexity. A focused assessment on a deteriorating patient might take 10 minutes and should still follow the same sequence. Do not compress the exam just because you are behind. You will miss something.
What beginners consistently do wrong
Auscultation order on the abdomen. You must listen before you palpate or percuss. Manipulation changes bowel sounds. If you palpate first, you are listening to altered reality. Documentation that contradicts the exam. Writing "lungs clear to auscultation" when you only listened to two anterior fields per lung is not defensible. Document what you actually assessed. If you did not reach the posterior bases due to patient agitation, note that limitation. Charts are legal documents. They are also liability traps when they look optimistic instead of accurate. Ignooring the patient's own words. If the patient says "this spot hurts" before you press it, note the location and character. Patient complaint often guides the exam better than algorithmic scanning.
Rushing the cardiac exam. A rush through heart sounds means you miss murmurs, split S2, and irregular rhythms. If the rhythm is irregular, listen for a full 60 seconds. One minute is the standard for apical pulse. Do not count 15 seconds and multiply by four on an irregular rhythm. That is how you miss atrial fibrillation with a ventricular rate of 110.
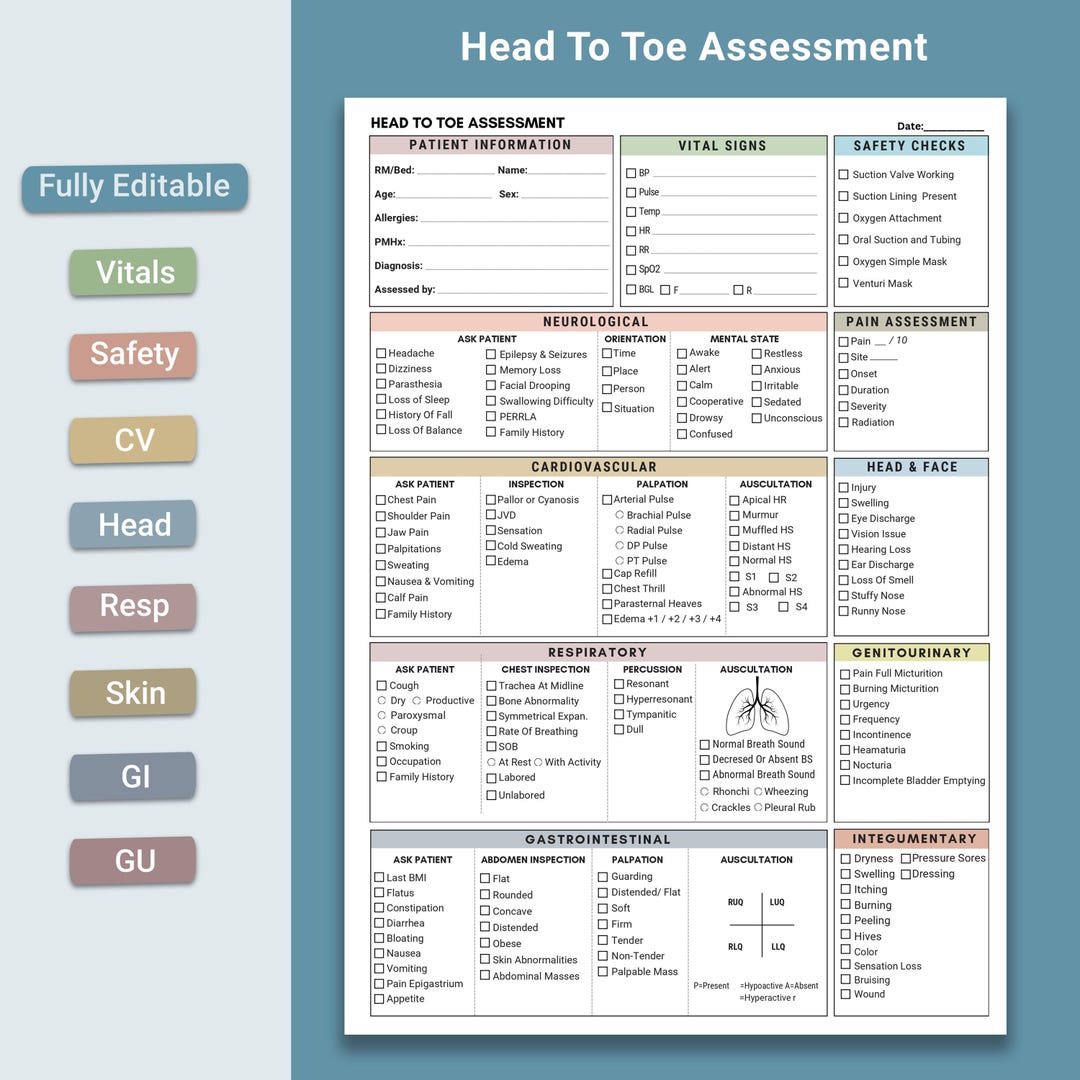
When the head to toe assessment fails you
The biggest blind spot in a standard head to toe is serial change. A single snapshot is useless if you do not know the baseline. I had a post-op spinal patient whose neurological exam was documented as intact at 0800. At 1100, the exam looked "normal" on paper because I had no prior detailed notes to compare. The patient actually had a epidural hematoma developing. The difference was subtle: decreased dorsiflexion strength on one side, slightly blunted sensation to pinprick at L5. If the 0800 assessment had included graded strength numbers and specific sensory levels, I would have caught it immediately. The assessment itself was not wrong. The documentation was a generic placeholder. Another failure mode: obese patients. Pulse palpation becomes unreliable. Lung sounds are muffled. Abdominal palpation is shallow. In these cases, you rely more on percussion, observation, and early diagnostic testing. Do not force a manual exam that cannot yield reliable data. Order the CT or the ultrasound. The assessment is a screening tool, not a diagnostic endpoint.
A useful edge-case workaround
When assessing a patient with an indwelling urinary catheter and you need accurate output tracking alongside the exam, do not wait until the end of the head to toe to check the bag. Check it immediately after positioning the patient. Moving the patient disturbs the tubing and can cause backflow or kinking. I learned this the hard way after missing a drop in urine output during a shift change because the tubing was pinched under the patient's hip and I did not realize it until the bladder scan showed 600 ml retention. The head to toe assessment should include a quick line and tube check as part of the exposure step, not as an afterthought. Use a penlight with a red filter for fundoscopy when you need to check for papilledema. The red light penetrates the pupil better in low light and makes the optic disc easier to visualize than white light alone. This is not standard nursing school teaching in most programs, but it works. For peripheral pulses, use the pads of your index and middle fingers, not the thumb. The thumb has its own pulse and you will confuse it with the patient's.
When assessing edema, grade it in mm of depth. 1+ is 2 mm, 2+ is 4 mm, 3+ is 6 mm, 4+ is 8 mm. Writing "moderate edema" is vague. Writing "3+ pitting edema, 6 mm depth, bilateral lower extremities" tells the next nurse exactly what you found. Bowel sounds vary by quadrant and by time. Normal is 5 to 30 sounds per minute. Absence for 5 minutes in all quadrants before calling it absent is the threshold. Do not call hypoactive after 30 seconds of silence. Listen longer. Clinical context matters more than a stopwatch number. The head to toe assessment is not a performance. It is a data gathering exercise. The quality of your data determines whether you catch deterioration early or respond to it late. Document specifically, examine systematically, and do not let pace override thoroughness.



