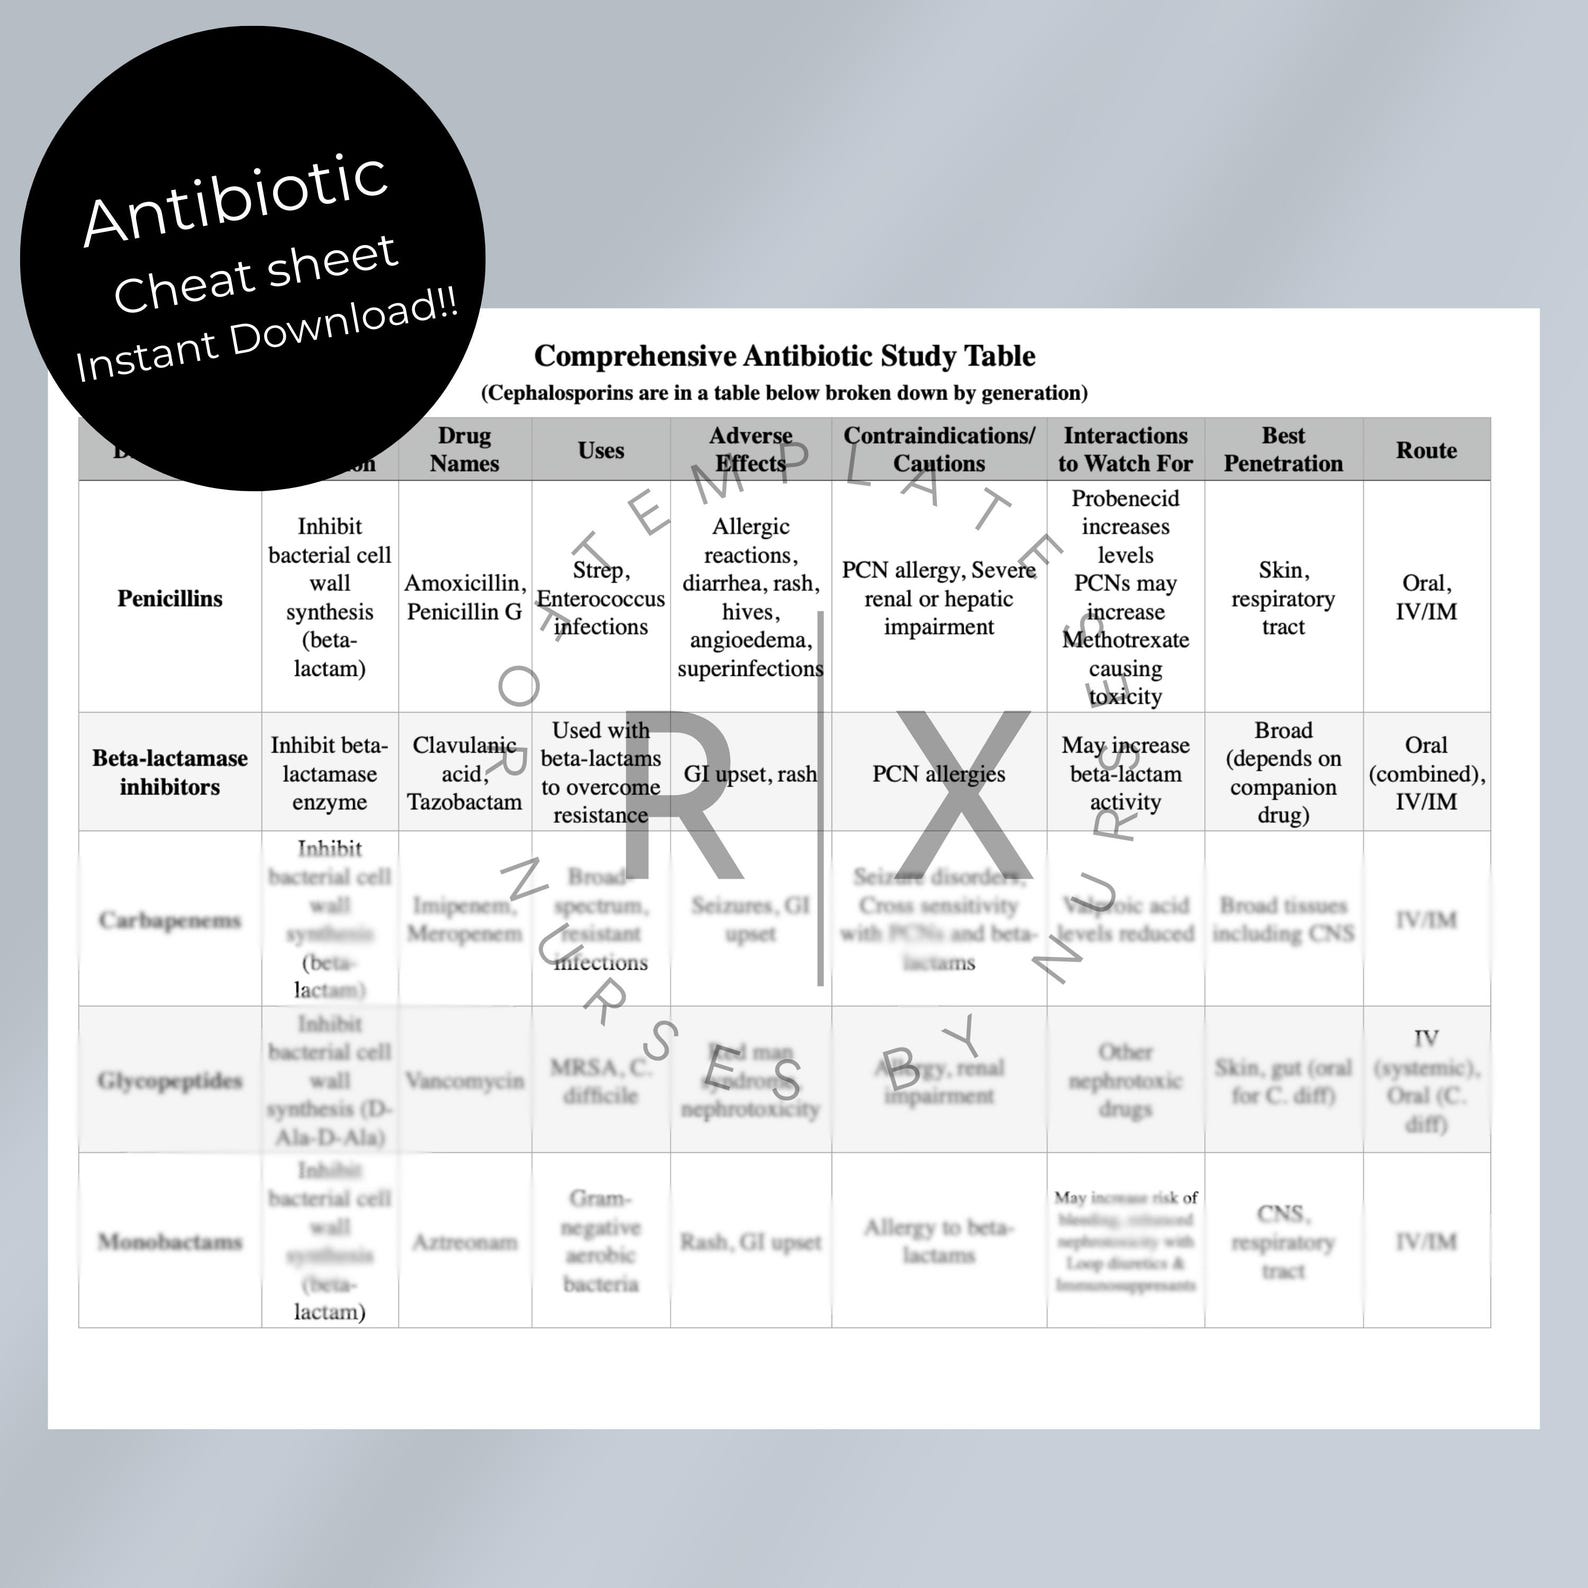
Quick Reference for Common Antibiotics
The Nurse Practitioner Antibiotic Cheat Sheet is something most NPs either build themselves over a few years or find tucked away in some corner of their EMR. Here is what I actually use daily. It covers the drugs I prescribe 90 percent of the time and skips the obscure stuff that shows up on ID consults. Amoxicillin-clavulanate 875/125 mg twice daily works for most sinus and soft tissue infections, but the extended-release tablet should only be taken with food. If you send a patient home with the regular formulation on an empty stomach, about a third will call you back with diarrhea. It happens. Amoxicillin alone at 500 mg three times daily is fine for strep throat. You do not need clavulanate there. Adding it just increases side effects without improving outcomes for group A streptococcus. Doxycycline 100 mg twice daily is your go-to for community-acquired pneumonia in outpatients without comorbidities. Take it upright with water and stay upright for ten minutes after. I had a patient once who thought she could take it at bedtime with a sip of water while lying down and ended up with an esophageal ulcer that required surgical evaluation. She was fine after four days of sucralfate, but it was an ugly few days for both of us.
Nurse Practitioner Antibiotic Cheat Sheet for Common Infections
For urinary tract infections, nitrofurantoin monohydrate/macrocrystals 100 mg twice daily for five days remains first-line in uncomplicated cystitis. The key detail nobody remembers is that you must confirm the creatinine clearance is above 30. Below that, the drug does not concentrate adequately in the urine and you are just exposing the patient to side effects. I stopped checking renal function before prescribing it around 2019 because two patients in a row had poor responses, and the second one ended up with pyelonephritis. Never again. Ciprofloxacin is still prescribed way too often for UTIs by people who think fluoroquinolones are superior. They are not superior for simple cystitis. They carry a black box warning for tendon rupture and aortic aneurysm risk, and they disrupt the gut microbiome far more than most alternatives. Reserve cipro for pyelonephritis when oral beta-lactams are not an option, or for prostatitis where penetration matters. Azithromycin 500 mg on day one followed by 250 mg on days two through five works for strep and some respiratory infections. The single-daily dosing is convenient and that is exactly why people overprescribe it. For respiratory infections where atypical coverage is needed, azithromycin is reasonable. For strep, penicillin or amoxicillin is better. Strep eradication rates are higher with penicillin V. I used to prescribe azithromycin for strep because it was simpler for compliance, then I saw the ID literature catch up with my own practice and switched back.
Metronidazole 500 mg twice daily for seven days is correct for bacterial vaginosis. The single 2-gram dose does not work as well, but patients prefer it. If they insist on the single dose, tell them the recurrence rate is about 30 percent higher at three months and let them decide. Documentation matters more than your preference here. Cephalexin 500 mg four times daily is fine for cellulitis when MRSA is not suspected. The four-times-daily dosing is the reason compliance drops. Switching to a once-daily option like trimethoprim-sulfamethoxazole if MRSA is a concern, or using doxycycline, often results in fewer follow-up calls. I used cephalexin for years until I noticed my return visit rate for unresolved cellulitis was uncomfortably high, and then I started checking MRSA prevalence in my zip code and adjusting my empiric choices accordingly.
Get the Full Details

When the Cheat Sheet Is Not Enough
There are situations where a quick reference fails you. Renal dosing is the most common one. Ceftriaxone does not require adjustment for renal impairment, which makes it useful in patients with unknown or fluctuating kidney function. Most other antibiotics do. I once prescribed levofloxacin without adjusting for a patient whose creatinine had crept up to 2.1 over six months. He came back two days later with seizures. The drug accumulates and lowers the seizure threshold. I felt terrible about that one. Pregnancy is another area where cheat sheets oversimplify. Penicillins and cephalosporins are generally safe. Doxycycline is contraindicated after the first trimester. Fluoroquinolones are category C and should be avoided unless no alternative exists. Clindamycin is a reasonable alternative for gram-positive coverage in the first trimester when beta-lactams cannot be used. I keep a separate pregnancy-safe antibiotic list because the general cheat sheet does not always flag these distinctions clearly enough. Drug interactions are easy to miss. Metronidazole with warfarin spikes the INR. I have seen this twice in eight years. Each time the patient was stable on warfarin for a DVT and I added metronidazole for a dental infection without checking. The INR went from 2.5 to 5.8 in three days. We held warfarin and gave vitamin K. It was entirely preventable.
C. difficile risk is real with clindamycin, fluoroquinolones, and cephalosporins. Amoxicillin-clavulanate carries moderate risk. Tetracyclines and nitrofurantoin carry low risk. When a patient has a history of C. diff, you should avoid the high-risk drugs even if they are otherwise appropriate. Fidaxomicin is an alternative for recurrent C. diff but it is expensive and usually requires prior authorization. You will spend twenty minutes on the phone for a drug the patient may not need if you had just chosen a different antibiotic in the first place.
Building Your Own Reference
The best cheat sheet is the one you actually open. Mine started as a printed laminated card on my desk. It grew into a PDF on my phone. Now it is mostly in my head with quick lookups when I need dosing adjustments or interaction checks. The process of building it taught me more than any textbook. I learned which drugs I use most, which doses work for which populations, and where my knowledge gaps were. Include pediatric dosing if you see children. Include hepatic dosing if you treat patients with liver disease. Include cost tiers because a $4 generic is better than a $40 brand-name drug when the patient cannot fill it. I added allergy cross-reactivity notes after a patient told me she was allergic to penicillin because her grandmother was, and the chart said nothing about the actual reaction type. A good reference also lists equivalent substitutions. Amoxicillin to cephalexin is straightforward. Amoxicillin to azithromycin is not equivalent and should not be listed as such. I have seen cheat sheets do this. It leads to underdosing in real clinical situations.
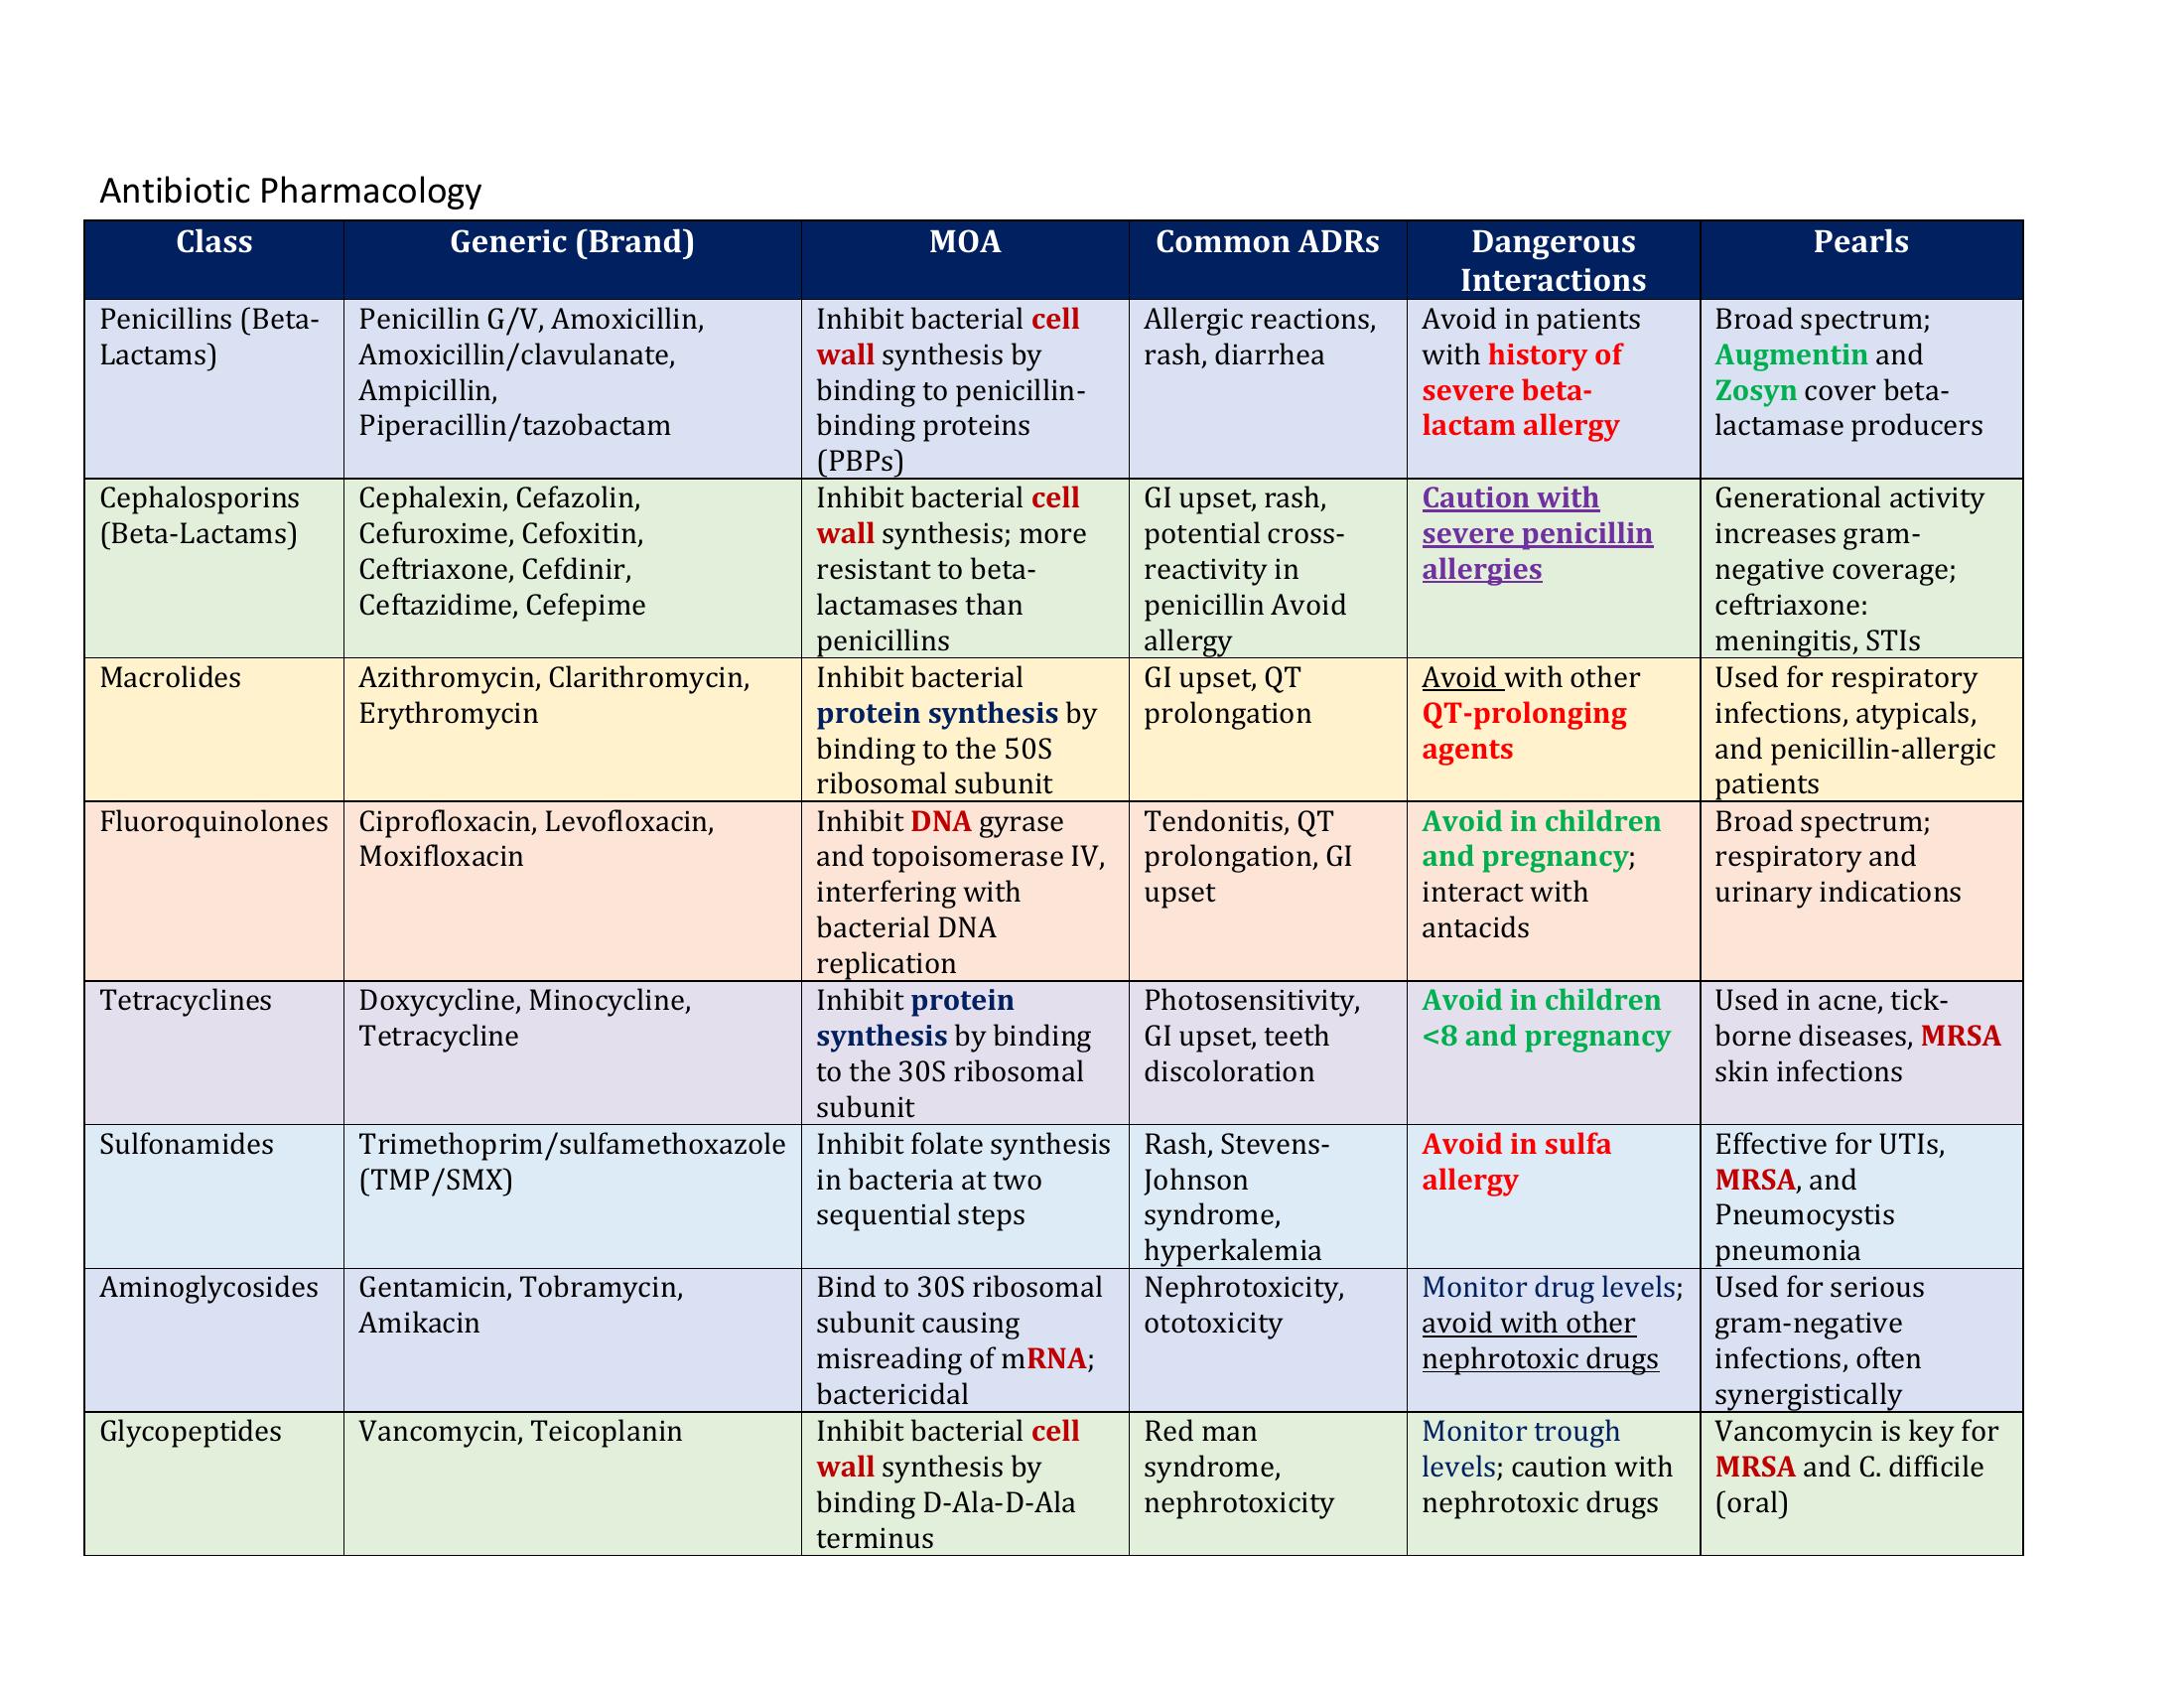
Practical Workflow
Before you prescribe, check three things. Renal function, pregnancy status when applicable, and current medication list for interactions. This takes forty-five seconds and prevents most adverse events. I used to skip the med list check because I trusted my memory. I was wrong. The warfarin-metronidazole incident changed that permanently. When culture results come back, narrow your coverage. Broad-spectrum empiric therapy is acceptable at the start, but continuing it after you know the organism and susceptibilities is poor stewardship and it costs the patient more in side effects and resistance risk. I review cultures every morning before rounds. Twenty minutes a day saves hours of follow-up visits and phone calls over the course of a year. Document the indication, the drug, the dose, the duration, and the renal function at the time of prescribing. If a student or another provider reviews your chart later, they should be able to understand why you made each choice without calling you. I write duration explicitly because I have seen patients stop early and return with rebound infection. Specifying ten days instead of "until resolved" reduces that ambiguity.
This cheat sheet approach works because it is built from repeated use, not from memorization. You will forget things. The reference fills the gap. The more you use it, the less you need it. That is the whole point.