
What a NP Assessment Cheat Sheet Actually Looks Like in Practice
I spent years watching nurse practitioner students and new grads struggle with physical assessments. They knew the theory. The textbooks were thorough. But when a patient walked in with a murmur or an abdominal complaint, they froze. That's where a Nurse Practitioner Assessment Cheat Sheet becomes genuinely useful, not as some magic shortcut, but as a quick reference to keep your process organized when fatigue and stress are working against you. A cheat sheet in this context is a condensed, one- or two-page reference that maps out the key components of a clinical assessment — head-to-toe or system-specific — with the essential questions, maneuvers, and red flags you need to hit. It's not memorization replacement. It's a safety net for when you're managing a full clinic schedule and need to stay consistent across dozens of patients per day.
How to Build Your Own Nurse Practitioner Assessment Cheat Sheet
Start by picking your most common patient population. If you're in family practice, you're seeing everyone from newborns to end-of-life care. That's too broad for a single sheet. Narrow it down. I always tell people to build separate sheets for pediatric, adult, and geriatric assessments, or better yet, by body system. Here's what I did early in my career. I was doing rotational precepting and noticed that my students would skip the cardiac exam when they were behind schedule. They'd move straight to labs and imaging. So I created a small card-sized cheat sheet with the absolute must-do steps for cardiovascular assessment: inspection, palpation of the point of maximal impulse, auscultation sequence from aortic to pulmonic to tricuspid to mitral, and the four classic murmurs you cannot miss — aortic stenosis, mitral regurgitation, atrial septal defect, and mitral valve prolapse. The fix was simple: laminated cards on their clipboards. I saw their compliance with cardiac exams go from maybe thirty percent up to nearly ninety percent within two weeks. That's the value of a well-designed cheat sheet — it's behavioral modification disguised as a reference document. The actual construction process is straightforward:
- Step one: Use a standard assessment framework as your backbone. The head-to-toe model or the system-based review are both fine. Pick one and stick with it. Don't mix frameworks on the same page.
- Step two: For each body system, list the key subjective questions first. These are the screening questions that separate a normal finding from something that needs further workup. For respiratory, that's dyspnea on exertion, orthopnea, paroxysmal nocturnal dyspnea, chronic cough, hemoptysis. You get the idea.
- Step three: Add the objective findings that matter. Not every possible sign. Just the ones you'd actually catch in a primary care timeframe. For a neurological screen, a rapid finger-to-nose test and pronator drift check will catch most significant issues. Don't clutter the sheet with rare exam maneuvers.
- Step four: Include red flags in a separate column or highlighted section. This is the most important part. A cheat sheet without red flags is just a checklist, and checklists don't save you when something serious is hiding in plain sight.
I learned this the hard way during my first independent practice rotation. I was seeing a patient for a routine follow-up on hypertension. The cheat sheet I was using had a blood pressure tracking section but no specific prompt to assess for end-organ damage beyond the numbers. The patient had a headache he'd been ignoring for weeks. I missed it because my sheet didn't have a neurological prompt in the hypertension follow-up workflow. After that, I started cross-referencing my system sheets. Every cardiovascular sheet now has a neurological sub-section that reminds me to ask about headaches, visual changes, and focal deficits. It added three lines to the page but probably prevented more than a dozen missed diagnoses over the next few years. Inspection: Look for visible pulsations, chest wall deformities, use of accessory muscles. Note any scars from prior procedures. Palpation: Locate PMI at the 5th intercostal space, midclavicular line. Assess for heaves, lifts, thrills. Check peripheral pulses bilaterally — rate, rhythm, amplitude. Capillary refill should be under two seconds.
Get the Full Details
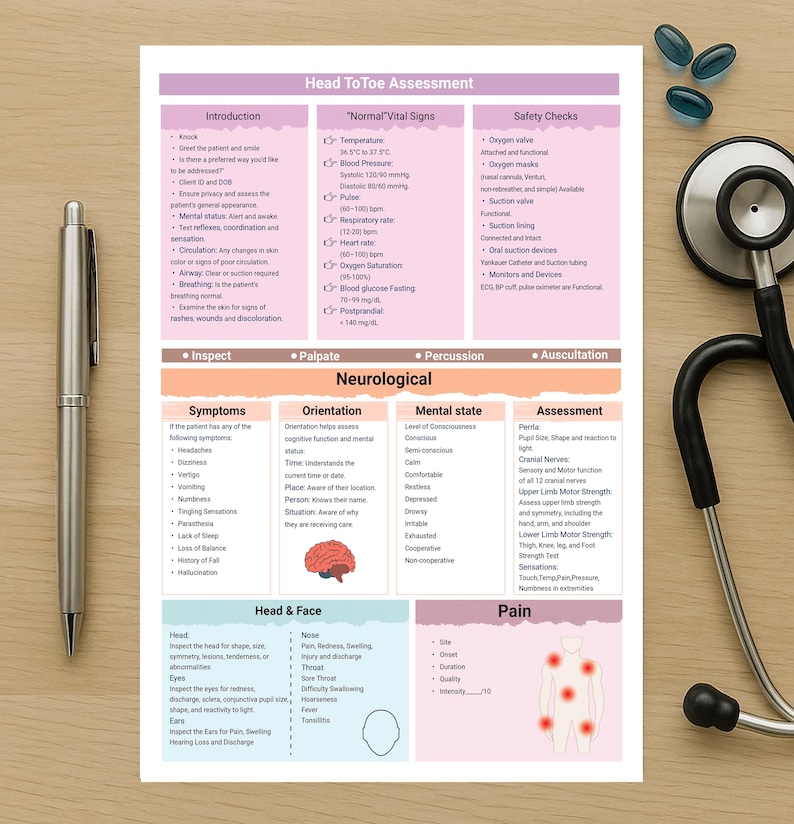
Auscultation: Use the diaphragm and bell. Four classic listening positions: aortic (right 2nd intercostal), pulmonic (left 2nd), tricuspid (left lower sternal border), mitral (5th ICS, MCL). Always listen for at least thirty seconds per area before moving on. Red flags: New murmur in a patient over fifty, systolic murmur with a thrill, grade three or higher, diastolic murmurs, S3 or S4 gallop, jugular venous distension above the clavicle at forty-five degrees, asymmetric peripheral pulses, unexplained peripheral edema. Any of these warrants echocardiography referral or cardiology consultation, not just watchful waiting.
Common Mistakes When Using an Assessment Cheat Sheet
The biggest problem I see is that people treat the cheat sheet as a substitute for clinical reasoning rather than a prompt. You read the item, you check the box, and you move on. That's how you miss the detail that matters. The cheat sheet is a reminder of what to look for, not a confirmation that you've found it. If the sheet says "assess lung sounds" and you hear clear breath sounds, you still need to document that you actually listened. Not just checked a box. Another mistake is making the sheet too detailed. I've seen twenty-page assessment documents that nobody actually uses because they take longer to read than the exam itself. Your cheat sheet should fit on one side of a letter-sized page, preferably two columns. If it doesn't, you're including information you don't need in the moment. There's also the issue of static content. Medical guidelines change. The 2022 USPSTF screening recommendations shifted on several items compared to previous years. If your cheat sheet is three years old and still says "screen all adults for abdominal aortic aneurysm," you're either using outdated guidance or you haven't updated your materials. One of my colleagues printed a vascular assessment sheet in 2018 that listed the American Heart Association's annual AAA screening recommendation without noting the USPSTF grade B cutoff for men aged sixty-five to seventy-five who have ever smoked. He caught the discrepancy himself when reviewing a patient chart, but it took him five minutes of confusion before he realized his reference material was stale.
Nurse Practitioner Assessment Cheat Sheet — Download and Adapt
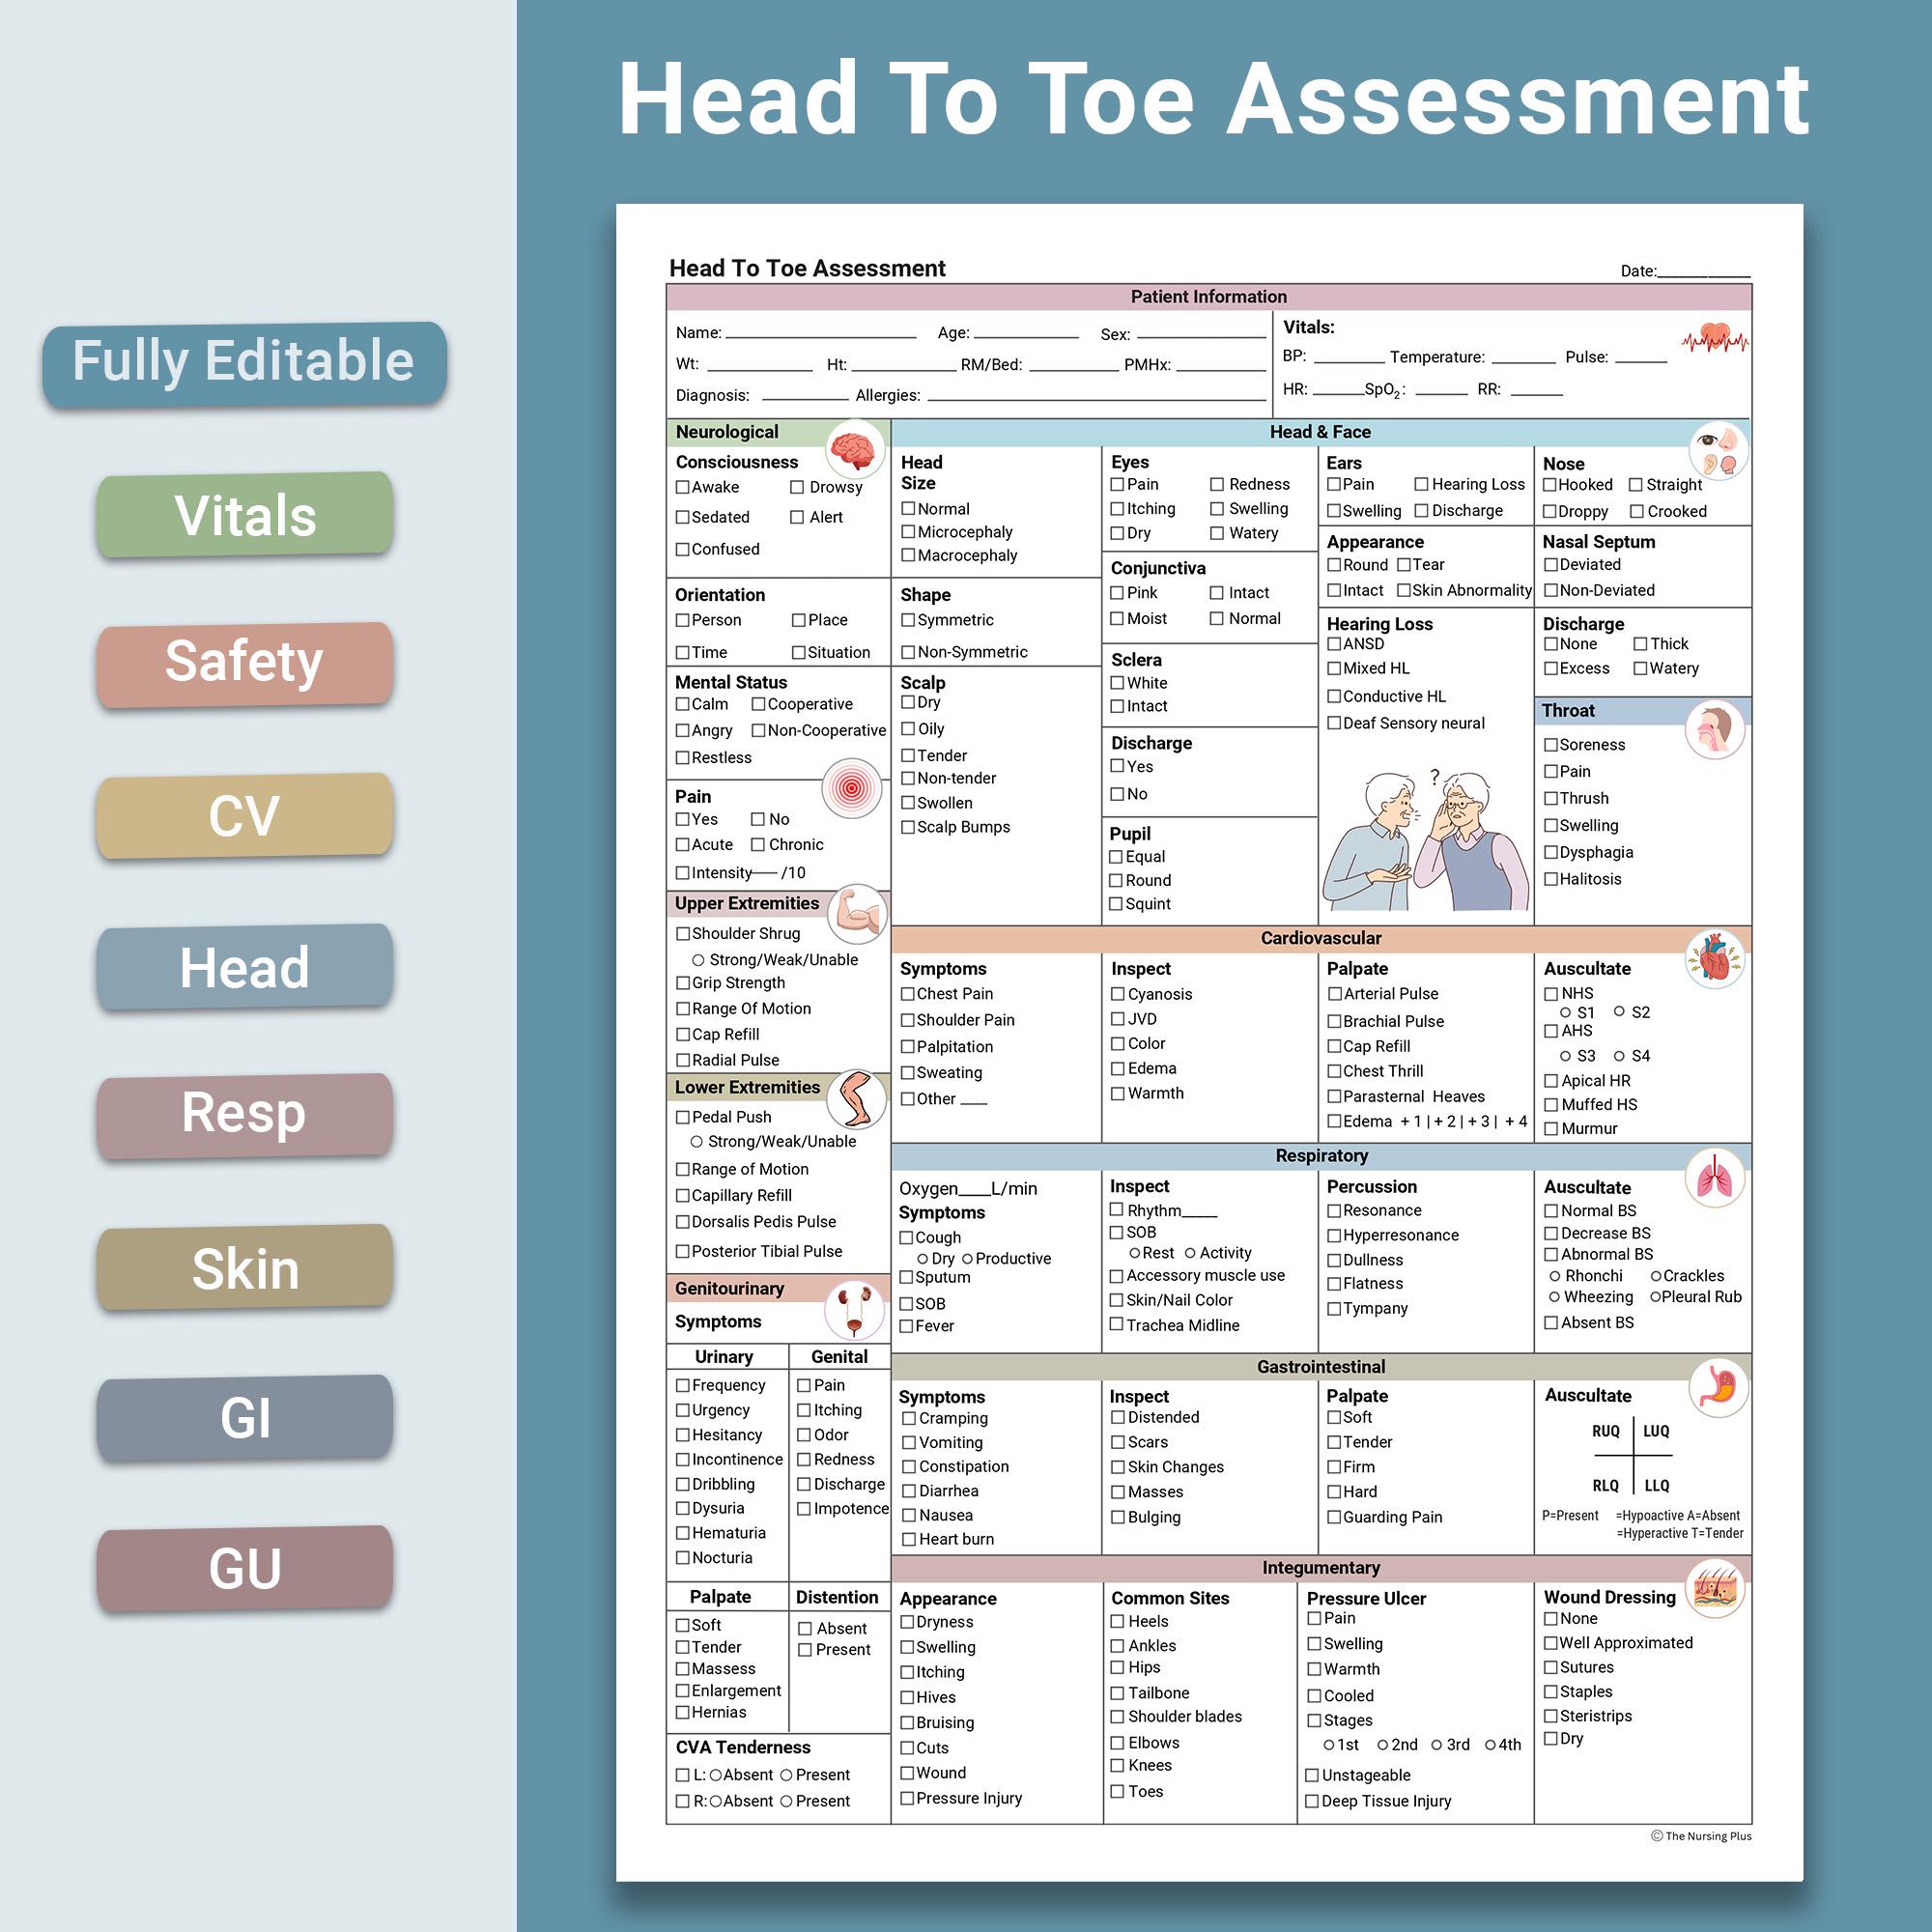
I don't host downloadable files directly, but here's a structured template you can copy into any word processor or note-taking app and format to your preference. Start with this skeleton and fill in your own clinical priorities: Section 1: Subjective Screening Questions Chief complaint and history of present illness

Review of systems — positive and negative findings Past medical, surgical, and family history relevant to current visit Current medications and allergies
Section 2: Objective Assessment by System Vital signs with age-appropriate reference ranges Head and neck — pupils, throat, thyroid, lymph nodes
Eyes — visual acuity screening, fundoscopic findings if applicable Ears, nose, throat — otoscopic and nasal inspection Cardiovascular — PMI, murmurs, peripheral pulses, edema
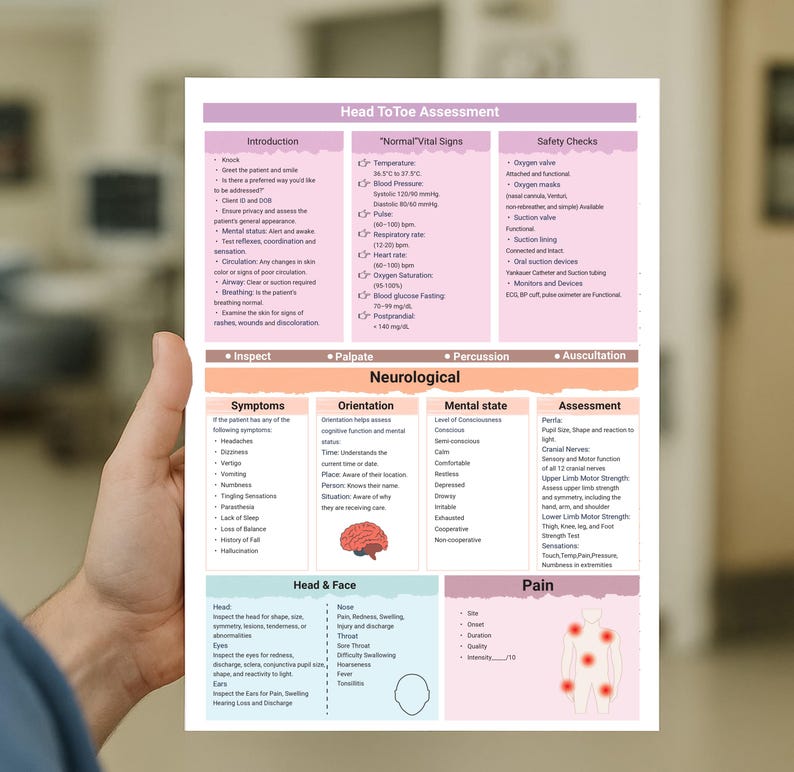
Respiratory — breath sounds, adventitious sounds, work of breathing Gastrointestinal — bowel sounds, liver span, splenic palpation, tenderness Genitourinary — indicated by age, sex, and chief complaint
MSK — range of motion, joint assessment, gait evaluation Neurological — mental status, cranial nerves, motor strength, sensation, reflexes, coordination Skin — lesions, rashes, turgor, changes in pigmentation
Section 3: Red Flags and Escalation Criteria System-specific warning signs that require urgent referral or emergency department activation Contact information for on-call services and urgent care facilities in your practice area
Section 4: Follow-Up and Documentation Prompts Assessment and plan structure — SOAP format reminders Labs and imaging ordered with rationale
Patient education points documented Return precautions given to patient The sheet I used for the majority of my early practice was a modified version of this structure, printed on cardstock and kept in a plastic sleeve on my clipboard. I updated it quarterly. The updates were usually minor — a new guideline citation here, a red flag I'd learned to watch for after a near-miss diagnosis there. But those incremental changes made a measurable difference in how consistently I performed assessments across different patient types.
If you're preparing for certification exams, this same structure applies. The ANCC and AANP both test your ability to recognize abnormal findings and know when to escalate, not just your ability to recite a sequence. A cheat sheet that includes red flags and escalation criteria will serve you better than one that only lists normal examination steps. Knowing what's normal is table stakes. Knowing when something isn't normal is what separates a competent NP from one who gets sued. I also keep a separate mental note about pediatric assessments. Kids don't cooperate with a head-to-toe approach the way adults do. My pediatric cheat sheet starts with observation — color, work of breathing, alertness, interaction with the parent — before I touch anything. That's non-negotiable. You can't force a toddler into a cardiac exam and expect useful data. Start with the least invasive observations and work your way down. The cheat sheet reflects that sequence. Geriatric assessments have their own complications. Frailty, cognitive impairment, and polypharmacy mean that a standard adult sheet misses critical context. I add a fall risk component and a medication reconciliation prompt to my geriatric version. The fall risk section alone — balance assessment, gait speed, history of falls in the past year — has caught more pre-fall situations than I care to count. It's three lines on the sheet and probably prevented a fracture or two in my practice.

The bottom line is that a Nurse Practitioner Assessment Cheat Sheet works when it's tailored to your actual clinical workflow, not when it's a generic document you printed from somewhere and hope covers everything. Build it yourself. Test it for a month. Then adjust it based on what you actually catch and what you almost missed. That iterative process is what turns a piece of paper into something that genuinely improves your clinical practice.
