What You Actually Need When You Walk Into a Room
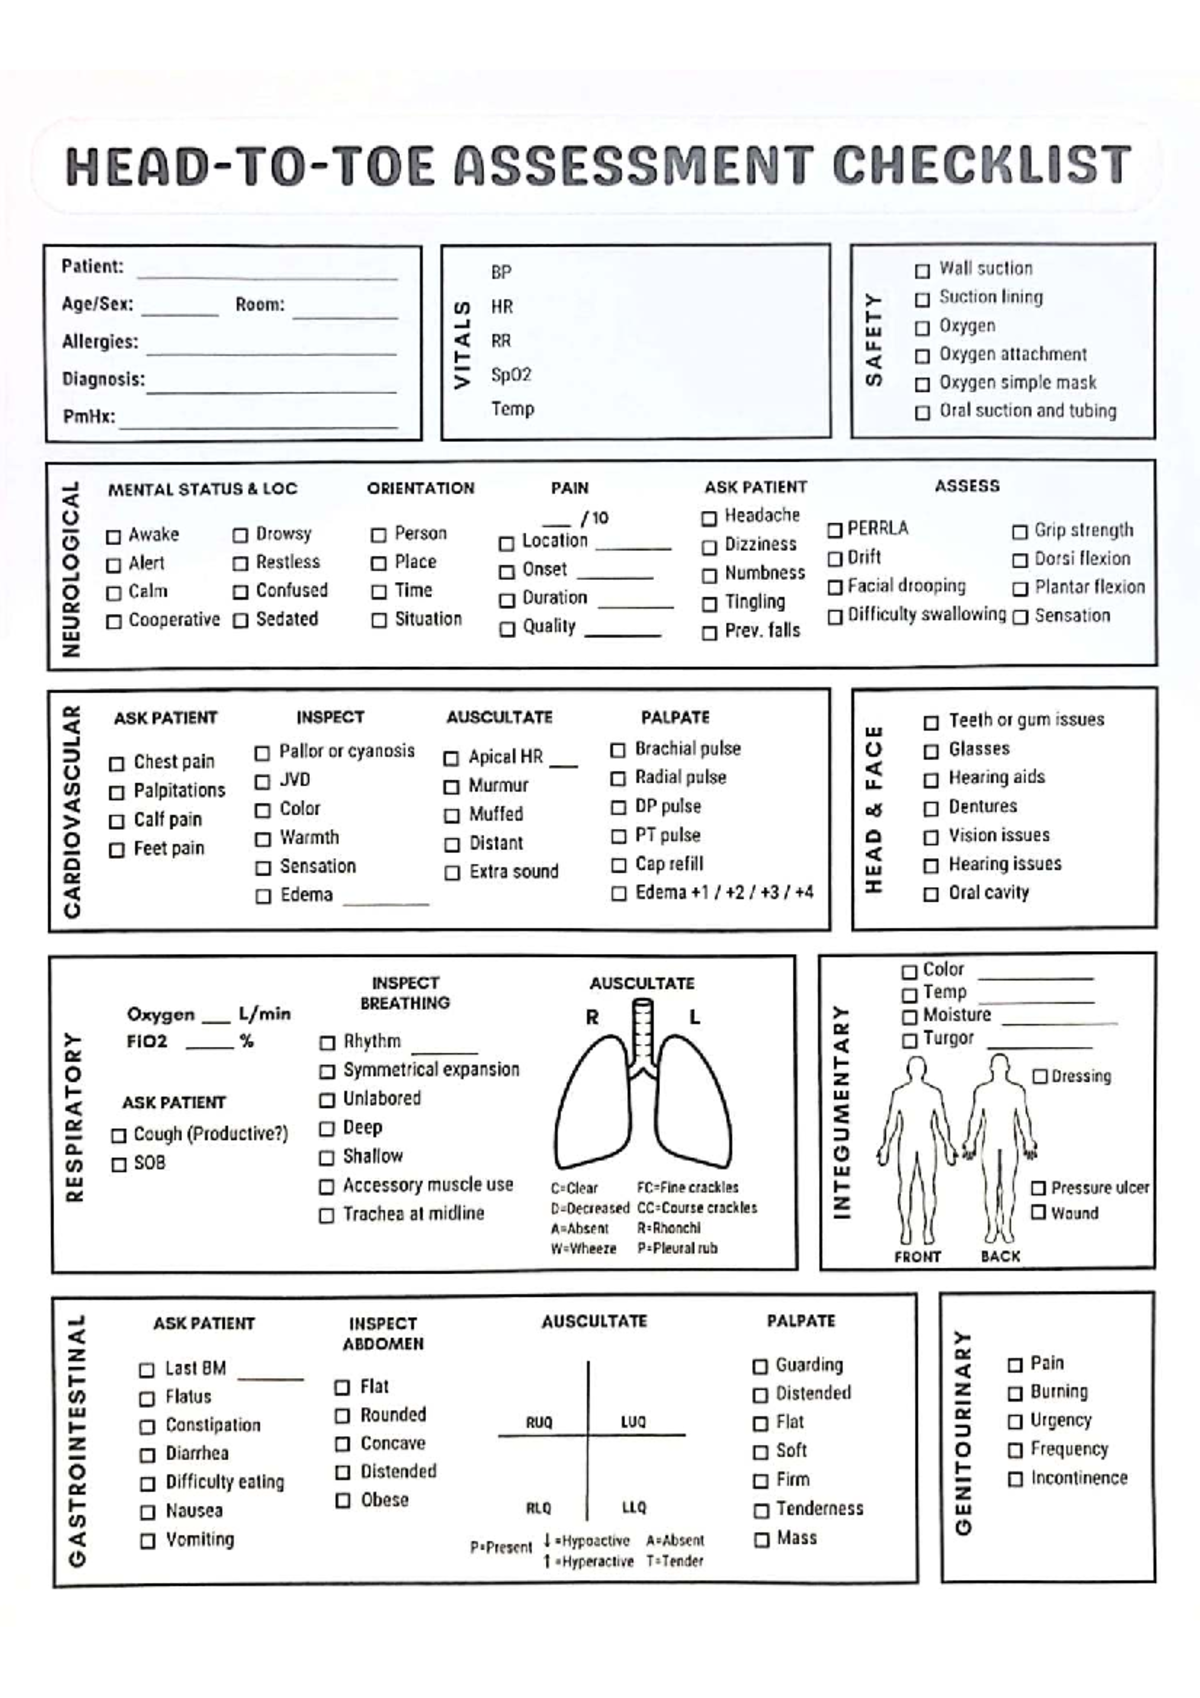
A head to toe assessment checklist isn't some rigid religious document you memorize and chant. It's a practical framework for not forgetting the stuff that matters when you're tired, rushed, or dealing with a patient who can't speak clearly. I've seen NPs skip steps because they relied on memory alone, and it usually comes back to haunt them. The core problem with assessment checklists is that most templates you find online are either too vague to be useful or so detailed they take longer to complete than the actual assessment. A good checklist sits somewhere in between. It reminds you of the sequence without forcing you to document every single breath sound individually.
Nurse Practitioner Head To Toe Assessment Checklist
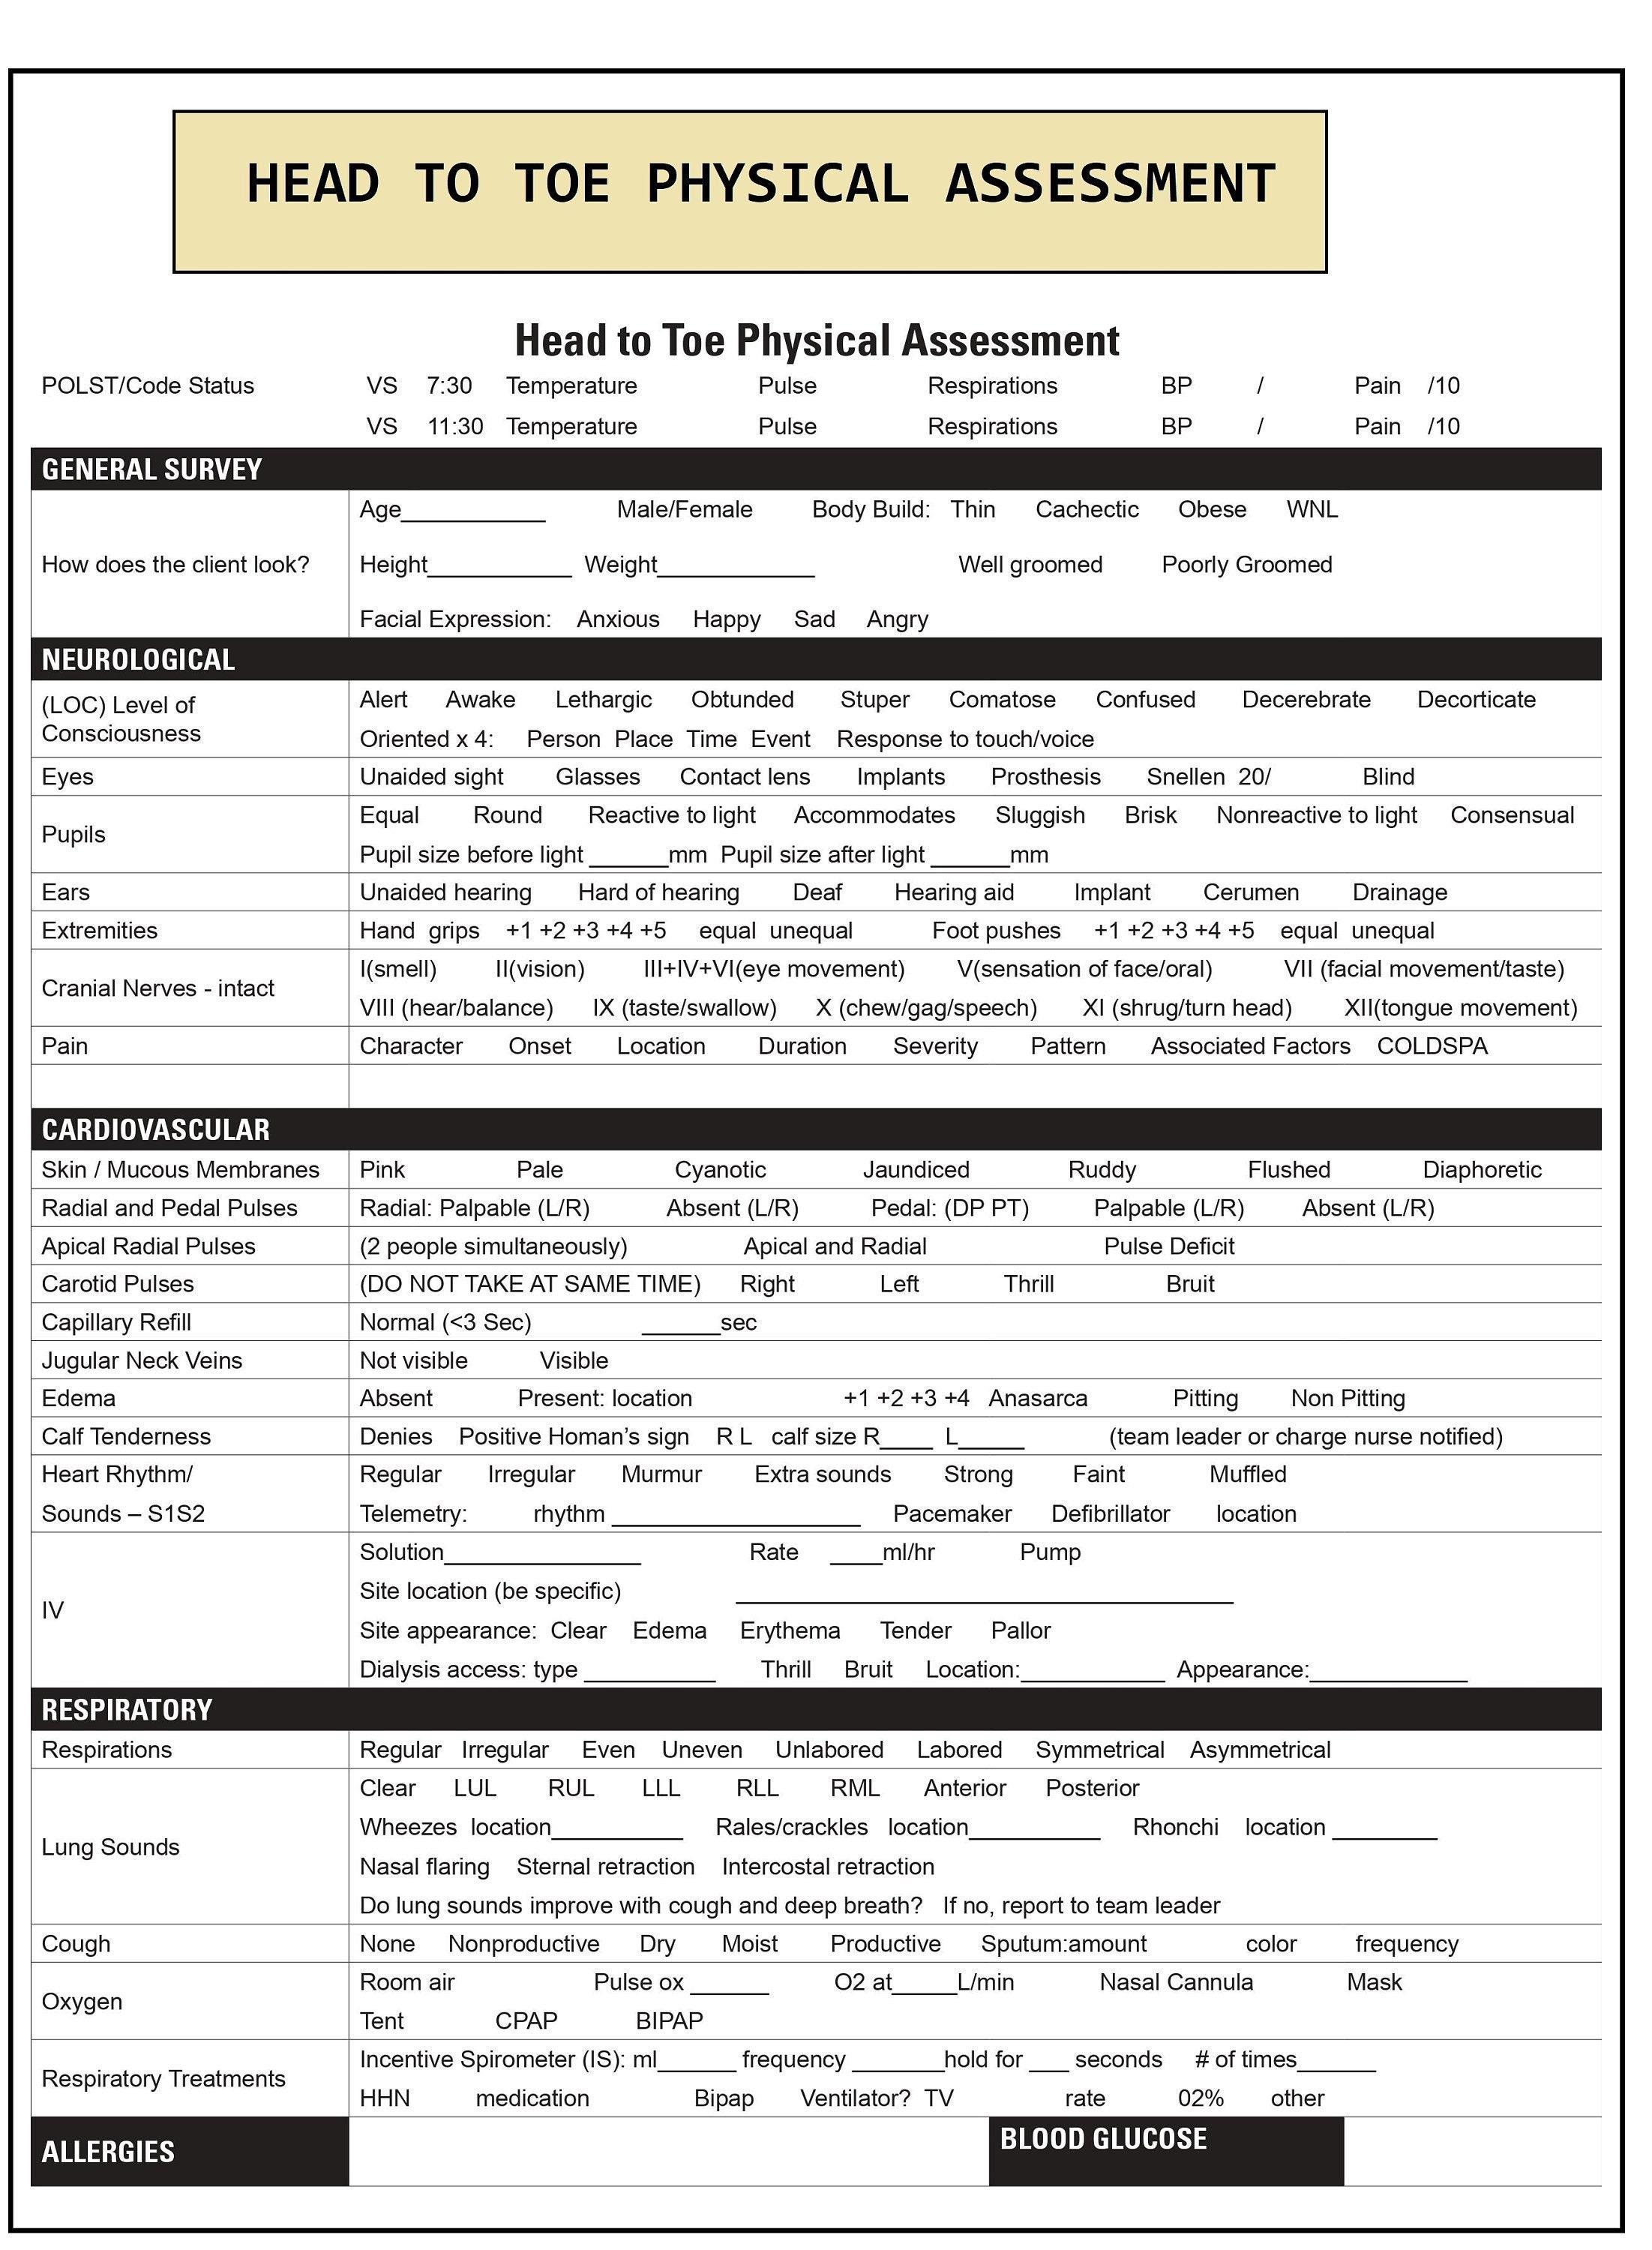
Here's what I actually use in practice. The structure starts at the head and moves downward, but the real value comes from knowing where to linger and where to move quickly. Vital signs go first, then general appearance, then system-by-system. Most people get tripped up on the ordering, which is why having a written framework helps even experienced practitioners. Start with vital signs and general survey. I know some programs teach you to do neuro first, but in my experience, getting blood pressure and oxygen saturation before you start poking around makes more sense. If that O2 sat drops below 92, everything else changes priority. Head to toe means you work systematically through these regions: neurological, HEENT, respiratory, cardiovascular, gastrointestinal, genitourinary, musculoskeletal, integumentary, and peripheral vascular. Each region has key assessment points that shouldn't be skipped. I once missed a unilateral pupil dilation in a trauma patient because I was rushing through the neuro portion. Took me three years to stop doing that.
What Goes in Each Section
Neurological assessment covers mental status, cranial nerves, motor strength, sensation, reflexes, and coordination. Don't skip the gait evaluation. People with normal strength and sensation can still have significant balance issues that only show up when they're walking. I use the four-step tandem walk test because it catches problems the stationary balance tests miss. HEENT gets abbreviated sometimes, but that's where you catch sinus issues, thyroid enlargement, and jugular venous distension. JVD is particularly important because it tells you about right heart function without needing an echo. I've learned to assess jugular venous pressure at 30 to 45 degrees rather than flat or upright. The angle matters more than most people realize. Respiratory assessment requires listening to all six lung fields anteriorly and posteriorly. That means three on each side, not just the typical two. I remember a COPD patient whose upper lobe consolidation was missed because I only listened to the standard spots. The auscultation points need to be systematic, not habitual.
Get the Full Details

Cardiovascular assessment includes heart sounds, pulses, and capillary refill. S3 and S4 gallops matter more in older adults than younger patients. A systolic murmur that was new today needs different follow-up than one that's been there for years. Document the timing, location, radiation, and changes with position or respiration.
Common Mistakes That Cost You Credibility
Skipping the genital examination when you're assessing an adult is a frequent error. I understand the discomfort, but omitting it means missing testicular masses, hernias, and pelvic pathology. If you're examining a patient of the opposite sex, have a chaperone available. Not because it's legally required everywhere, but because it protects both of you. Another mistake is documenting normal findings without actually assessing them. Saying "lungs clear to auscultation" when you only listened to two spots isn't accurate. Document where you listened. It takes an extra ten seconds and prevents questions during peer review. Pulse assessment gets abbreviated too often. Radial pulses tell you about rhythm and strength, but you should also check peripheral pulses in the feet for vascular patients. I assess dorsalis pedis and posterior tibial pulses bilaterally because asymmetry can indicate peripheral arterial disease that wouldn't show up in symptoms alone.
When the Checklist Fails You
Head to toe assessments don't work well in emergency situations where you need focused evaluation. A chest pain patient doesn't need a complete genitourinary exam in the ER. Use the checklist as a baseline, not a rigid mandate. Prioritize based on chief complaint and acuity. Obese patients make certain assessments harder. Heart sounds, bowel sounds, and liver edge palpation require different techniques. I use the sternal angle as a landmark for second rib identification because it works regardless of body habitus. Subcutaneous fat changes how you apply the stethoscope, not where you place it. Cognitive impairment complicates cooperation. Patients with dementia may not follow commands for strength testing or coordination exercises. Document what you can assess and note barriers clearly. "Inability to perform tandem gait due to cognitive deficits" is better than skipping the assessment entirely.
Documentation That Actually Helps
Write findings in a way that another provider can understand without asking questions. "Lungs clear bilaterally" is insufficient. "Lungs clear to auscultation in all six fields, no wheezes, rales, or rhonchi" gives better information. The extra words prevent miscommunication during handoff. Abnormal findings need specific documentation. Don't write "increased work of breathing." Describe what you see: nasal flaring, use of accessory muscles, tripod positioning. Quantify respiratory rate and note oxygen requirements. These details matter when the next provider picks up the chart. Reference ranges vary by age and population. A heart rate of 110 in a pediatric patient means something different than in an elderly adult. Document the patient's age when reporting vital signs. It helps contextualize whether a finding is truly abnormal or expected for that demographic.
Practical Tips from Actual Practice
Bring a penlight and reflex hammer to every patient encounter. I've been caught without them multiple times, and it delays assessment completion. Keep supplies in your pocket or lab coat, not in a drawer across the room. Wash your hands between patients, but also between body regions on the same patient. Cross-contamination happens more often than you'd expect. I transition from feet to face without hand hygiene and then wonder why foot fungus ended up near a conjunctival examination. Position patients appropriately for each assessment. Supine for abdominal exam, sitting for cardiac and pulmonary, lateral decubitus for certain heart sounds. Movement between positions takes time but improves assessment accuracy. Don't rush through positional changes.
When to Use Alternative Assessment Tools
Point-of-care ultrasound complements physical assessment but doesn't replace it. I use POCUS for cardiac function and lung pathology, but I still listen to heart sounds and breath sounds directly. Technology augments assessment skills, it doesn't substitute for them. Lab work supports assessment findings but shouldn't drive the entire evaluation. A normal BNP doesn't rule out heart failure in a patient with elevated JVP and bilateral edema. Physical exam findings often precede laboratory changes. Trust what you see and hear before ordering tests.
The Real Value of a Structured Approach
A systematic checklist prevents omission errors, especially during busy shifts or when you're managing multiple patients. I've completed assessments in approximately 15 to 20 minutes for stable patients using a structured approach. Unstructured assessments sometimes take longer because I circle back to things I forgot. The checklist becomes a safety net, not a crutch. Experienced NPs internalize the sequence and don't need to read it constantly. But having it available during training or when learning a new specialty provides structure without requiring memorization of every detail. Patient comfort matters alongside assessment completeness. Cover exposed areas between examinations. Explain each step before performing it. A patient who understands what you're doing cooperates better and provides more accurate responses to your questions.
Building Your Own Framework
Adapt checklists to your practice setting. Hospital NPs assess differently than clinic NPs. Postpartum patients need breast and perineal evaluation. Surgical patients require incision and drain assessment. Modify the standard framework based on patient population and clinical context. Create a abbreviated version for quick visits and a comprehensive version for new patient evaluations. I keep a one-page summary for follow-up encounters and a detailed template for initial assessments. The abbreviated version covers vital signs, review of systems, and focused exam findings in approximately 10 minutes. Review and update your checklist periodically. Clinical guidelines change, and new evidence emerges about assessment techniques. I revise my framework annually based on current literature and practice feedback. What worked five years ago may not represent best practice today.
Training Others to Use the Checklist
Teach NPs and students the rationale behind each assessment point, not just the sequence. Understanding why you assess jugular venous pressure helps retention better than memorizing "check JVP" as a checkbox item. Clinical reasoning develops when learners connect assessment actions to pathophysiology. Provide feedback on assessment technique during training. Watching someone palpate the liver or auscultate heart sounds reveals errors that checklist completion alone doesn't catch. I demonstrate techniques first, then observe learners, then correct specific issues. This approach improves skill development faster than written evaluation alone. Use standardized patients for assessment practice. Role-playing exercises help learners develop communication skills alongside technical abilities. A patient who explains their symptoms clearly enables better assessment than one who remains silent throughout the examination.

Integrating Technology with Traditional Assessment
Electronic health records often include assessment templates, but they sometimes force documentation into categories that don't match clinical reality. I customize templates to include fields for findings I regularly assess, such as thyroid examination and peripheral vascular evaluation. Mobile applications provide reminder checklists, but they don't replace clinical judgment. A phone app can remind you to check reflexes, but it can't tell you whether a diminished Achilles reflex is normal for that patient or warrants further investigation. Use technology as a supplementary tool, not a decision-making substitute. Telehealth assessment requires adaptation of traditional techniques. You can't palpate abdominal masses or assess joint range of motion remotely. Focus on history, visual examination, and patient-reported outcomes during virtual encounters. Document limitations clearly and recommend in-person evaluation when appropriate.
The Bottom Line on Systematic Assessment
A head to toe checklist serves as a cognitive aid, preventing oversight in complex patients. It doesn't guarantee diagnostic accuracy, but it reduces the likelihood of missing important findings through carelessness or fatigue. I've encountered patients with subtle presentations where systematic assessment revealed diagnosis clues that focused evaluation alone missed. Balance thoroughness with efficiency. Not every patient needs a complete assessment at every visit. Use clinical judgment to determine appropriate examination scope based on chief complaint, history, and prior findings. The checklist provides structure, but your expertise determines application. Continuous improvement comes from reflection on assessment experiences. Review cases where diagnosis was delayed or missed, and identify which assessment steps were omitted or performed inadequately. This retrospective analysis strengthens future practice more than any checklist revision alone.
The checklist you use should fit your workflow and patient population. Experiment with different formats until you find one that feels natural and promotes comprehensive yet efficient examination. What works for one practitioner may not suit another, and that's acceptable. Adaptation leads to better outcomes than rigid adherence to any single template.