The Paperwork That Actually Matters Before You Open Your Doors
Most nurse practitioners building a private practice spend months worrying about their business plan format. They chase five-year projections and perfect pitch decks while their credentialing applications sit in limbo because they never started the process early enough. The truth is that the document itself matters far less than the sequencing of the actual work it represents. I learned this the hard way back in 2019 when I built my first independent practice. I had drafted a perfectly formatted business plan, printed it in leather binding, and everything looked great on paper. Then UnitedHealthcare rejected my application because I listed my scope of practice as "general primary care" instead of specifying "adult-gerontology primary care with prescriptive authority in the state of Texas." Three months lost. Three months of zero patient volume while I resubmitted with corrected documentation. The formatting was flawless. The specificity was nonexistent.A Nurse Practitioner Private Practice Business Plan needs to function as both an internal roadmap and a document that payers and lenders will actually read without putting it down. It should cover entity formation, credentialing timelines, malpractice procurement, revenue cycle setup, and realistic patient volume projections. That is the baseline. The nuances are where people fall apart.
Nurse Practitioner Private Practice Business Plan: What It Actually Needs to Contain
The core sections are straightforward, but the execution reveals whether you understand how this business works or whether you copied a template from SCORE. Start with your legal structure and jurisdiction. A PLLC or professional corporation is standard in most states for NP-owned practices. Your business plan should note which state you are incorporated in and whether you plan to practice across state lines under telehealth regulations. Interstate practice adds a whole layer of complexity to credentialing that most first-time founders gloss over. Your payer mix strategy is the next critical section. I see too many new practices project they will have Medicare, Medicaid, and three major commercial plans enrolled within ninety days. In reality, payer enrollment averages four to six months per contract. You need to project at least six months of lean operations before you see full revenue from multiple payers. Plan for that gap or you will be personally funding your overhead by month three. Malpractice insurance selection deserves more attention than it gets. Tail coverage versus claims-made policies is a decision that can cost you thousands later. If you leave a job or close a practice under a claims-made policy without purchasing tail coverage, you are personally liable for incidents that occurred during your practice period even after your policy ends. I worked with an NP who closed her practice after two years and skipped the tail coverage because it cost $8,000. She had a claim filed against her seventeen months later and had no protection. Do not be that person. The revenue cycle section should specify your billing approach. Self-billing versus outsourcing to a medical billing company changes your cash flow timing significantly. A billing company typically takes twelve to eighteen percent of collections and can shorten your days in accounts receivable from forty-five days to twenty-eight days. The math usually favors outsourcing once you are billing beyond three thousand claims per month, but that threshold takes time to reach.The Sections People Skip And Regret Later
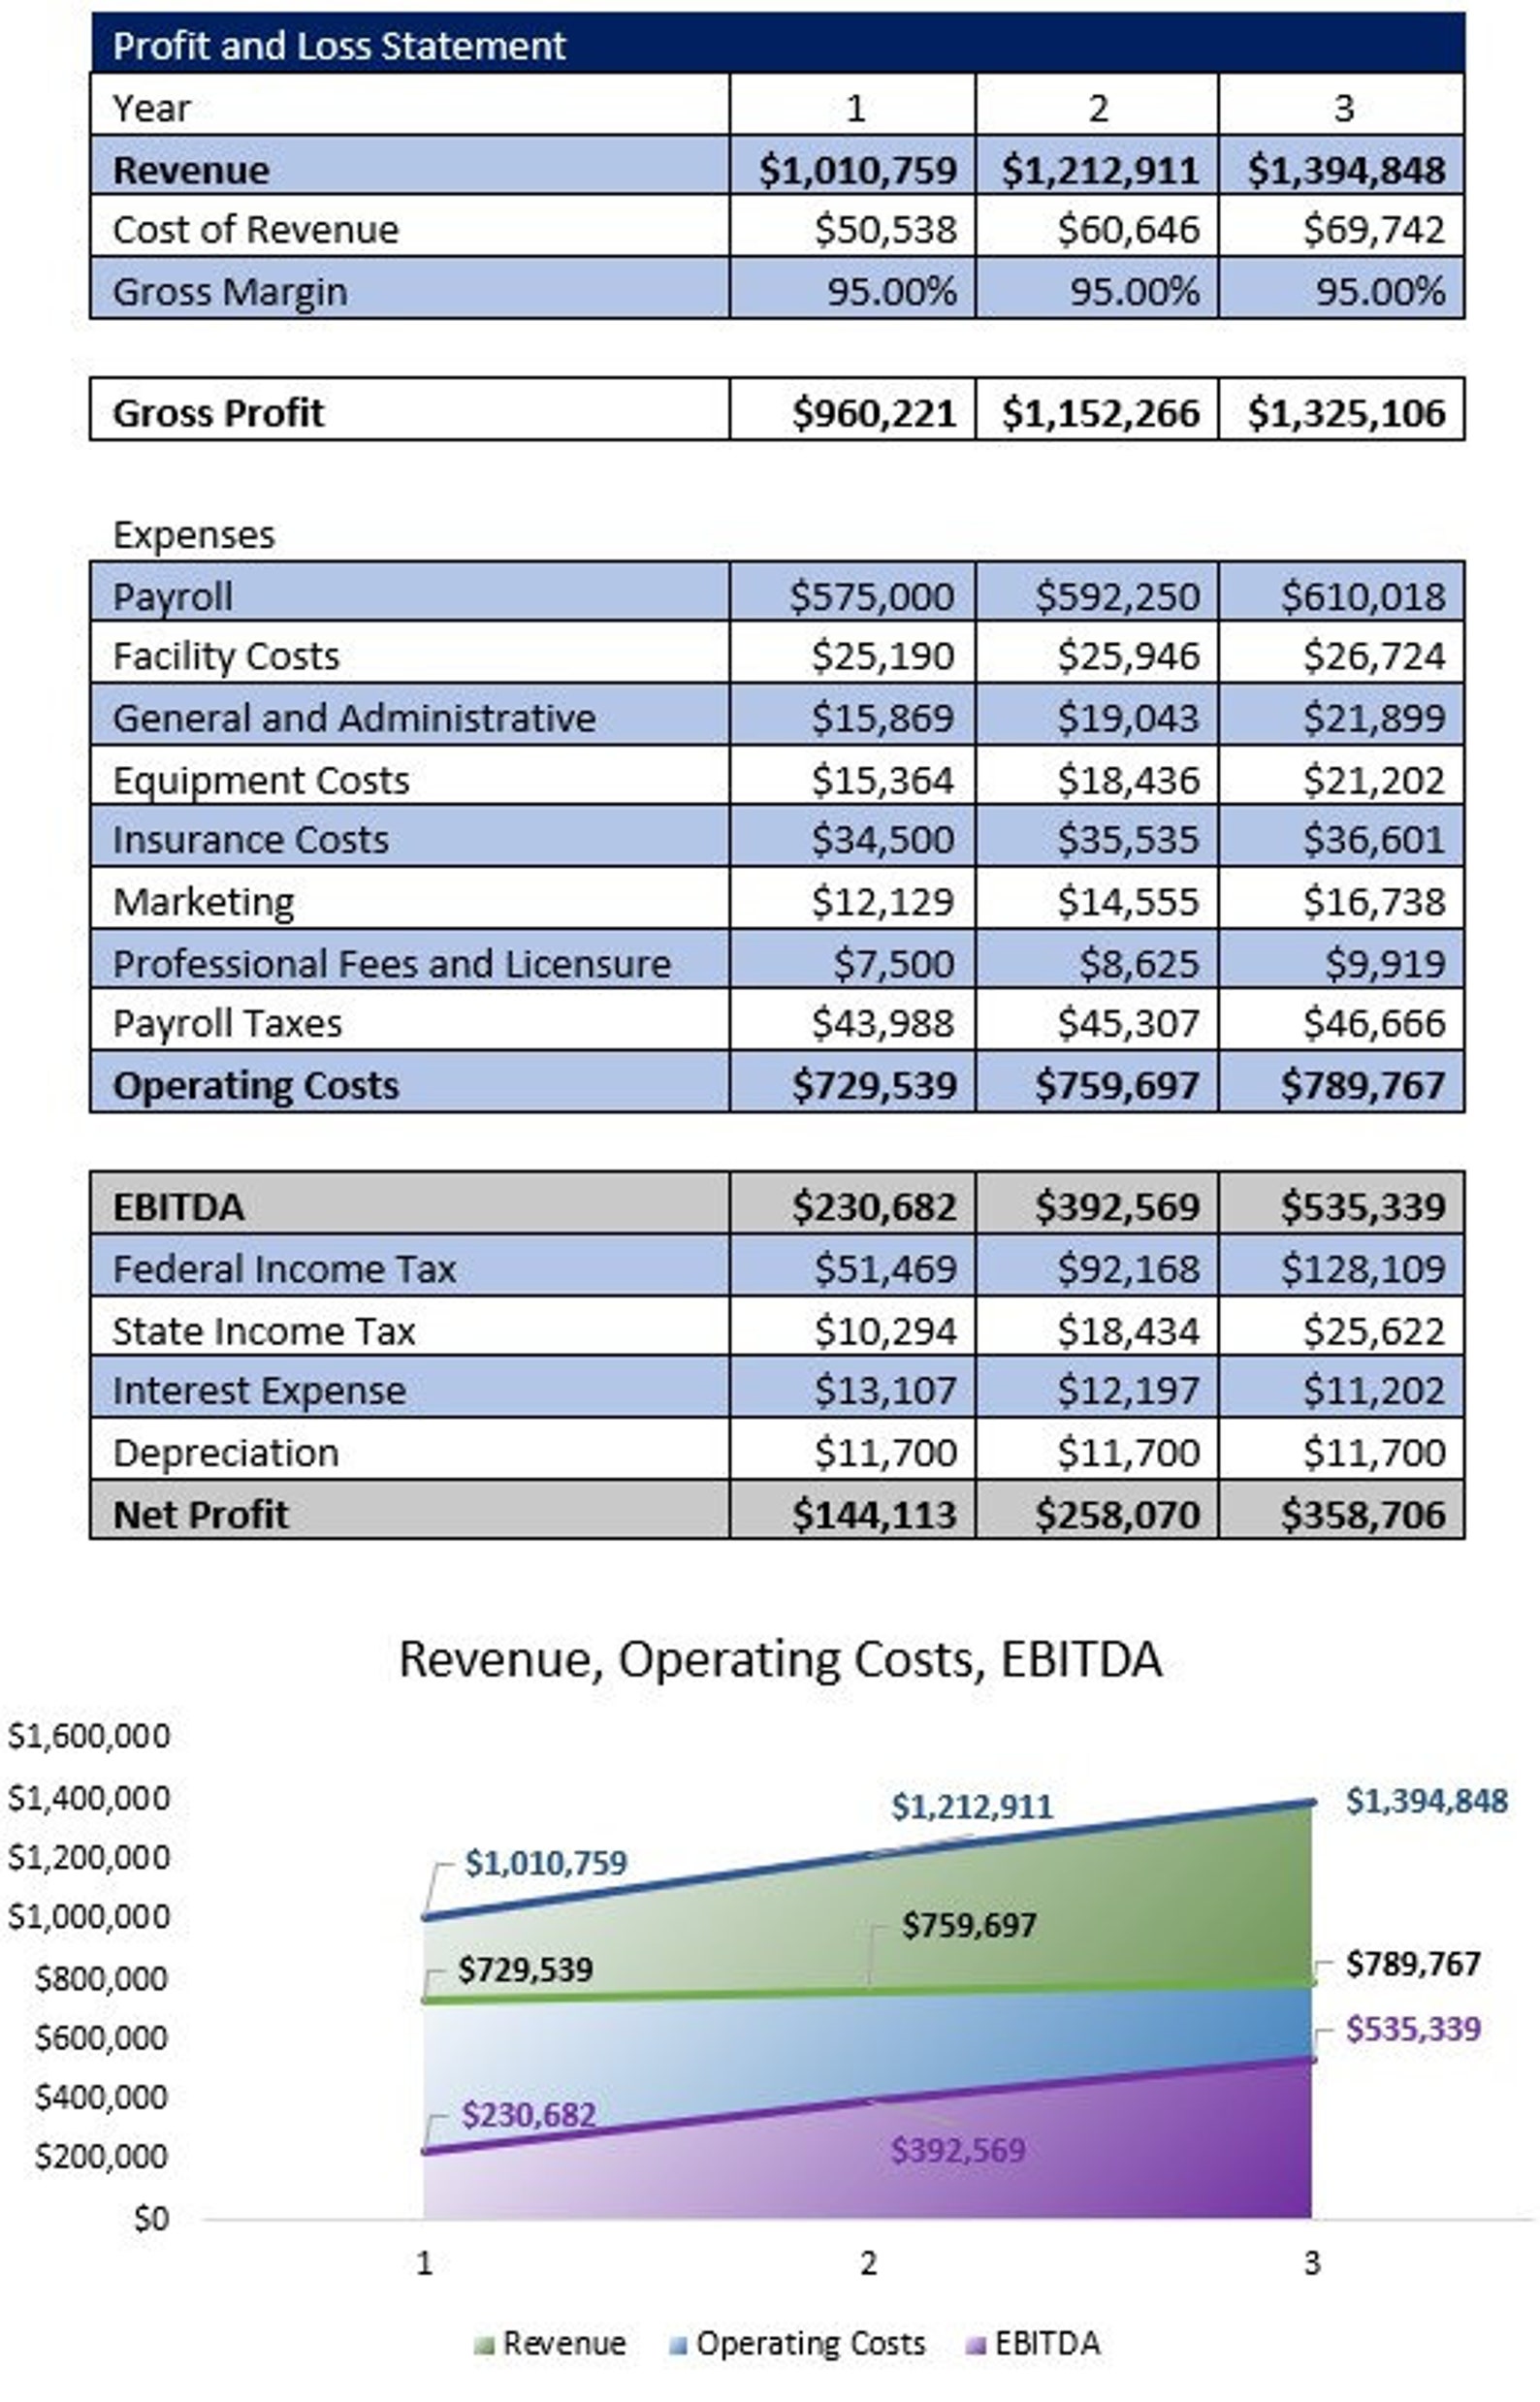
Your compliance and quality metrics section is not optional filler. If you plan to apply for CAHPS bonuses, MIPS reporting, or value-based contracts down the line, you need baseline processes in place from day one. Setting up chart auditing protocols and quality tracking after you are already seeing patients creates a massive administrative burden. I had a colleague who added a chart review process at month eight and spent roughly forty hours catching up on documentation standards for the previous seven months. That is unpaid time. Your expansion roadmap should be realistic about staffing. Advanced practice clinicians are difficult to recruit in many markets. I factored in a minimum ten-month timeline to hire and credential an additional NP or PA for a growing practice. Anything faster is speculative and usually leads to hiring someone who is not a good fit because you were desperate. Patient acquisition strategy is where most plans fail on paper and in practice. Writing "we will market through referrals" is not a strategy. You need to specify whether you are building referral networks with local hospitals, participating in hospital employed networks, leveraging digital marketing, or relying on community presence. Each channel has different cost structures and time to results. Digital marketing can start generating calls within six weeks. Hospital employed network contracts take eight to fourteen months. You cannot reasonably project the same timeline for both.Financial projections deserve specific assumptions rather than optimistic generalizations. Use actual per-visit reimbursement rates for your area from Medicare fee schedules and commercial payer data. A visit-level revenue estimate of one hundred eighty dollars might work in Manhattan. In rural Kansas it is closer to eighty-five dollars. Your plan should reflect your actual geography, not a national average that makes your numbers look better than they will be.