What Nurse Preceptor Training Modules Actually Look Like in Practice
I spent a decade on the med-surg floor before I was pulled into precepting, and the first time I sat through a formal preceptor training module, I thought it was going to be another compliance checkbox. It wasn't. The good ones force you to examine how you actually teach, not just what you know. The bad ones are PDFs buried in your employee portal that nobody reads until orientation week hits and someone panics. Most hospitals use a blended approach. There's a self-paced online component covering foundational theory, followed by an in-person or virtual session where you practice the actual skills of orienting a new nurse. The online piece typically takes between two and four hours depending on how many interactive scenarios they've baked in. The live session runs anywhere from three to eight hours. Together, they should total roughly six to ten hours of structured training before a preceptor is cleared to run their own orientation.
Building Your Own Nurse Preceptor Training Modules
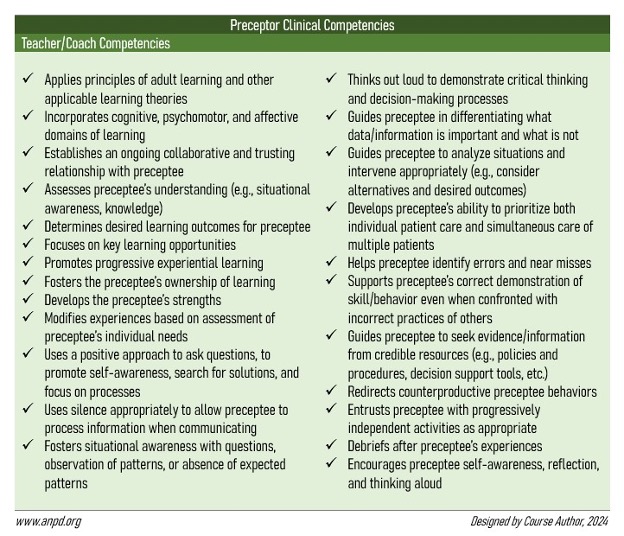
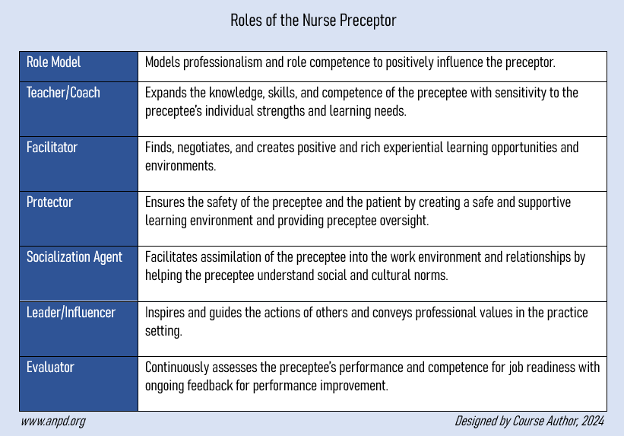
If you're designing these from scratch, start with the outcomes, not the content. A lot of programs flip that around and dump a bunch of materials into an LMS hoping retention sticks. It doesn't. Figure out what a newly credentialed preceptor needs to do on day one of an orientation, then work backward to build modules that train those specific behaviors. The core modules most facilities need fall into five buckets. First, the role clarification module. This covers what a preceptor is and isn't responsible for. New preceptors almost universally overextend themselves because they were never told where the boundary sits between teaching and doing the work for the student. Second, adult learning theory basics. Not the academic version, just the practical application. How do you adjust your teaching when someone has clinical experience but doesn't know your unit protocols? Third, assessment and evaluation techniques. This is where most programs stumble. They teach preceptors to fill out forms but not to have the conversation when a nurse is struggling. Fourth, communication and feedback models. Structure matters here. I recommend using something like SBI — Situation, Behavior, Impact — because it gives preceptors a script when they're dealing with a nurse who's defensive or disengaged. Fifth, cultural competency and inclusion. This isn't optional anymore. New nurses come from varied educational backgrounds, and the preceptor needs tools to recognize when bias is affecting their judgment of a learner's competence. I ran into a specific problem last year that exposed a gap in my hospital's existing training. We had a preceptor who was technically excellent but consistently rated new nurses poorly on their final evaluations. The training modules never addressed implicit bias or unconscious comparison — the tendency to measure a new grad against yourself at the same point in your career rather than against the competency checklist. I worked around it by adding a mandatory calibration session where three preceptors independently rated the same simulated case, then compared scores. The variance was brutal. One preceptor was giving failing marks for things that weren't even on the rubric. Another was inflating scores across the board because they couldn't have an uncomfortable conversation. After the calibration, the agreement rate jumped from about forty percent to seventy-two percent. That's not perfect, but it's functional.
Here's something most people don't tell you about these programs: the timing of the training matters more than the content depth. If you complete your modules three months before you're actually paired with a new nurse, roughly half of what you learned has faded by the time orientation starts. I've seen programs try to solve this by requiring annual recertification of the training modules, which sounds reasonable until you realize that most preceptors treat the annual refresh as a compliance hurdle. The workaround is spacing. Do the initial training four to six weeks before the anticipated orientation start date, then schedule a brief follow-up session two weeks after they begin precepting. That follow-up doesn't need to be long. Thirty minutes to debrief what's actually happening between the preceptor and the new nurse catches problems before they become tenure-level failures. Another counter-intuitive thing: experienced nurses often resist these modules the most. A nurse with fifteen years on the floor will sit through a two-hour training on how to teach and think it's basic. They're not wrong, but they're also not seeing the parts designed for them. The modules should explicitly call out the advanced topics — how to handle a nurse who's competent but resistant, how to manage orientation when you're short-staffed, how to escalate when a learner shows signs of impairment. Without those sections, veteran preceptors disengage and the training loses its value for the people who need it most. The biggest bottleneck in any Nurse Preceptor Training Modules program is faculty development. You can build the best curriculum in the world, but if the person facilitating the live sessions has never precepted or hasn't done it recently, the training becomes theoretical. I've watched skilled nurses try to facilitate these sessions using only their textbook knowledge, and the result was predictable. Preceptors walked away with frameworks they couldn't apply. The solution is straightforward but expensive. Make sure your module facilitators are currently active or were active in a precepting role within the last two years. If your budget doesn't allow that, bring in a clinical educator from a neighboring facility who specializes in this work. The cost of a consultant for a few sessions is nothing compared to the cost of a failed orientation and a nurse who quits before probation ends.
Get the Full Details

There's also a structural problem that most programs ignore. Preceptor training assumes the preceptor has the bandwidth to complete the modules and attend the live sessions without their regular workload suffering. In reality, hospitals rarely adjust schedules to accommodate this. Preceptors complete the training on nights, weekends, or during breaks, which means they're already fatigued before the module starts. I've recommended building in protected time as a condition of the training program. If the hospital won't give preceptors two hours of paid time to attend the live session, the program is setting them up to underperform from the start. It's a policy decision, not a training issue, but it directly impacts how effectively the modules land. If you need a starting point and your organization doesn't already have something in place, look at the resources from the American Nurses Credentialing Center and the Society for Nurse Preceptors. ANCC has a preceptor preparation toolkit that's free with membership. SNO offers downloadable module templates that you can adapt. The catch is that these are templates, not turnkey solutions. They require customization to match your facility's competencies, your electronic documentation system, and your specific patient populations. Budget about two to three weeks of part-time work to adapt a standard template to your environment. The alternative is buying a commercial program, which will run anywhere from five thousand to fifteen thousand dollars per year depending on the vendor and the number of seats you need. The metric that actually matters for evaluating these modules isn't completion rate. Everyone hits one hundred percent completion if you make it mandatory and punish people for not finishing. Look at orientation passage rates. Compare the percentage of new nurses who pass probation in their first year before and after you implement or overhaul the training. If the number doesn't move, the modules aren't the problem — the problem is usually something downstream, like lack of ongoing support or institutional turnover that makes it impossible to track outcomes properly. In my experience, well-designed modules combined with a structured check-in process during the first ninety days of an orientation can reduce early attrition by fifteen to twenty-five percent over a twelve-month period. That's not a guarantee. It depends heavily on your unit culture and whether nursing leadership actually acts on the red flags preceptors are trained to identify.