Writing Notes That Actually Work in Practice
Nurses notes are the legal backbone of patient care documentation. They're what gets pulled during audits, referenced during shift handoffs, and dissected in malpractice cases. Getting them right isn't about fancy language. It's about recording what you saw, did, and assessed in a way that other clinicians can actually use. I'm going to walk through how I approach charting notes, the format that stuck with me, and what trips people up more often than you'd think.
Standard Nurses Notes Examples to Build From
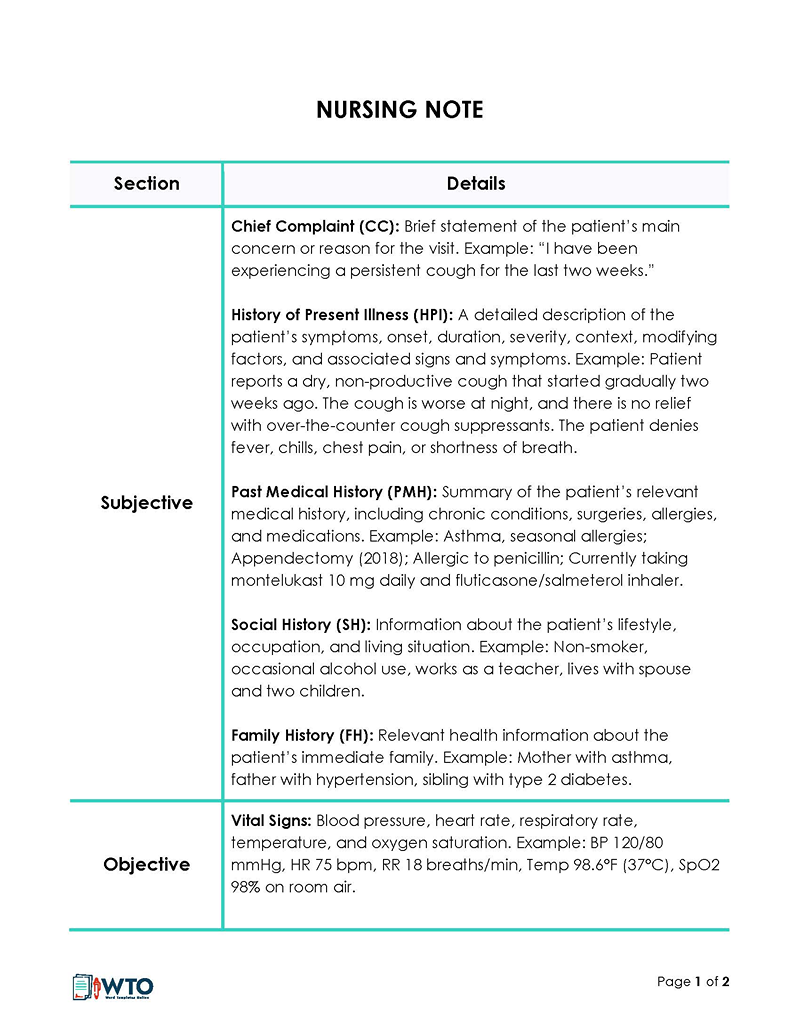
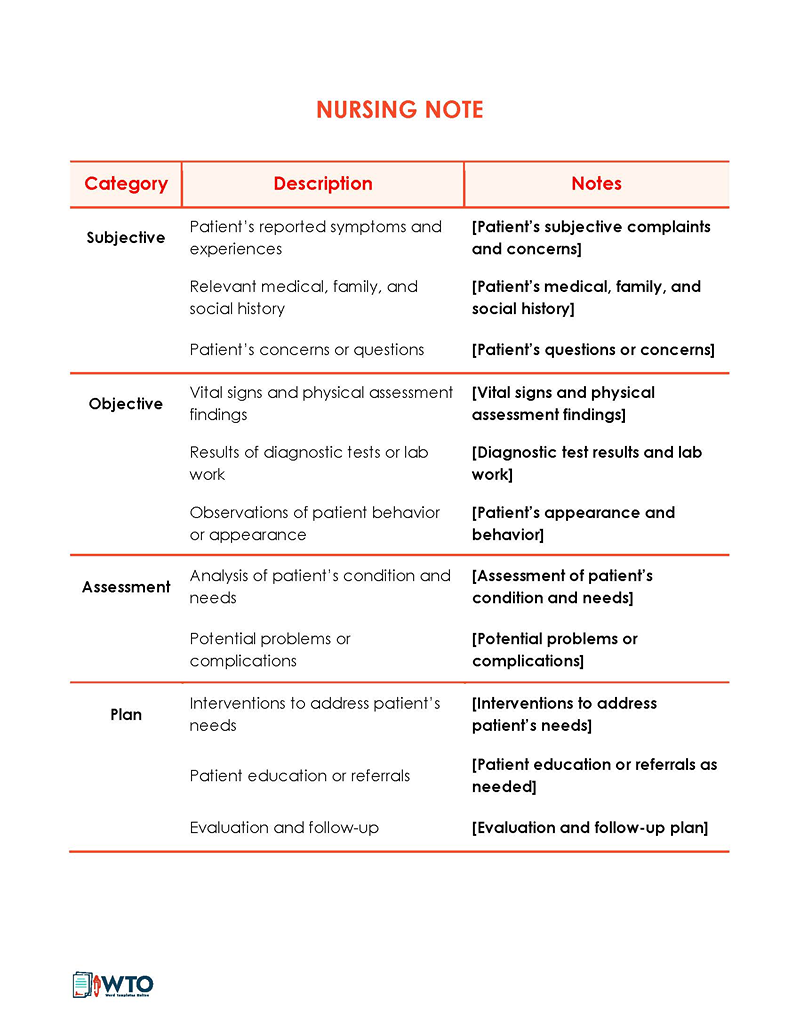
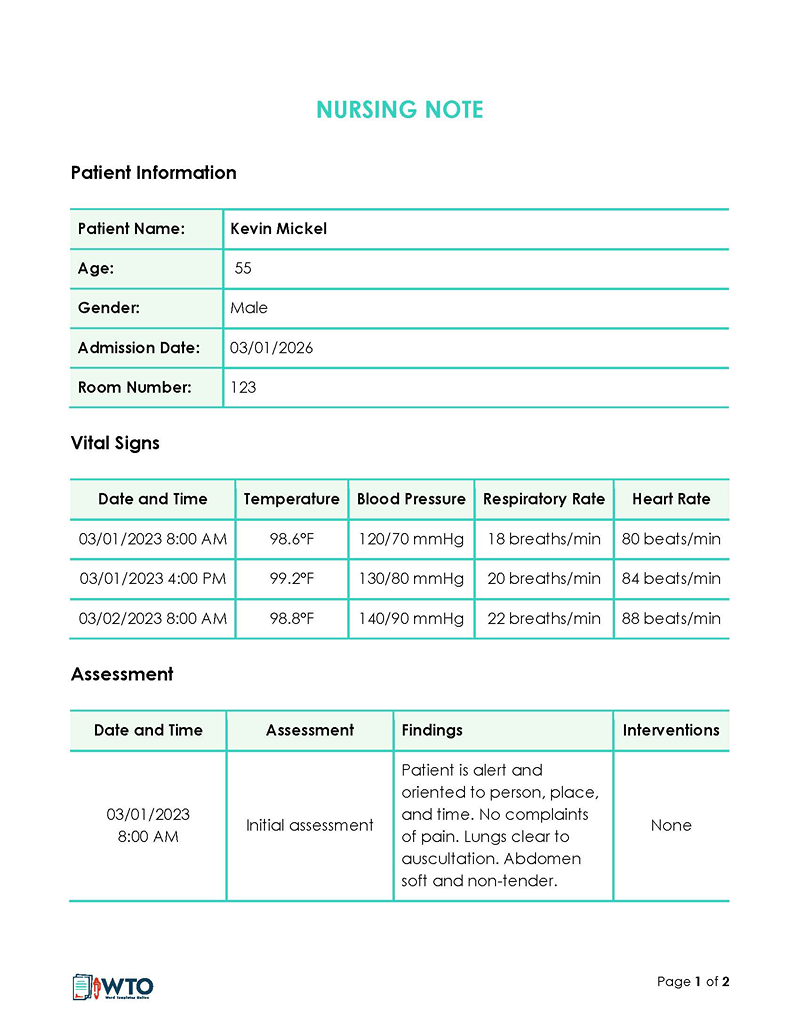
Most units still rely on the SOAPIER framework or variations of it. SOAP stands for Subjective, Objective, Assessment, Plan, Intervention, Evaluation, and Revision. Each piece maps to a specific type of information. Subjective is what the patient told you. Objective is what you measured. Assessment is your clinical read. Plan is what you're going to do. Intervention is what you actually did. Evaluation is whether it worked. Revision is the change if it didn't. Here's a basic example that covers a routine post-op check: Subjective: Patient reports pain level 6/10 at surgical site. States nausea improved since last dose of ondansetron. Objective: T 37.8°C, HR 88, BP 128/76, RR 16, SpO2 96% on room air. Incision site clean, dry, intact with no erythema or drainage. Lungs clear bilaterally. Abdomen soft, non-distended. Bowel sounds present in all quadrants. Assessment: Post-op day 1 from laparoscopic cholecystectomy. Vitals stable. Pain manageable with current regimen. Plan: Continue current pain management protocol. Advance diet as tolerated. Monitor I&Os. Intervention: Administered hydromorphone 0.5mg IV per order. Reassessed pain at 30 minutes post-administration. Encouraged oral intake. Evaluation: Post-medication pain reduced to 3/10. Patient tolerated 4oz of clear liquids without nausea. Revision: None needed. Continue current plan.
That's a complete note. Takes about 4 to 6 minutes to write if you have a template loaded. The trick is keeping every section honest. I've seen nurses pad the subjective section with fluff and then leave the assessment vague. That's where documentation falls apart.
Get the Full Details
The Format That Actually Saves Time
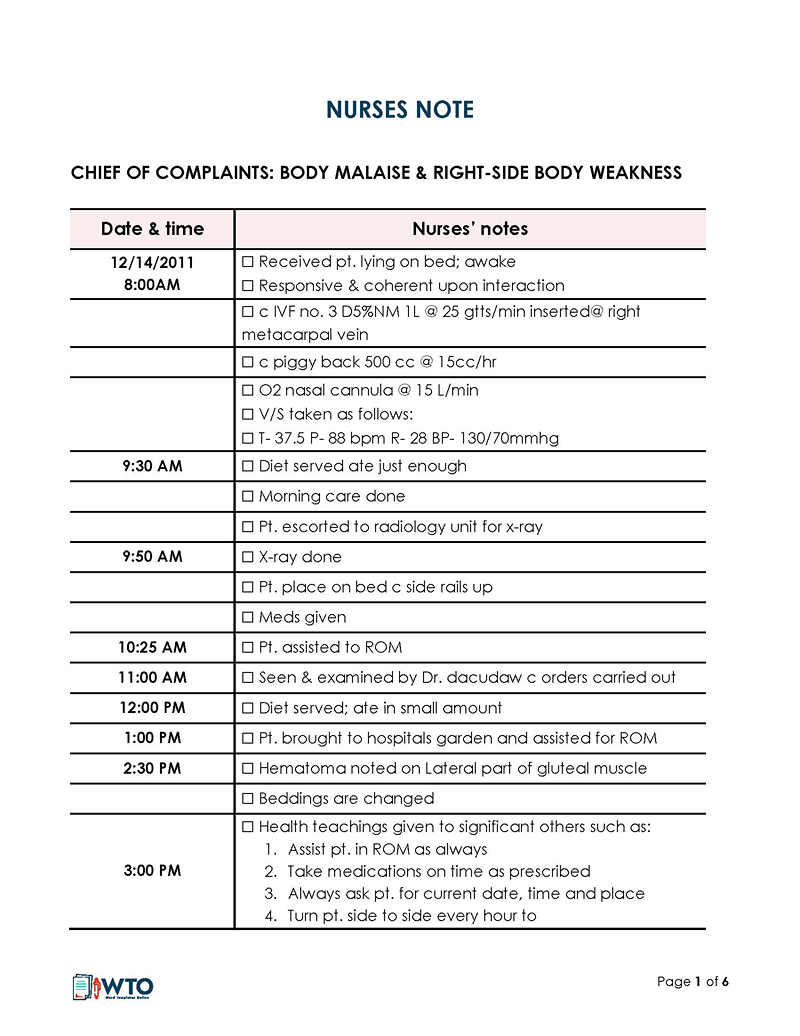
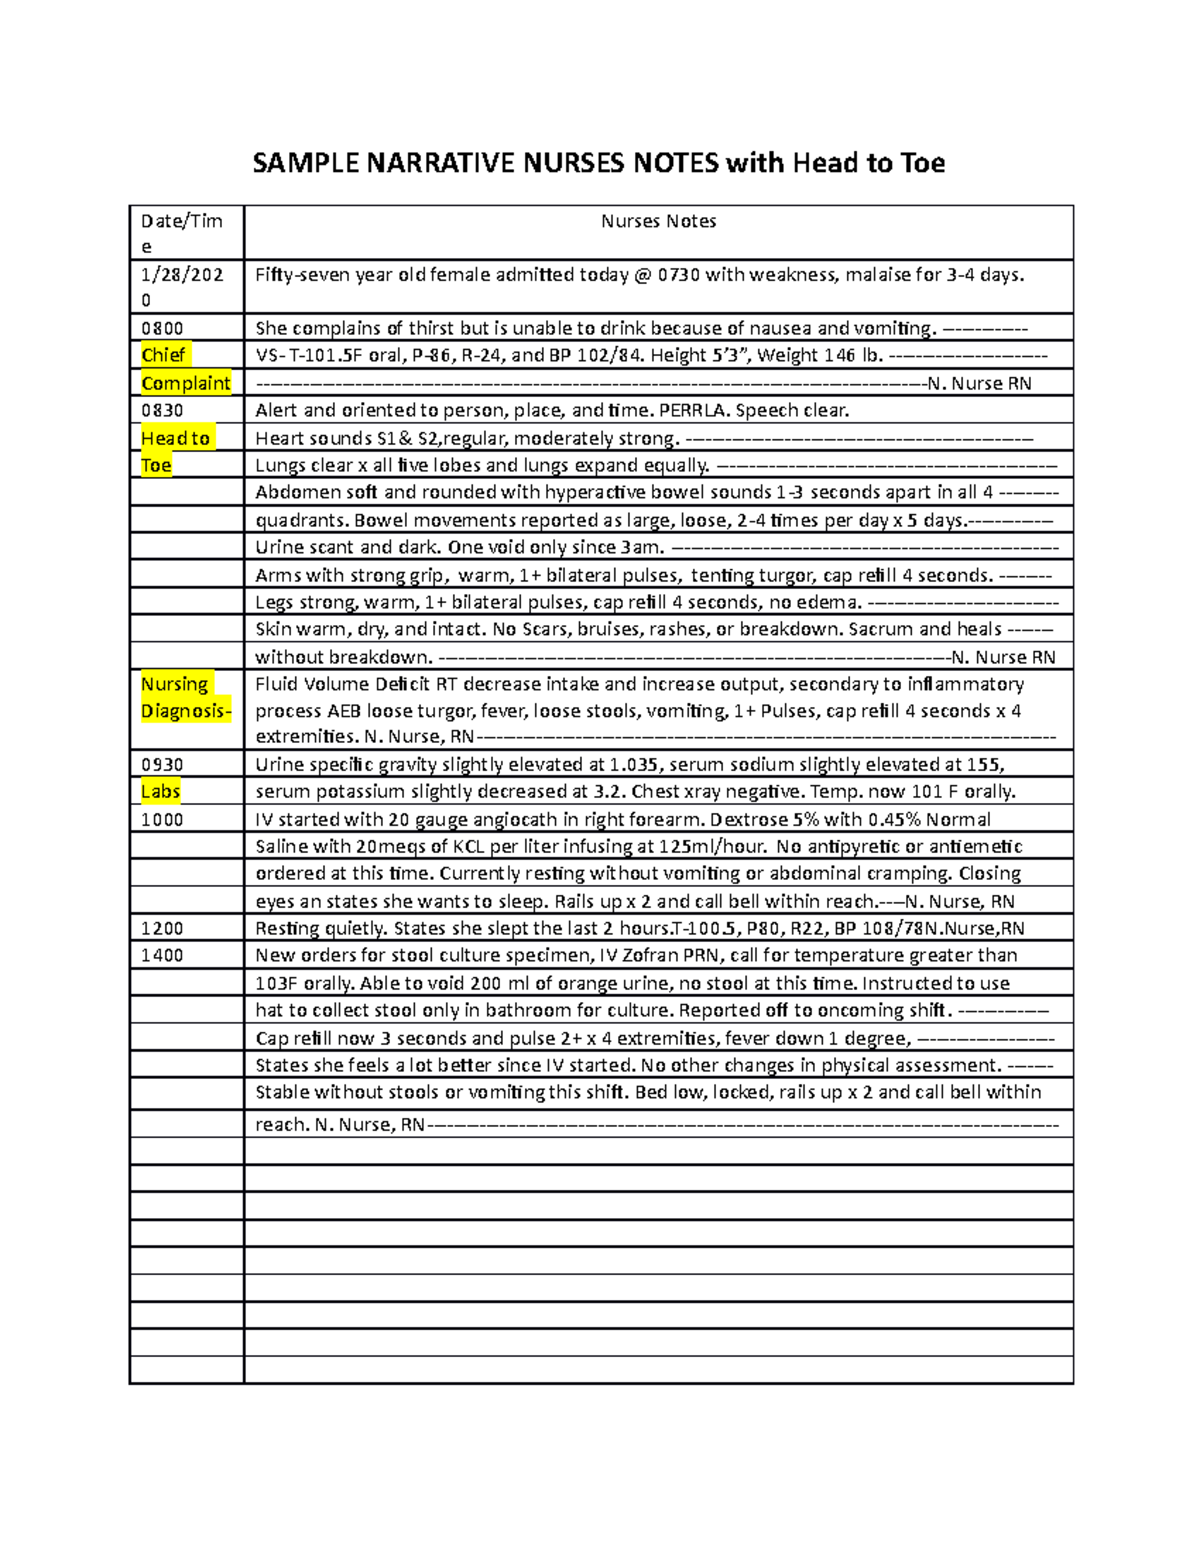
Electronic health records push you toward checkbox documentation, but checkboxes don't capture nuance. I learned early to treat the narrative fields as the real record and the checkboxes as supplemental. When I started using a consistent structure for every note, I cut my average charting time from about 12 minutes per patient to around 5. That's a huge difference over a 12-hour shift. Here's the structure I use for everything from med passes to wound assessments to admission notes: Start with a one-line header that includes the date, time, and what kind of note this is. Then go chronological within that category. Don't jump between topics. If you're documenting a fall risk assessment, don't weave in medication changes in the middle of it. Keep related things together. Use precise measurements. Not "moderate amount of drainage" but "approximately 3cm diameter of serosanguinous drainage on dressing." The first tells a story. The second holds up in court.
I also stopped using subjective terms like "patient appears well" or "vitals stable." Those words mean nothing to anyone reading the chart later. Replace them with the actual numbers and observations. If vitals are within normal limits, say which parameters and what the ranges were. Stability isn't a observation. It's a conclusion, and conclusions belong in the assessment section, not scattered through objective data.
Common Pitfalls That Sink Documentation
The biggest mistake I see is documentation lag. Nurses chart after the fact, sometimes hours later, and memory fills in gaps that shouldn't be there. I had a patient whose intake and output didn't match my initial assessment. I'd written "urine output adequate" without noting the exact volume because I hadn't measured it at the time. Four hours later I realized I'd estimated. That's not documentation. That's a guess dressed up as a fact. Another pitfall is copy-forward error. You copy a note from yesterday and update one line but forget to change the rest. I caught this once when a colleague documented a wound as "healing well" three days after I'd charted it as "newly dehisced." The copy-paste had carried over the old assessment verbatim. That's a serious liability issue. Always review the entire note before signing off, even if you're only changing one sentence. There's also the problem of incomplete intervention documentation. You gave a medication. You documented the medication name and dose. But you didn't document the route, the time of administration, or the patient's response. That's an incomplete record. The absence of documentation is legally treated as if the intervention never happened. I make it a habit to confirm route, time, and response every single time, regardless of how routine the medication seems.
When Standard Formats Fall Short
SOAPIER works for most situations. It doesn't work well for rapid events like codes or acute deteriorations. In those cases, I switch to a timeline-based format. I write the exact minute of each intervention as it happens, even if I'm filling in details afterward. During a recent code, I documented in real time on a scratch pad and then transcribed it into the EHR within 20 minutes of the event ending. The accuracy mattered because the family asked specific questions about what happened and when. Being able to pull exact timestamps from the original note made the difference between a clear explanation and a confused one. For daily progress notes on chronic patients, I've found that a modified DAR format works better than SOAP. DAR is Data, Action, Response. It's shorter and forces you to focus on what changed since the last note rather than rehashing the same baseline every day. A typical daily note might read: Patient reporting improved sleep quality since starting melatonin 5mg at bedtime. No breakthrough anxiety episodes recorded in 48 hours. Vitals unchanged from previous assessment. Continued current treatment plan with follow-up scheduled in 2 weeks. This kind of note takes about 90 seconds to write and still covers the essentials. The tradeoff is that it's less detailed than a full SOAP note. For stable chronic patients, the detail isn't necessary. For acute or complex cases, stick with the longer format.
Nurses Notes Examples for Specific Scenarios
Here's a quick reference for a few common documentation scenarios: Medication administration: Med administered per order. Route, dose, time, and site documented. Patient tolerating without adverse reaction. Vitals assessed pre and post-administration as applicable. Wound care: Wound assessed using ABCD method. Measurements recorded. Exudate characterized by amount, color, and consistency. Dressing applied per protocol. Patient report of pain level noted before and after dressing change.
Fall risk documentation: Patient assessed using Morse Fall Scale. Score recorded. Risk factors identified. Interventions implemented including bed alarm, non-slip socks, and hourly rounding. Patient and family educated on fall prevention. Acknowledgment of understanding confirmed. Pain assessment: Pain assessed using appropriate scale for patient's age and cognitive status. Location, intensity, character, and duration documented. Analgesic administered per order. Reassessment completed within specified timeframe. Pain level response recorded. The key across all of these is consistency. Use the same format for the same type of note every time. Your future self and whoever reads your chart at 2 AM will thank you. Inconsistent documentation is one of the top reasons nurses get cited during audits. It's not about being perfect. It's about being predictable in your documentation style so that anyone reading the chart knows exactly where to find what they're looking for.
What I Wish I'd Known Earlier
The thing that took me the longest to learn is that documentation is a skill separate from clinical skill. You can be an excellent clinician and still write terrible notes. The reverse is also true. I've worked with nurses who weren't the fastest at IV starts but whose charts were models of clarity. Those nurses rarely had any documentation issues during audits. Another counter-intuitive point: sometimes less is more. I used to write paragraphs describing everything I did. Now I write concise, factual statements that cover the same ground. "Assessed lungs. Clear bilaterally. No wheezes, rales, or rhonchi." That's four sentences instead of a long descriptive paragraph. It's faster to write and harder to misinterpret. The legal standard isn't thorough prose. It's accurate, timely, and complete documentation. Those are different things. One final practical tip: keep a personal cheat sheet of common abbreviations and documentation phrases that your unit accepts. Unit policies vary widely on what's allowed. What's standard on one floor might be flagged as non-compliant on another. I carry a laminated card with my unit's approved abbreviations. It's saved me from having to rewrite notes multiple times during audit review.
Nurses Notes Examples aren't about following a formula rigidly. They're about building a habit of clear, accurate, timely documentation that survives scrutiny. The formats I've described are starting points. Adapt them to your patient population and your unit's workflow. The goal is notes that any other nurse could read and immediately understand what happened, what you did, and what needs to happen next. Everything else is secondary.