What a Nursing Admission Assessment Actually Looks Like on the Floor
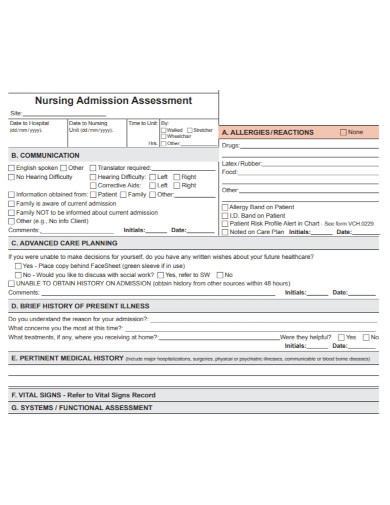
A nursing admission assessment is the document you complete when a patient arrives from the emergency department, transfers from another unit, or comes in for an elective procedure. It's not one form. It's a collection of checks — vitals, history, skin, pain, fall risk, medication reconciliation, allergy verification, and a handful of standardized screening tools that vary by hospital and specialty. I've done this on med-surg, ortho, and step-down. The paperwork changes, the discipline doesn't. Most places still use paper first pass, then scan into the EMR. Some are fully digital. Either way, the structure is roughly the same because the regulatory requirements behind it are the same: The Joint Commission standard MM.01.01.03, CMS Conditions of Participation §482.23, and your state nurse practice act all require a comprehensive assessment within a defined window after admission. The window is usually 8 hours for adults, 2 hours for pediatrics in many facilities. Miss the clock and you get a citation, not a warning.
Sample Nursing Admission Assessment Form
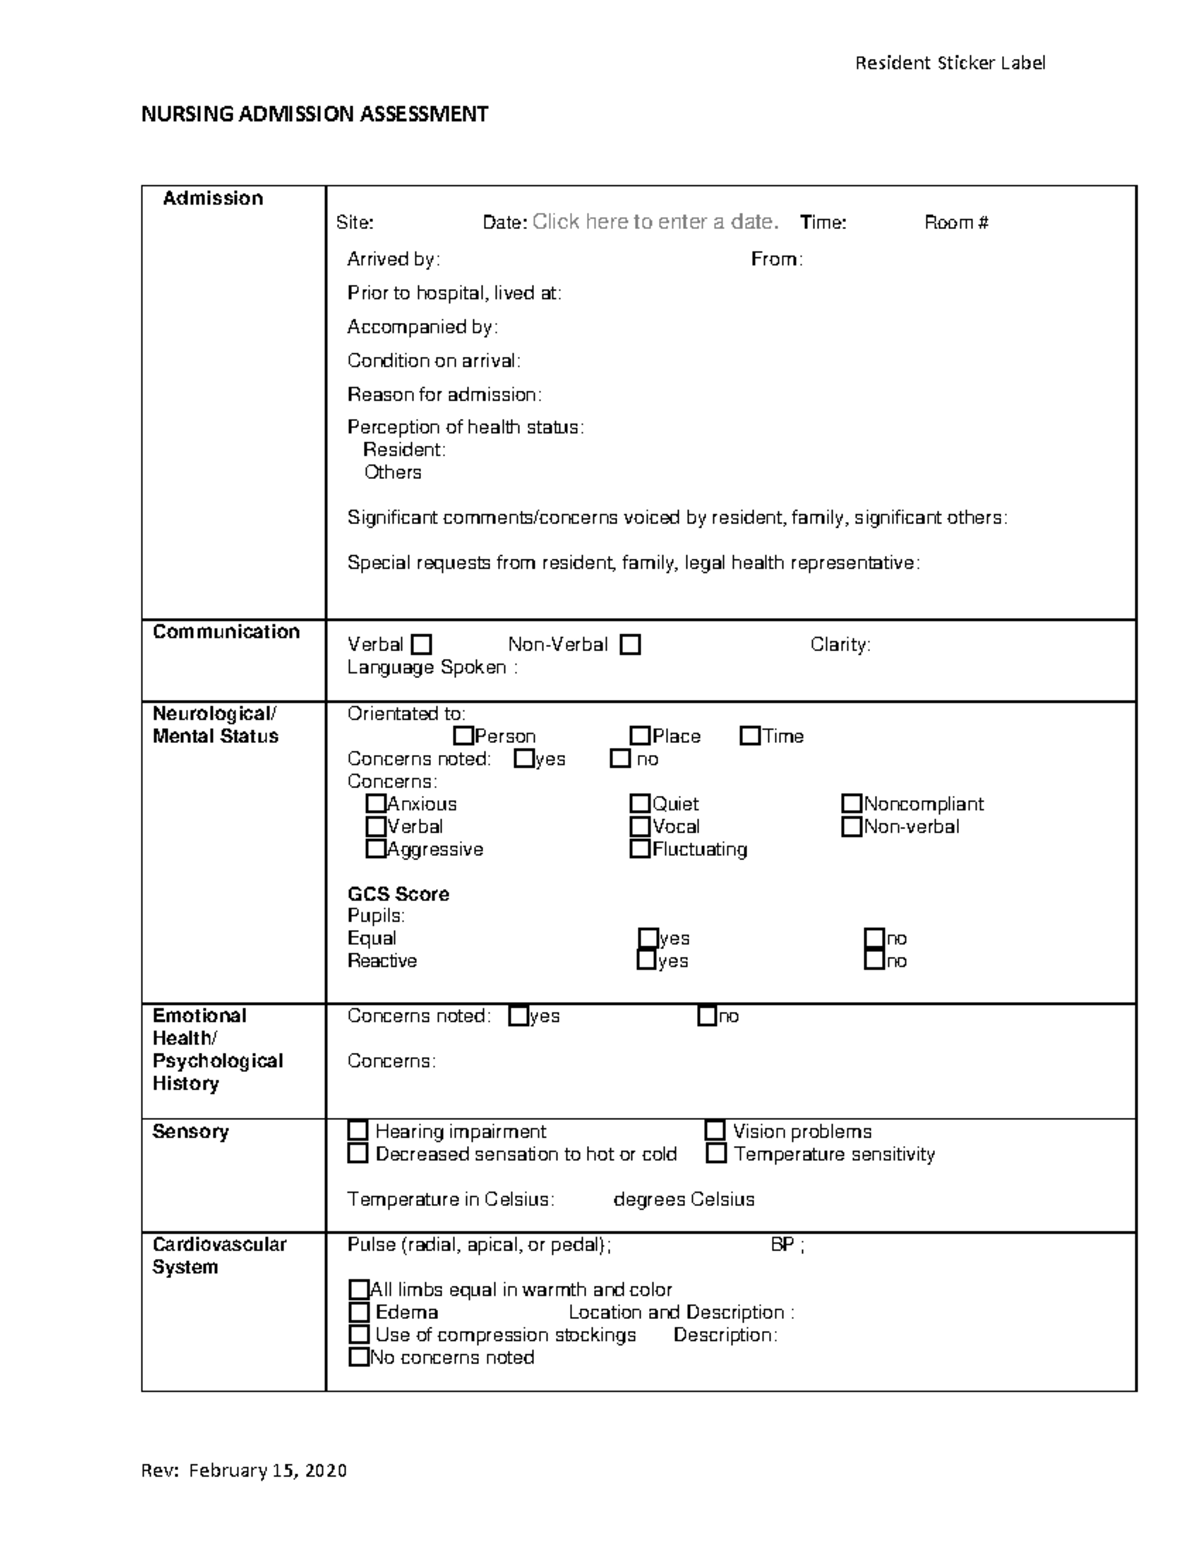
Here's a simplified example that mirrors what you'd actually see at the bedside. This is a composite — no single hospital uses all of these exactly — but it's close enough that you can use it as a reference template for training or competency validation. Section 1 — Identifying & Admission Data Patient name: ____________ Date of birth: ____________ Medical record #: ____________ Date/Time of admission: ____________ Admitting diagnosis: ____________ Source (ED/OBH/transfer/L&D): ____________ Insurance/authorizing #: ____________ Admitting provider: ____________
Section 2 — Chief Complaint & HPI CC: ____________ Onset: ____________ Duration: ____________ Aggravating factors: ____________ Relieving factors: ____________ Severity (0–10): ____________ Associated symptoms: ____________ Section 3 — Past Medical History
PMH: Hypertension / Diabetes / CHF / COPD / CAD / Cancer / Stroke / Renal disease / Thyroid disease / Depression / Other: ____________ Past surgeries (dates + outcomes): ____________ Hospitalizations (last 12 months): ____________
Get the Full Details

Section 4 — Medication Reconciliation Home medications listed by name, dose, route, frequency, and indication. Include OTC and supplements. Mark reconciled / held / changed / new per provider order. Signature of RN completing reconciliation: ____________ Section 5 — Allergies
Allergen: ____________ Reaction: ____________ Severity (mild/moderate/anaphylaxis): ____________ Verified (Yes/No/Unable): ____________ EHR allergy band applied: ____________ Section 6 — Vitals & Baseline Measurements BP: ____/____ HR: ____ RR: ____ Temp: ____ O2 sat: ____% on: ____________ Pain: ____/10 Height: ____ Weight: ____ BMI: ____ Cap refill: ____ Skin temp/texture: ____________
Section 7 — Pain Assessment (PQRST if applicable) P - Provocation/palliation: ____________ Q - Quality: ____________ R - Region/radiation: ____________ S - Severity: ____/10 T - Timing: ____________ Section 8 — Neurological Screening
LOC (Alert / Verbal / Pain / Unresponsive): ____________ Pupils (PERRLA / abnormal): ____________ GCS (E: __ V: __ M: __ = __): ____________ Orientation (person/place/time/situation): ____________ Strength (UE/L UE/LE/L LE 0–5): ____________ Speech: ____________ Section 9 — Respiratory Lung sounds (clear / crackles / wheezes / diminished): ____________ Cough (none/non-productive/productive): ____________ Sputum color: ____________ Respiratory effort: ____________ Smoking history (pack-years): ____________

Section 10 — Cardiovascular Heart rhythm (regular/irregular): ____________ S1/S2 (normal/abnormal): ____________ Edema (0–4+ location): ____________ Peripheral pulses (radial/dorsalis pedis/posterior tibial — 0 to 4+): ____________ IV sites (location/gauge/date/site condition): ____________ Section 11 – GI/GU
Bowel sounds (active/hypo/hyper/absent quadrants): ____________ Last BM date/character: ____________ Abdomen (soft/tender/distended): ____________ Urine output last 4 hrs: ____________ Voiding pattern: ____________ Foley catheter in place: Yes/No — if yes, indication: ____________ Section 12 — Skin & Mobility Braden scale score: ____________ (lower = higher risk). Score breakdown: sensory perception ____ moisture ____ activity ____ mobility ____ nutrition ____ friction/shear ____
Skin integrity: ____________ Pressure injury present (Yes/No) — if yes, stage/location: ____________ Mobility (independent / assist with device / bedbound/ chairbound). Turner-Fadell or similar: ____________ Section 13 — Psychosocial & Functional Living situation: ____________ Caregiver support: ____________ Advance directive status (Yes/No/Refused): ____________ Health literacy (understands instructions / needs interpreter / unclear): ____________ Interpreter needed: Yes/No — language: ____________ Suicide risk screen (PHQ-2/PGW or facility tool): ____________ Substance use screen (CAGE or CIWA if applicable): ____________
Section 14 — Safety / Restraints / Fall Risk Morse Fall Scale score: ____________ (score bands: 0–24 low, 25–50 medium, 51 high). Factors contributing: ____________ Restraint status: None / chemical / physical — if physical, indication/order/reassessment schedule: ____________ Section 15 — Nursing Diagnoses / Problems
Primary: ____________ Secondary: ____________ Plan of care goals (measurable, time-bound): ____________ Signature RN name, credentials, signature, date/time completed
I've seen this exact layout across three different health systems, and the variations are smaller than people assume. The differences live in the screening tools — some hospitals swap Morse for a specialty-specific tool, some add a literacy screener, some bundle social work referral into the same form rather than leaving it as a separate note. But the core structure doesn't shift much.
How to Actually Fill This Out Without Losing Your Mind
The hardest part of an admission assessment isn't knowing what to write. It's doing it in one pass when the patient is in pain, the family is asking questions, and your next patient is boarding in the hallway. Here's how I'd approach it in practice, in the order that usually works on a real shift. Walk in and establish what you already know before you touch anything. Check the ED chart, the transfer summary, or the discharge note from yesterday. Vitals and basic history are often already done. Document them, don't redo them. If the source says BP 152/88 and HR 94, and you recheck five minutes later and get 148/84 and 90, note both. The first number isn't wasted data. It tells you whether the patient is trending toward stabilization or deterioration after the initial intervention. Do the physical assessment in head-to-toe order, but let the chief complaint dictate where you spend the most time. If they're admitted for CHF exacerbation, listen to the lungs twice and check for sacral edema. Don't skip peripheral pulses because you're rushing. I've missed a diminished dorsalis pedis on an ortho admission because I was focused on the cardiac lung sounds. The vascular consult call came two hours later. That was avoidable.
Medication reconciliation should happen before the patient takes their first hospital dose, not after. This is where most admission errors hide. Home beta-blockers get dropped. Warfarin gets continued without a baseline INR check. OTC NSAIDs get forgotten until the patient calls for a headache and you realize they've been on ibuprofen 800 mg TID at home. Document every medication with a reason. If you can't establish why the patient was taking it, flag it for the pharmacist and the provider. That flag matters more than you think during a medication error root cause analysis. Allergy verification needs to be explicit. "NKDA" is not a verified allergy. It's an assumption. Ask the patient or the caregiver what happens when they take the drug. Penicillin causing diarrhea is not the same as penicillin causing angioedema, but both get documented, and both affect prescribing. If the patient says "I'm allergic to codeine" and can't describe a reaction, record that as "allergy reported — reaction not described." Don't infer anaphylaxis from a vague statement, and don't ignore it because the description is thin. Either way, the order set will flag it, and the pharmacist will verify it before dispensing. Pain assessment deserves its own moment separate from the physical exam. A patient who just had a thorough lung auscultation and is now sitting up to talk about their pain often scores lower than when you first walked in. Don't let the pain number from door-in freeze the assessment. Reassess after positioning, after breathing room, after the acute discomfort settles. Document both the initial number and the post-intervention number. That delta is clinically meaningful.

Common Pitfalls I've Seen On Competency Evaluations
I've sat on skills committees and watched nurses lose points on things that aren't really clinical. Here are the patterns that come up most often. Documentation timing. Several facilities require the admission assessment to be flagged as completed within the 8-hour window in the system notes. If you finish the paper form at hour seven but don't sign and timestamp it in the EMR until hour nine, the chart audit shows a late admission assessment even though you physically did the work. The fix is simple — sign as you go, or timestamp the form immediately upon completion before moving to the next patient. But people forget this under pressure, and it costs points on evaluation rubrics. Inconsistent scale use. Braden subscores should add up to the total. Morse components should sum correctly. GCS elements need to be consistent across shifts. I've seen a nurse document GCS 14 (E4 V4 M6) and then write "alert and oriented x4" in the neuro section without noting the V4 means confused conversation, not oriented. Those details matter during transfer Huddles and when the intensivist reads the overnight nursing summary.
Forgetting the advance directive screen. This one shows up everywhere. It's not a clinical assessment, but it's required documentation on admission in most jurisdictions, and it's almost always missed during the first pass. Ask about existing directives at the same time you ask about code status preferences. Document the answer regardless of whether a form exists. If the patient says no directive, write that. If they refuse to discuss it, write that too. Allergy band mismatch. The form gets filled out as penicillin-allergic, but the patient walks in wearing an allergy band that says "no known drug allergies." This discrepancy trips up medication administration teams and triggers pharmacy alerts. Verify the band at admission, reconcile any conflicts, and update both the band and the form simultaneously. Don't assume the band is right and the form is wrong, or vice versa. Both could be wrong.
When the Standard Form Doesn't Fit
There are edge cases where a generic admission assessment falls apart, and knowing how to handle them is what separates someone who's done this a hundred times from someone who's done it once and followed the template blindly. Pediatric admissions require age-adjusted vitals, developmental screening, and a different fall risk tool. Morse doesn't apply to a two-year-old. Use the facility's pediatric admission pathway, which usually includes a pediatric-specific pain scale (FLACC or Wong-Boker depending on age), a immunization verification check, and a growth parameter plot against percentiles. I've worked shifts where the pediatric admission packet included a separate parental consent verification section that wasn't in the adult form. Skipping it meant the lab couldn't draw without a signed consent on file, and we lost three hours waiting for a parent to return to the unit. Psychiatric admissions have their own admission assessment tracks. The medical assessment still happens — vitals, meds, allergies, skin — but the psych admission form adds a suicide risk screen, a violence risk assessment, and a substance withdrawal scale if applicable. A patient admitted for depression needs a PHQ-9 or CDS screen, not just a Morse fall score. Forgetting the suicide risk screen on a psych admission is a sentinel event waiting to happen. I've seen it caught during a handoff, and the admitting psychiatrist reordered the safety protocol before the nurse even finished the vitals section.
Emergency admissions where the patient can't provide history. Stroke, trauma, altered mental status — these patients often can't recount their medication list or allergy history. In those cases, you document "unable to obtain accurate history from patient." Then you chase it: call the family, check the patient's medication bottles at home if policy allows, pull the PCP's medication list from the health information exchange, and document each source. The "history from" field matters more than people realize. A chain-of-custody for the med list protects you clinically and legally. Transfers from another unit within the same hospital. Some facilities accept a recent assessment from the originating unit and waive the full admission assessment, but only if it was done within a specified time window — usually 24 hours. Others require a fresh assessment regardless. Check your policy. I've watched nurses skip the second assessment on a med-surg-to-ICU transfer because the ICU accepted the med-surg form, and then the transfer summary didn't include the respiratory assessment because the med-surg nurse hadn't documented lung sounds in real time. The ICU nurse had to redo half the assessment on an unstable patient. Wrong move on all sides.

Efficiency Tips That Actually Work
Two hours is the old standard for a comprehensive admission assessment. With practice and a clean workflow, you can cut that to forty-five minutes to an hour and a half without sacrificing quality. Here's what helps. Pre-read the incoming chart before you walk into the room. Twenty minutes of scanning the ED notes, the lab results, and the provider's admission orders saves you an hour of redundant questioning. You already know the diagnosis. You already know the relevant history. Walk in with a focused plan instead of starting from zero. Use a voice-enabled documentation tool if your facility supports it. Speaking the assessment while performing it cuts documentation time by roughly half compared to typing during or after. The tradeoff is accuracy — dictated assessments often need a quick review pass to catch medical terminology errors. But the time savings are real, especially during high-acuity admission blocks.
Batch the standardized screens. Braden, Morse, pain, fall risk, and advance directive screening can all be done in the same pass if you structure the interview that way. Don't do vitals, then walk away, then come back for the fall risk screen. Do them together while the patient is already positioned and talking. It's more efficient and the patient notices less disruption. Know which sections your unit's auditors actually review. Every facility has different chart audit priorities. Some focus heavily on medication reconciliation and allergy verification. Others weight fall risk scoring and skin integrity documentation more heavily. Understanding where the audit eyes land lets you prioritize your double-checks without spending equal time on low-yield sections.
Downloadable Reference
The example form I laid out above isn't tied to any specific hospital system. You can adapt it as a study guide for NCLEX prep, a competency validation tool for new-hire orientations, or a template base for building your own facility-specific admission assessment. If you're a nursing student, print it out and fill it in with a simulated patient scenario. If you're a charge nurse setting up a new unit, use it as a starting point and customize the screening tools to match your state's requirements and your electronic system's built-in flowsheets. Keep in mind that this example covers adult medical-surgical admissions. It's not a replacement for your facility's official form, and it won't satisfy regulatory requirements at your specific hospital unless it's been formally adopted and your policy references it. Use it as a learning tool, not as a legal document. The structure is portable. The details are not.
