
Practical Guide To Nursing Assessment For Anemia In Clinical Settings
I have spent more years than I care to count doing hematology assessments, and the thing nobody tells you is that pallor is about as reliable as a weather forecast in April. You look at someone's conjunctiva, nail beds, palmar creases, and mucous membranes, and you think you have your answer. Then the CBC comes back and shows a hemoglobin of 8.2 when they looked pink enough to drive home. This happens constantly, especially in patients with darker skin tones where the classic textbook descriptions simply do not apply. The reality of nursing assessment for anemia involves recognizing that visual inspection is only the starting point, not the diagnostic endpoint. What actually matters is combining subjective symptoms with objective findings in a systematic way that catches patients before they decompensate.Core Components Of Nursing Assessment For Anemia
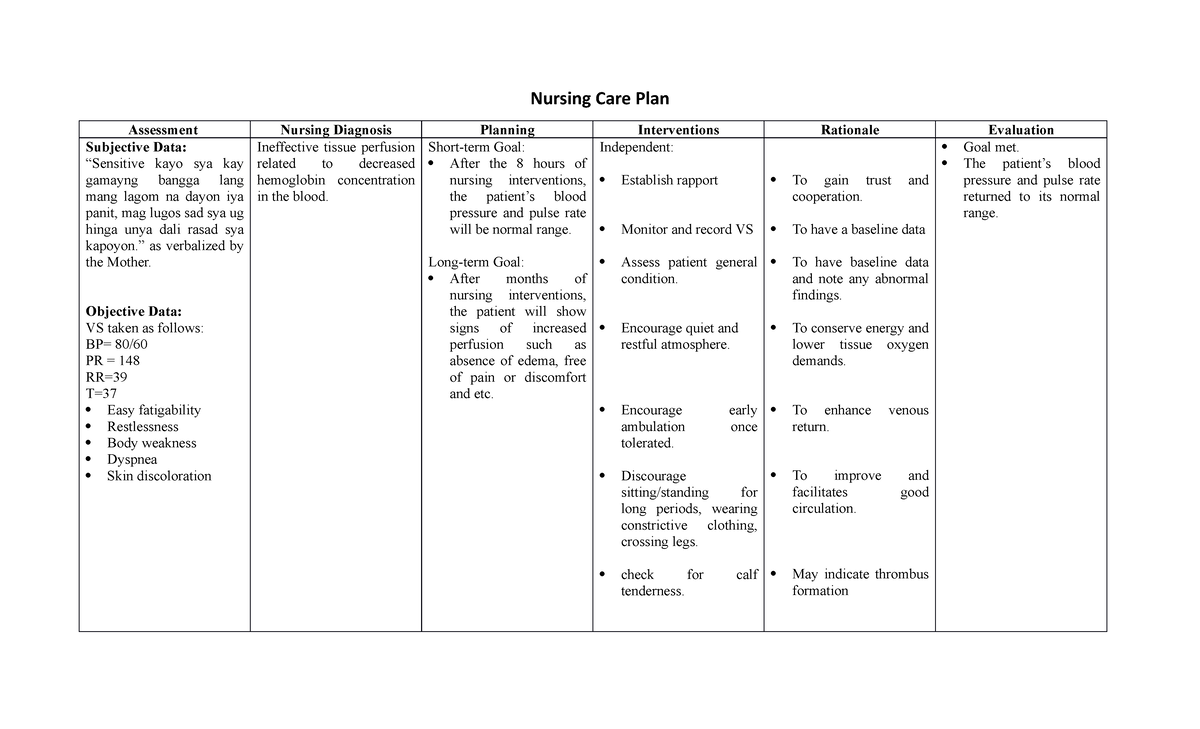
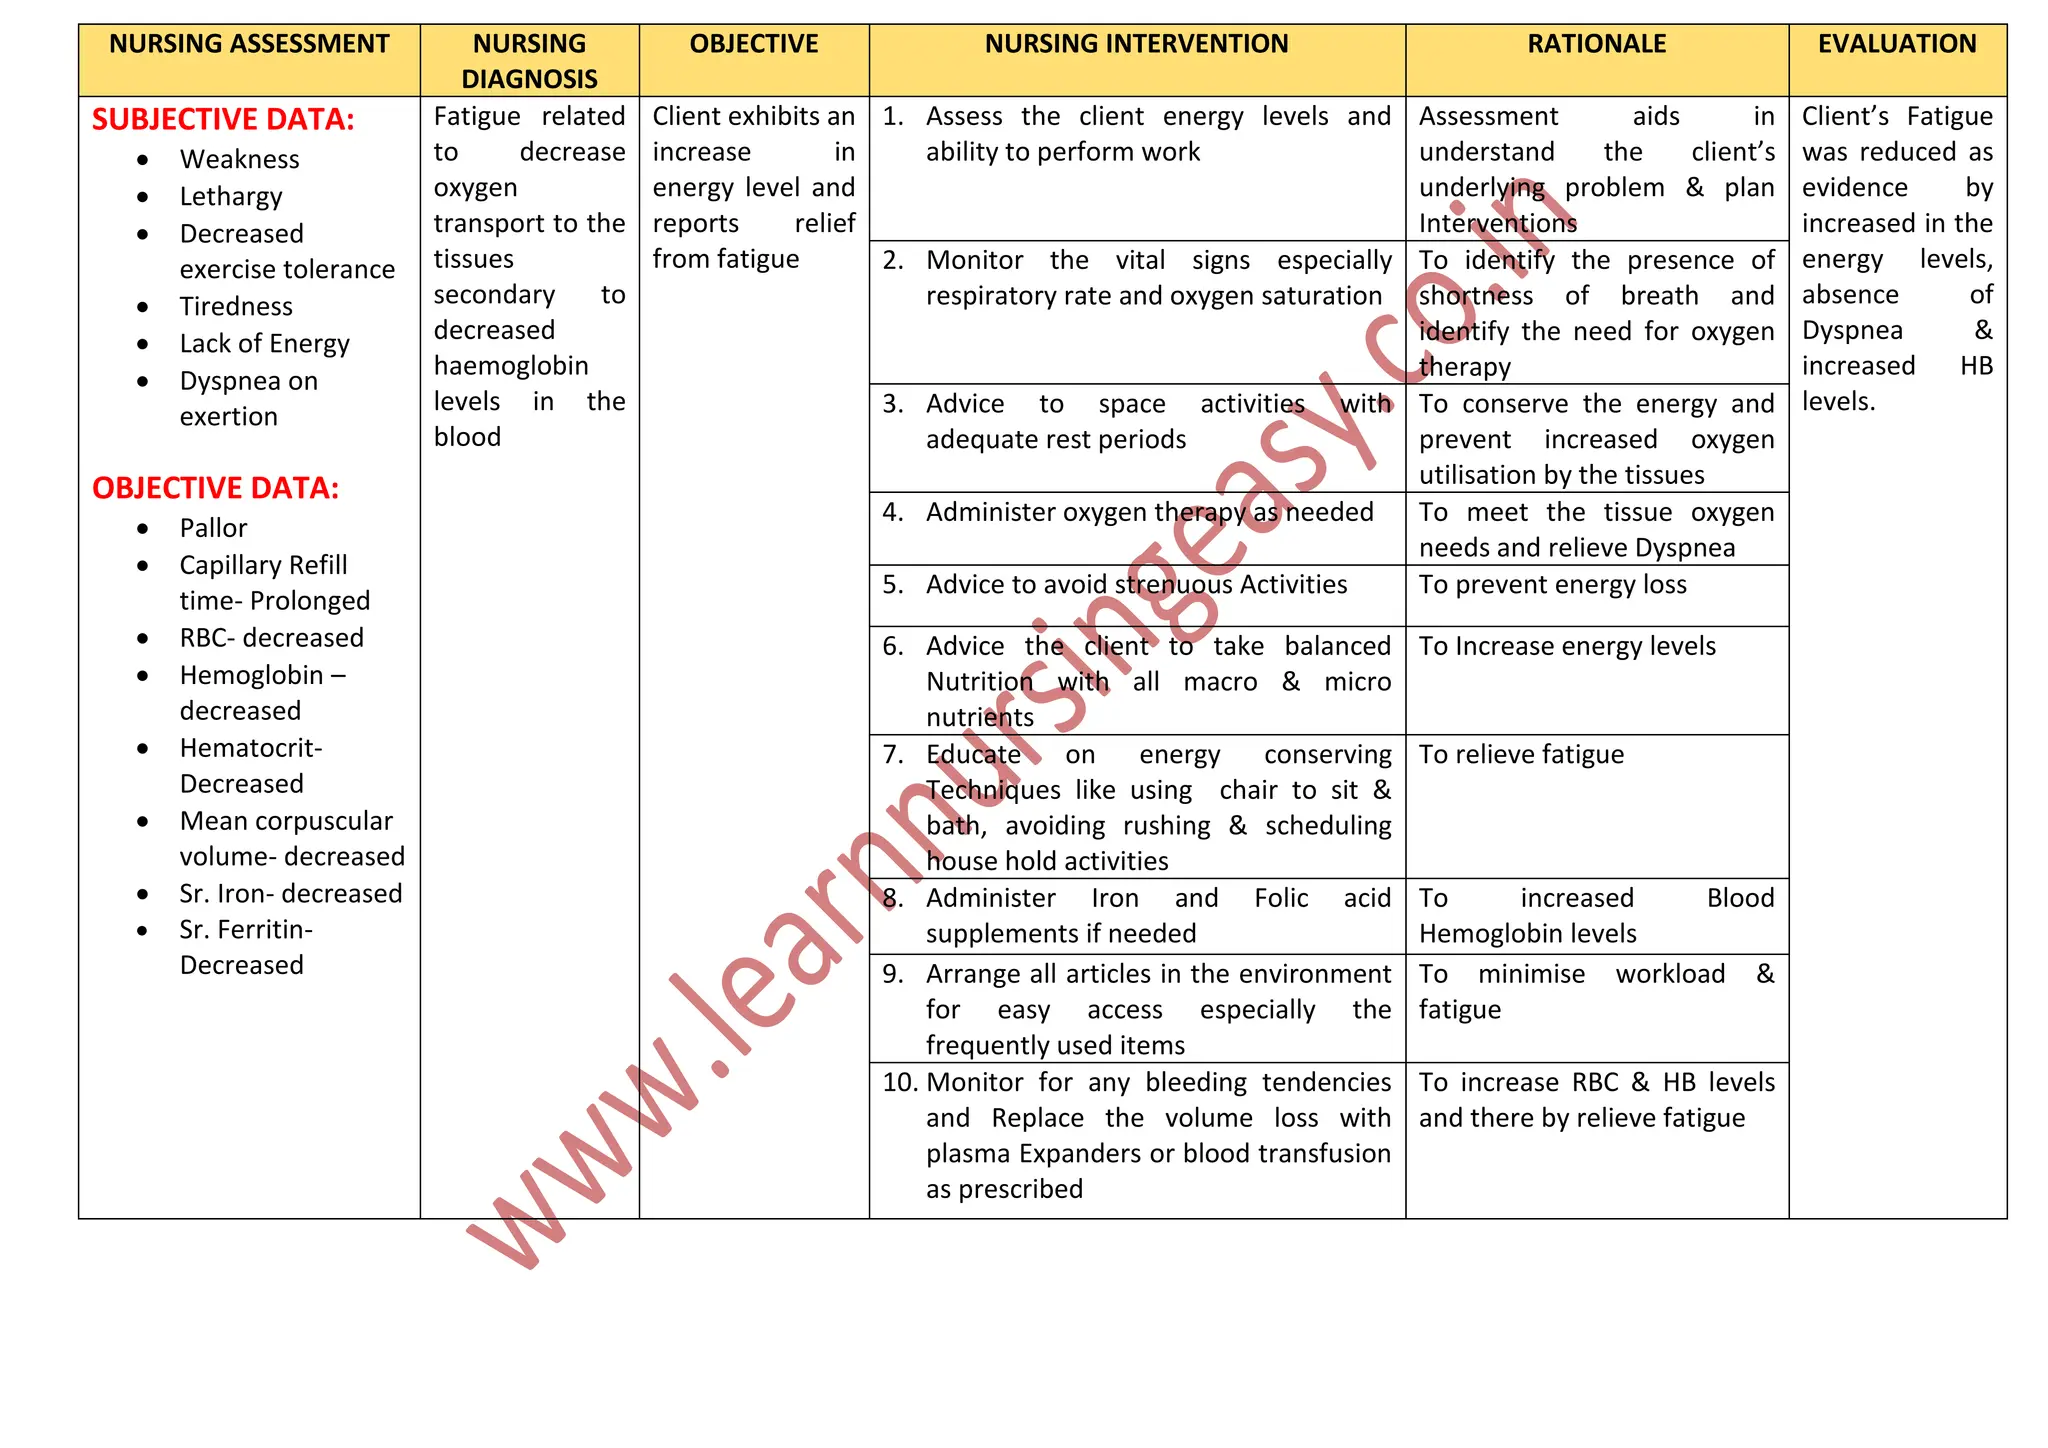
The assessment breaks down into several interconnected domains that need to be evaluated together. Starting with health history, you are looking for specific risk factors rather than generic complaints. Iron deficiency anemia presents differently depending on whether the patient is a menstruating woman, a patient with chronic GI blood loss, or someone with malabsorption issues. Each of these requires different questioning strategies.Subjective assessment elements include fatigue patterns, exercise tolerance changes, dyspnea on exertion, palpitations, headache, and pica. The pica component deserves special attention because patients rarely volunteer this information unless you ask directly. One of my patients, a 67-year-old man with refractory iron deficiency, was eating ice cubes by the handful. When I asked about it, he said he did not realize this was a symptom until I mentioned it. That question alone changed the entire trajectory of his workup. Cardiovascular assessment is where many nurses rush through too quickly. Tachycardia is an early compensatory mechanism, but so is widened pulse pressure in severe cases. I have seen patients present with heart failure symptoms that resolved completely once the anemia was corrected. The key is listening for a flow murmur over the carotid arteries and checking for orthostatic vital sign changes. A drop of more than 20 mmHg systolic or 10 mmHg diastolic upon standing suggests volume depletion compounded by anemia, which is a clinical emergency.
Objective Findings That Actually Matter
Conjunctival pallor is the classic teaching, but it has poor sensitivity, especially in patients with hemoglobin levels above 8 g/dL. Palmar crease pallor is more reliable because the thenar and hypothenar eminences show changes earlier. However, the most useful finding I have discovered is checking the nail beds under natural light versus fluorescent lighting. Fluorescent light distorts color perception in ways that make pallor harder to detect accurately.The skin assessment needs to go beyond color. Dry skin, brittle nails, and glossitis all point toward iron deficiency specifically. Koilonychia, or spoon-shaped nails, is a late sign that indicates chronic iron deficiency lasting months or even years. I encountered a 45-year-old woman with these exact nail changes who had no idea she was anemic because she attributed the fatigue to her busy schedule. Her hemoglobin was 6.8 g/dL at presentation. Respiratory assessment focuses on tachypnea and dyspnea with minimal exertion. The heart assessment should include checking for a systolic flow murmur, which is present in up to 80% of patients with hemoglobin below 8 g/dL. This murmur is typically heard best at the left upper sternal border and increases in intensity with anemia severity. Understanding this helps differentiate anemia-related cardiac findings from primary cardiac pathology.
Diagnostic Interpretation Skills
The complete blood count provides the foundation, but nursing assessment for anemia requires understanding what the indices actually tell you. Microcytic anemia with low MCV points toward iron deficiency, thalassemia, or anemia of chronic disease. The red cell distribution width helps distinguish between these conditions. A high RDW suggests iron deficiency, while a normal RDW with microcytosis points toward thalassemia trait.Mental status assessment is often overlooked but clinically significant. Cognitive slowing, difficulty concentrating, and irritability are common in severe anemia. I worked with a patient who presented with what was initially thought to be early dementia. Her folate level was critically low, and her cognitive function improved substantially after replacement therapy. This case changed how I approach neurological complaints in elderly patients. The musculoskeletal assessment should include checking for bone pain, which can indicate hemolytic anemia or marrow expansion in chronic hemolytic conditions. Patients with sickle cell disease often present with vague bone pain that is attributed to other causes. Understanding the connection between hemolysis and bone pain helps in early recognition of vaso-occlusive crises.
Get the Full Details
Common Pitfalls And How To Avoid Them
One of the most dangerous mistakes I have witnessed is attributing fatigue solely to aging or depression without checking hemoglobin levels. This is particularly problematic in postmenopausal women and elderly patients where anemia is common but frequently missed. A simple CBC takes minutes and can prevent months of misdiagnosis and inappropriate treatment.Another frequent error is focusing exclusively on hemoglobin while ignoring the patient's baseline. A hemoglobin of 10 g/dL might be well-tolerated in a young healthy woman but cause severe symptoms in an elderly patient with coronary artery disease. The clinical presentation matters more than the number on the lab report. I have seen patients with chronic anemia tolerate hemoglobin levels of 7-8 g/dL without significant symptoms, while others with acute drops to the same level require immediate transfusion. The timing of assessment is critical. Patients with chronic anemia develop compensatory mechanisms over time, including increased cardiac output and tissue extraction of oxygen. These adaptations allow them to function at near-normal levels despite significant anemia. When the anemia becomes acute, as in hemolytic crises or acute blood loss, the body has no time to adapt, and symptoms appear much more dramatically. Understanding this difference helps in prioritizing interventions.
Documentation And Communication Strategies
Effective documentation of nursing assessment for anemia requires specific, measurable findings rather than vague descriptors. Instead of writing "patient appears pale," document the specific areas assessed and findings noted. "Conjunctival pallor noted bilaterally, palmar crease pallor present, nail bed capillary refill less than 3 seconds" provides actionable information for the healthcare team.Communication with the physician should include not just the assessment findings but also the patient's functional status and symptom progression. I developed a simple scoring system that tracks fatigue levels, exercise tolerance, and symptom impact on daily activities. This system has helped identify patients who are deteriorating before they reach crisis levels. The scores are tracked over time and shared during interdisciplinary rounds. Patient education is an essential component that many nurses underemphasize. Teaching patients about the signs and symptoms of worsening anemia, when to seek medical attention, and the importance of follow-up laboratory testing can prevent emergency department visits and hospitalizations. I create simple written materials that patients can reference at home, and I schedule follow-up calls to reinforce the teaching and assess understanding.
Special Populations And Considerations
Pregnant patients require special attention because physiological changes during pregnancy can mask or mimic anemia symptoms. The expected hemoglobin drop during pregnancy is approximately 1 g/dL in the second trimester and 1-2 g/dL in the third trimester. However, symptomatic anemia during pregnancy requires prompt evaluation and treatment to prevent maternal and fetal complications.Elderly patients often present atypically, with confusion, falls, or urinary incontinence as the primary symptoms rather than classic fatigue and pallor. I have treated multiple elderly patients who were admitted for behavioral changes or falls, only to discover severe anemia as the underlying cause. This pattern has changed how I approach geriatric assessments and prompted our facility to implement routine hemoglobin screening in patients over 65 presenting with nonspecific complaints. Critical care patients present unique challenges because the stress of acute illness can unmask previously compensated anemia. Patients with chronic kidney disease on hemodialysis often have well-tolerated anemia due to adaptive mechanisms, but acute blood loss during procedures or surgery can cause rapid decompensation. Understanding the baseline hemoglobin and hematocrit values for individual patients is essential in these settings.
Tools And Resources
Several validated assessment tools can help standardize the evaluation process. The Anemia Symptom Scale, which rates fatigue, dyspnea, palpitations, and dizziness on a numeric scale, provides a quantitative measure of symptom severity. I use this tool in my practice and have found it helpful in tracking patient progress over time and communicating with the healthcare team.Electronic health record templates can streamline documentation but should not replace thorough assessment. I have seen nurses rely too heavily on dropdown menus and checkboxes, missing subtle findings that require detailed description. The template should guide the assessment, not replace clinical judgment and observation skills. Continuing education resources on hematology assessment are available through professional nursing organizations and hospital-based training programs. I recommend seeking out workshops on head-to-toe assessment techniques and hematology-specific training whenever possible. These opportunities help refresh skills and learn new approaches from experienced practitioners.
LIMITATIONS OF THIS APPROACH
It is important to acknowledge that nursing assessment for anemia has inherent limitations. Visual inspection cannot replace laboratory confirmation, and clinical findings may be absent in mild anemia or early stages of the disease. The assessment is most useful when combined with diagnostic testing and serves as a screening and monitoring tool rather than a definitive diagnostic method.Additionally, cultural and ethnic variations in skin and mucous membrane color can affect the reliability of visual assessment. Patients with darker skin tones may not exhibit classic pallor until anemia is severe. In these cases, focusing on mucous membrane color, conjunctival assessment, and symptom evaluation is more appropriate than relying solely on skin inspection. The time required for comprehensive assessment can be challenging in busy clinical settings. A thorough anemia assessment may take 15-20 minutes, which is difficult to accommodate during short appointment times or high patient loads. Prioritizing assessment components based on clinical urgency and patient risk factors can help balance thoroughness with efficiency. When laboratory confirmation is not immediately available, consider alternative approaches such as bedside hemoglobin testing or point-of-care testing. These methods can provide rapid results to guide initial management decisions while awaiting formal laboratory confirmation. However, they should be interpreted with an understanding of their accuracy limitations and used in conjunction with clinical assessment rather than as standalone diagnostic tools.



