Getting the Assessment Right When It Matters
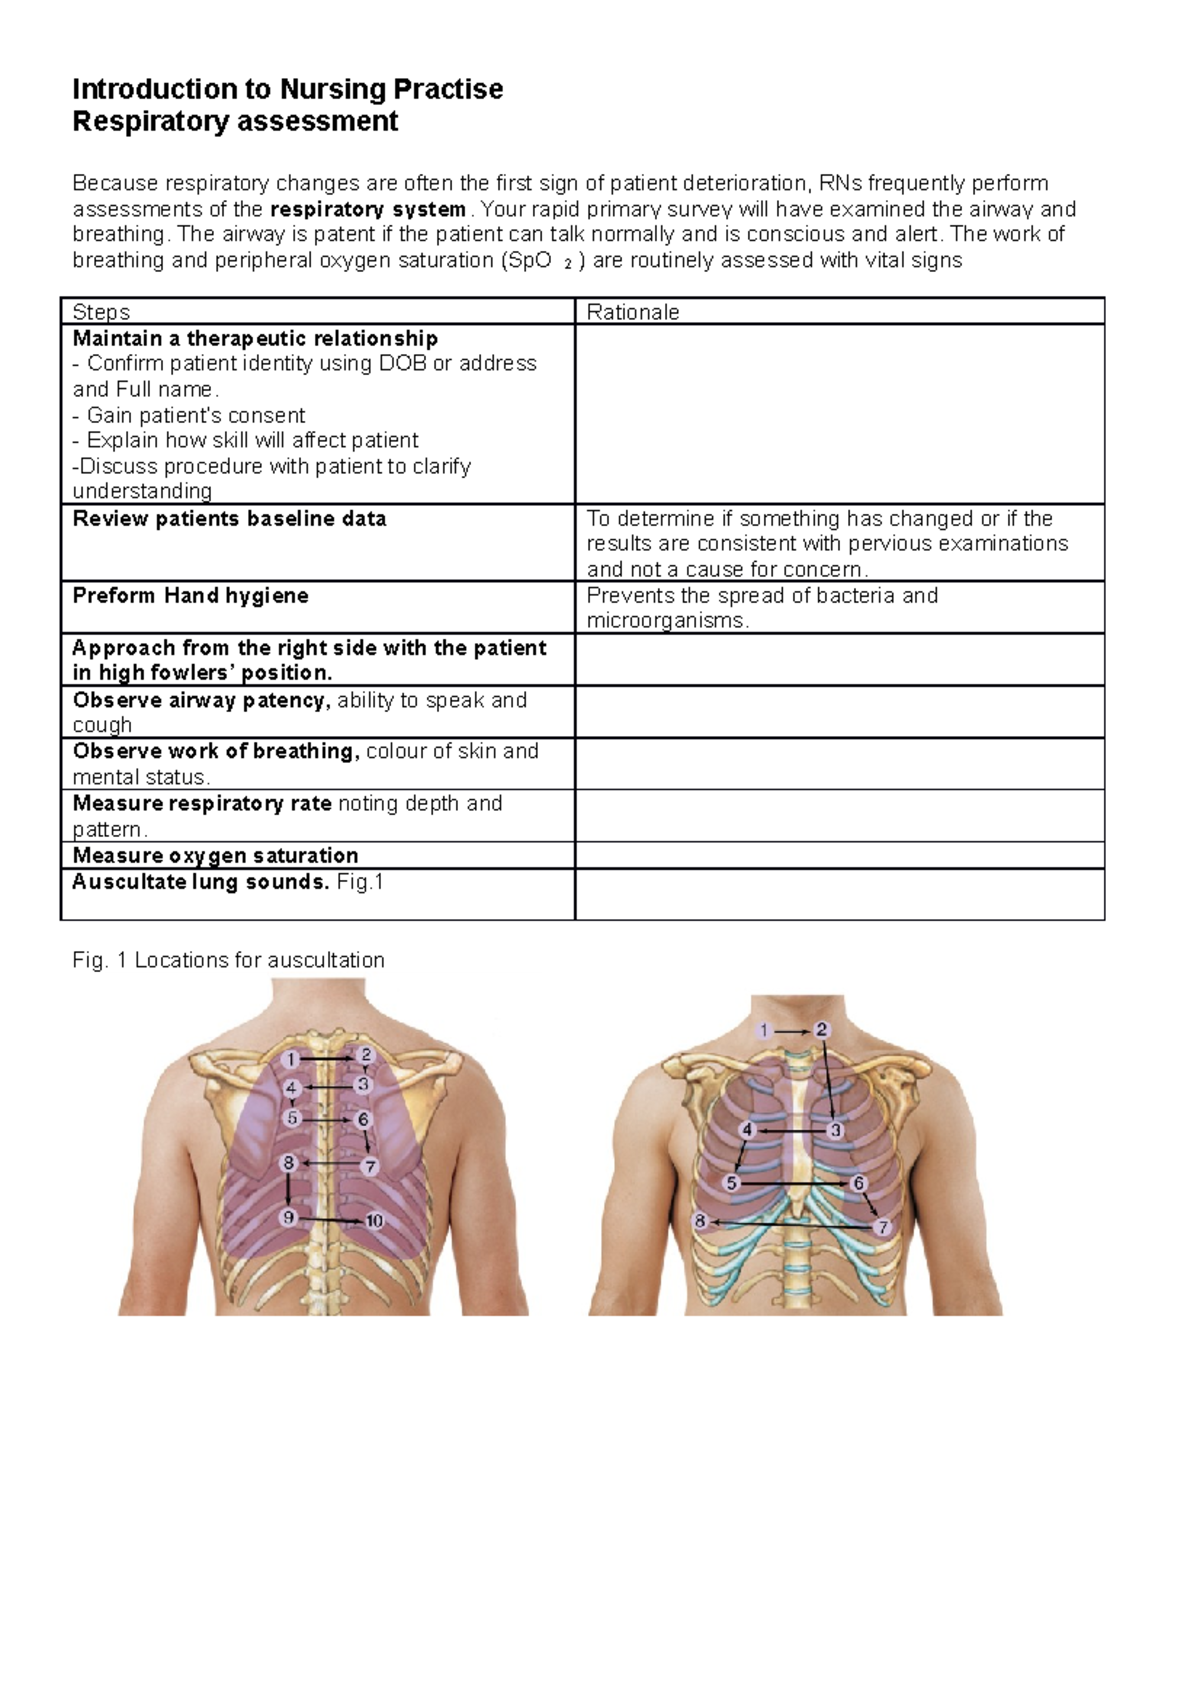
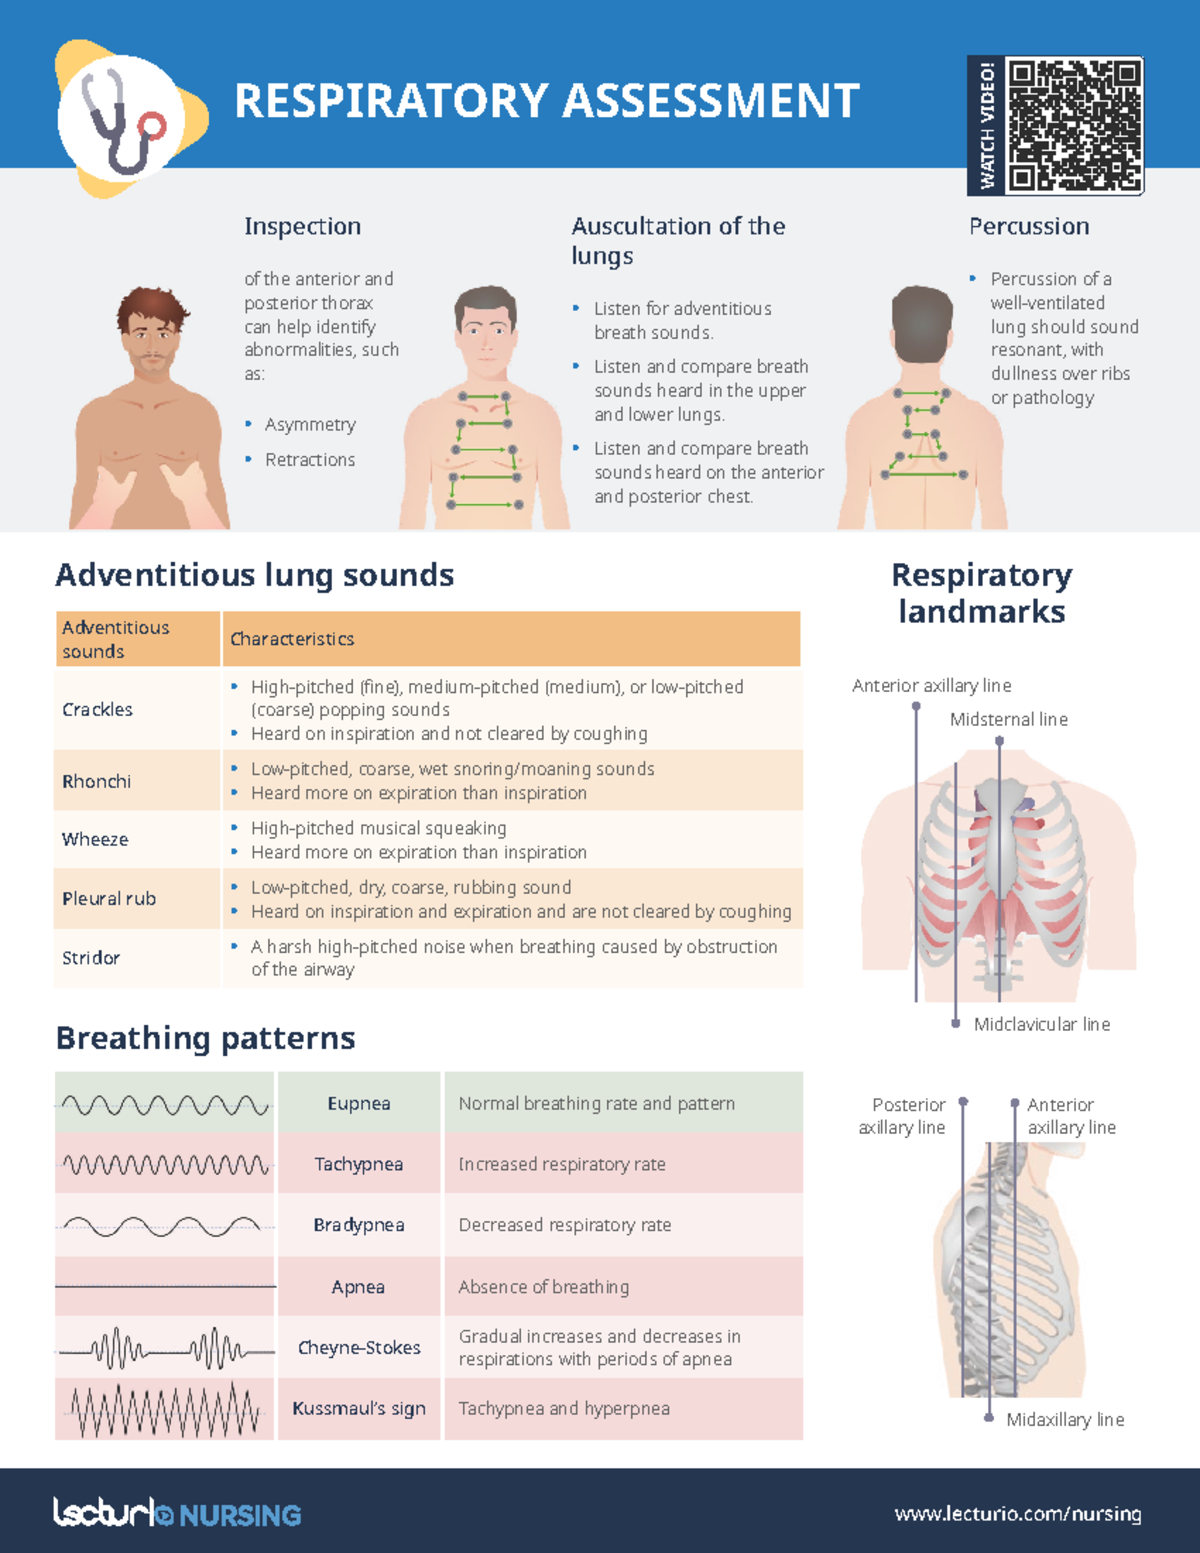
A respiratory assessment is one of those things that sounds straightforward on paper but falls apart the moment you're dealing with a real patient who's barely able to talk. I've walked into rooms where the chart said stable and the person couldn't finish a sentence without pausing for air. The difference between a textbook answer and what actually happens comes down to practice and knowing where to look. Start with inspection before you touch anything. Look at the patient from across the room. Are they using accessory muscles? Is there intercostal retractions? That tells you more than anything you'll hear in the first five minutes of listening. I once assessed a COPD patient whose SpO2 was holding at 91% and his lungs sounded barely audible on auscultation. He looked completely fine sitting in the chair. Then he stood up to go to the bathroom and immediately went into distress. The issue was orthopnea he wasn't telling me about. Now I always ask patients to describe their positioning before I start the hands-on part. Auscultation is where most people rush. You need at least ten seconds per lung field to catch anything meaningful. Listen to the full cycle, not just the inspiratory phase. Crackles versus wheezes are easier to distinguish when you're giving each one proper time. I recommend starting at the apices and working down systematically, comparing left to right at every level. That's how you spot the subtle unilateral findings that get missed when you're skimming.
Percussion isn't emphasized nearly enough in nursing programs but it has real value. Dullness over the lower lobes pointed me toward a pneumonia that auscultation alone was going to miss because the sounds were so muffled by body habitus. You don't need to be perfect at it. A quick comparison of symmetrical areas is usually enough to flag something worth investigating further. Respiratory rate remains the most underestimated vital sign. A lot of clinicians calculate it while checking pulse or blood pressure without the patient knowing. Patients will often temporarily normalize their breathing when they realize they're being watched. That's why counting for a full minute or at least thirty seconds matters. I've caught tachypnea that was being missed because nurses were grouping it with pulse checks and only counting for fifteen seconds during a window where the patient happened to be between breaths. Pulse oximetry deserves a realistic conversation. It reads fine in healthy lungs and decent perfusion. It becomes unreliable with poor peripheral perfusion, dark nail polish, movement artifact, and certain hemoglobin variants. A patient can have an SpO2 of 96% and still be significantly hypercapnic. That's especially relevant with COPD patients who live at lower saturation targets. Don't let the number give you false comfort. Look at the patient, not the monitor.
I ran into a situation a few years back with a post-operative patient who had clear breath sounds bilaterally, a respiratory rate of 18, and an SpO2 of 94% on room air. Everything looked acceptable on the surface. But she had mild confusion and was breathing through her mouth with visible nasal flaring. Her chest X-ray showed a small pneumothorax that was completely silent on auscultation because it was anterior and high. The workaround I use now is to always correlate findings against the clinical picture rather than treating each parameter in isolation. If something feels off even when the numbers are fine, you investigate further instead of writing it off.
Get the Full Details

Putting It All Together
The sequence I follow is inspection, palpation for fremitus and tactile vibration, percussion, then auscultation. Document exactly where you heard abnormal findings with anatomical specificity. Upper lobe versus lower lobe changes mean different things clinically. Lateritic basilar crackles are common in older adults and don't always indicate pathology, but you still need to note them and track whether they're new or baseline. Subjective data matters just as much. Ask about dyspnea on exertion, orthopnea, paroxysmal nocturnal dyspnea, chronic cough, and sputum characteristics. A patient who says they need three pillows to sleep is giving you information that might not show up on any monitor until things get worse. Capnography is becoming more available at the nursing level and it fills a gap that pulse oximetry doesn't address. If your facility has waveform capnography, use it alongside SpO2 for patients who are at risk for hypoventilation. The combination catches deterioration earlier than either number alone.
There are limitations to this approach. A thorough respiratory assessment takes time and most nursing shifts don't have much of it. You'll develop shortcuts over the years and some of them are reasonable, like relying more heavily on inspection when you're short-staffed and the patient is stable. But shortcuts become dangerous when the patient isn't stable. The assessment isn't a checkbox exercise. It's the foundation for every clinical decision that follows. When you're learning this skill, practice on healthy lungs first so you know what normal sounds like. You can't recognize abnormal if you haven't built a reliable mental catalog of normal variation. Different body types produce different baseline sounds. A thin young adult will have bronchial sounds over the manubrium that would be unusual in someone with a larger chest wall. Context matters more than rigid rules. Documentation should include your findings clearly enough that another clinician could understand the patient's status without having been there. Vague notes like lungs clear to auscultation aren't useful when the next nurse needs to know whether something changed. Specify areas, sounds, and whether they're new compared to previous assessments.