How to actually build a usable nursing care plan for diabetes mellitus
Most students and junior nurses copy-paste templates that look correct on paper but fall apart the moment they try to implement them. I have spent years watching this happen in clinical rotations and hospital units. A nursing care plan needs to reflect what actually happens with a diabetic patient, not what a textbook says should happen. Let me walk you through how to construct one that holds up under real conditions.
What a Nursing Care Plan Diabetes Mellitus Actually Needs
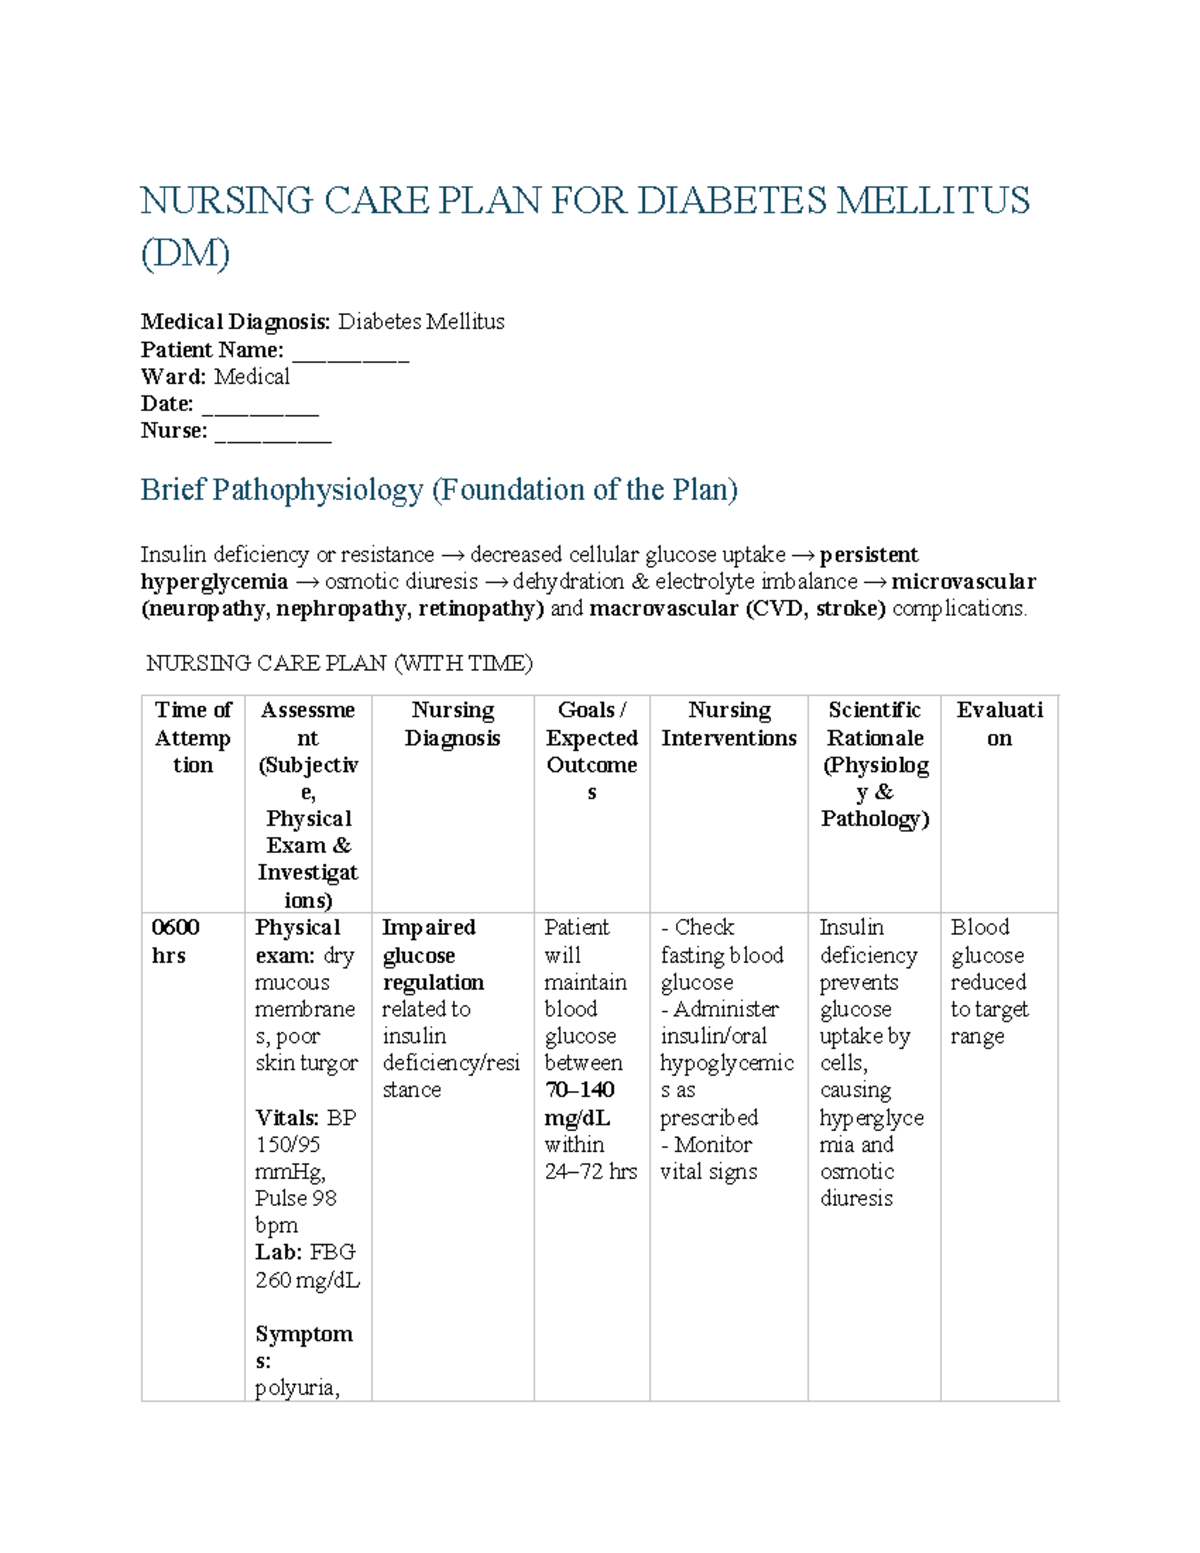
Start by understanding the problem set. Diabetes mellitus is not a single condition you treat with one approach. Type 1 is autoimmune destruction of beta cells requiring exogenous insulin. Type 2 involves insulin resistance paired with relative deficiency, managed through multiple pharmacological and lifestyle interventions. Gestational diabetes adds pregnancy-specific monitoring parameters. A plan that treats all three the same is wrong from the start. The structure I use has four components: assessment data, nursing diagnosis, measurable outcomes, and interventions with rationales. That is standard. What most people miss is the sequencing and specificity inside each section. Take assessment data. The bare minimum is a blood glucose reading, medication list, and dietary history. That gets you a passing grade in school. On a real unit, you need the trend data. When did the hypoglycemic episode occur? Was it before lunch or after evening insulin? What was the carbohydrate count at that meal? Without the temporal and contextual layer, your plan is guessing.
The diagnostic statements that actually work
Standard NANDA diagnoses like Imbalanced Nutrition: Less Than Body Requirements or Risk for Unstable Blood Glucose are fine as headers, but they are empty without the related factors and defining characteristics properly linked. Here is what I mean. If your patient has Type 2 diabetes and presents with recurrent postprandial hyperglycemia, the diagnosis should read something like: Imbalanced nutrition: less than body requirements related to inadequate dietary management as evidenced by consistent post-meal glucose readings above 200 mg/dL over the past 72 hours. The related factor and evidence are tied together. The plan that follows from that statement is specific enough to act on. A vague diagnosis like Risk for unstable blood glucose related to diabetes produces vague interventions. Everyone writes "monitor blood glucose" regardless. That intervention costs nothing and proves nothing.
Get the Full Details

Interventions that survive contact with reality
The intervention section is where most plans collapse. Here is how to keep them functional. Medication management goes beyond "administer insulin as prescribed." Document the insulin type, onset, peak, and duration. Match the timing to the patient's meal schedule. If you are writing a plan for a patient on sliding scale Regular insulin with NPH coverage, note that Regular peaks in two to four hours and NPH peaks in four to eight hours. The intervention becomes actionable when you specify monitoring windows that align with those peaks rather than just stating a generic check every four hours. Dietary planning requires more than "refer to dietitian." Specify the carbohydrate counting approach, the target grams per meal, and how the patient will self-monitor after eating. For a patient with a known preference for high-carbohydrate Asian cuisine, the plan should acknowledge that barrier and include a culturally specific substitution list. Generic dietary advice fails because it ignores what the patient actually eats.
Foot care education is another area where plans go wrong. Writing "teach foot care" is insufficient. The intervention should specify inspection frequency, proper footwear requirements, and signs of neuropathy that require immediate provider notification. Diabetic peripheral neuropathy affects approximately 50 percent of long-term patients. The plan needs to address early detection, not just prevention. I had a patient once where the standard care plan called for monitoring blood glucose four times daily. The patient was working night shifts. The monitoring times conflicted with sleep schedules and the data collected was essentially random with respect to meals and medication peaks. I rewrote the plan to tie glucose checks to actual insulin administration windows and meal times relative to the patient's work schedule. The pattern of hyperglycemia and hypoglycemia became visible within two days. The original plan would have taken a week to produce the same visibility, if it ever did.
Outcome criteria that are actually measurable
Poor outcome statements look like: Patient will maintain blood glucose within normal limits. Normal limits is a range spanning from 70 to 140 mg/dL depending on the source. That is not measurable in any useful way. Specific outcomes look like: Patient will maintain fasting blood glucose between 80 and 130 mg/dL and postprandial readings below 180 mg/dL for 5 out of 7 days before discharge. This gives you a concrete benchmark. You can track it daily. You can adjust interventions based on whether the patient meets the threshold or misses it. Another measurable outcome often missed: patient will demonstrate correct insulin injection technique with zero errors during return demonstration before discharge. Not "will understand" or "will be educated about." Will demonstrate correctly. The difference matters because understanding and doing are separate skills and patients routinely fail the second one.

Pitfalls I have seen repeatedly
The first pitfall is over-assuming patient literacy. Care plans frequently include interventions like "patient will adhere to complex insulin adjustment protocol" without accounting for health literacy levels. A patient who cannot read a syringe marking or understand the concept of insulin-to-carbohydrate ratio will not follow a protocol designed for someone who can. Assess baseline understanding before writing interventions that assume it exists. The second pitfall is ignoring comorbidities. A diabetic patient with chronic kidney disease requires different dosing intervals for certain medications and different dietary phosphorus restrictions. A diabetic patient with heart failure needs sodium restriction layered on top of carbohydrate management. The care plan must address the intersection of conditions, not just diabetes in isolation. The third and most damaging pitfall is writing the plan after the fact. Some nurses fill out care plans retrospectively at the end of a shift or before discharge. By then, the actual clinical decisions have already been made without documentation. The plan becomes a fictional narrative rather than a living guide. Write it when the assessment happens. Update it when the patient's status changes. Treat it as a working document, not an administrative checkbox.
A note on limitations
No care plan covers every scenario. Diabetic ketoacidosis presentations can shift rapidly from stable to critical within hours. A plan written for a routine admission may be entirely inadequate when the patient presents with an acute complication. Sickle cell trait combined with diabetes requires different fluid management strategies. Pregnancy with pre-existing diabetes changes every parameter in the plan. If your plan is static, it will fail when the patient's condition changes. Build in revision points. Reassess the plan every 24 to 48 hours during acute phases and weekly during stabilization. The framework should accommodate change without requiring a complete rewrite. I also want to be straightforward about the tools. Many electronic health record systems have built-in care plan templates that auto-populate common diagnoses and interventions. These save time but tend to produce generic output. The template will suggest "monitor blood glucose" for every diabetic patient regardless of context. Use the template as a starting point, not a final product. Spend the extra ten minutes customizing the relevant factors and measurable outcomes. That customization is what separates a plan that guides care from one that satisfies compliance requirements.