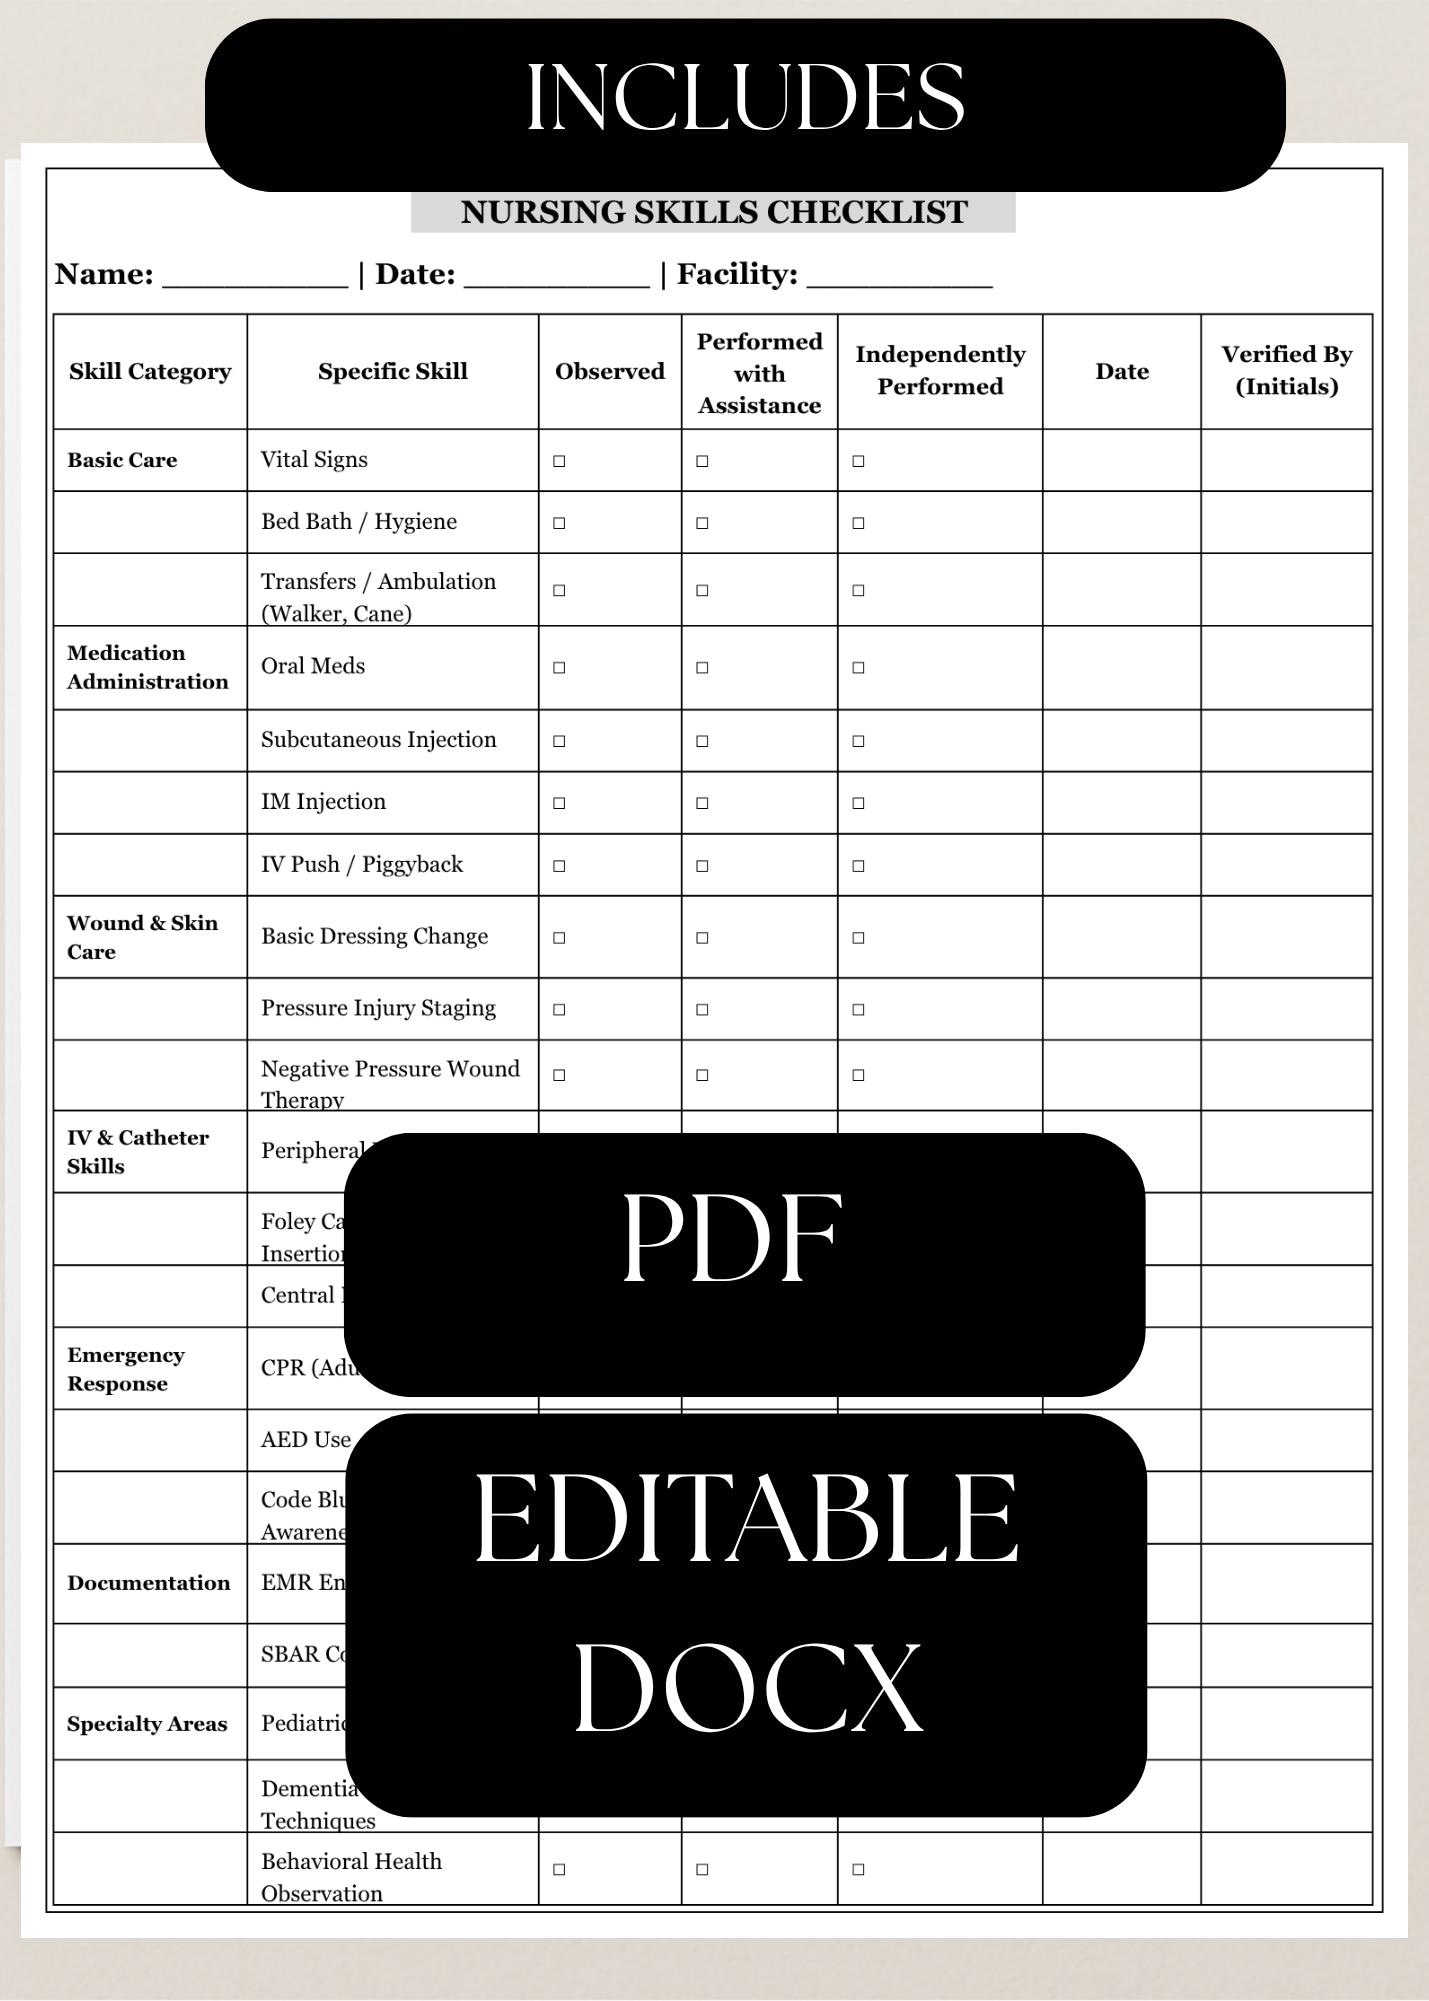
Why Most Nursing Checklists Fail Before They Leave the Printer
I spent roughly four years working shift nursing before moving into clinical operations and documentation compliance. The checklist concept sounds simple on paper. You write down steps, nurses follow them, everything gets tracked. In practice, it falls apart because nobody asks the people actually doing the work what they need. A comprehensive nursing checklist isn't just a longer to-do list. It's a documented safety net that covers assessment, intervention, communication, and documentation across different care settings. The word comprehensive means it should address the full patient encounter from admission through discharge planning, not just the med pass portion. I see a lot of facilities treat them like compliance checkboxes and wonder why nurse turnover on checklist adherence is so high.
Nursing Checklist Comprehensive: What It Actually Looks Like in Practice
Here's the structure that works without burning people out. A comprehensive nursing checklist typically runs about eight to twelve sections depending on the unit. Start with patient identification and allergy verification, then move through current condition baseline, active treatment review, fall and pressure injury risk scores, pain assessment with current management, skin integrity check, fluid balance monitoring, and discharge planning readiness. That's the skeleton. The actual content changes based on whether you're on med-surg, ICU, pediatrics, or a mental health floor. I built and maintained these checklists for about eighteen months across two hospital systems. The first version we rolled out was thirty-seven items long. Nurses completed maybe forty percent of them accurately because the rest required clicking through three different screens. We cut it to eleven items with clear yes-or-no responses and documentation shortcuts. Completion rates went from forty percent to about eighty-nine percent within six weeks. That's not a small difference. That's the entire program either working or dying. The sections you include depend heavily on your population. A comprehensive checklist for a post-operative surgical unit looks very different from one designed for a geriatric long-term care floor. Don't copy a template from a different setting and expect it to function. I've seen units adopt trauma bay checklists for general med-surg floors and then wonder why nurses started skipping the entire form. The disconnect between the tool and the actual workflow is the most common failure point I've encountered.
How to Build One That People Will Actually Use
First, you need to map the current workflow before writing a single item. Watch nurses complete their assessments for two full shifts. Don't ask them what they think they do. Watch what they actually do. Then identify the gaps between the clinical guidelines and the real behavior. The gaps are where your checklist needs to exist. If a step isn't already happening informally, adding it to a formal checklist won't make it happen. It'll just create a blank box someone checks without thinking. Keep each item action-specific and measurable. Write "assess lung sounds bilaterally" instead of "evaluate respiratory status." The second example is vague enough that a nurse could listen to one lung field and legitimately claim they checked it. I ran into this exact problem with a respiratory checklist at my old facility. Eighty percent of the documented respiratory assessments were incomplete because the wording allowed for minimal effort. We rewrote every item with explicit parameters. Completion accuracy improved dramatically. Integrate the checklist into your existing EHR workflow rather than creating a separate document. Nurses already navigate through admission, reassessment, and discharge modules. Adding an external paper form or a second standalone screen creates cognitive load that nobody needs. The comprehensive nursing checklist should live inside whatever system your facility uses for charting. If your EHR can't support custom checklist fields, then you need to push for that upgrade or find a compatible add-on module before rolling anything out.
Get the Full Details

Common Pitfalls That Break These Systems
The biggest mistake I see is treating the checklist as a one-time project instead of a living document. Guidelines change. Drug protocols change. Facility policies get updated quarterly. If your checklist isn't reviewed and revised at least every six months, it's already behind the current standard of care. I worked with a facility where the fall risk checklist hadn't been updated since 2019. The Morse Fall Scale had been revised in 2021 with new scoring parameters. The old checklist was technically inaccurate, and the compliance audit flagged it but nobody followed through with corrections because the process felt too burdensome. Another pitfall is making the checklist punitive. When nurses know that incomplete checklists result in disciplinary action, they start gaming the system. They fill things out prematurely, they copy-paste previous assessments, and they stop documenting honest problems because the paperwork burden outweighs the clinical value. I saw this happen firsthand when one hospital tied checklist completion percentages to performance reviews without accounting for actual patient acuity. Nurses on high-acuity units completed checklists faster but documented less clinically relevant information. The numbers looked good on a spreadsheet. The patient outcomes told a different story. You also need to consider the documentation burden carefully. A comprehensive checklist that takes more than ten minutes to complete during a standard shift will face resistance regardless of how useful it theoretically is. I calculated that a typical med-surg nurse has roughly fifteen to twenty minutes of documentation time between direct patient care activities during a twelve-hour shift. If your checklist consumes more than a quarter of that window, it's competing with actual charting that matters for legal and clinical purposes. Balance is everything.
When a Comprehensive Checklist Isn't the Right Tool
Checklists work best for standardized, repeatable processes. They don't work well for complex clinical decision-making that requires nuanced judgment. A nurse evaluating a deteriorating patient in real time doesn't need a checklist. They need clinical judgment supported by early warning score systems and rapid response protocols. I've seen facilities try to force checklists into triage and emergency assessment situations where they don't belong. The result is delayed recognition because the nurse is filling boxes instead of observing the patient. If your goal is improving patient safety through systematic processes, a comprehensive nursing checklist is a solid starting point. But it's not a substitute for adequate staffing, proper training, or a culture that encourages reporting near misses without fear. I worked at a facility that implemented a forty-item comprehensive checklist while simultaneously cutting nursing ratios by fifteen percent. The checklist became another source of frustration rather than a safety improvement. The numbers on completion rates went up. Patient satisfaction scores and staff retention both went down. The tool wasn't the problem. The context was.
What to Do If Your Current System Isn't Working
Start by auditing your existing checklist against current clinical guidelines for your specific unit type. Cross-reference it with the Joint Commission standards and your state's nursing practice regulations. Identify items that are outdated, redundant, or misaligned with actual workflow. Remove the clutter. Then present the revised version to a small group of frontline nurses for a two-week trial before full rollout. Pay attention to which items they skip and why. That feedback is more valuable than any compliance metric. The comprehensive nursing checklist is only as good as the people using it and the environment they're using it in. Build it with them, revise it regularly, and measure its impact on actual patient outcomes rather than just completion percentages. That's the part most facilities get wrong.